Getting it Right the First Time
Most people who read about 12 Lead Ecg Placement online end up more confused than when they started. The diagrams look clean. The websites sell you on color-coding systems that vary between manufacturers. I have spent roughly eight years placing these on patients who range from cooperative clinic volunteers to trauma cases with limited access, and the core problem is always the same: people learn the order instead of understanding the anatomy. Here is what actually works when you need a clean tracing without spending twenty minutes repositioning electrodes.
Standard 12 Lead ECG Placement
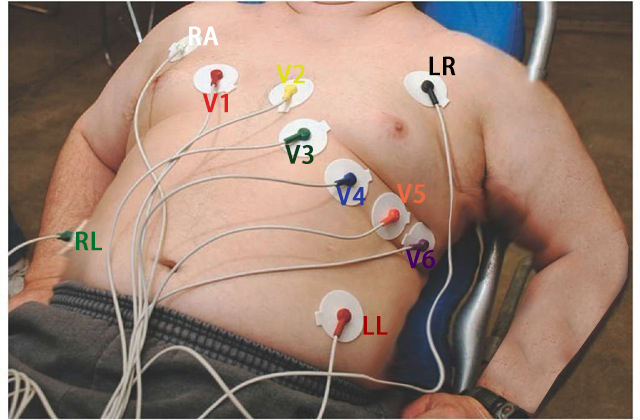
The leads break into two groups: limb leads and precordial leads. You need four limb electrodes and six chest electrodes. That is twelve total, and each one maps to a specific view of the heart. Get the positions wrong and you are not just getting a messy tracing. You are potentially missing a lateral wall infarct or misidentifying an inferior STEMI. The limb electrodes go on the extremities, not around the shoulders or ankles. I see that mistake constantly in new tech orientations. Proximity to the torso matters because that is where the electrical signal is strongest. Place them on the wrists and ankles, or as close to those joints as possible on patients with amputations or severe edema. The color coding follows the AHA standard in the United States: white on the right arm, black on the left arm, red on the left leg, and green on the right leg. The right leg is your ground. It does not record anything meaningful but it does reduce noise. If you skip it or swap it with another color, the tracing picks up more artifact and you waste time troubleshooting.
Chest Lead Positioning
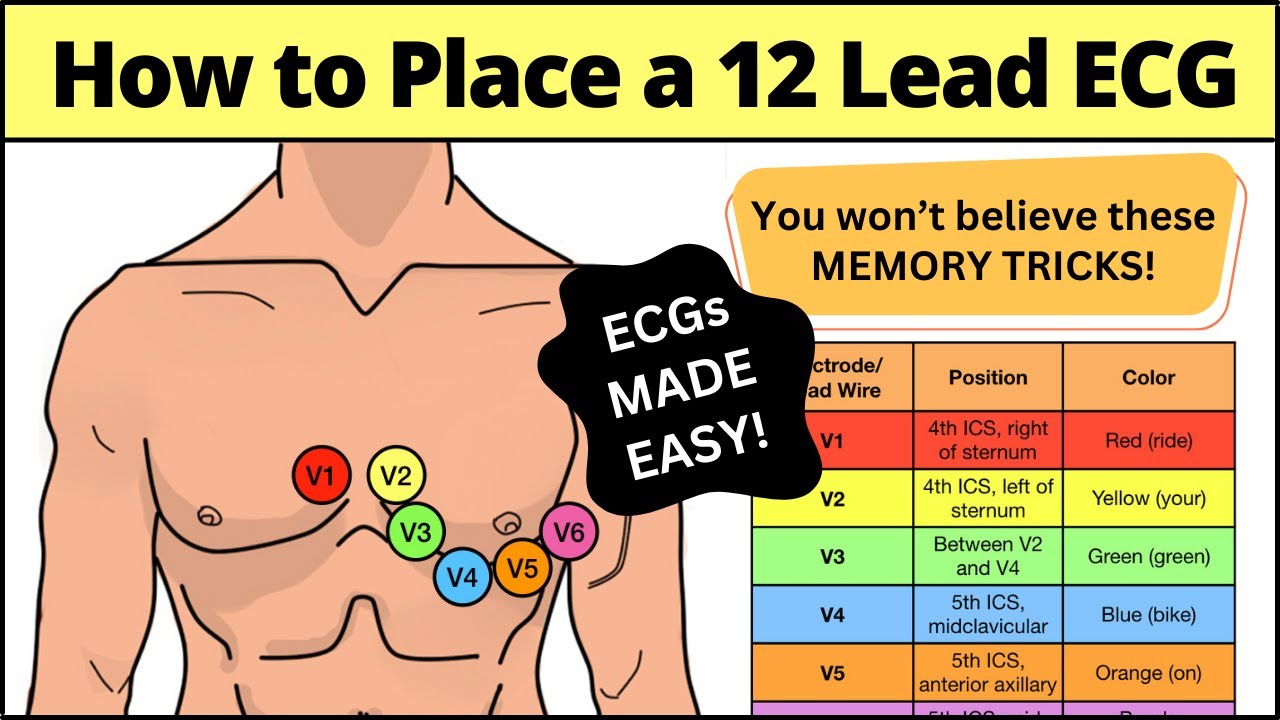
This is where most errors happen. The six precordial leads need precise anatomical landmarks, and approximating them leads to inconsistent tracings across serial ECGs. V1 sits in the fourth intercostal space at the right sternal border. V2 goes in the fourth intercostal space at the left sternal border. V4 is positioned in the fifth intercostal space at the midclavicular line. V3 falls halfway between V2 and V4. V5 aligns horizontally with V4 at the anterior axillary line. V6 sits at the same level as V4 and V5 but on the midaxillary line. Before you place any electrode, you need to find the angle of Louis. Run your finger up from the xiphoid process until you hit the second rib, then slide laterally to feel the joint where the second rib meets the sternum. That is your landmark. Count down from there to the correct intercostal space. If you start counting from the xiphoid or the nipple line, you will consistently be one space too low, especially on larger chests.
Get the Full Details

Practical Problems I Have Encountered
I once worked a shift where a patient had undergone a bilateral mastectomy with lymph node dissection. Standard placement was not possible on the right side because of surgical sites and lymphedema. The left side had intact skin but the patient was extremely emaciated, making landmark identification difficult. I ended up placing the right arm electrode on the right shoulder rather than the wrist, which gave us a usable tracing without significant artifact. The left side electrodes stayed on the extremities where possible, and for the chest leads on the left, I relied heavily on bony landmarks since breast tissue was absent. It took longer than a normal placement, roughly three to four minutes instead of the usual sixty to ninety seconds, but the resulting ECG was diagnostic. Another common issue involves patients with significant kyphosis or those who are bedbound. The chest leads shift upward when the spine is curved, so what looks like the fourth intercostal space anatomically may actually sit higher on the torso. I learned to palpate each space individually rather than estimating from the overall posture. Skipping that step resulted in misplaced V1 and V2 on three separate patients in a single week, and all three tracings showed misleading ST changes that looked like inferior ischemia until I repositioned and repeated the study.
Things Beginners Miss
Shaving chest hair is not optional when the skin is heavily haired. Electrode contact fails over hair, and you will chase artifact for minutes before realizing the issue. Use clippers, not a razor, to avoid micro-abrasions that cause patient discomfort and skin reactions. I keep a disposable clipper head in every ECG kit for this reason. Skin preparation matters more than people realize. Oils from lotions, sweat, and natural sebum create impedance. Rub the site firmly with an alcohol pad or gauze until the skin looks slightly pink. This usually reduces impedance by several kilo-ohms and eliminates baseline wander in most cases. Inter-electrode distance affects signal quality. When limb electrodes are placed too far apart on patients with large body habitus, the electrical signal weakens and you get low voltage QRS complexes. This can mimic conditions like pericardial effusion or hypothyroidism when the problem is purely technical. Repositioning closer to the torso often resolves this without changing anything else about the study.
Limitations and When This Approach Fails
Standard 12 lead ECG placement has real constraints. It does not provide posterior or right ventricular views. If you suspect a posterior MI based on the standard tracing showing tall R waves in V1 and V2 with ST depression, you need additional leads. Place V7 through V9 horizontally at the same level as V6 along the left posterior axillary to spine line. For right ventricular involvement, add V4R on the right side at the same position as V4. This takes roughly thirty additional seconds and changes the diagnostic yield significantly in the right clinical context. The technique also breaks down in patients with severe obesity, where intercostal spaces are difficult to palpate and chest wall thickness attenuates signal amplitude. In those cases, increasing gain on the machine and using larger adult electrodes helps, but you may still need to accept a lower quality tracing or consider alternative monitoring like telemetry with frequent repositioning checks. Another limitation involves pacemaker and ICD patients. The device generator and leads create artifact that can obscure intrinsic activity. Placement itself is unchanged, but interpretation requires different considerations. Do not place chest electrodes directly over the device pocket or along the lead trajectory if you can avoid it, as this creates additional noise.

Quick Reference for Placement Order
I place the limbs first because they establish the baseline for the entire study. Right arm, left arm, right leg, left leg. Then the chest leads in this sequence: V1, V2, V4, V3, V6, V5. Placing V4 before V3 prevents you from having to reach across an already-placed electrode, and putting V5 last rather than in sequence keeps your hand from brushing over fresh adhesive sites. Total time for an uncomplicated placement is about two minutes. Complicated cases with shaving, extensive skin prep, or anatomical variations run five to eight minutes. Anything beyond that usually means you are searching for landmarks rather than using them.
Documentation Notes
Always document if placement deviated from standard positions. I note right arm electrode placement on the shoulder or any cephalad caudad shifts caused by body habitus. This information proves critical when comparing serial ECGs because a change in lead position can mimic clinical change. A tracing that appears to show new anterior ST elevation may simply reflect a chest lead placed one intercostal space too low on repeat study. Quality control is straightforward: check that all twelve electrodes are adhered, the cables are secured to prevent tug artifact, and the tracing displays clean baseline without interference before releasing the patient. A bad placement costs more time than doing it correctly the first time, even accounting for the extra twenty seconds of landmark palpation and skin prep.