A Practical Look at 177 Lu-PSMA-617 Therapy
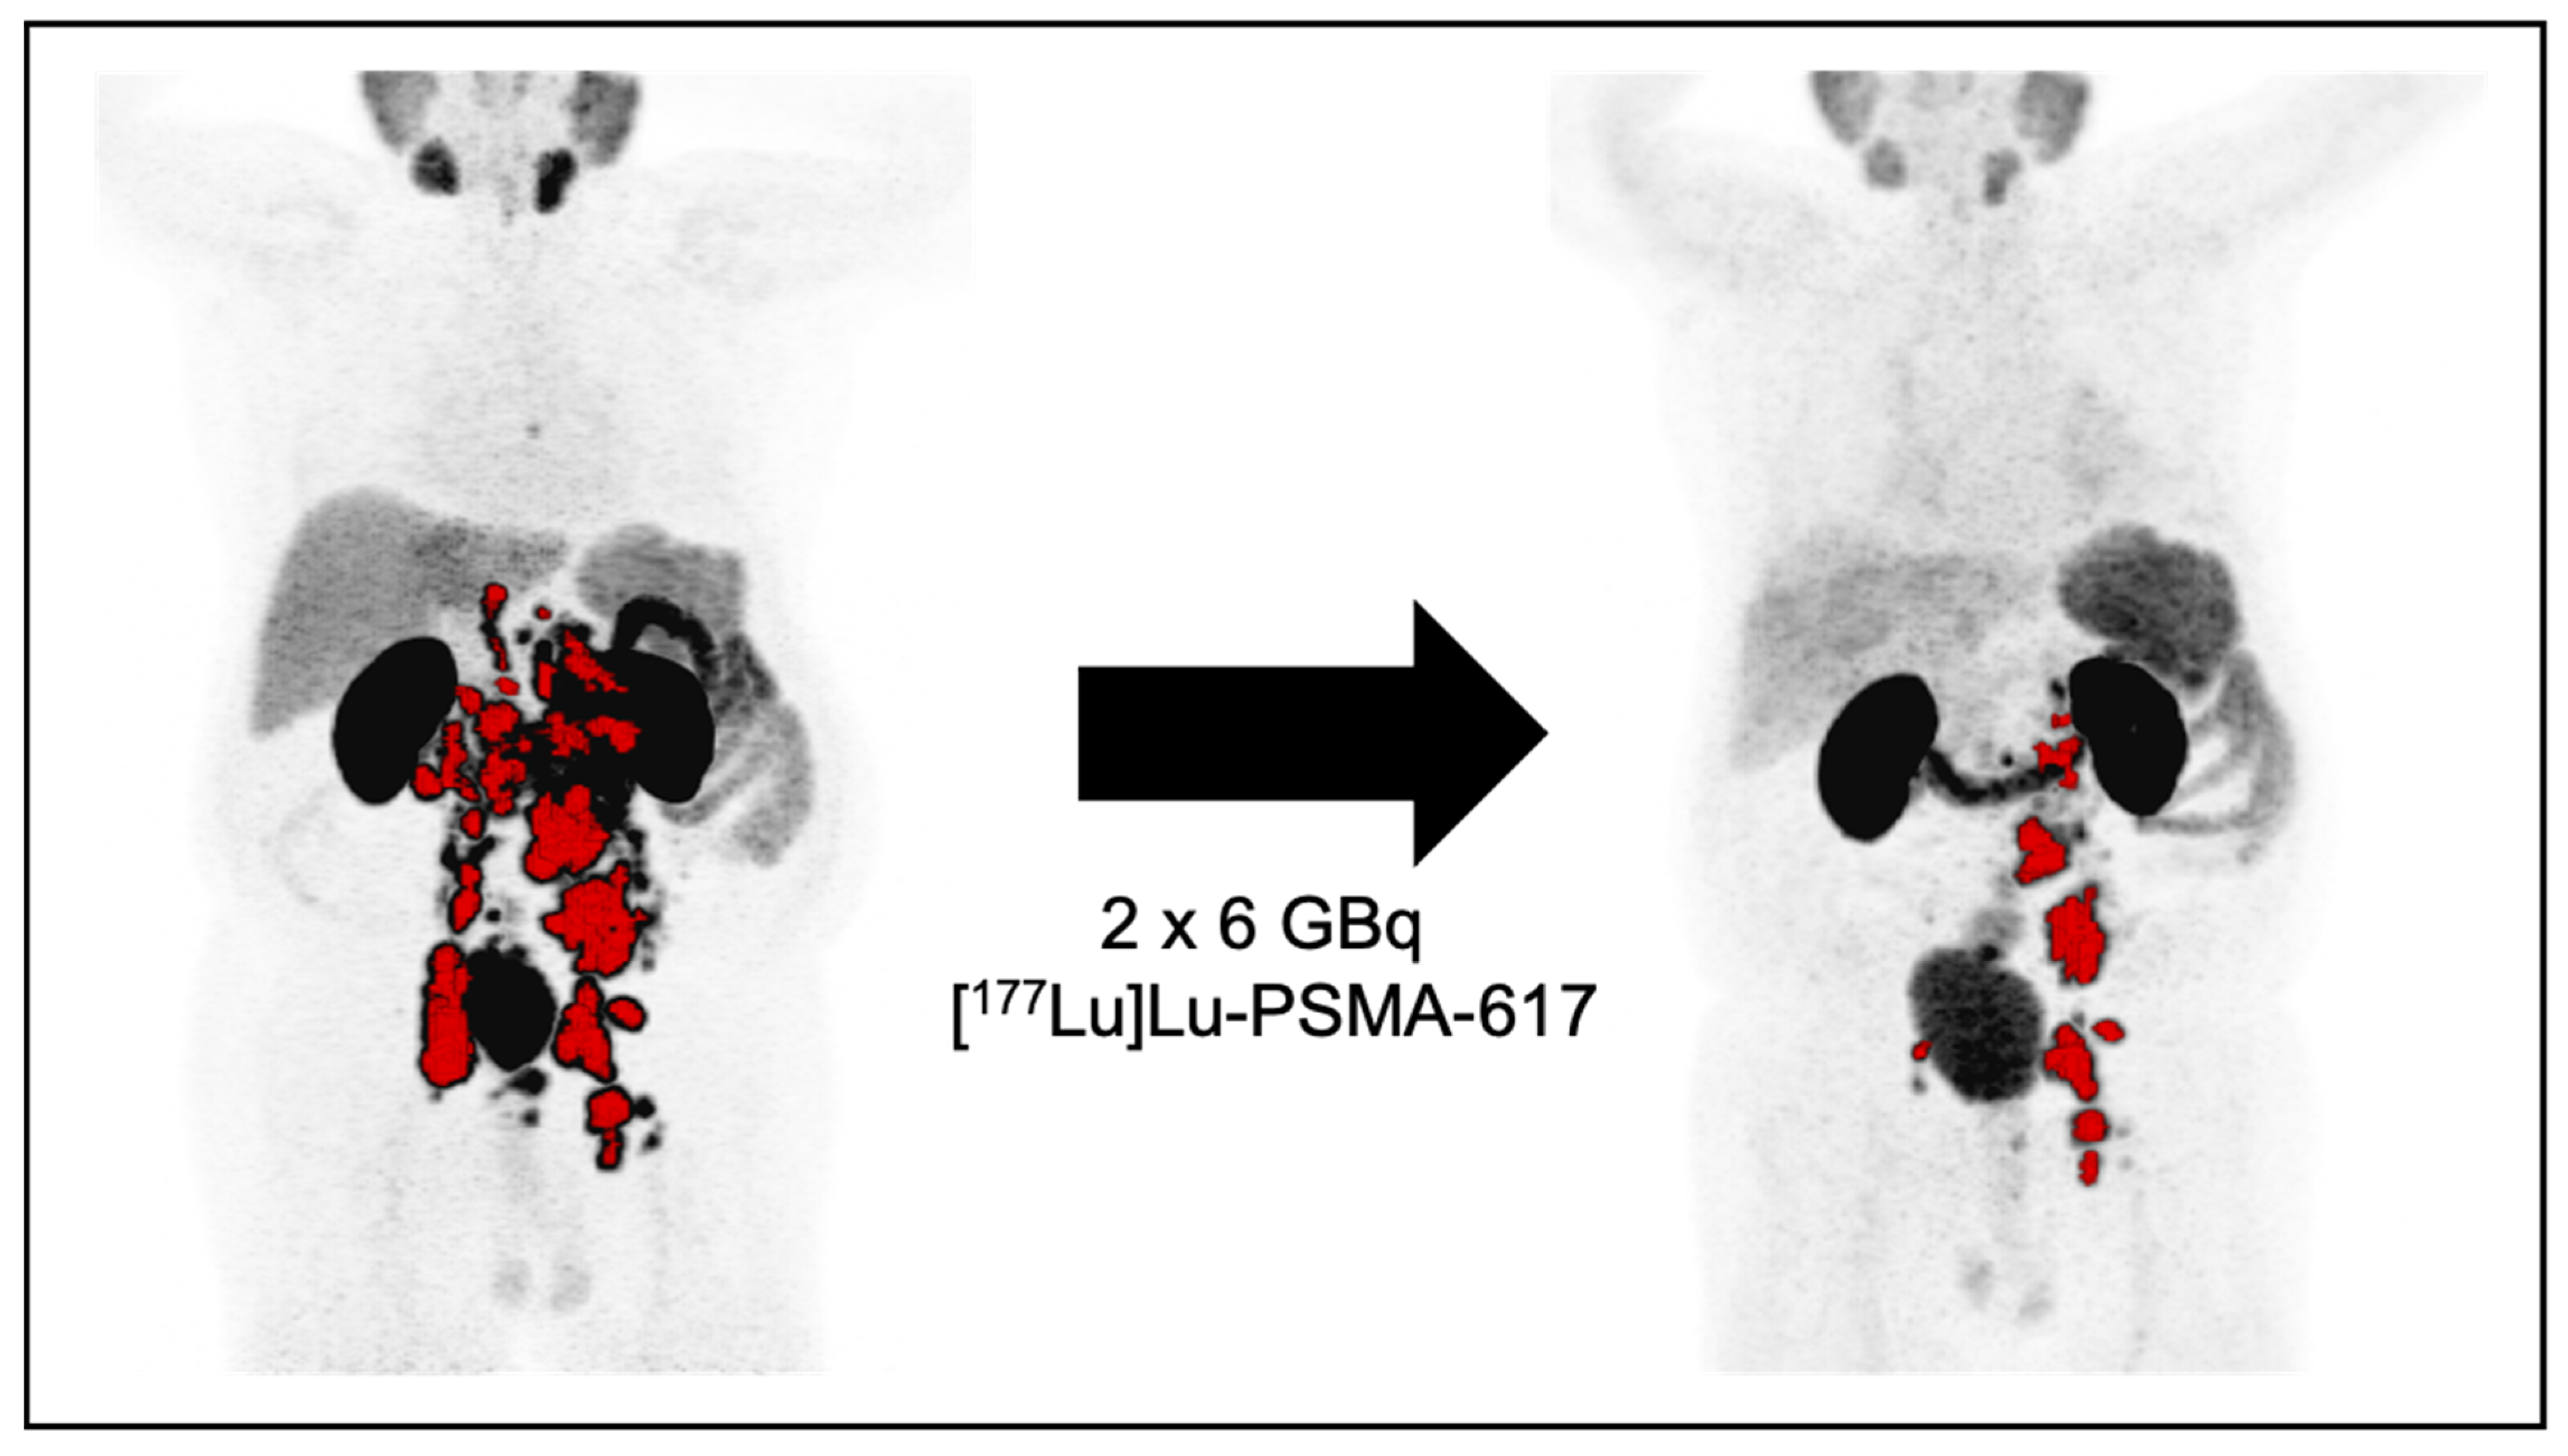
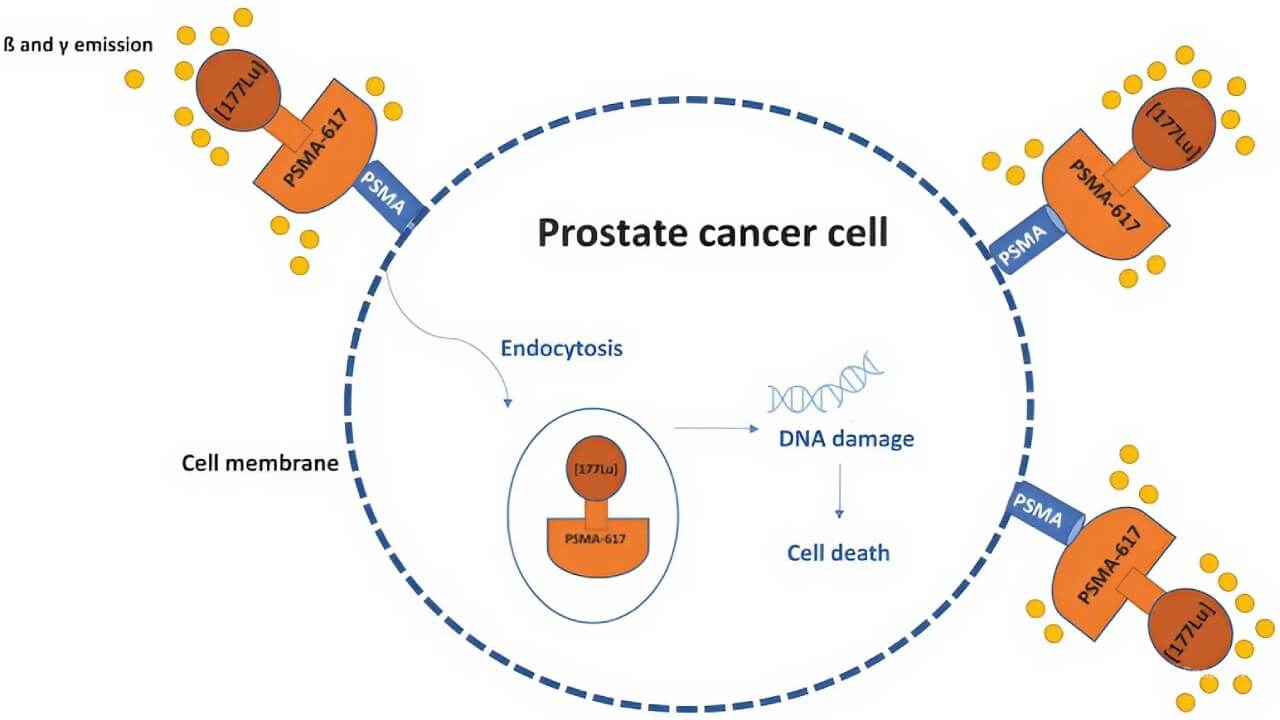
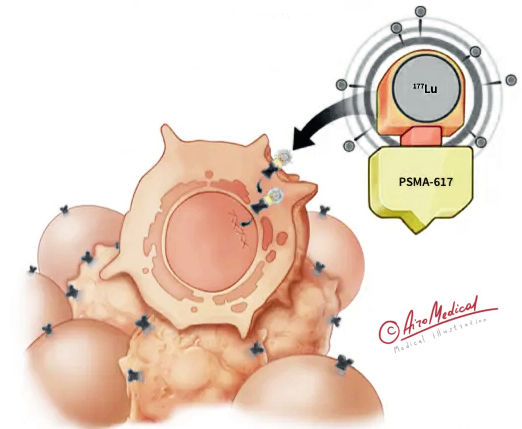
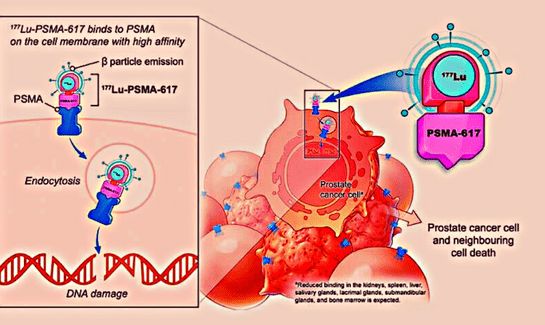
It is a radioligand treatment that targets prostate-specific membrane antigen using a beta-emitting isotope attached to a small-molecule inhibitor. The drug links lutetium-177 to PSMA-617, a urea-based ligand that binds to the PSMA protein expressed on prostate cancer cells. The radioactivity travels short distances inside the tumor, which spares surrounding healthy tissue more than conventional external beam radiation would. The standard protocol I see in practice involves a cycle of about 6 to 8 weeks, and most patients receive 4 to 6 cycles. Each infusion typically delivers between 6.5 and 7.4 GBq (175 to 200 mCi) of lutetium-177-PSMA-617. Before each dose, you need imaging to confirm the tumor is PSMA-positive on a Ga-68 or F-18 PSMA PET scan, because the treatment simply will not work if the cancer no longer expresses the target antigen. You also check renal function, complete blood counts, and albumin levels before proceeding. I once worked with a patient whose kidneys were clearing the radiopharmaceutical too slowly due to subclinical renal impairment. The whole-body counts suggested residual activity hanging around his soft tissues between cycles. The workaround was extending the interval from 6 weeks to 8 weeks and cutting the dose by 15 percent, while giving him aggressive hydration with Mannitol pre and post infusion. It cut his response curve, but it kept his creatinine from climbing, which matters more in the long run than pushing the first dose hard.
Sometimes I see centers skip the pre-treatment PSMA PET and rely only on the earlier diagnostic scan. That is a mistake. Tumor biology changes, PSMA expression can drop after several lines of hormone therapy, and treating blindly wastes both the isotope and the patient's recovery time. Do the confirmatory scan within 4 to 8 weeks of the planned infusion. If the uptake is clearly below background, stop and rethink the plan.
What Actually Happens During and After Infusion
The infusion itself takes roughly 20 to 30 minutes. Most centers run it through a peripheral IV with standard radiation safety precautions, though a port is fine if the patient already has one. The key timing factor is when you do the post-therapy whole body scan. I recommend doing it between 24 and 72 hours after infusion. The bone marrow and kidney uptake are clearer at 24 hours, while the tumor targeting shows more contrast later. A mid-point scan around 48 hours gives the best balance for most cases. Side effects are mostly dose-limiting rather than dangerous. Dry mouth from salivary gland uptake is very common, and it is usually mild to moderate. I tell patients to chew sugar-free gum, stay well hydrated, and use warm compresses on the parotid and submandibular regions. Some centers prescribe pilocarpine starting a few days before the first cycle and continuing through the treatment course, which I have found helps in about two-thirds of patients. Taste changes show up in roughly a quarter of people, and they typically resolve within a few months. Hematologic toxicity is the real bottleneck. Platelets and lymphocytes drop first, then hemoglobin and neutrophils follow if you keep dosing without checking. I usually hold a cycle if the platelet count falls below 100 x 10^9/L or if the lymphocyte count is under 0.5 x 10^9/L. Pushing through these thresholds leads to prolonged cytopenias that delay the next cycle by weeks and sometimes months. A patient who misses three cycles due to poor marrow recovery is worse off than one who gets three solid cycles with appropriate dosing.
Get the Full Details

Common Pitfalls and What I Do Differently
One thing that catches people off guard is physiological uptake in the lacrimal glands and upper gastrointestinal tract. These areas light up on post-therapy scans and can be mistaken for metastatic disease on follow-up imaging. The pituitary gland does the same thing. If you do not know the normal biodistribution pattern, you will overcall progression on the first post-treatment PET scan. I always compare the new images against the baseline and flag any symmetric uptake in those expected structures as physiological before declaring anything pathological. Another issue is the way different hospitals handle saline hydration. Some centers give 500 mL pre-infusion and none after. I have seen better results with 1 liter of normal saline during the infusion plus an additional 500 mL over the next 2 hours. It does not change efficacy, but it improves renal clearance and reduces kidney absorbed dose by an estimated 10 to 15 percent based on MIRD calculations. It is a small change that matters when you are nearing the kidney tolerance limit across four or five cycles. There is also the question of whether to combine this therapy with continued androgen deprivation. The VISION trial included patients who remained on ADT, and in practice, keeping patients on their GnRH antagonist or agonist during treatment is standard. Stopping ADT abruptly in patients with castration-resistant disease tends to cause a PSA bounce that obscures whether the radiotherapy is working. I keep them on their baseline endocrine therapy and reassess at 8 to 12 weeks after the first cycle.
Who This Does Not Help
Lu-PSMA therapy is not a universal solution. It requires adequate PSMA expression on imaging. Patients with neuroendocrine differentiation or extensive dedifferentiation often have low or absent PSMA targets, and the treatment will not produce meaningful responses in that population. It is also less effective when disease burden is very high, because the ligand gets saturated by circulating tumor markers and normal tissue binding before enough reaches the metastases. I tend to recommend this approach for patients with moderate-volume metastatic castration-resistant prostate cancer, not for those with widespread bulky disease where I would consider platinum-based chemotherapy first. Renal impairment beyond a certain point is a hard stop. If the glomerular filtration rate drops below 45 mL/min consistently across cycles, the risk of permanent dialysis dependence rises significantly. I do not push past that threshold. Some centers attempt dose reductions to keep treating, but the data does not support meaningful benefit in that range, and the cumulative nephrotoxicity is real. When that line is crossed, I switch to palliative care discussions or clinical trial enrollment rather than continuing to expose the kidneys to another cycle. The biggest limitation I see in practice is access and logistics. Not every hospital has the radionuclide therapy certification, the hot lab setup, or the radiation safety officer experience to handle lutetium-177 properly. Patients sometimes travel two or three hours to a center that does, and the travel itself becomes a factor when cycles repeat every 6 weeks. I make sure patients understand this upfront so they are not surprised when the second or third cycle requires the same commute.