Why Everyone Gets The 206 Bones Count Wrong
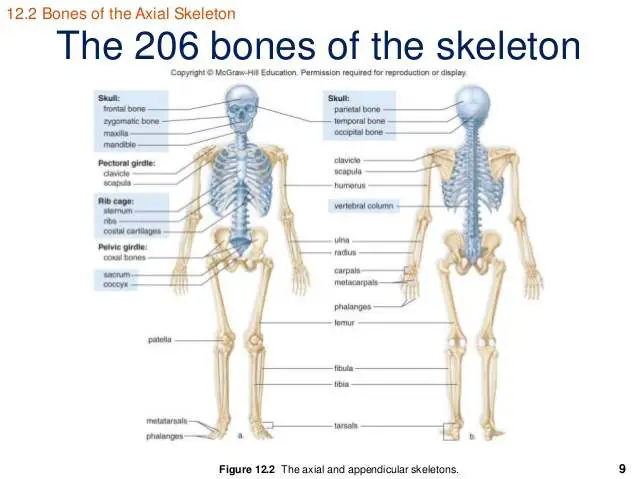
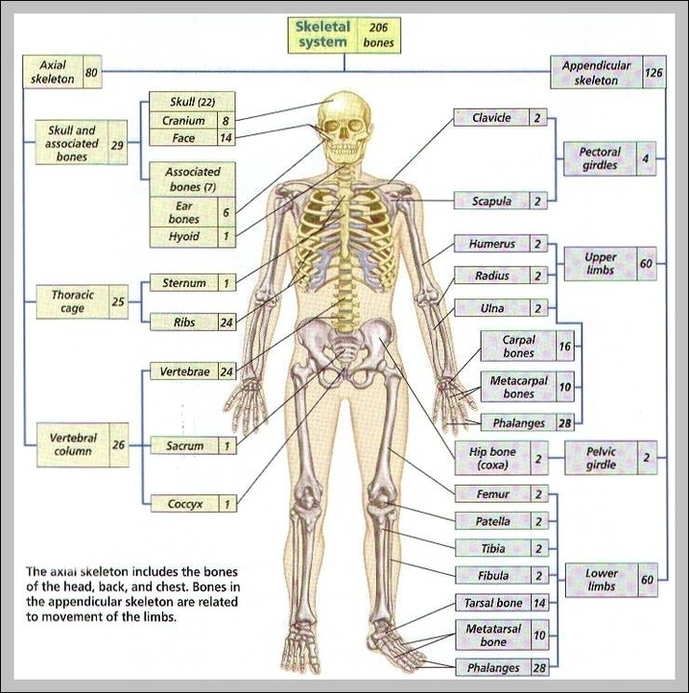
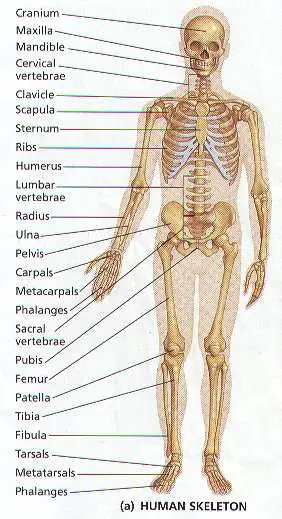
The standard 206 Bones Of The Body Diagram you see in anatomy textbooks is technically accurate for an average adult, but it's a simplification that will trip you up the moment you open a real CT scan or cadaver. I spent three years doing clinical imaging, and the first time I tried to map a standard diagram to an actual patient, I wasted almost two hours because certain bones just weren't where they were supposed to be. The number 206 isn't a law of nature. It's an average. The adult human skeleton is divided into the axial skeleton (80 bones: skull, vertebral column, rib cage, and hyoid) and the appendicular skeleton (126 bones: shoulders, arms, pelvis, legs, and hands). That's the breakdown. Standard stuff. But here's what most diagrams leave out. Sesamoid bones are the first gap. The patella is the only sesamoid bone consistently shown, but there are dozens more scattered through tendons, especially in the feet and hands. Some people have them, some don't. If your diagram includes sesamoids, you're looking at 206 plus whatever extras that individual carries. If it doesn't, the count drops depending on which bones you're excluding from the skull.
The vertebral column alone varies. Most diagrams show 26 vertebrae, but the fusion of the coccyx is wildly inconsistent. I've seen coccyges count anywhere from three to five distinct segments, sometimes fully fused into a single bone. That shifts your total by a couple bones either way.
How To Actually Use A Skeletal Diagram In Practice
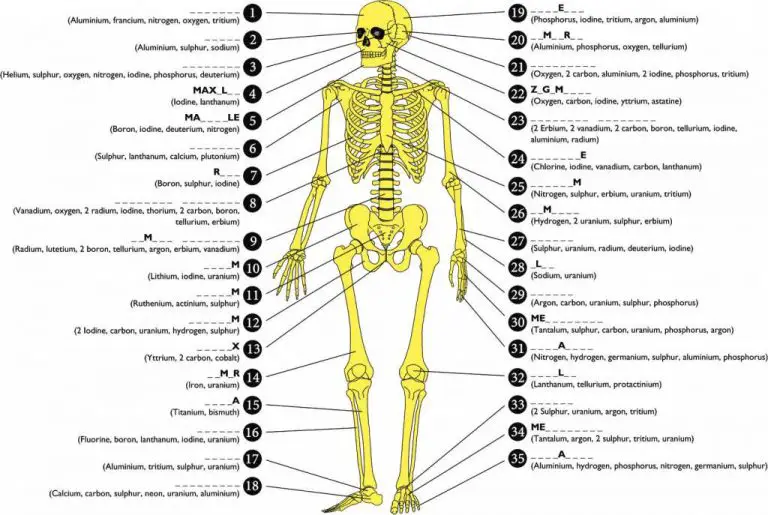
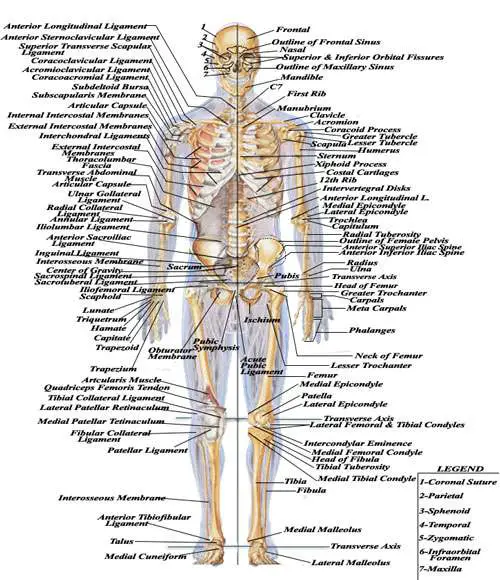
Start by picking a diagram that labels both osteological landmarks and articular surfaces separately. Most student diagrams merge these, which makes them useless for anything beyond labeling exercises. A proper reference separates the palpable prominences from the joint surfaces so you can cross-reference with live anatomy. When I was building my reference materials for a radiology rotation, I needed diagrams where each bone was individually labeled with both its common name and its Latin designation, plus the key landmarks relevant to imaging. I found that standard textbook atlases were too detailed and clinical illustrations were too simplified. What I ended up doing was taking a clean grayscale skeletal diagram and annotating it myself with translucent SVG layers. Each layer was a different system: axial, upper appendicular, lower appendicular. That took about four hours and has saved me probably a hundred hours since. Here's the practical workflow I use now:
Get the Full Details
Step one, load the diagram into your annotation tool. I use a simple vector editor. Don't overcomplicate this. Step two, color-code by region. Axial in blue, upper limbs in orange, lower limbs in green, girdles in yellow. This takes about twenty minutes if you're methodical. Step three, add landmark callouts for the ones that matter in your context. If you're studying fractures, focus on common break sites. If you're doing palpation work, focus on bony prominences. I learned this the hard way after spending an entire study session highlighting landmark after landmark, only to realize later that half of them were irrelevant to what I was actually trying to do.
Common Pitfalls And What To Watch For
The biggest issue with the 206 Bones Of The Body Diagram as a teaching tool is that it presents a static, averaged skeleton as if it's universal. Real variation is significant. The clavicle is the most variable bone in the body. Some people have a fully fused sternal end while others retain a cartilaginous interface well into their forties. Diagrams never show this. Another problem is the treatment of the skull. The diagram typically shows 22 bones in the cranium and face, but the ossicles in the middle ear (six total, three per side) are often omitted or listed separately. Add those in and you're at 224 before you even consider sutural bones or sesamoids. I encountered a specific edge case during a musculoskeletal ultrasound rotation where a patient had a persistent synchondrosis between the basilar and preterinal parts of the occipital bone. On a standard diagram, that area is one bone. In that patient, it was clearly two separate ossification centers that hadn't fused. The difference mattered for interpreting a subtle fracture line that was actually a unfused growth plate variant. My workaround was keeping a reference of common persistent synchondroses and sutural variants at hand, which I compiled from published radiological case studies. That reference cut my uncertainty time in half when I hit these edge cases.
Downsides You Should Know About
The 206 count assumes a fully fused adult skeleton. If you're working with pediatric cases, the numbers are completely different. A newborn has roughly 270 bones, and the count doesn't settle until late adolescence. Using an adult diagram with pediatric imaging is one of the fastest ways to misidentify a normal growth plate as a fracture. Diagrams also fail to convey bone density variation. The trabecular architecture in the proximal femur versus the cortical thickness of the tibia are fundamentally different, and a flat 2D diagram flattens that distinction entirely. If you're studying biomechanics or implant placement, you'll need supplementary material that shows cross-sectional bone morphology. For most people doing basic anatomical reference work, a well-labeled diagram is sufficient. But if you're in a clinical or research setting, you should pair any diagram with a 3D volumetric reference. The time investment is worth it. A proper 3D skeletal model from a public dataset like the Visible Human Project loads in seconds and lets you rotate, section, and isolate individual bones in a way that any flat diagram simply cannot match.
I keep a lightweight open-source viewer running alongside my diagram library now. It handles the cases where the 2D representation breaks down, and it only takes about five minutes to set up on a standard machine. The diagram handles quick lookups and labeling. The 3D model handles spatial relationships and pathological variation. Using both together covers the gaps that either one leaves open on its own.