How Tissue Actually Recovers After an Athletic Injury
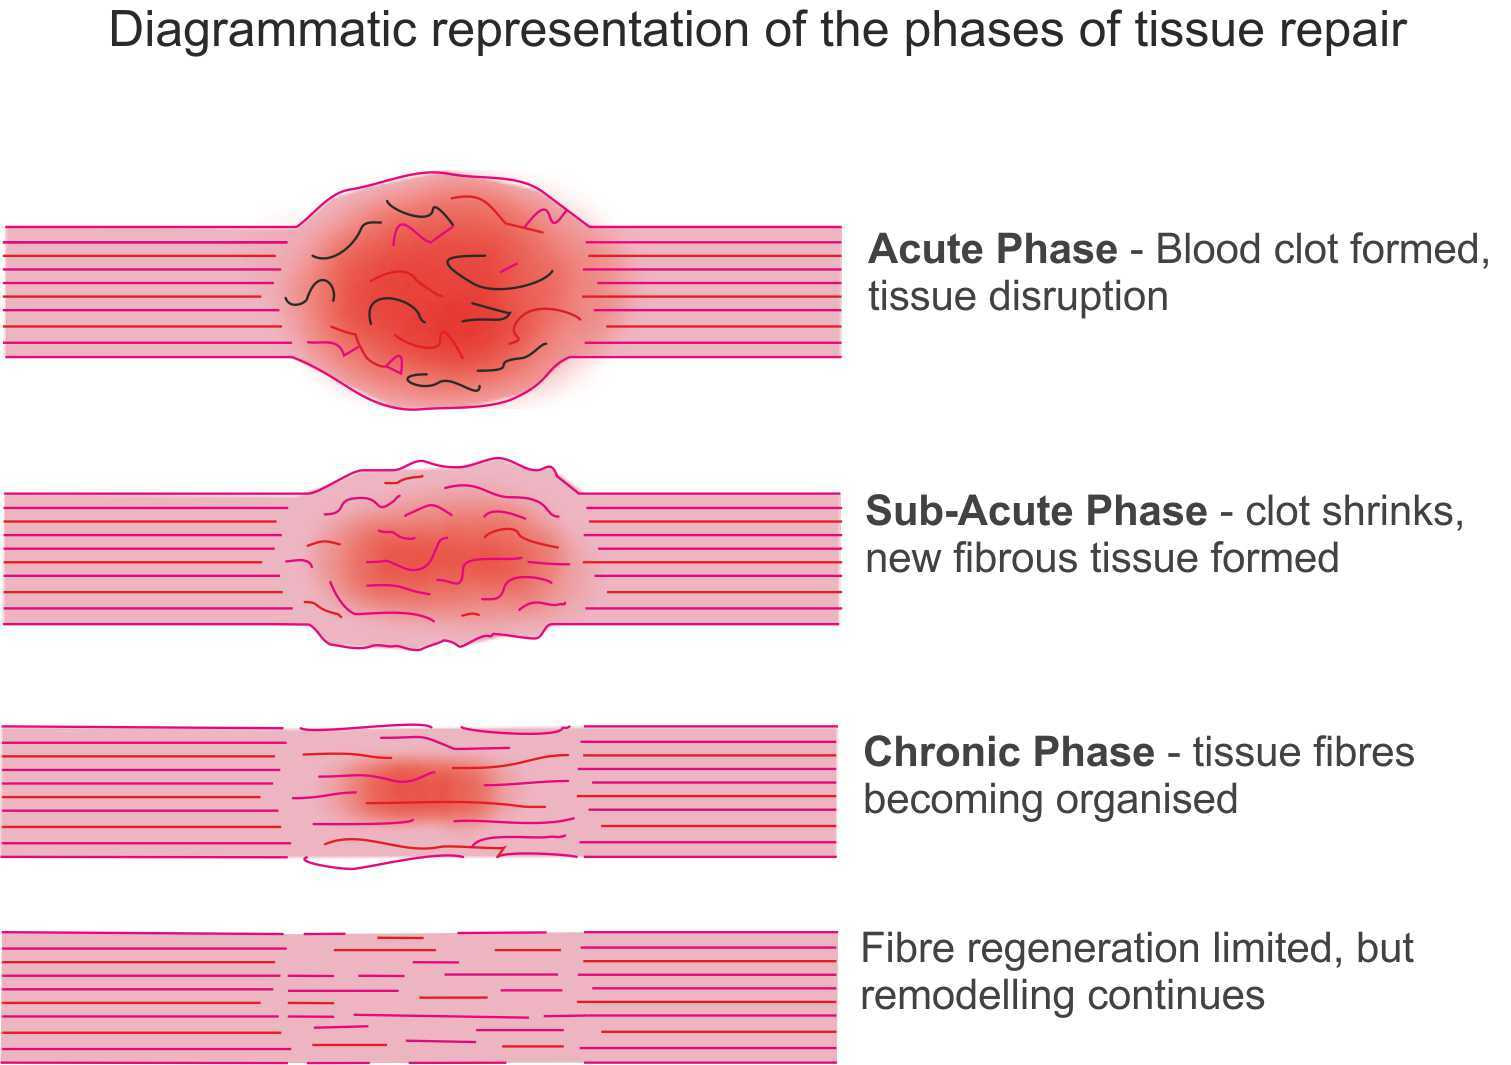
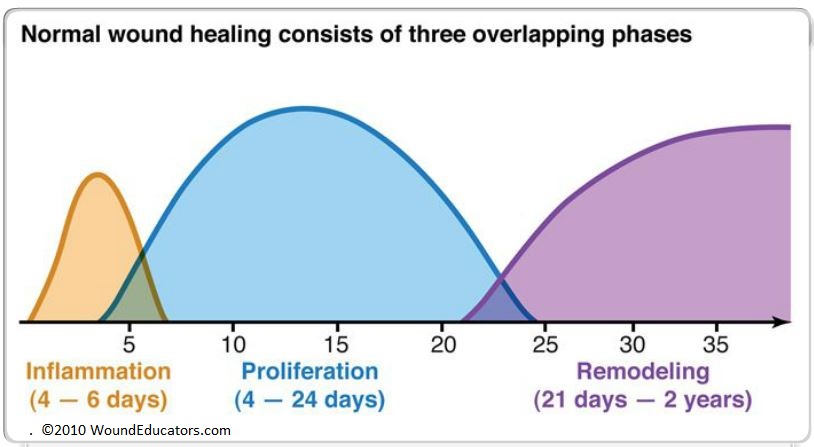
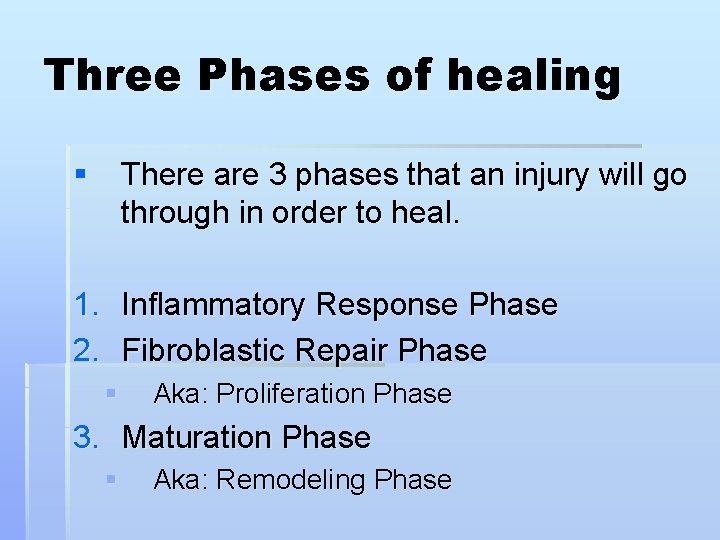
Most trainers and athletes think healing is linear. It isn't. When a ligament, tendon, or muscle tears, the body runs through three distinct biological windows, and each one demands completely different handling. Treat the phase wrong and you reset the clock. I've seen people lose weeks because they pushed load during the inflammatory stage or held back too long during remodeling. The three Phases Of Healing Athletic Training professionals rely on are the inflammatory phase, the proliferative phase, and the remodeling phase. Understanding when you transition between them is the actual skill. Not memorizing the names.
The Inflammatory Phase (Days 1–7)
This is the cleanup crew. Blood vessels rupture, platelets plug the area, and inflammatory cells flood in to remove damaged tissue. Swelling, heat, redness, and pain are the signals. They're not problems to suppress aggressively — they're the process working. I used to ice everything for twenty minutes straight after a soft tissue injury. That was wrong. What actually works is controlled compression and gentle movement within pain tolerance, not complete rest. The old RICE protocol overprescribes immobilization. Tendons and ligaments need controlled mechanical loading early to align collagen fibers properly, but the tissue is mechanically weakest right now. A grade 2 ankle sprain will re-injure itself if you load it too aggressively on day three. I learned that the hard way with a client who returned to cutting drills too soon and ended up with chronic ankle instability that took another four months to address. The practical rule: protect the area, allow inflammation to run its course, begin pain-free range of motion as soon as tolerable. Anti-inflammatory medication can blunt this phase if taken in high doses during the first 48 hours. Some research suggests this delays healing. I don't recommend them during this window unless the pain is preventing basic movement.
The Proliferative Phase (Days 5–21)
Granulation tissue forms. New blood vessels grow in. Fibroblasts lay down collagen — initially disorganized, type III collagen that's weaker than the final product. The tissue is rebuilding but it's structurally compromised. This is where most rehab programs shift gears, but they usually shift too fast. Progressive loading is the key here, and I mean progressive in the strictest sense. Isometric holds first, then slow eccentric work, then controlled concentric loading. A common pitfall is jumping into sport-specific movement patterns too early. The collagen matrix needs shear stress in multiple directions to organize properly. I use cross-friction massage and graded mechanical loading at this stage to encourage the fibers to align along stress lines rather than lying in a chaotic mesh. The counter-intuitive part: some discomfort during this phase is expected and doesn't necessarily mean you're causing damage. Pain that stays below a 4 out of 10 during and after exercise, and doesn't increase swelling the next morning, is generally acceptable. Pain above that threshold or with next-day swelling means you've exceeded the tissue's current capacity.
Get the Full Details
The Remodeling Phase (Week 3 – 12+)
Type III collagen slowly converts to type I collagen. The tissue gains strength and orientation along functional lines. This phase lasts months, not weeks. The mistake athletes and trainers make is assuming the injury is "healed" once pain disappears. It's not. The tissue is still gaining strength. Return-to-sport decisions based on pain alone result in re-injury rates of 30 to 40 percent in many studies. Testing should be objective. Compare the injured limb to the uninjured side. Strength should be within 90 percent of the contralateral side before returning to cutting, jumping, or ballistic movements. Range of motion should match. Hop tests, balance tests, and sport-specific drills under fatigue should all pass before clearance. A specific edge case I run into regularly: calcific tendinopathy that develops during the proliferative phase. Sometimes the body overproduces calcium deposits in the healing tendon, especially in the shoulder and Achilles. It's painful and it slows everything down. The workaround is shockwave therapy — one or two sessions at moderate intensity can break up the deposit and restart the normal healing cascade. I've seen it add three to four weeks back onto a timeline that was looking like months of stagnation.
Another limitation worth noting: the 3 Phases Of Healing Athletic Training framework assumes normal physiology. It breaks down with diabetic patients, smokers, people on chronic corticosteroids, and older athletes over 40. Healing timelines stretch significantly in these populations. The phases still happen in the same order, but each one takes longer and the transition points are less clear-cut. In those cases, you rely more heavily on objective testing than on calendar estimates. The bottom line is that healing isn't something you wait through. It's something you guide. The right intervention at the right phase accelerates recovery. The wrong one at the right phase causes setbacks. And most people don't even realize which phase they're in.