Walking Tests in Clinical Practice
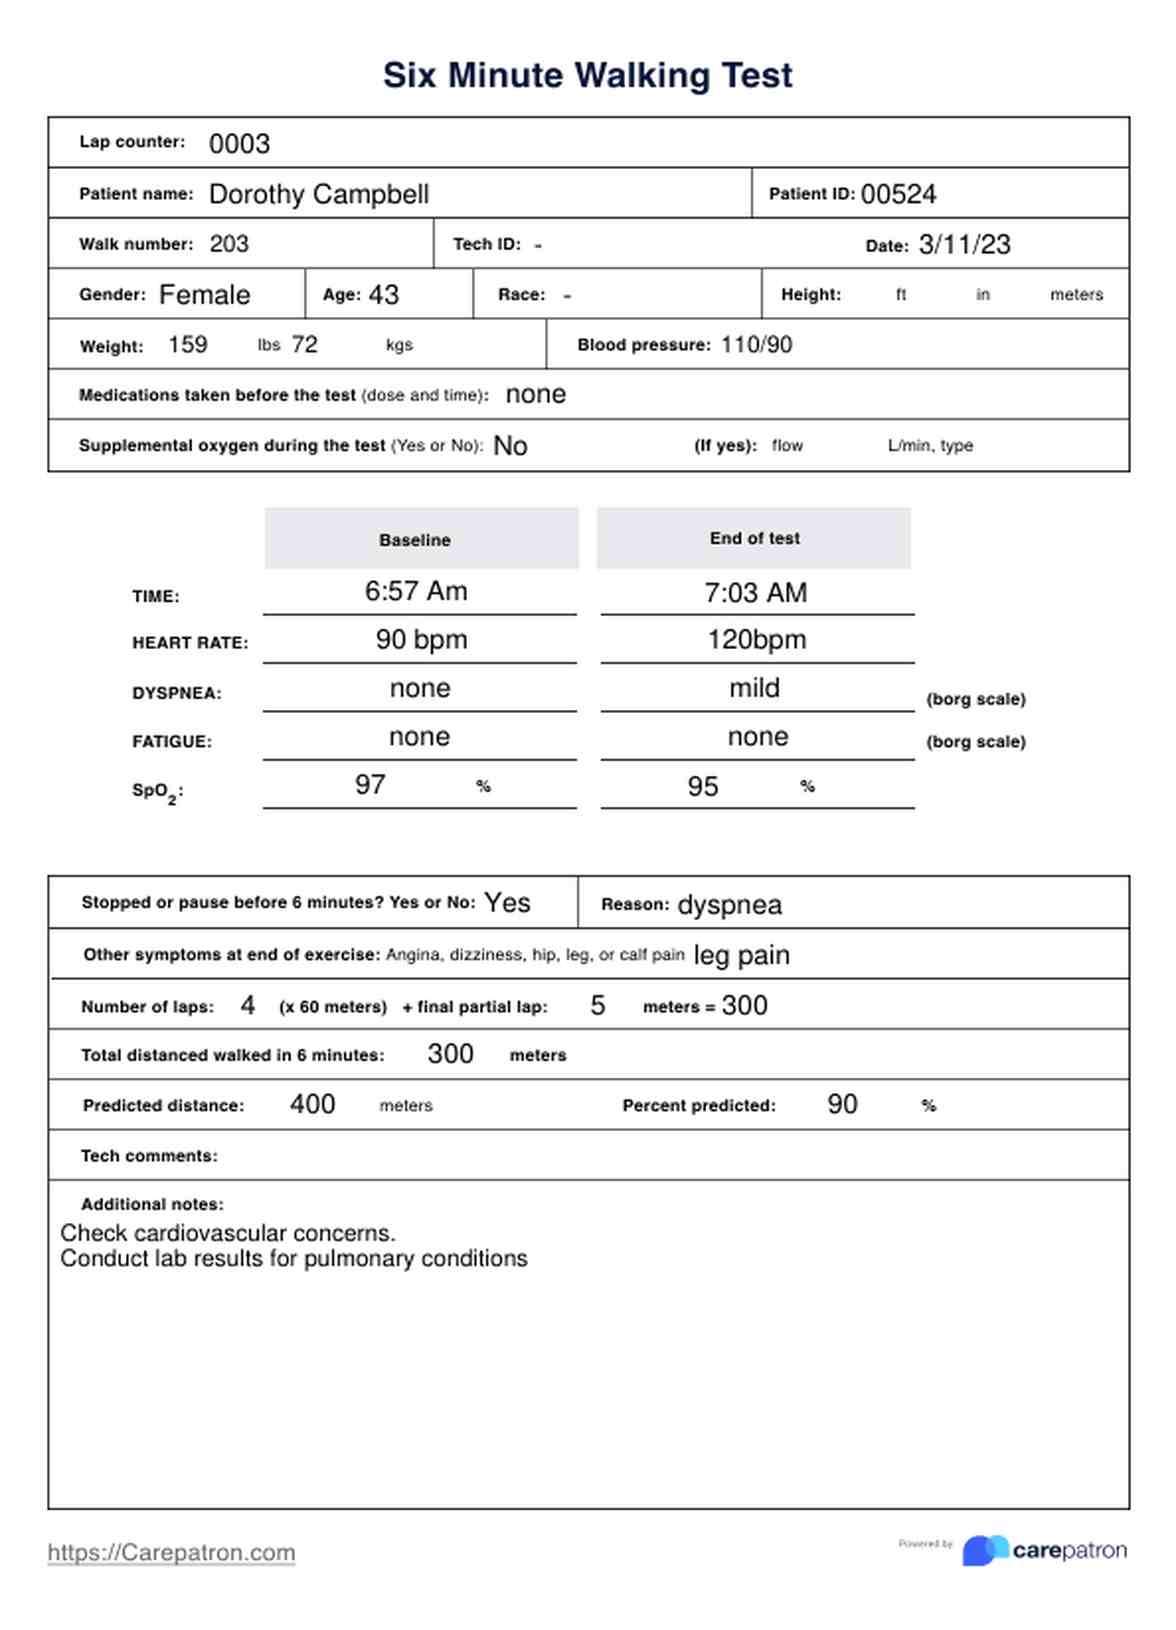
The 6 Minute Walk Test is a standard way to measure functional exercise capacity. It has been around for decades and shows up in pulmonary rehab, cardiology, geriatric assessments, and research protocols everywhere. But the actual paperwork attached to it—the 6 Minute Walk Test Worksheet—is where most people trip up. Not because the test is complicated. Because the documentation side is poorly designed or simply not standardized. I ran these tests in a rehab clinic for years. We used printout sheets, then switched to tablets, then went back to printouts because tablets introduced data entry errors we couldn't ignore. The worksheet itself is pretty minimal. It records distance walked, oxygen saturation before and after, Borg scale ratings at minute 2 and minute 5, and whether the test was terminated early and why. That's it. Five to six data fields. The problem isn't the content. It's the version you end up using.
Getting Your Hands on a 6 Minute Walk Test Worksheet
There are several versions floating around. Some come from the ATS guidelines. Others are clinic-specific adaptations. A few are straight copies of the original Goris template from the 1990s with minor modifications slapped on. For actual clinical or research use, I recommend starting with the ATS-referenced worksheet. It aligns with the official standards and gives you a clean baseline. If you search for "6 Minute Walk Test Worksheet ATS" or "6 Minute Walk Test Worksheet PDF," you'll find downloadable versions from university hospitals and pulmonology departments that are free to print. One thing worth noting: the ATS does not publish a single proprietary form. Many sites claim theirs is "ATS approved," which just means they followed the guidelines. It doesn't mean anything more than that. As long as your worksheet captures distance, resting and post-test O2 saturation, pre-test vital signs, Borg scale at minutes 2 and 5, and termination criteria, you're covered.
How the Test Actually Runs
Set up a 30-meter corridor. Mark every meter with tape on the floor. That's the standard. You can do it at 10 meters if you're short on space, but 30 meters is what the reference equations assume. Place a timer where the walker can see it. Stand at the far end with the worksheet. Instruct the patient to walk as far as they can for 6 minutes. They turn around every meter mark. You call out "minute 1, minute 2..." and so on. At minute 2 and minute 5, you ask them to rate their shortness of breath and leg fatigue on the 0-10 Borg scale. Record it. At the end, record the total distance, check their post-test O2 saturation, and note any stops. The Borg scale measurement is where people get lazy. Some clinicians skip the minute 2 rating because the patient hasn't been walking long enough to give a meaningful score. That's reasonable. But the minute 5 rating absolutely matters—it tracks whether fatigue is accelerating toward the end, which is clinically relevant. Also record submaximal symptoms like chest pain, dizziness, or calf pain. If either shows up, note it on the worksheet and terminate. That's a safety issue, not a data issue.
Get the Full Details

A Real Problem I Hit
Once, during a research study, I had a patient who stopped at 4:30 because he developed unilateral calf pain. He refused to continue. My worksheet had a box for "reason for termination," and I wrote "calf pain." The PI flagged it because the reason wasn't one of the predefined options on the form. Turns out the worksheet I'd downloaded was a modified version from a different lab, and the stop criteria list didn't match ours. We had to go back and annotate the form or redo the data entry with extra documentation. Lesson learned: always cross-check the termination criteria listed on your worksheet against your study protocol before running a single subject. Another common issue: the distance field. Walkers stop at the next marker. So if someone walks 187.5 meters and turns at the 187-meter mark, you record 187 meters. But some worksheets have a field that looks like it expects whole numbers and the user writes "187.5" anyway. That's fine, but be consistent. Mixing integer and decimal entries across subjects makes your dataset messy and introduces noise in later analysis. Pick a format and stick with it.
What Most Worksheets Miss
Standard worksheets rarely capture something important: whether the patient used an assistive device during the test. A walker, cane, or rollator changes the expected distance. If you're using reference equations, those equations have separate norms for device users versus non-users. So add a checkbox or line for "assistive device used: yes/no/type." Takes three seconds on the form and saves you from guessing later. Also missing from many forms: the floor surface type. Tile, carpet, linoleum, outdoor asphalt. These all affect walking speed and distance, especially for elderly or mobility-limited patients. Again, one line item. I usually just write "indoor tile" or "indoor carpet" in the notes section. Doesn't look like much but it matters if you're comparing your results to published norms that were mostly done on smooth indoor surfaces.
When the 6MWT Falls Flat
This test has real limitations. It's effort-dependent, which means a motivated patient will walk further than an unmotivated one, and you can't fully control for that. It's also influenced by motivation, cognitive ability, and fear of falling. A patient with mild dementia might complete the distance but not understand the Borg scale, making those ratings unreliable. In those cases, just record the distance and note the limitation. Don't fabricate data to fill a blank field. For patients with severe peripheral arterial disease, the 6MWT underestimates their functional limitation because claudication pain kicks in well before cardiovascular or pulmonary limits are reached. If you're testing a vascular patient, consider supplementing with a 4-Meter Gait Speed test or an ankle-brachial index assessment. The 6MWT alone will miss key clinical information. Another blind spot: the test assumes bilateral lower extremity function. Patients with unilateral amputations or asymmetric paralysis don't fit the reference equations. Their distances will be lower, but that doesn't necessarily reflect worse cardiopulmonary function. It reflects biomechanics. Document the asymmetry and interpret accordingly.

Quick Reference for Standard Values
For healthy adults, average distances typically range from 400 to 700 meters depending on age, sex, and height. The Qureshi equation is one commonly used reference. It factors in age, sex, height, and weight. But don't treat the predicted value as a hard cutoff. A patient scoring 20% below predicted isn't automatically abnormal, especially in chronic conditions where baseline is already depressed. Use trends over time, not single measurements. Three consecutive worksheets showing improvement from 320m to 380m to 410m tells you more than a single number compared to a prediction. Print out your worksheet. Fill it in carefully. Check the termination criteria against your protocol. Add a line for assistive devices if your version doesn't have one. And don't waste time hunting for the "perfect" form—the ones that exist are close enough. What matters is consistency in how you use them, not which version you chose.