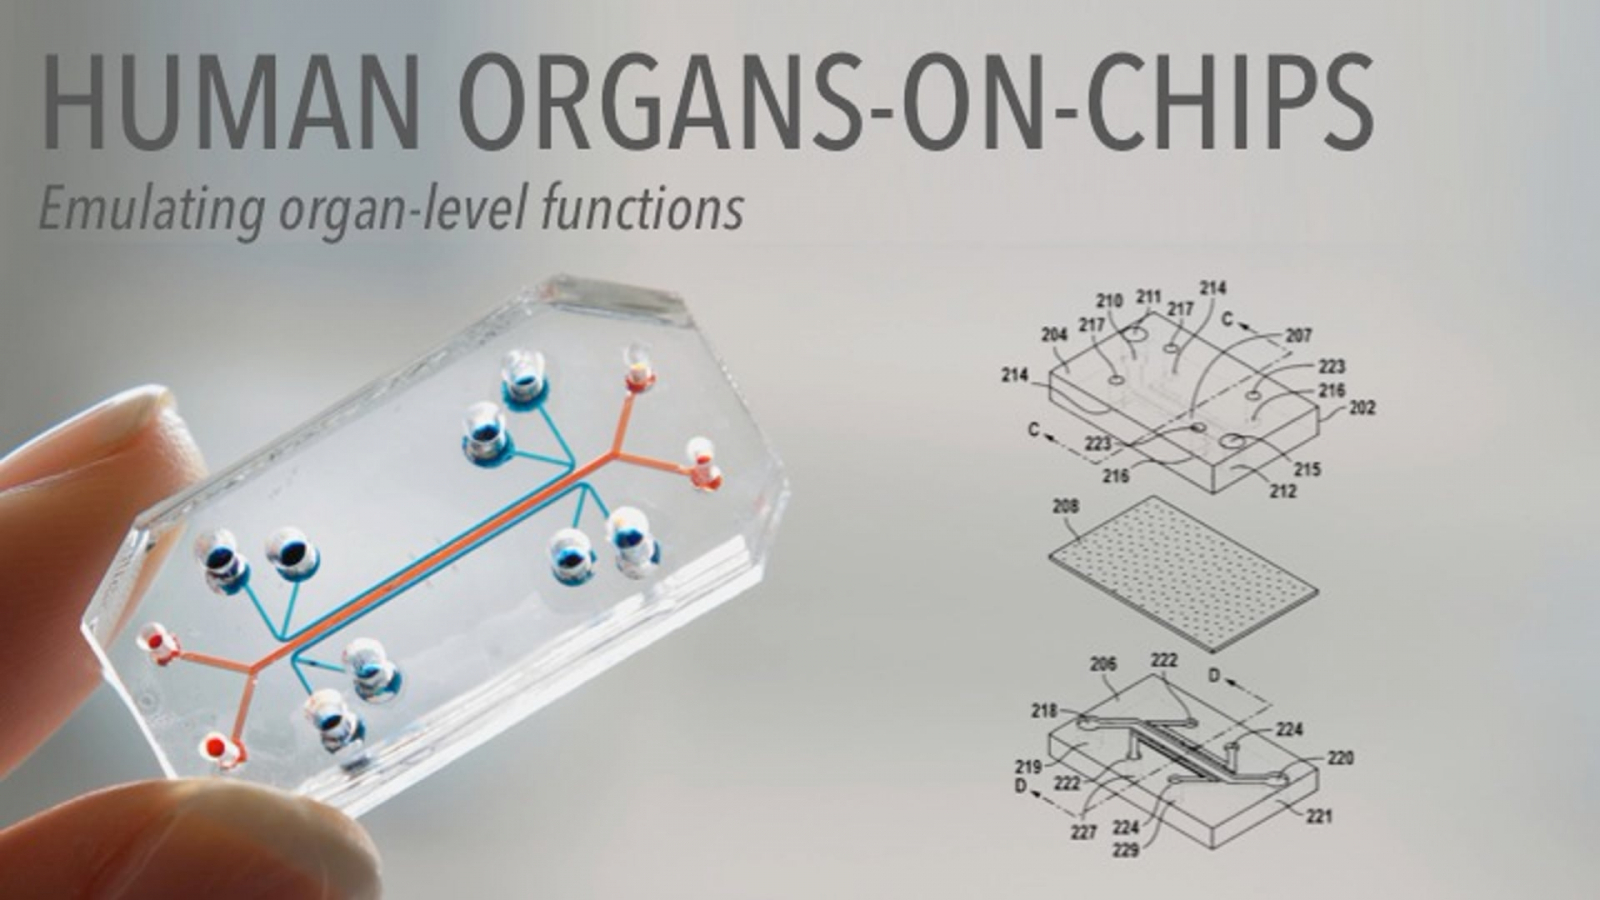
Most people see the term and picture something sci-fi, but it's just a microfluidic device that replicates the structural and functional characteristics of human organs at a fraction of the size. You get a thin polymer channel lined with living cells, subjected to mechanical forces like stretching or fluid flow, and it mimics what happens inside your body. I've spent years working with these systems, and the reality is far less glamorous than the hype cycles suggest.
A Guide To The Organ On A Chip
The basic setup involves three main components: a microfluidic channel architecture, human-derived cells (usually primary cells or iPSCs), and a mechanical actuation system. The chips themselves are typically made from PDMS or thermoplastics, and they range from simple two-chamber devices to complex multi-organ systems with hundreds of inputs and outputs.
When you're building one, the first thing you deal with is cell sourcing. Primary human cells give you the most physiologically relevant results but they have a limited lifespan. iPSC-derived cells are more reproducible but require significant differentiation protocols that can vary between labs. I've seen teams waste three months trying to get consistent hepatocyte function from iPSCs because the differentiation buffer conditions weren't standardized.
The microfluidic design is where most people stumble. You need to get the shear stress, the oxygen gradient, and the mechanical strain right. A liver chip needs portal vein-like flow conditions, roughly 1 to 5 dyne per square centimeter of wall shear stress. Get it wrong and your cells either detach or start behaving abnormally. I had a chip where the flow rate was calibrated for a different channel geometry and the endothelial layer washed out within six hours. Took me a day to realize the calibration was based on a nominal flow setting rather than actual volumetric output through that specific channel width.
How It Actually Works In Practice
Cell seeding is deceptively simple but absolutely critical. You're typically seeding one cell type in each compartment and letting them adhere before introducing flow. The interface between compartments usually has a porous membrane with pores around 0.4 to 8 micrometers depending on what you're modeling. For a blood-brain barrier chip, you want tight junctions forming across an endothelial monolayer on one side and astrocytes on the other. The transendothelial electrical resistance should hit at least 300 ohm-centimeters squared before you consider the barrier functional.
Perfusion systems matter more than anyone admits upfront. You can't just hook a syringe pump and walk away. Air bubbles will kill your culture, pressure fluctuations will shear your cells, and long-term experiments require media replenishment. I use a dual syringe pump setup with inline bubble traps and pressure monitoring. The bubble traps are essential because even tiny microbubbles can occlude channels and create uneven flow distribution.
Characterization is where the real time goes. You're measuring TEER for barrier integrity, running lactate dehydrogenase assays for cytotoxicity, checking cytokine profiles with ELISA or bead-based multiplex assays, and doing immunostaining at various time points. A typical characterization workflow for a validated chip takes about two weeks from cell seeding to readiness for dosing.
Applications That Actually Matter
Toxicology screening is the most mature application. Companies are using organ-on-chip systems to predict hepatotoxicity and nephrotoxicity with better accuracy than static 2D cultures. The FDA has been clear about wanting to incorporate microphysiological systems into regulatory decision-making, and several companies have validated chip platforms against clinical datasets.
Drug-dosing prediction is another practical use case. You can model pharmacokinetics across multiple organ types simultaneously, which gives you exposure-response relationships that single-organ models can't capture. I've seen teams use kidney-liver-chip systems to predict drug accumulation and metabolite formation with error margins under 30 percent compared to clinical data.
Disease modeling works well for conditions with clear mechanical or fluid dynamics components. Lung chips for fibrosis and asthma research have produced useful data. Heart chips for arrhythmia detection are commercially available. Cancer metastasis models are emerging but still technically challenging to validate.
Common Pitfalls That Will Waste Your Time
Batch variability in PDMS is a real problem. Different lots of Sylgard 184 cure at slightly different rates and have different gas permeability. I stopped accepting supplier certificates and started testing each batch with control experiments before committing to a full study. The extra week of validation prevents months of downstream headaches.
Surface treatment consistency matters enormously. Plasma oxidation of PDMS is temporary and hydrophobic recovery begins within hours. I treat chips immediately before cell seeding and seed within ninety minutes of exposure. Anything longer and you get uneven cell adhesion that ruins monolayer integrity.
Contamination control is harder than with standard culture. The closed microfluidic environment means you can't easily swap out media or treat infections without disrupting the system. Antibiotic-free protocols are strongly recommended, and working in a biosafety cabinet with ethanol-wiped tools reduces risk significantly.
Media composition is another area people underestimate. Standard DMEM with ten percent FBS doesn't work well in most chip configurations. You typically need reduced serum concentrations, specific growth factor additions, and sometimes specialized media formulations designed for perfusion culture. I follow published protocols closely for the first few runs rather than trying to optimize media composition experimentally.
Validation And Regulatory Reality
The field has made significant progress but validation remains the bottleneck. Organizations like the International Alliance for Organ on a Chip and the Foundation for Innovative New Approaches have developed validation frameworks. The key is demonstrating that your chip predicts clinical outcomes with acceptable sensitivity and specificity for your intended use case.
If you're planning to submit data to regulatory agencies, you need to document everything: cell passage numbers, channel dimensions measured by microscopy, flow rates recorded in real time, and statistical analysis plans. Regulatory reviewers want to see that you understand your system's limitations as much as its capabilities.
Commercial platforms from companies like Emulate, Mimetas, and TissUse offer validated systems with supporting documentation. They're expensive but save considerable time on method development. Building in-house is cheaper per chip but requires substantial expertise in microfabrication, cell biology, and fluid dynamics.
The technology is genuinely useful for specific applications but it's not a replacement for animal models across the board. It excels at mechanistic studies and high-throughput screening. It struggles with whole-organism complexity and long-term chronic effects. Being honest about where the technology falls short will make your work stronger than overhyping it.
Gallery A Guide To The Organ On A Chip
State-of-the-Art Organ-on-Chip Models and Designs for Medical Applications: A Systematic Review
1 Various organ-on-chip systems reported in the literature mimicking... | Download Scientific ...
2) Human Organ-on-a-Chip: The State of Organ-on-a-Chip Technologies
Medical Technology: Organ-on-a-Chip Infographic | LivePhysics™
Organ On a Chip Visualized Infographic - Best Infographics