Understanding the Sarcomere in Practice
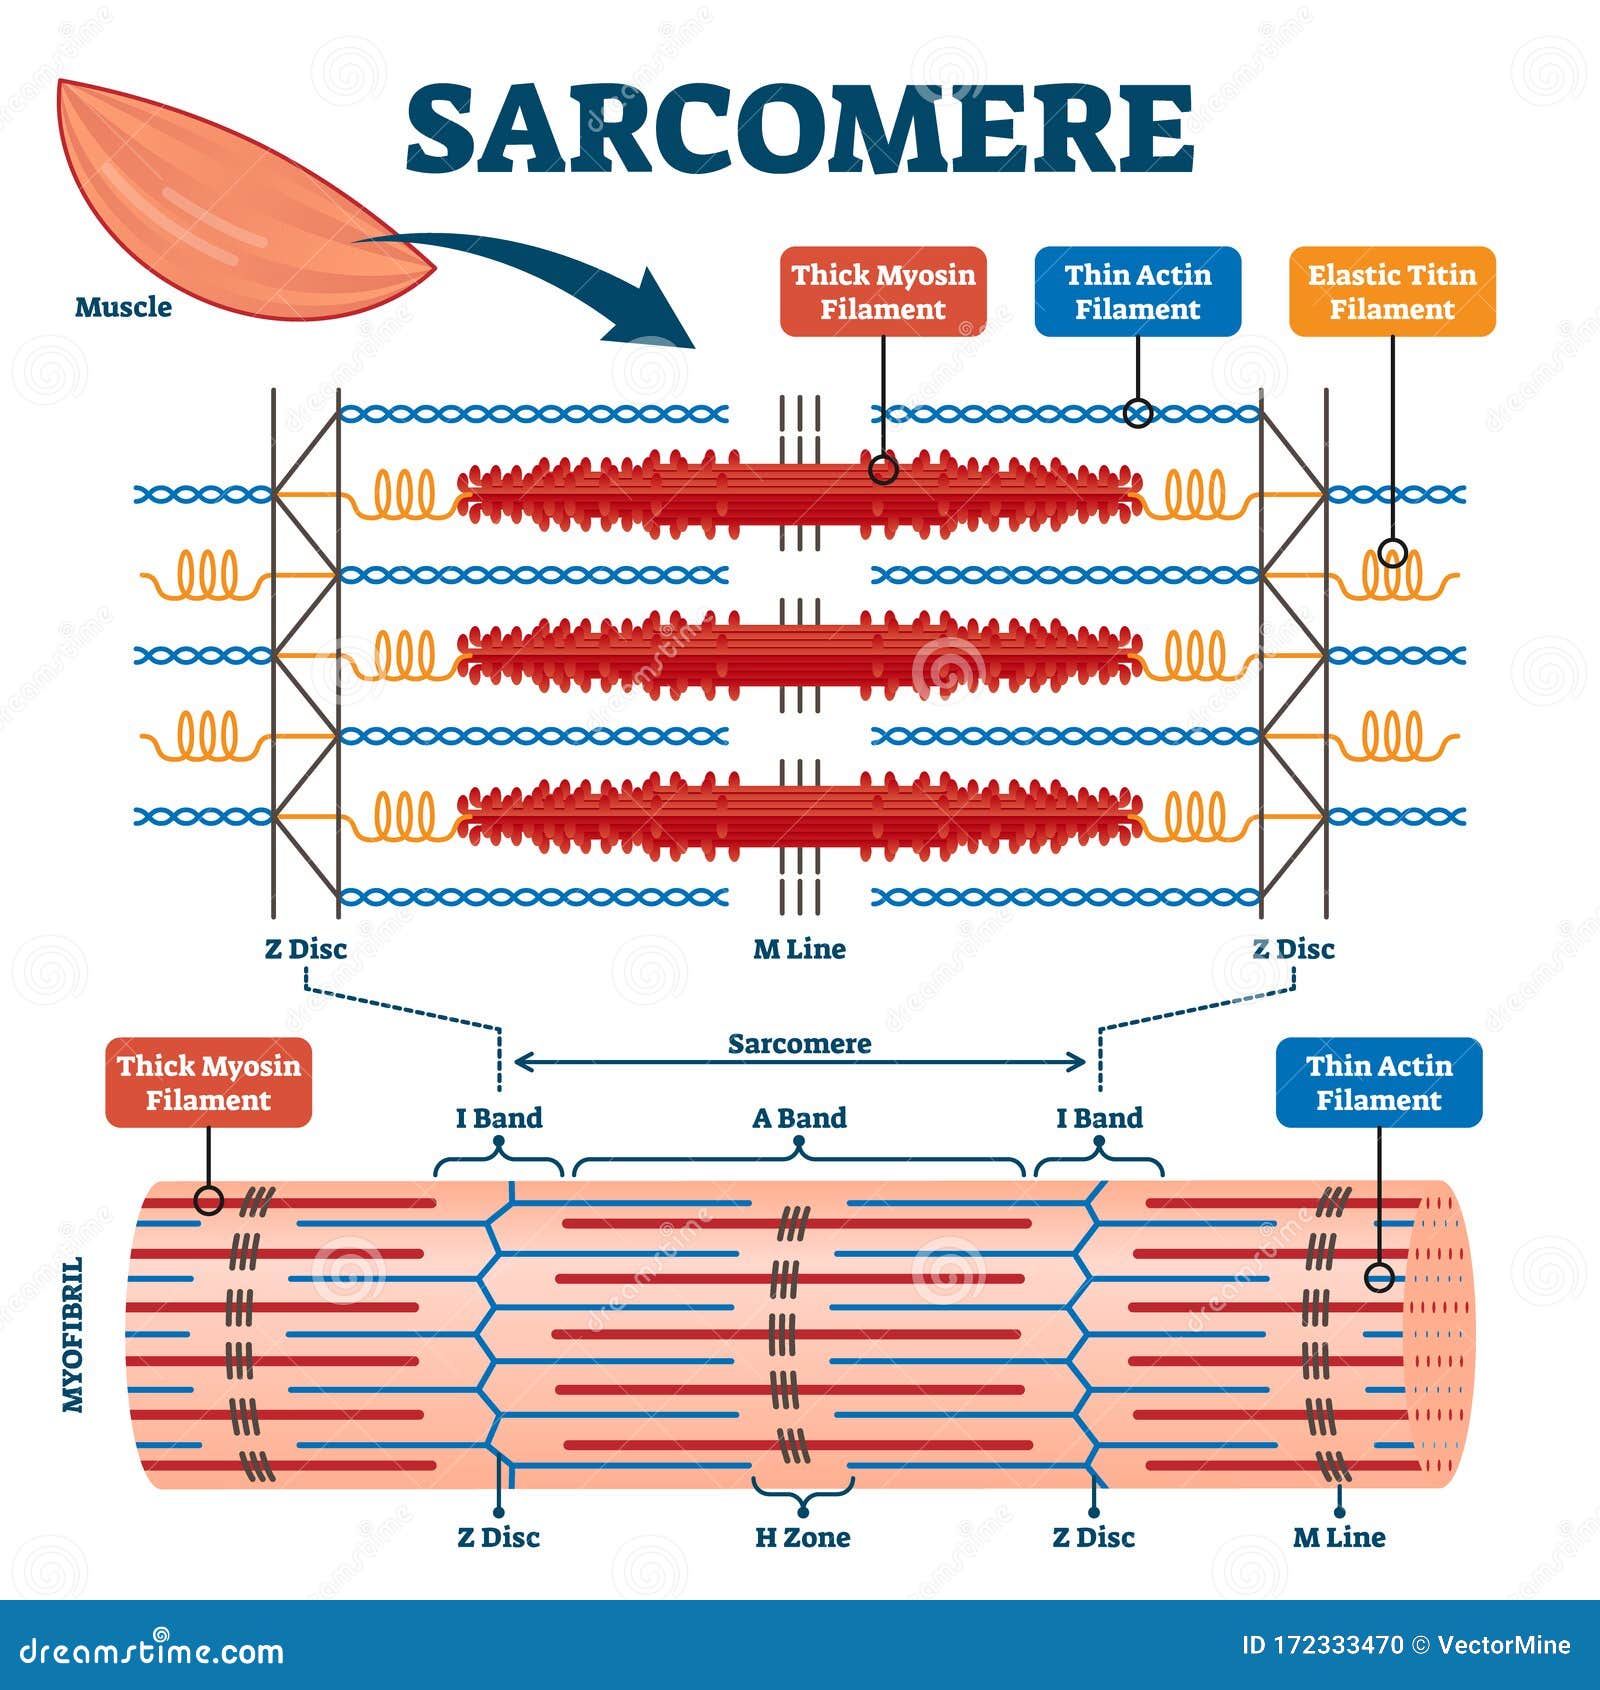
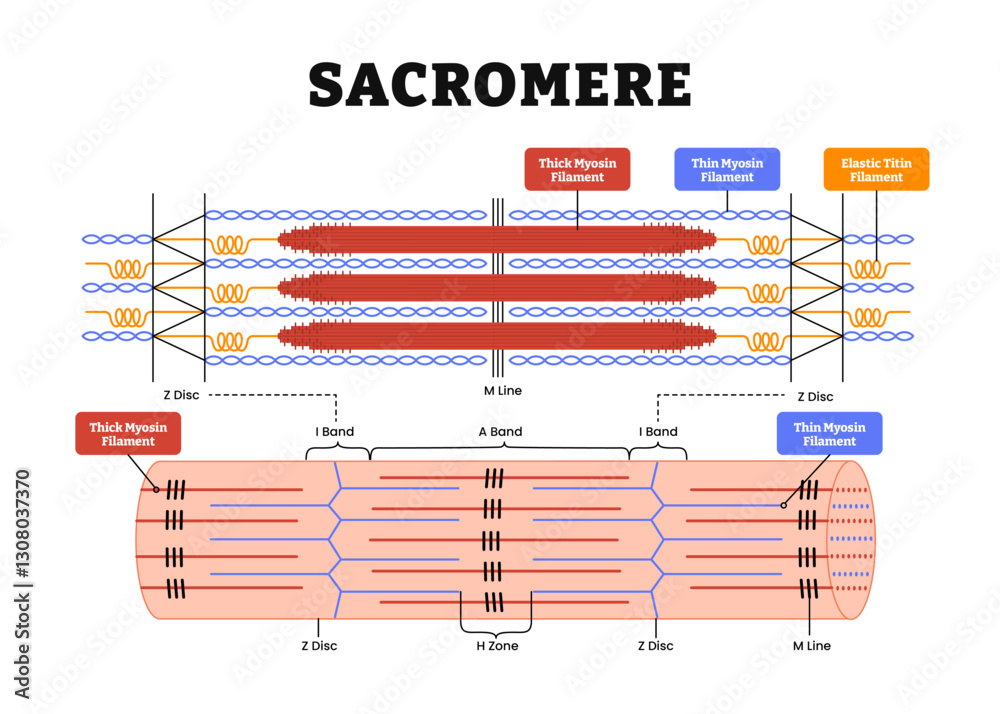
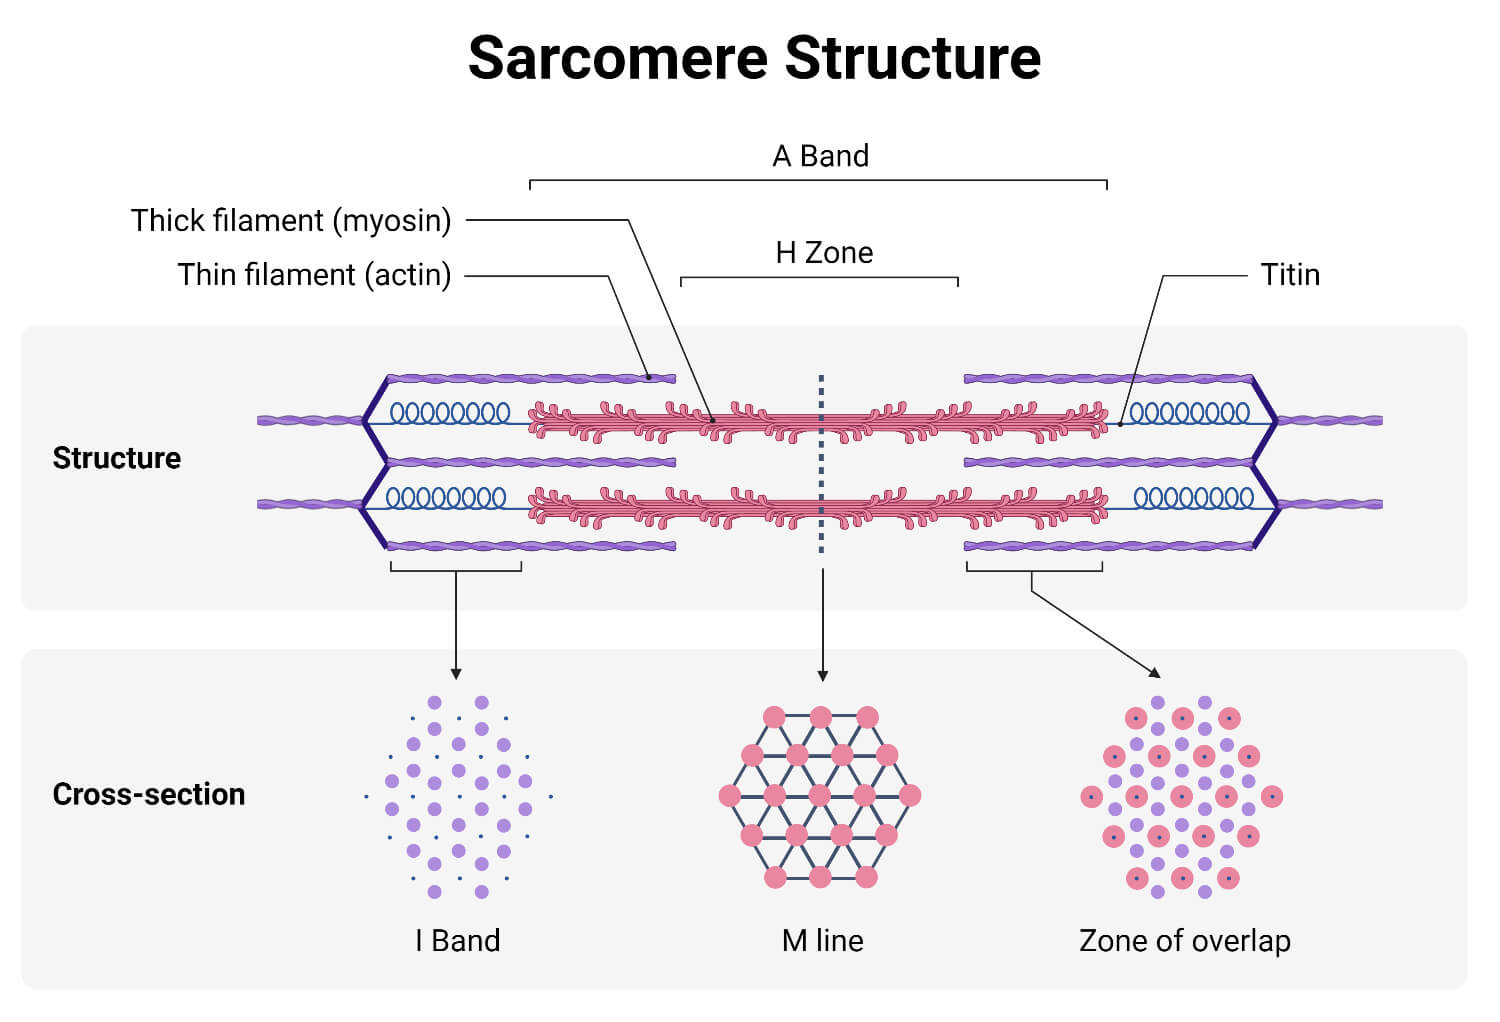
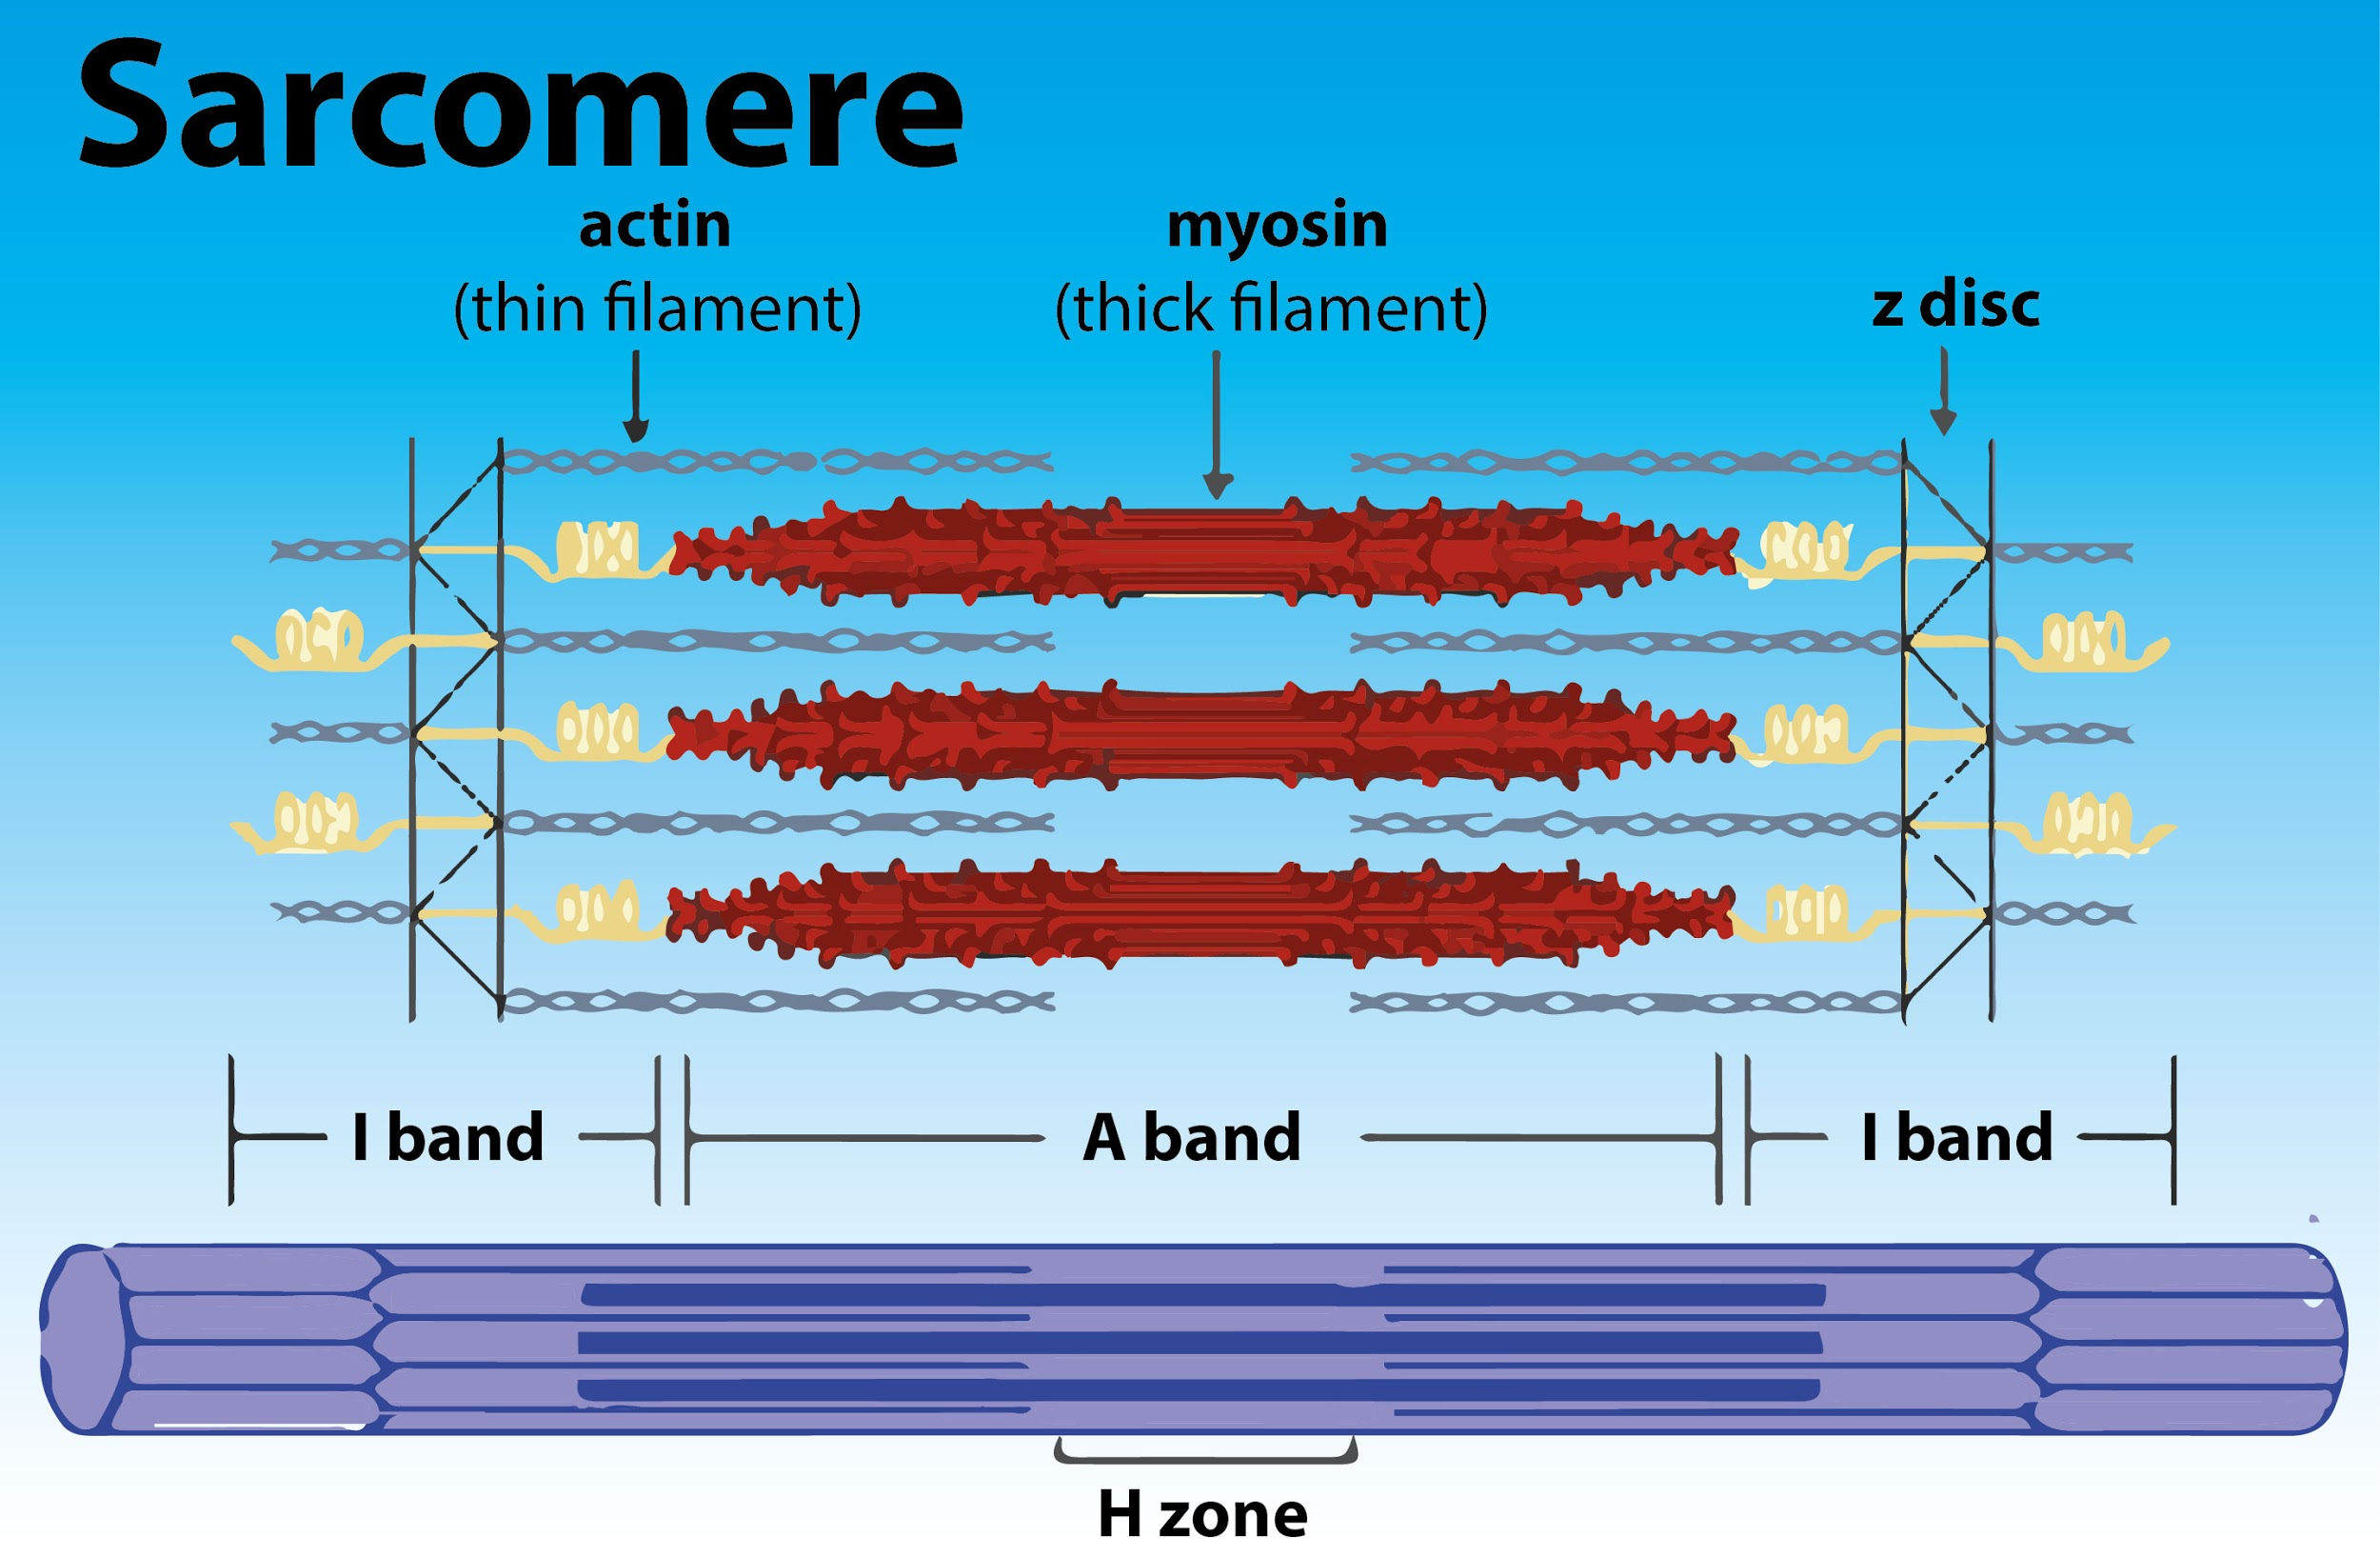
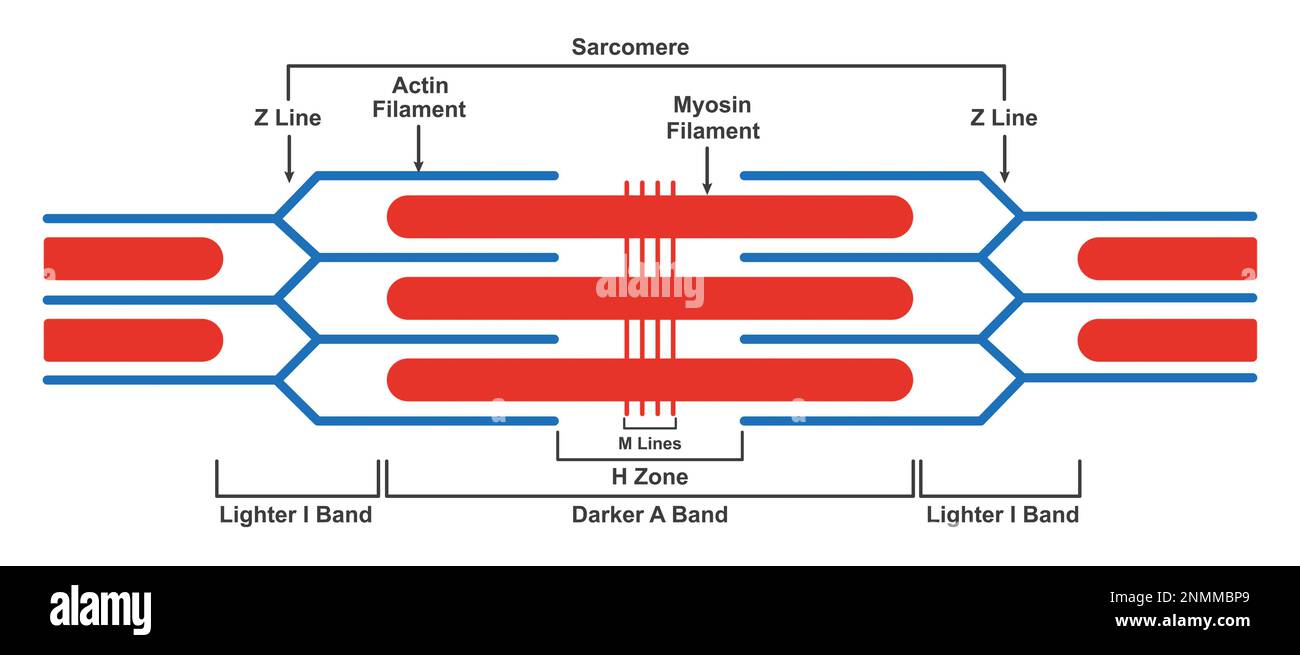
A sarcomere is a region between two Z-lines in a striated muscle fiber. That is the textbook definition, and it is accurate enough for most introductory courses. The Z-lines act as boundaries. Inside that space you find the arrangement of thin and thick filaments that generate force when calcium triggers the cross-bridge cycle. Myofibrils are made up of repeating sarcomeres lined end to end. When they shorten, the whole myofibril shortens. It is a straightforward mechanical system once you stop trying to visualize it as abstract geometry and treat it like a cable. The phrasing comes up in exam questions because instructors want you to know the anchors. Z-line to Z-line. That defines one sarcomere. The I-band sits on either side of the Z-line and contains only thin filaments. The A-band spans the full length of the thick filaments and overlaps with thin filaments in the outer regions. The H-zone is the central area of the A-band where thick filaments exist without thin filament overlap. The M-line runs down the middle of the H-zone and holds the thick filaments in place. If you are drawing this for a class, label every zone and band. Missing the distinction between H-zone and I-band is the most common mistake I see on first-year histology exams. I spent years looking at electron micrographs of skeletal muscle. One thing you learn quickly is that sarcomere length is not fixed. It changes with muscle stretch and with the phase of contraction. A resting sarcomere sits around 2.0 to 2.2 micrometers. When you stretch it beyond 3.5 micrometers, thin and thick filaments stop overlapping and force generation drops toward zero. When it is under 1.5 micrometers, thin filaments from opposite sides collide and interfere with each other. Maximum tension lands somewhere near 2.0 to 2.2 micrometers, which is why muscles in vivo operate in a relatively narrow range. This is why understanding sarcomere length matters if you are doing anything involving muscle mechanics or biomechanics modeling.
The Frank-Starling Relationship and Sarcomere Mechanics
The length-tension relationship is not just a diagram in a textbook. It is the reason cardiac output changes when venous return changes. In skeletal muscle, it explains why certain joint angles are stronger than others. I worked on a project a few years back where we were calibrating an in vitro muscle preparation and the force readings kept coming out lower than expected across the full range of lengths. We assumed a problem with the transducer or the myosin ATPase activity. It turned out the mounting was slightly compressing the muscle ends. That compression shortened the sarcomeres at the attachment points even though the middle of the fiber looked normal under the microscope. The fix was switching to sutures tied through small copper rings and letting the muscle hang freely in the bath. Force curves normalized after about ten minutes of rest. Here is something people usually miss. The overlap zone does not tell the whole story. Cross-bridge formation depends on myosin head availability, actin binding site exposure, and calcium concentration. A sarcomere can be at optimal length but still produce very little force if calcium handling is impaired. In pathological conditions like heart failure with preserved ejection fraction, the sarcomere itself might look fine under light microscopy. The issue is titin isoform switching, altered calcium sensitivity, and impaired sarcoplasmic reticulum function. You cannot diagnose those problems by looking at sarcomere dimensions alone. You need functional measurements.
Measuring Sarcomere Length in Real Experiments
If you are working in a lab and need to measure sarcomere length directly, high-speed video analysis of laser diffraction patterns is the standard approach. A single laser beam shone through a muscle fiber produces a diffraction pattern where the spacing between orders is inversely proportional to the sarcomere length. It gives you real-time readings during contraction, which static histology cannot do. I used this method for a study on fatigue in fast-twitch fibers. The alternative is measuring from fixed tissue sections, but fixation shrinks the sarcomeres by roughly 10 to 15 percent depending on the protocol. You have to correct for that shrinkage if you want physiologically relevant numbers. Titan is worth a separate mention because it changes how you think about passive tension. This giant elastic protein runs from the Z-line to the M-line and acts as a molecular spring. When the sarcomere stretches, titin unfolds and generates passive force. In cardiac muscle, titin dominates the passive stiffness profile. Different isoforms exist. The stiffer N2B isoform is more prevalent in adult ventricular myocardium, while the more compliant N2BA isoform appears in fetal tissue and in certain pathological states. If you are modeling cardiac mechanics without including titin, your passive diastolic curve will be wrong. I learned that the hard way when a colleague asked me to review a finite element model of left ventricular filling that ignored titin entirely. The model predicted pressures that were about 40 percent too low at end-diastolic volumes above 120 milliliters.
Get the Full Details
Common Misconceptions About Sarcomere Structure
The A-band does not shorten during contraction. That is a point that causes confusion. What shortens is the sarcomere length, the I-band width, and the H-zone width. The A-band stays the same because the thick filament length does not change. Only the degree of overlap changes. Students often draw the A-band shrinking and then lose points on practical exams for it. Another misconception is that all muscle types use the same sarcomere configuration. Cardiac sarcomeres have a different organizational precision compared to skeletal muscle. The intercalated discs in cardiac tissue create a different mechanical coupling. Smooth muscle does not have sarcomeres at all. It uses dense bodies and a different arrangement of actin and myosin. If you are studying smooth muscle contraction and apply skeletal sarcomere logic, you will get the wrong answer every time. Sarcomere research has moved beyond basic structure. Single-molecule optical tweezer experiments can now pull individual myosin heads and measure step size and force production. Cryo-EM has resolved atomic-level structures of the thick and thin filament regulatory complexes. These techniques have revealed details about how troponin and tropomyosin shift position during activation that electron microscopy alone could not show. The field is no longer satisfied with "the sliding filament model explains contraction." That explanation is correct but incomplete. The regulation of force, the energy cost per cross-bridge cycle, and the role of titin in active mechanics are active research areas with clinical relevance.
For anyone studying this, start with the basic zones and bands. Draw them from memory until you can do it without looking. Then move to the length-tension relationship and the calcium dependence of activation. After that, look into titin and the passive properties. If you skip titin, you are missing half the picture of what makes a sarcomere work as a mechanical unit.