Reading Dysrhythmias on the AACN Exam Is Different From Reading Them at 3 AM
The AACN exam doesn't test whether you can memorize rhythm strips. It tests whether you can distinguish life-threatening arrhythmias from benign variants under time pressure, and the questions are designed to trip people up with nearly identical-looking ECGs. I've proctored the exam prep sessions, and the failure point is almost always the same: candidates confuse atrial fibrillation with multifocal atrial tachycardia because they're looking at heart rate alone instead of the P wave morphology. Here's what actually matters for the identifying dysrhythmias portion. You need to work through each rhythm strip systematically. Don't glance and guess. The AACN questions will give you a rhythm strip with a two-lead format, and you have roughly 45 seconds per question. That means your pattern recognition needs to be automatic, not tentative.
Aacn Identifying Dysrhythmias Exam Answers
I'll walk through the breakdown strategy that works, then get into the edge cases that actually show up on the real exam. Start every rhythm strip with the same four checkpoints in this exact order: regularity, ventricular rate, P wave presence and morphology, and PR interval consistency. Most candidates skip regularity and jump straight to rate, which loses them points on irregular rhythms. The AACN loves throwing in sinus arrhythmia as a distractor, and if you mark it as abnormal because the rate fluctuates, you've fallen into the trap. Here's the practical method. When you see a strip, put your finger on the paper and slide it along to compare R-R intervals. If they're consistent, note regular. If they vary, note irregular. Then count the QRS complexes in a six-second strip and multiply by ten. That gives you ventricular rate. Then look for P waves before every QRS. If there's no discernible P wave and the baseline is fibrillatory, that's atrial fibrillation. If there are P waves but they change shape in different leads, think multifocal atrial tachycardia. The difference between those two is a single exam question that appears almost every cycle.
I ran into a specific problem once during a practice exam that mirrored the real thing. The question showed a narrow-complex tachycardia at 170 bpm with no visible P waves. My initial read was supraventricular tachycardia. But when I went back and checked the PR intervals more carefully, I noticed a subtle RP interval that was longer than the PR interval, and there were faint flutter waves visible in the inferior leads. The answer was atrial flutter with 2:1 conduction masquerading as SVT. The AACN exam gives you exactly this kind of strip where the diagnosis hinges on a detail most people miss on first pass. The workaround is simple: always look at leads II and V1 first, and if P waves aren't obvious, zoom in on the ST segment between QRS complexes. Flutter waves hide there. Let me share two things that most candidates get wrong about dysrhythmia identification. First, a wide QRS tachycardia is ventricular tachycardia until proven otherwise. This is non-negotiable on the AACN exam. You might see a case where the rhythm looks like SVT with aberrancy, and the clinically correct answer in real practice might require electrophysiology consultation. On the exam, wide QRS tachycardia is VT. There is no exception they test. I've seen candidates lose three to four points on a single exam by second-guessing this rule.
Get the Full Details

Second, Mobitz Type I (Wenckebach) and Mobitz Type II are distinguished by the pattern of PR interval behavior, not by whether the patient is symptomatic. The exam will describe a patient who is hypotensive and diaphoretic with a Mobitz Type I rhythm. That might make you lean toward choosing Mobitz Type II because it's considered more dangerous. It doesn't matter what the symptoms suggest. You diagnose based on the ECG morphology alone. Type I shows progressive PR lengthening until a beat drops. Type II shows a constant PR interval with random dropped beats. Memorize that distinction and stop letting clinical vignettes influence your rhythm diagnosis. Here's a quick reference for the rhythms that carry the most weight on this section of the exam: Normal sinus rhythm: rate 60 to 100, regular, one P wave before every QRS, PR interval 3 to 5 small squares. Anything outside this range gets labeled sinus tachycardia or sinus bradycardia, and the treatment implications are different enough that the exam tests them separately.
Atrial fibrillation: absolutely irregular rhythm, no P waves, chaotic baseline. The ventricular rate determines urgency. Controlled AFIB with a rate under 110 doesn't need acute intervention. Uncontrolled AFIB above 150 requires rate control, usually with a beta blocker or calcium channel blocker. Ventricular fibrillation: no organized electrical activity, no pulse, immediate defibrillation. The exam sometimes disguises this as coarse VF to see if you'll hesitate. Coarse VF is still VF. Shock it. Third-degree heart block: complete AV dissociation. P waves and QRS complexes march to entirely different drums. The atrial rate is usually normal, and the ventricular escape rate is 30 to 40 if the block is at the AV node or 20 to 30 if it's infrahisian. The exam tests this distinction because transcutaneous pacing is the bridge to treatment, but the underlying cause determines whether you need atropine first or not.
I should be straightforward about where this approach breaks down. The AACN identifying dysrhythmias questions assume you're working with clean, well-prepared ECG strips. In practice, you'll encounter artifact, lead misplacement, and patients with baseline bundle branch blocks that make every tachycardia look like VT even when it isn't. The exam doesn't test those messy scenarios directly, but if you're using these answers to prepare for actual clinical work, you'll hit gaps. For real patient care, consult with cardiology and use all twelve leads, not just the rhythm strips the exam provides. Another limitation worth noting: the AACN exam tends to favor classic presentations. Real dysrhythmias are often hybrid patterns. Junctional rhythms with retrograde P waves. Atrial tachycardias with variable block. The exam strips are usually textbook examples, which means your clinical skills might outpace what the test measures. That's fine for passing, but don't mistake exam competence for bedside competence. If you want additional practice materials, the AACN official website provides certification study guides and sample questions. Third-party resources exist, but the official material aligns closest with the actual exam format. I'd recommend doing at least two hundred rhythm identification questions before test day, timed conditions included. The speed component is what catches people off guard, not the difficulty of the rhythms themselves.
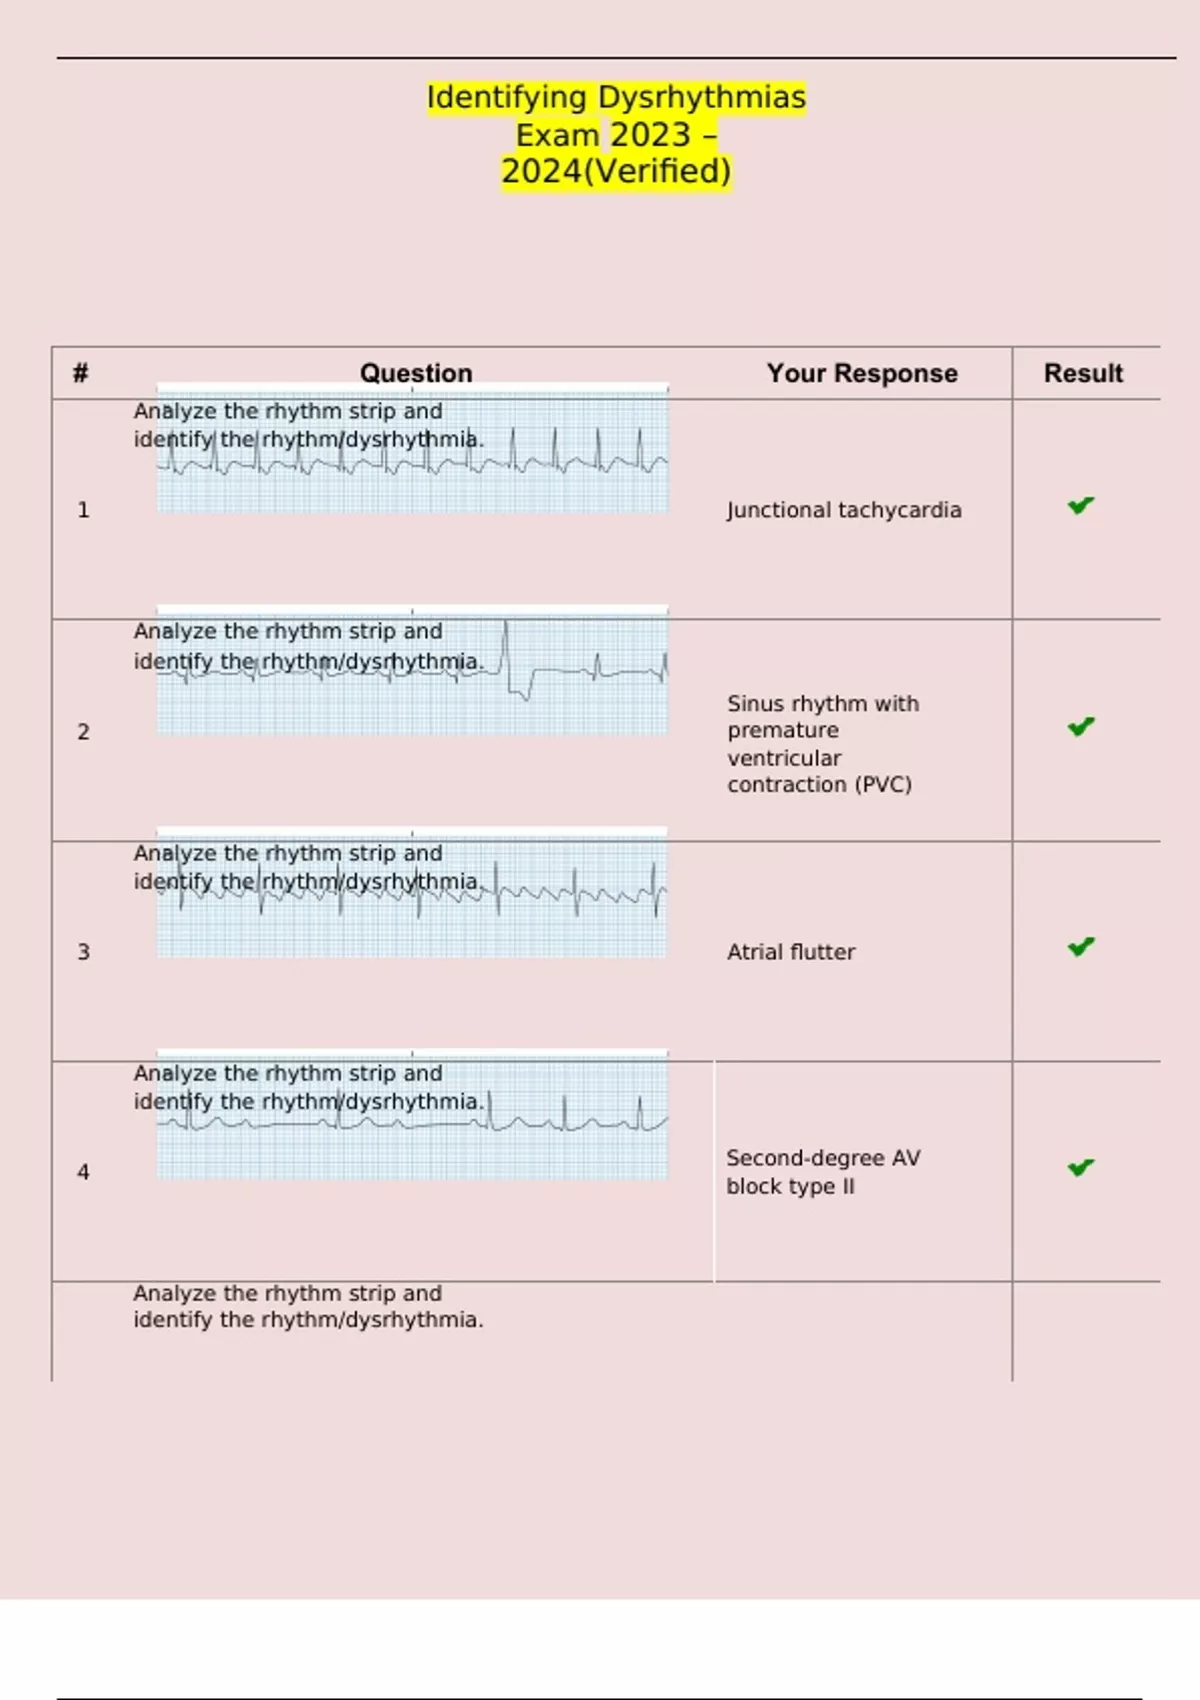
The bottom line: master the four-step systematic approach, stop letting symptoms distract you from the ECG morphology, treat wide QRS tachycardia as VT every time, and practice until the patterns are instant. The exam rewards precision and punishes hesitation.