Getting Started With Early ABA Intervention
A two-year-old is not a small adult who happens to be quieter. They do not sit still for table work, they do not understand "good job," and traditional ABA programs designed for older children will fail within a week if you try to force them. I learned that the hard way with my first case. The child wouldn't touch the picture cards, wouldn't make eye contact, and would scream whenever the therapist tried to do discrete trial training at a table. So we stopped doing that entirely and built the program around what he was actually doing—throwing blocks, spinning wheels, and grabbing things. The core of ABA at this age is not drilling skills. It is establishing communication as a functional tool while building tolerance for structured interaction. Verbal Behavior methodology works better here than classic DTT because toddlers learn language through motivation, not repetition. You embed teaching into activities the child already wants to do, then gradually add demands. Mand training comes first. If a child cannot request a desired item or action, every moment of frustration becomes a behavioral problem waiting to happen. Here is what the actual session structure looks like in practice. You start with whatever the child is drawn to—an iPad, a bubble machine, a stack of cups. You place it just out of reach or keep it available only through a clear request. The child reaches for it. You wait three seconds. If they vocalize any sound toward it, you immediately give it and label it. "Ball. You got the ball." You do this twenty times in a row before moving anywhere else. The thirty-second rule applies: if the child has not produced an approximating response within thirty seconds, you prompt immediately rather than letting the session stall into extinction bursts.
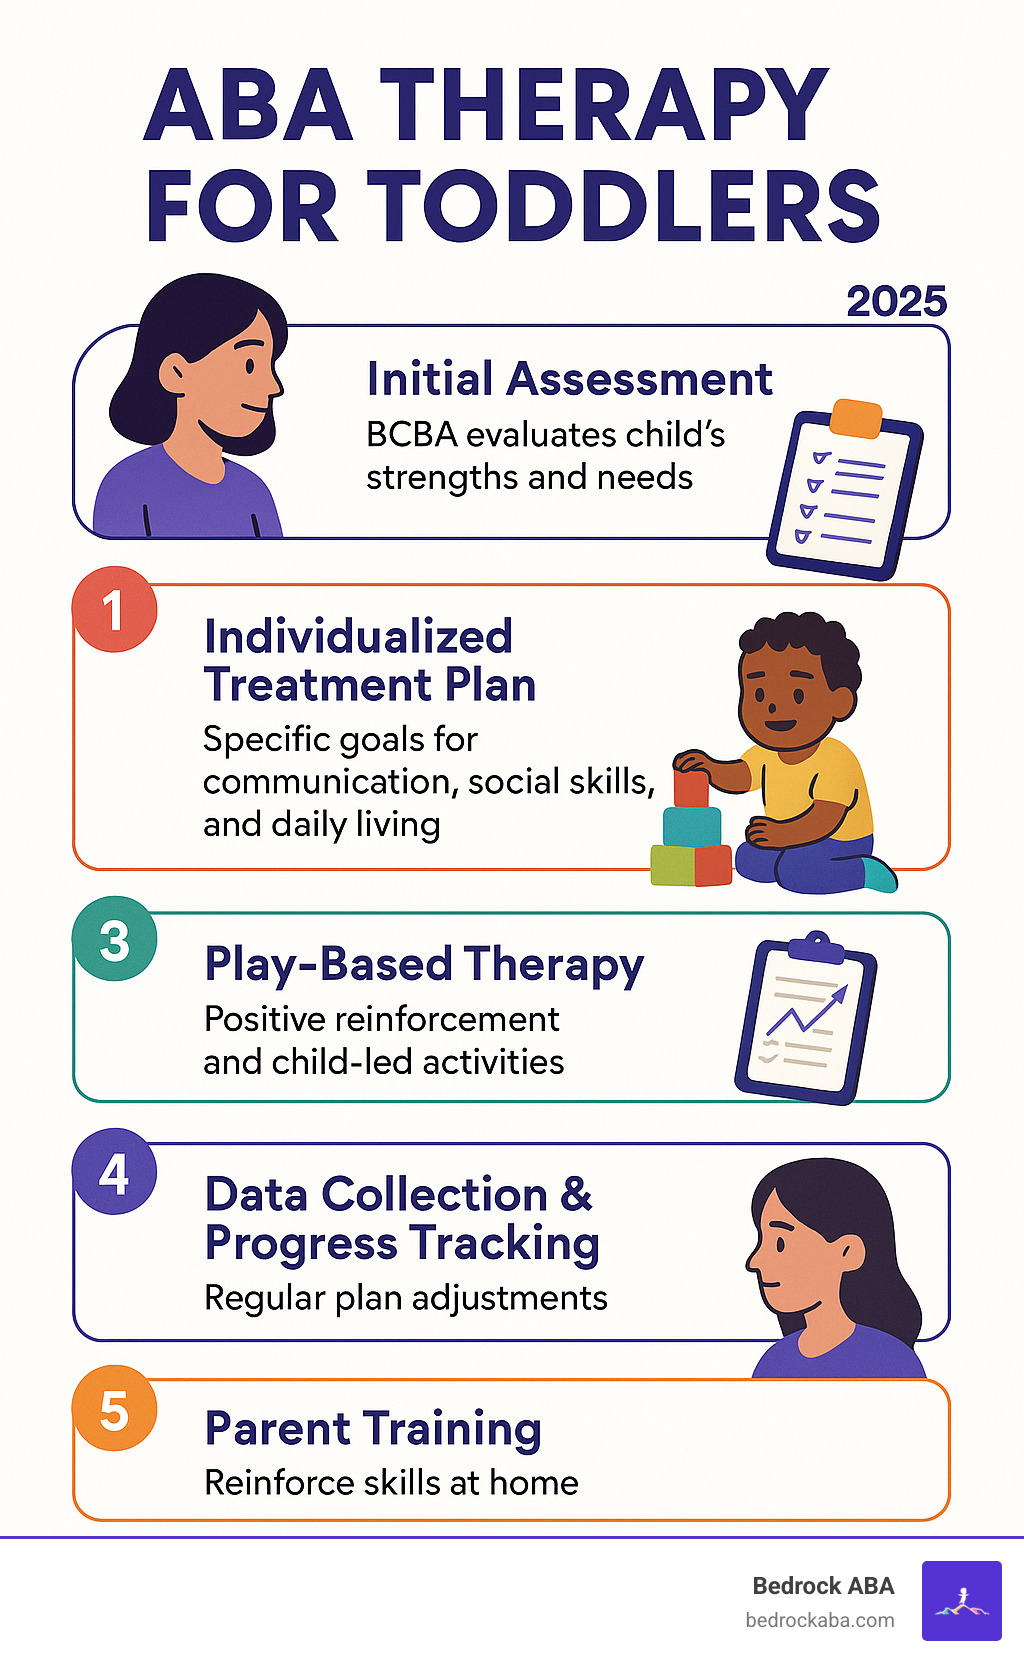
Parent involvement changes everything at this age. Two hours of weekly therapy produces negligible results compared to twenty minutes of parent-implemented trials scattered through the day. I have seen parents who committed to recording video of their natural interactions and reviewing them with the BCBA weekly make more progress in six weeks than children who had five hours of clinic time per week with disengaged caregivers. The difference is not intensity. It is consistency of reinforcement across environments. One counterintuitive thing nobody tells you upfront: the most disruptive behaviors during early ABA often come from the program itself, not from the child's baseline. When you start mand training and remove access to preferred items until a response occurs, you will see an increase in tantrums before you see a decrease. This is called an extinction burst and it typically lasts between four and fourteen days. I have watched parents cancel programs during this phase because they thought they were making things worse. They were not. The data will show you. Record frequency, duration, and intensity daily. If the trend is flat after ten sessions, modify the program. If the trend is improving even slightly, stay the course. A specific edge case I ran into involved a child who had severe oral sensory seeking behavior. He would mouth everything—toy edges, the therapist's pen, his own fingers—and every time we tried to shape a verbal mand, he would simply mouthing the object instead of vocalizing. Standard prompt hierarchies did not work because the oral stimulation was reinforcing the incorrect response. What finally broke the loop was pairing a brief oral motor task before each trial. We had him take three deep breaths through a straw and blow it sideways, which interrupted the mouthing pattern and put his oral system in a different state. Then we presented the mand opportunity. The mouthing dropped by roughly eighty percent within six sessions and vocal approximations increased correspondingly. I am not saying this works for every child with oral seeking, but it is worth considering when standard procedures stall.
Screening and assessment tools matter less than people think at this age. The VB-MAPP and ABLLS-R are useful reference points but they assume a level of compliance and cognitive organization that many two-year-olds simply do not have yet. I rely more on naturalistic observation during the first three sessions than on any standardized instrument. Watching how a child handles transitions, how quickly they recover from minor frustrations, and what specifically reinforces their behavior tells you more about where to start than a score. There are real limitations to acknowledge. ABA for two-year-olds does not work well when the child has significant motor delays that prevent clear mands, when there is untreated medical issues like ear infections or reflux driving irritability, or when the family cannot commit to daily home practice. In those scenarios, you will burn through three months of program development before realizing the foundation is cracked. Address the medical issues first. Work with a speech-language pathologist on pre-vocalic skills simultaneously. Get the parents trained on basic reinforcement principles before launching into skill acquisition. Another limitation is the window itself. Two is young enough that neuroplasticity is high, but old enough that some behavioral patterns are already entrenched. A child who has spent eighteen months without any structured intervention will have a different profile than one who started at twelve months. The earlier the start, the more naturalistic the approach should be. After eighteen months of age, you can introduce slightly more structured teaching because the child has had more time to develop maladaptive response patterns that need deliberate replacement.
Get the Full Details

Data collection at this age is notoriously difficult because sessions are short and the child moves constantly. Keep it simple. Use a tally sheet divided into fifteen-minute blocks. Mark correct responses, prompted responses, and refusals. That is all you need in the beginning. Once you have baseline data across five sessions, you can add more sophisticated measurement. Most therapists overcomplicate data collection early on and end up spending more time writing than teaching. If you are a parent reading this and considering ABA for a two-year-old, look for a provider who emphasizes natural environment teaching over table-based drill work. Ask about their approach to mand training specifically. Ask how they involve parents in daily sessions. Ask what they do when a child escalates during the first two weeks. A competent provider will have concrete answers to all three questions. The goal at two years old is not to produce a child who follows instructions perfectly. It is to produce a child who communicates needs before resorting to behavior, who can tolerate brief structured interactions, and who has learned that adult attention is more reliably accessed through appropriate means than through screaming. Everything else builds on top of that foundation.