Reading an upright abdominal film doesn't require any special talent, just a repeatable system
I still see residents and even some junior radiologists scanning an AXR and missing the obvious because they're looking for pathology before they've actually confirmed the anatomy. The sequence matters more than you think. Start with the basics of what should be there, then move to what shouldn't. First, confirm you're looking at the right projection. An upright AXR shows the diaphragm, the costophrenic angles, the lumbar spine, and the psoas shadows. If the film is supine, you're getting a different picture entirely — fluid levels won't settle the same way, and bowel gas distribution looks completely different. I had a case once where a reported pneumoperitoneum turned out to be Chilaiditi syndrome because nobody checked whether the gas was actually under the diaphragm or between the liver and colon. A lateral decubitus view cleared it up in five minutes.
Abdomen X Ray Anatomy breakdown
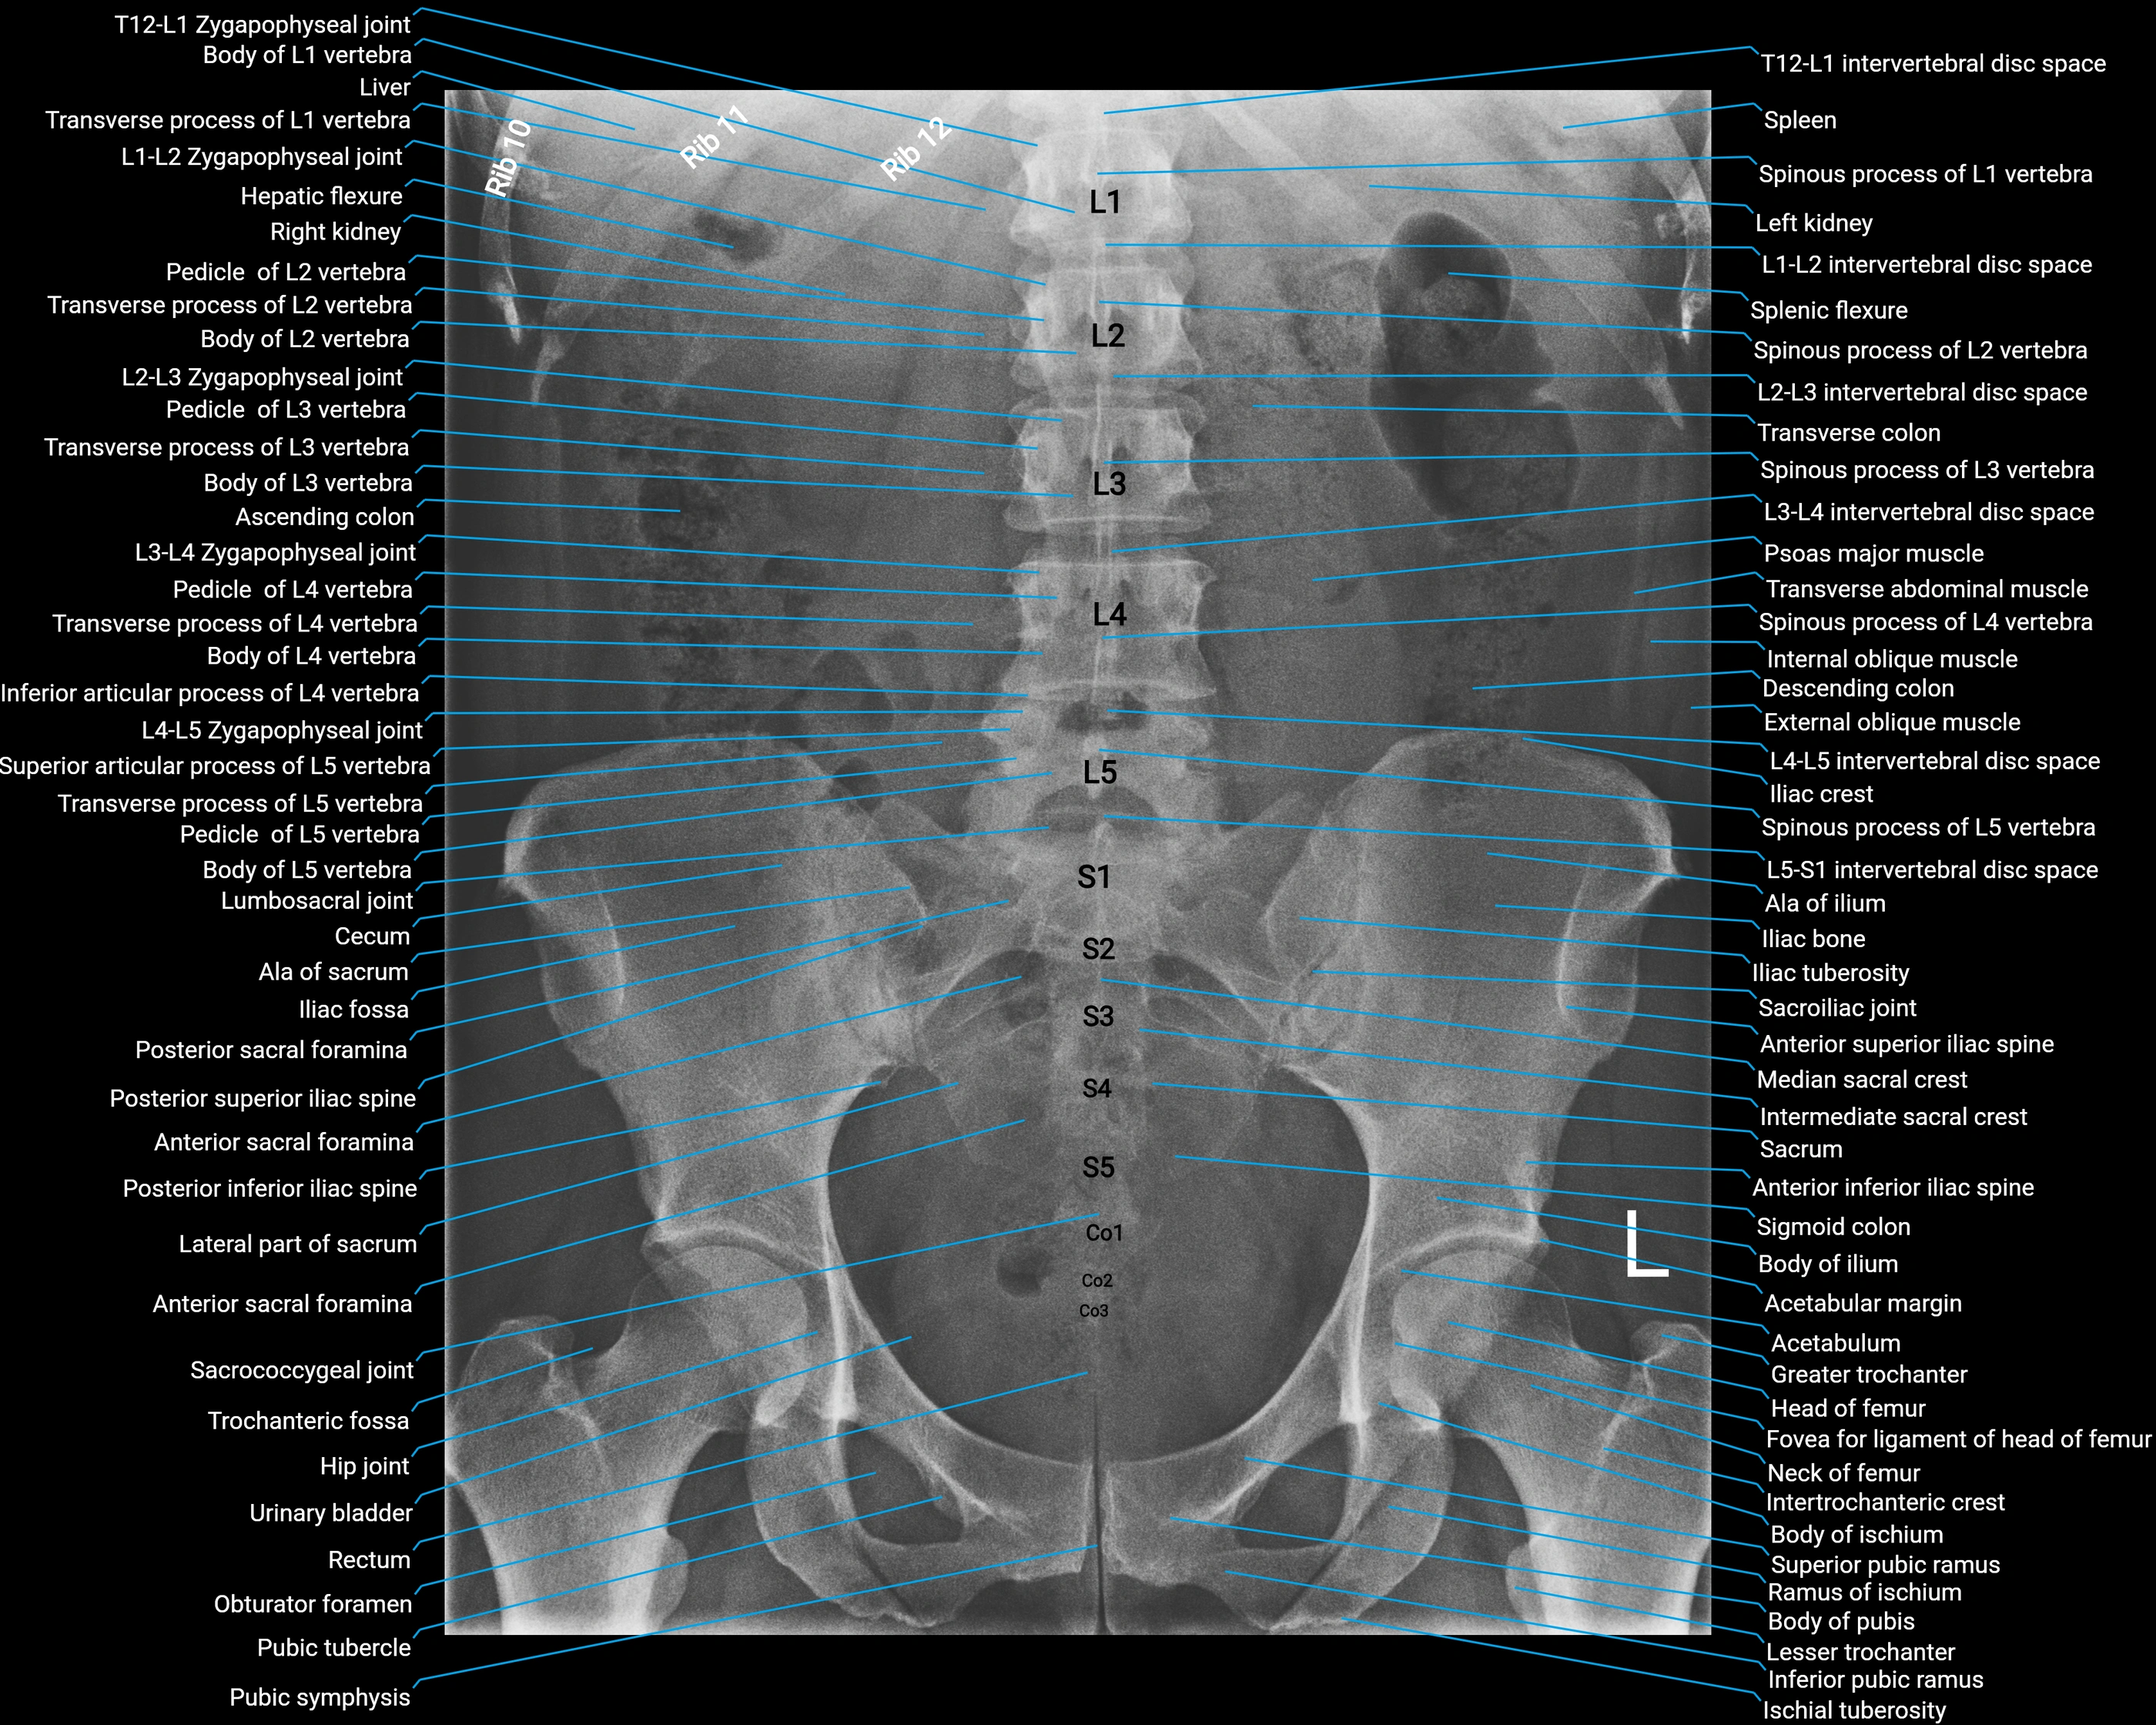
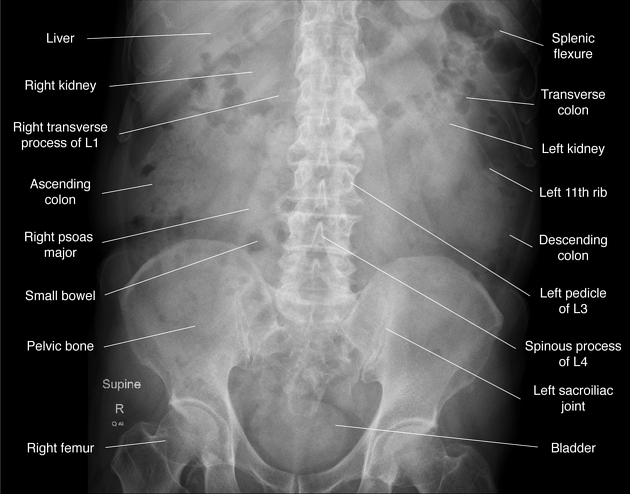
The liver shadow sits on the right side below the diaphragm. It should be a homogeneous soft tissue density. If you see gas within it, that's either emphysematous pyelonephritis tracking up, a hepatobiliary drain, or a fistula. The spleen is on the left and usually smaller. The stomach bubble is visible under the left hemidiaphragm — if it's absent, consider gastric outlet obstruction or prior gastrectomy. The psoas margins are your road map. Both should be visible unless there's retroperitoneal pathology obscuring them. A loss of the right psoas shadow is one of the earliest signs of an appendix abscess, and it often appears before the patient even has a fever. The kidneys sit on either side of the spine. You can sometimes see their outlines, and occasionally a renal calculus will show up as a small dense opacity. Not all stones are radio-opaque though — uric acid stones are lucent and will absolutely hide from you on a plain film. Bowel gas patterns deserve actual attention. The colon frames the abdomen. The transverse colon crosses mid-abdomen. The ascending and descending colon run vertically on each side. The cecum sits in the right lower quadrant and is normally the widest part of the colon. If the cecum is dilated past twelve centimeters, you're in surgical territory regardless of what the rest of the film shows. Small bowel is central and has valvulae conniventes that cross the full width of the lumen. Those are your distinguishing feature from colon, which has haustra that only partially cross.
The spine is part of the exam too. Look for degenerative changes, compression fractures, or unusual densities. I spotted a vertebral body collapse on an AXR that was ordered for bowel obstruction. The surgeon wasn't happy I'd diverted the conversation, but the patient needed a CT of the spine, not just the abdomen. Free air is the thing everyone wants to see and everyone misses. On an upright film it collects under the diaphragm as a thin crescentic lucency. The key detail is that it's more obvious on the right side because the liver provides a soft tissue contrast backdrop. On the left, the stomach bubble can be confused with subdiaphragmatic air. If you're unsure, get a left lateral decubitus view and watch for air rising along the liver edge instead. The soft tissues are easy to overlook. Surgical clips from prior operations will show up as tiny metallic densities. Calculi in the urinary tract appear at various points along the ureteric course. And bowel wall calcification, while rare, is a real finding that points to things like chronic mesenteric ischemia or prior tuberculosis.
Get the Full Details
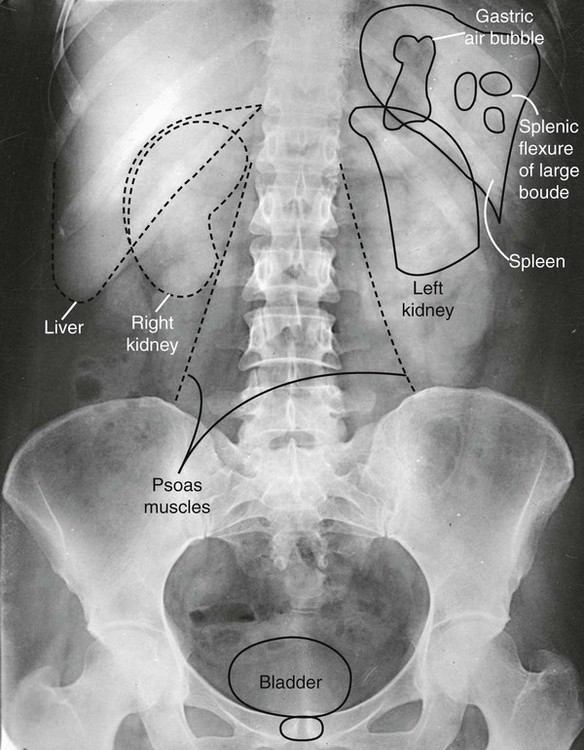
The biggest limitation of a plain abdominal X-ray is that it's essentially a projection of overlapping structures. Everything gets flattened into two dimensions. A thirty-millimeter stone sitting directly on top of a vertebral body is going to be much harder to spot than one projecting over soft tissue. Contrast studies or CT solve that problem, and they should be the next step whenever the AXR is equivocal or the clinical picture doesn't match the film. A normal AXR in an adult typically shows a few pockets of gas in the colon and perhaps a small amount in the stomach. The rest of the abdomen should be relatively gas-free. When you see extensive small bowel dilation with multiple air-fluid levels on an upright film, that's a mechanical obstruction until proven otherwise. The transition point is where the dilated loops meet the collapsed distal bowel, and it's often visible as a abrupt change in caliber. I keep a mental checklist borrowed from my attending back in residency: diaphragm, lungs bases, bones, soft tissues, gas pattern, free air, calcifications. That covers roughly ninety-five percent of what you need without spending more than two minutes per film. The remaining five percent is the stuff that shows up on follow-up imaging and makes you wish you'd been more systematic the first time.