The timing of when you start moving your core matters more than the actual movements
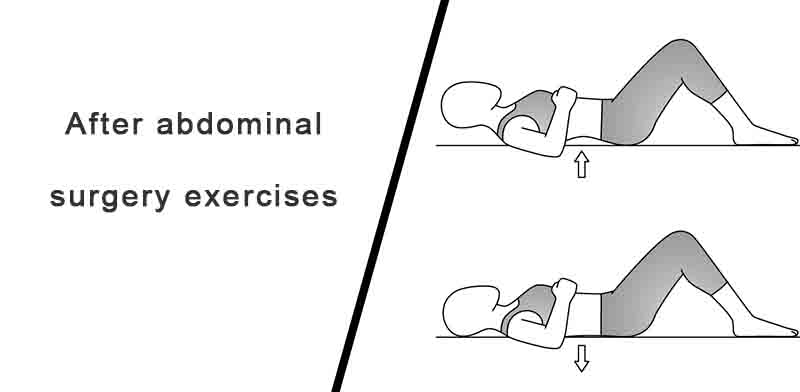
I spend a lot of time reading recovery questions on surgical forums, and almost everyone gets the order wrong. They want to jump into crunches or planks within weeks because they see influencers doing hollow bodies six weeks post-op. That's not how this works. The fascia needs time to actually regain tensile strength, not just close up. The general timeline I see in clinical protocols looks roughly like this. Weeks zero through two after surgery are complete rest for the abdominal wall. You're not doing anything intentional. Walking is encouraged, but only because it prevents blood clots and helps bowel function. Any exercise that loads the core directly should be treated as off-limits during this window, period. Between weeks two and four you introduce diaphragmatic breathing and pelvic floor engagement. This is the foundation. Most people skip straight past this phase because it feels useless, but it's actually where you rebuild the connection between your breath and your deep core stabilizers. Without that reconnection, you're going to compensate with your hip flexors and lower back, which is exactly what causes those weird pulling sensations a few months later.
Abdominal Exercises After Surgery: A Practical Progression
Weeks four through six are where you begin actual core work, but I mean the lightest possible loading. Dead bugs with no leg extension, heel taps, and bird dogs. The range of motion should be so small it barely feels like work. If you're sweating from it, you're doing too much. The incision site and the internal suture line are still gaining maybe ten to fifteen percent of their final tensile strength at this point. I've seen patients who pushed through into leg lowers at week five and ended up with a small seroma at the operative site. Once you get a seroma, you're looking at another two weeks of setbacks minimum. Weeks six through eight allow you to add in more challenging variations. You can extend the dead bug legs fully. You can try the hollow hold, but keep it to five to ten second holds, three sets at most. Side planks on the knees are reasonable if there's no pain. The key metric here is whether you feel any pulling or tension at the incision line. If you do, you go back to the previous week's exercises. That happens more often than people want to admit, especially if your surgery involved a longer incision or if they entered the rectus sheath rather than working between the muscles. By weeks eight through twelve you can start introducing actual resistance. Pallof presses, farmer's carries, light cable woodchops. Even here, you're using barely any weight. I'm talking about the lightest setting on the cable machine or two-liter water bottles. The goal isn't hypertrophy at this stage. It's proprioception and gradual load tolerance. Your nervous system needs to relearn that it's safe to fire your core under load again.
Full intensity training typically doesn't happen before month four, and even then you're rebuilding from scratch. A lot of people assume that by month three they're back to normal. They're not. A study I came across in theJournal of the American College of Surgeons found that abdominal wall strength only reaches about sixty-five to seventy percent of baseline at twelve weeks post-op after open procedures. Laparoscopic cases tend to recover faster, closer to eighty percent by then, but the variability between individuals is huge. It depends on your age, whether you smoke, your pre-operative fitness level, and the type of surgery you had. Elective hernia repair is different from a Whipple procedure. Don't compare your recovery to someone who had a lap gallbladder. Here's something that surprised me when I was working through my own recovery from abdominal surgery a few years back. The exercise that felt the most threatening turned out to be completely harmless, and the one I felt fine doing turned out to cause problems. It was the bird dog. I avoided it like crazy because extending one arm and the opposite leg seemed like it would torque my midsection. But it was actually the dead bug that caused issues. I extended my leg too far and felt a sharp, pinching sensation along my scar. I ignored it for a couple days thinking it would pass. It didn't. Ended up having to back all the way down to just diaphragmatic breathing for a week before I could restart. The pinching sensation is a real warning sign. Don't push through it. Another thing that comes up a lot is the difference between open and laparoscopic approaches. Open surgery, whether it's for hernia repair, hysterectomy, or bowel resection, involves cutting through layers of abdominal wall. The healing timeline is measured in months, not weeks. Laparoscopic surgery involves port sites that go through the muscles but don't split them the same way. Recovery is faster, but the internal fascial closure at each port site is what matters. A poorly closed port site, especially one larger than twelve millimeters, can develop a small hernia even with light exercise. If your surgeon didn't close the fascia at the port sites, that risk goes up significantly. Worth asking about if you're unsure.
Get the Full Details
Resistance bands are a reasonable tool once you're past the early stages, usually around week eight or later. They provide variable resistance that's easier on the healing tissues than free weights. The problem is that most rehab guides don't emphasize band control enough. If you're doing a Pallof press and the band pulls you off balance, you're not ready for that exercise yet. The band shouldn't be stronger than your ability to resist its force through the entire range of motion. Start with the lightest band and treat it as a mediating tool, not a progressive load. The biggest mistake I see people make is trying to preserve their old workout intensity. They want to maintain their deadlift numbers or their plank records. That mindset is counterproductive. You're not preserving anything at this stage. You're rebuilding from a degraded baseline. Your core endurance before surgery is irrelevant. What matters is where you are now. Approach this like you're a complete beginner. It's demoralizing the first few weeks, but it gets better. Most people are doing reasonable bodyweight work by month three and light loading by month four. Returning to heavy compound lifts usually takes six to twelve months depending on the procedure. There are scenarios where this whole approach doesn't apply cleanly. If you had surgery that involved a midline incision above the belly button, the transverse abdominis and rectus muscles were likely separated or retracted. The healing mechanics are different and the timeline extends further out. If you received mesh during a hernia repair, the integration phase takes additional months before you can safely load the area through dynamic movement. The mesh itself doesn't weaken, but the tissue around it does, and that tissue is what you're loading when you do exercises like the hollow hold or dead bug. Patience here isn't abstract advice. It's a mechanical requirement.
If you're past the twelve-week mark and still feeling pain or instability with basic movements, stop and get it checked. That's not normal recovery behavior. Scar tissue adhesions can form and limit your range of motion, and in some cases physical therapy focused on scar mobilization helps. Other times the issue is a recurrence or a different complication altogether. There's no substitute for an actual examination at that point.