What You Need to Know About Left Upper Quadrant Discomfort
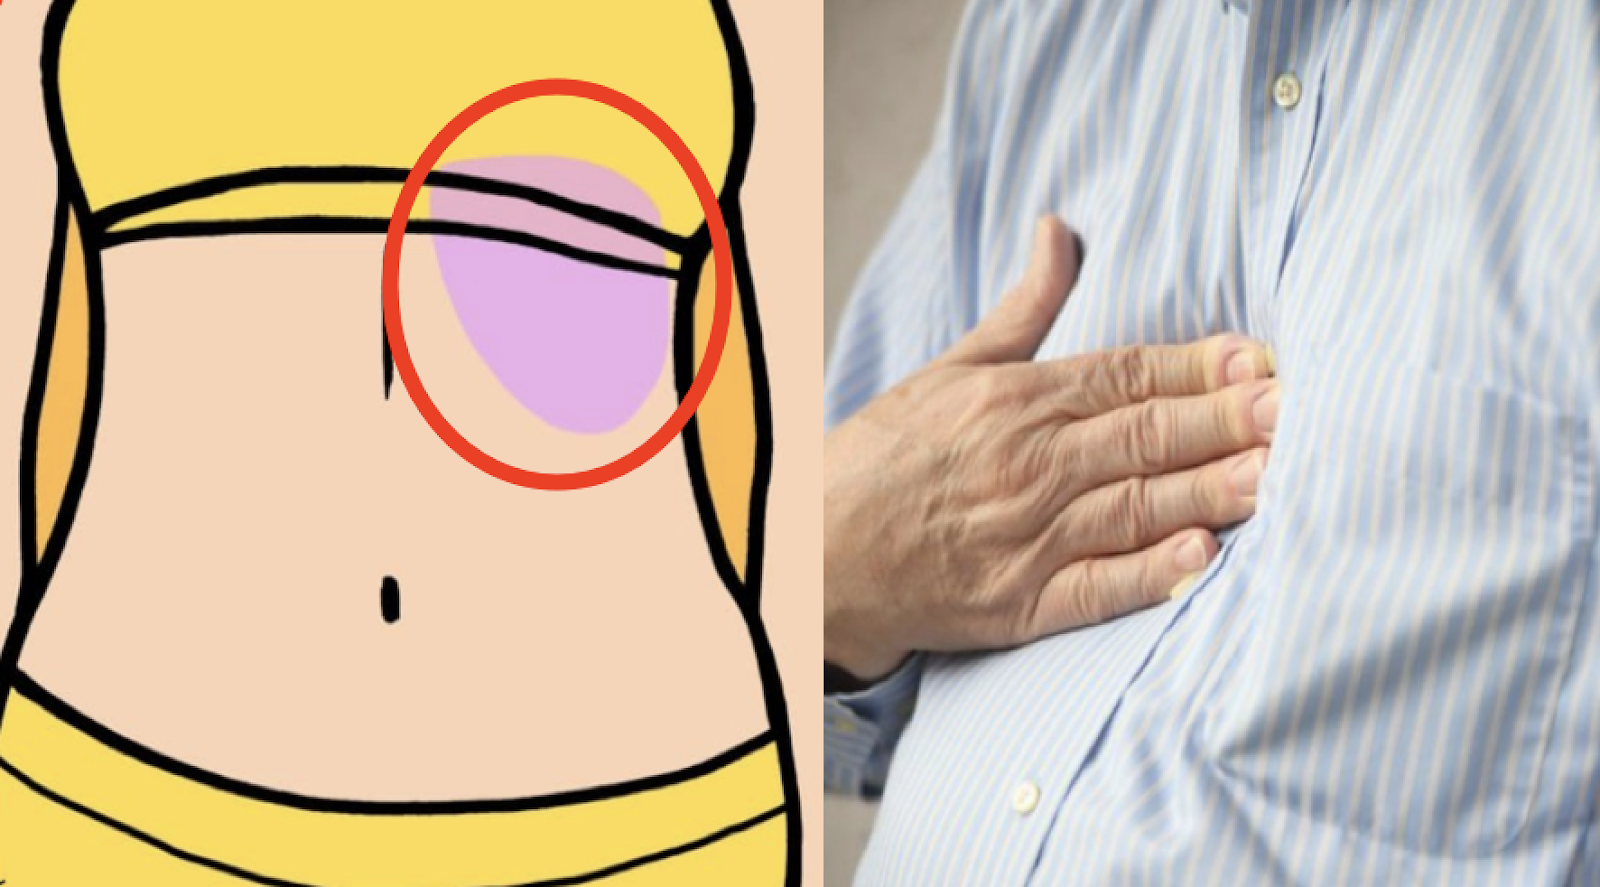
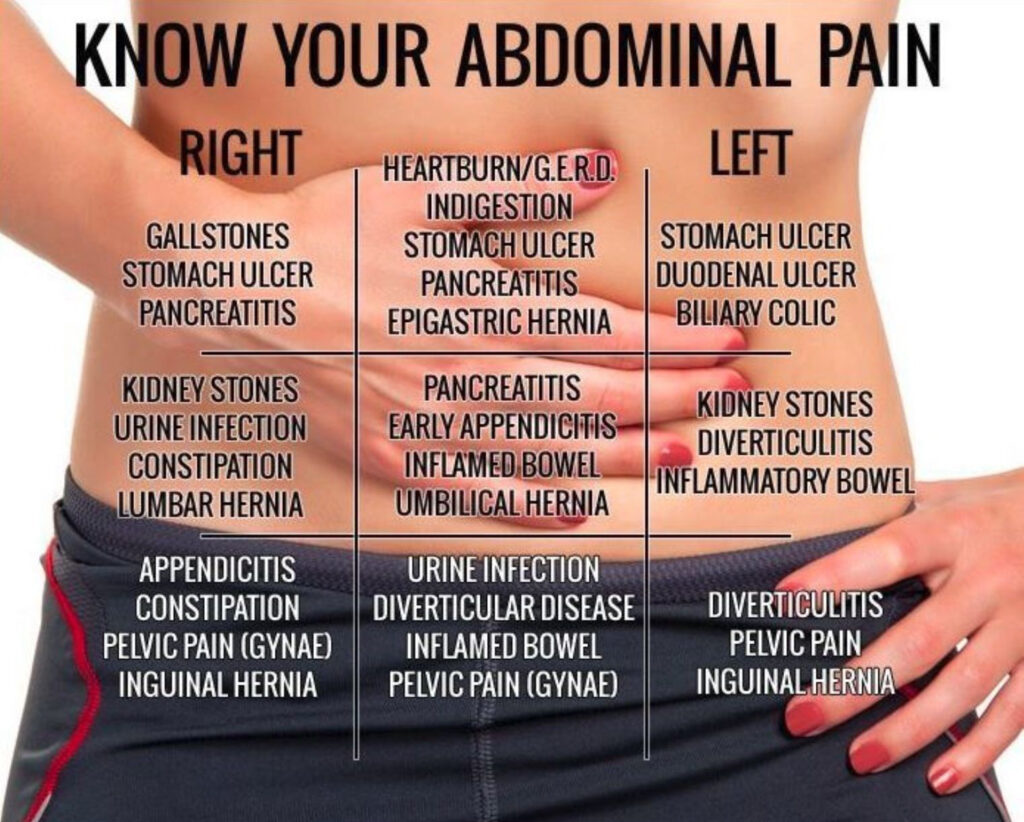
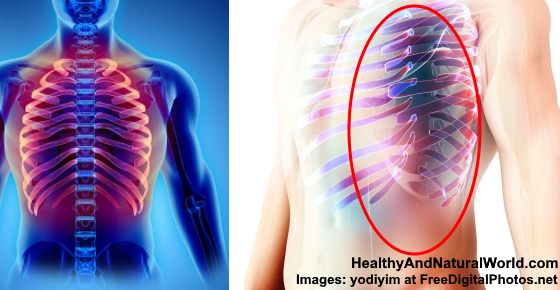
I see this come up constantly on forums and in clinic waiting rooms. People feel something sharp or dull under their left rib cage and immediately assume the worst. Usually it is nothing critical, but sometimes it is worth paying attention to. The area below the left ribs contains several structures: the spleen, the tail of the pancreas, the left kidney, part of the colon, and the lower portion of the stomach. Each of these can produce different types of pain, and telling them apart matters. The first thing most people miss is that the quality of the pain tells you more than the location alone. I had a patient last year who described his discomfort as a constant pressure that worsened after eating heavy meals. He was convinced it was cardiac referral pain because of his family history. We ran the standard workup. Troponins were clean. The CT showed a pancreatic tail pseudocyst, nothing emergent but definitely the source. If you are guessing, you will either miss something or waste a lot of money on tests that turn up nothing. Musculoskeletal causes are far more common than people admit. Costochondritis, where the cartilage connecting your ribs to the sternum gets inflamed, often presents as pain below the left rib margin. The distinguishing feature is reproducibility. Press on the area. If you can push your finger into the exact spot and reproduce the pain, it is almost certainly chest wall related. I have seen patients go through three rounds of cardiac workups for what turned out to be slipped rib syndrome, where the 9th through 11th ribs subluxate and irritate the intercostal nerve. The fix is usually a rib belt or targeted injection, not another echo.
GI causes cluster around the stomach and colon. Gastritis or a gastric ulcer produces a burning or gnawing sensation that typically improves temporarily with antacids but returns. The pain may radiate to the back in cases of posterior gastric ulcers. Splenic flexure syndrome is another common culprit. This is trapped gas at the bend of the colon under the left ribs. It causes sharp, crampy pain that comes in waves and shifts position. A warm compress and simethicone will usually resolve it within twenty minutes, though some people find that walking helps more than anything else. Pancreatic pain tends to be deeper and more constant. It often bores through to the back and does not change much with position. This one you should not sit on. Acute pancreatitis can develop over hours and becomes serious fast. Chronic pancreatitis pain is more insidious but always warrants imaging. If your pain wakes you from sleep or is accompanied by unexplained weight loss, get checked before you try home management.
When to Actually Worry
I am not going to give you a long list of red flags because most of them are obvious. Severe unrelenting pain, fever with chills, vomiting blood, black tarry stools, jaundice, sudden pain after trauma, or pain with shortness of breath all deserve immediate medical attention. But here is the nuance that gets missed: pain that is constant and progressive over several days, even without dramatic symptoms, is more concerning than pain that comes and goes aggressively. Splenic infarction, for instance, can present with mild persistent left upper quadrant discomfort and subtle findings on exam. The classic textbook presentation is dramatic, but real patients rarely follow the textbook. One thing I learned the hard way involves diabetic patients. Their pain perception can be blunted, and a splenic abscess or pancreatic process may present with minimal discomfort until it is advanced. If you have diabetes and new onset left upper quadrant pain, do not assume it is muscular. A low threshold for imaging here saves lives.
Get the Full Details

Practical Steps If You Suspect Something Serious
Start with your primary care provider. A basic workup for persistent left-sided abdominal pain should include a CBC, CMP with liver enzymes and lipase, urinalysis, and an abdominal ultrasound as a first-line imaging study. If the ultrasound is inconclusive or shows something concerning, a CT with contrast is the next step. I know people hate the radiation, but this is not the time to be cautious. An ultrasound misses pancreatic pathology about forty percent of the time due to bowel gas obscuring the view. A CT gives you the anatomy you need. For occasional pain that seems muscular or gas-related, try positional changes first. Many people find that lying on their right side relieves splenic flexure pain by allowing gas to move distally. Others get relief from leaning forward, which takes tension off the posterior structures. Keep a symptom diary for two weeks. Note timing, food triggers, bowel habits, and what makes it better or worse. That diary is worth more than most initial office visits. Over-the-counter NSAIDs are a double-edged sword here. They help musculoskeletal pain but can worsen gastritis or ulcers. If you suspect gastric involvement, stick with acetaminophen and avoid NSAIDs entirely until you have been evaluated. I have seen too many people take ibuprofen for what they thought was muscle pain, only to discover they had a bleeding gastric ulcer afterward.
Spleen issues deserve a mention because they are underrecognized in primary care. Splenomegaly from any cause can cause a dull ache below the left ribs. The spleen sits against the posterior abdominal wall, so the pain is often vague and poorly localized. If you have known liver disease, mononucleosis, or a hematologic condition, any new left upper quadrant pain should be evaluated for splenic enlargement. A palpable spleen tip is easy to miss on self-exam but straightforward for a clinician once you know where to look. Kidney pain from the left side typically presents more posteriorly, but referred pain can manifest anteriorly below the ribs. If your pain changes with hydration status or is associated with urinary symptoms, consider renal colic or pyelonephritis. A simple urinalysis takes five minutes and rules in or out most renal causes. The bottom line is that most left-sided pain below the ribs is benign, but the ones that are not tend to share patterns that are easy to overlook if you do not know what to ask for. Getting the right test at the right time matters more than getting every possible test done. Start conservative, track your symptoms, and escalate if anything feels off or does not improve within a reasonable window. Four weeks of persistent symptoms is a fair threshold before pushing for imaging and specialist referral.