What Abdominal Pain Out Of Proportion To Exam Actually Means In Practice
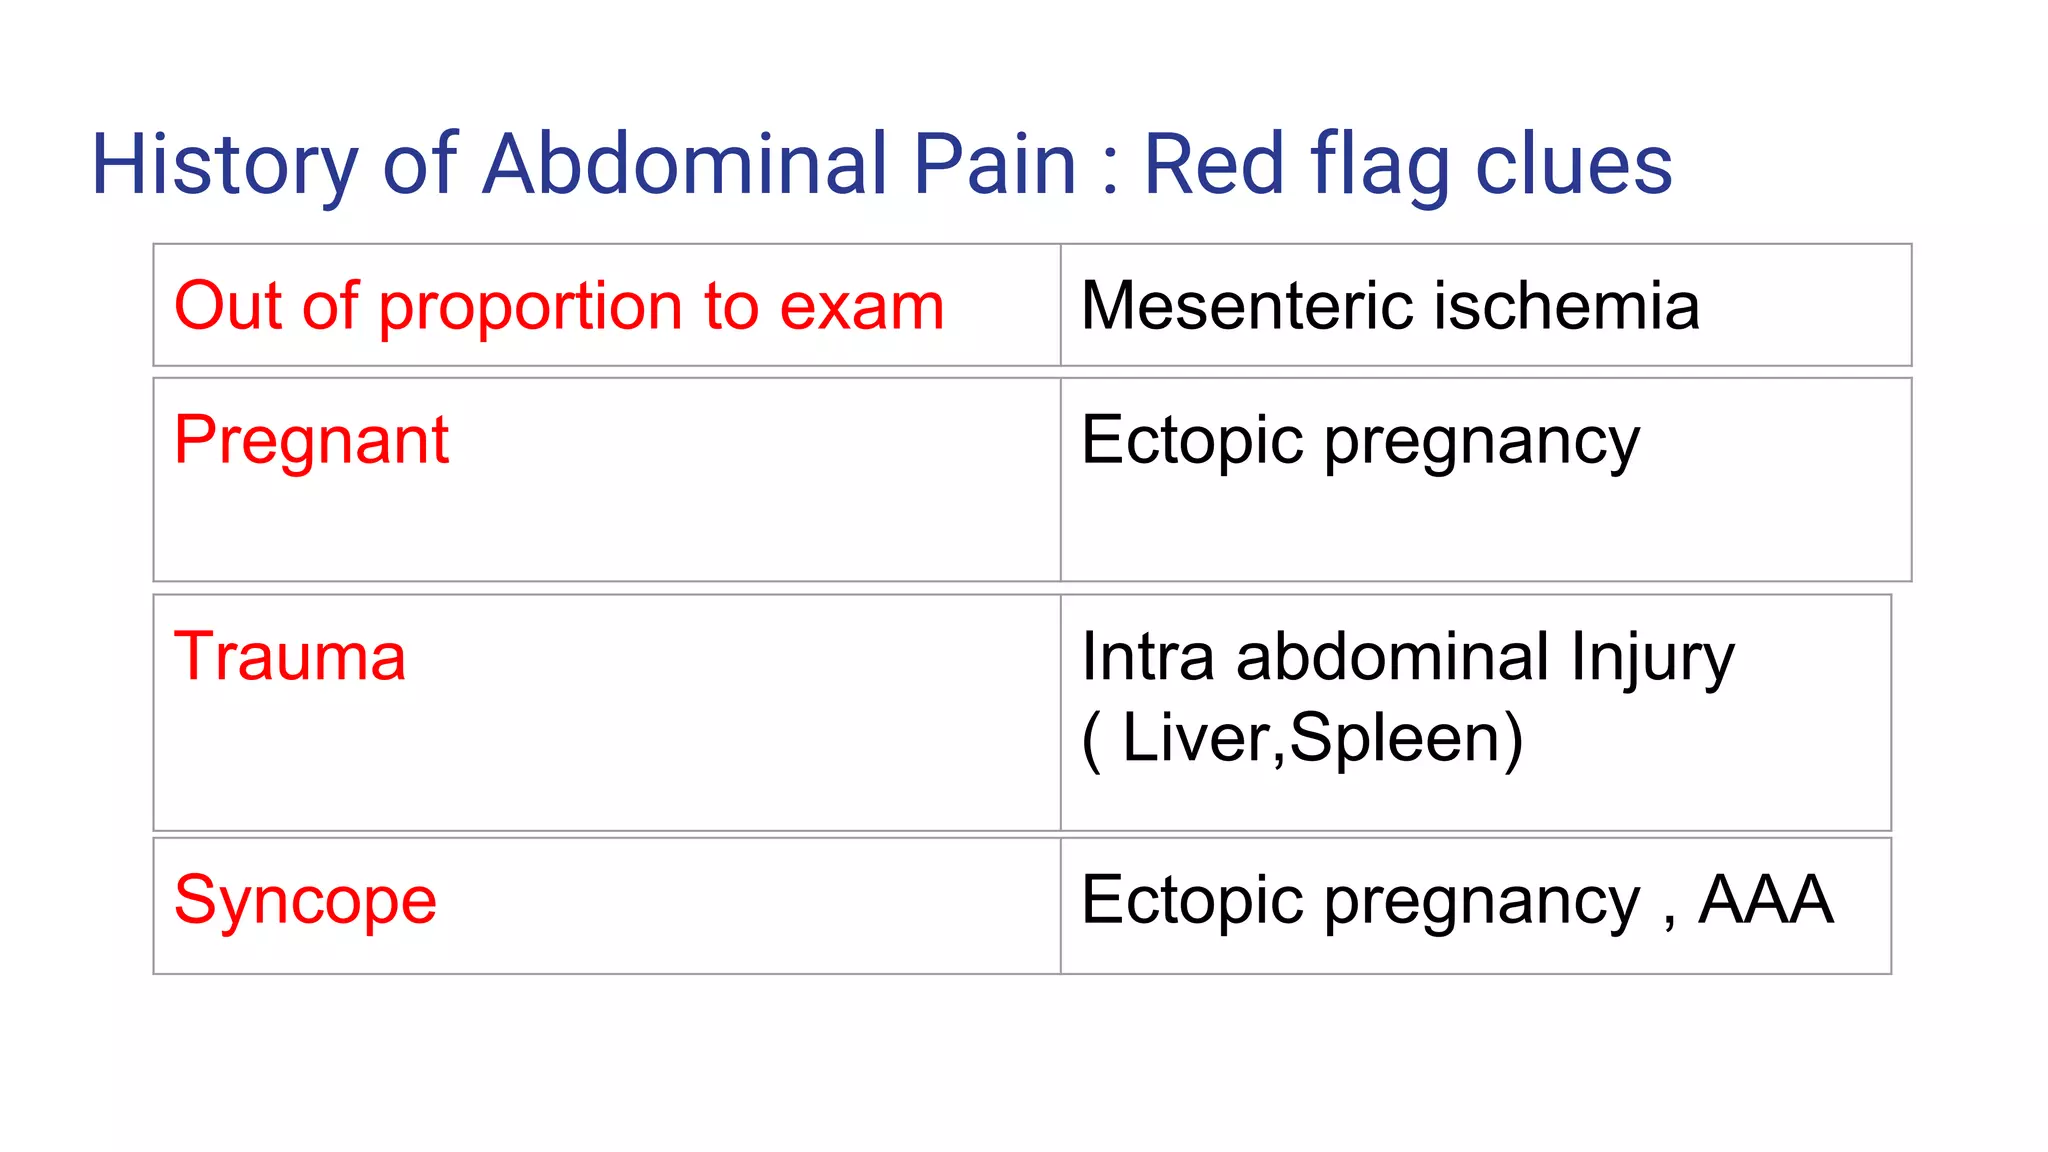
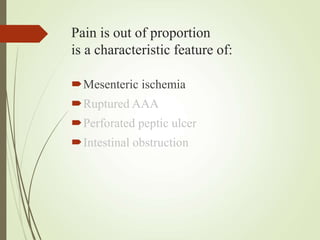
This is a clinical descriptor, not a diagnosis. It means the patient is in severe pain but the physical exam shows little to no tenderness, guarding, or rigidity. You press on their abdomen and nothing happens, but they are sweating and rolling around. That discrepancy matters because it usually signals something serious happening inside the abdomen that isn't creating peritoneal irritation yet. The classic teaching scenario is acute mesenteric ischemia. An older patient with atrial fibrillation presents with sudden, crampy abdominal pain. Their pain score is 9 out of 10. You palpate and the abdomen is soft and nontender. No rebound. No guarding. This isn't a trick question. This is mesenteric ischemia until proven otherwise. The bowel is dying but the parietal peritoneum hasn't been involved yet, so the exam doesn't reflect the severity of the underlying pathology. I worked a shift a few years back where we had a diabetic patient in their 60s who came in complaining of the worst abdominal pain they'd ever felt. Exam was essentially benign. Lactate was 4.2. CT with contrast showed extensive superior mesenteric artery thrombosis. They went straight to the OR. If we had waited for the exam to become more dramatic, the bowel would have been nonviable and mortality would have been significantly higher. The disconnect between symptom and sign was the entire diagnostic clue.
Other conditions that present this way include aortic dissection extending into the mesenteric vessels, early appendicitis before rupture and peritoneal involvement, diabetic ketoacidosis, sickle cell crisis, and even lead colic. Acute pancreatitis can sometimes show this pattern too, though the exam findings vary widely depending on severity. The mechanism is straightforward. Visceral pain fibers from the gut are carried by sympathetic nerves and don't localize well. They produce diffuse, poorly localized discomfort. When the peritoneum becomes involved, somatic pain fibers take over and you get localized tenderness and guarding. So when pain is severe but the exam is relatively quiet, you're dealing with a purely visceral process or vascular compromise before peritoneal irritation develops. Labs and imaging are where you go from suspicion to confirmation. A lactate level is useful but it's late and nonspecific. A normal lactate does not rule out mesenteric ischemia, especially in early presentation. D-dimer has poor specificity in the emergency setting. CT angiography is the workhorse here and it should be your first-line imaging when this presentation comes through the door. The sensitivity is roughly 80 to 90 percent for acute mesenteric ischemia when you use a proper protocol with arterial and venous phases.
If CT isn't available or the patient is unstable, you do an abdominal X-ray to look for pneumoperitoneum and a portable ultrasound to assess aortic diameter and flow. I've seen this approach fail because someone assumed the ultrasound was adequate and missed an SMA occlusion. CT angiography is the standard and you shouldn't compromise on it unless the patient literally cannot leave the resuscitation bay. The main pitfall I see is anchoring bias. You get a patient with a history of IBS or chronic abdominal pain and you dismiss their complaints because the exam is benign. A 72-year-old with atrial fibrillation and a history of IBS still deserves a full ischemic workup. Another common error is ordering a CT without contrast or with a non-vascular protocol and then wondering why you can't see the vessels. Use a dedicated mesenteric CTA protocol. It takes about the same time and it actually shows you what you need to see. Management depends entirely on the underlying cause. For mesenteric ischemia, you start anticoagulation immediately if there are no contraindications, give broad-spectrum antibiotics because translocation is likely, and get a vascular surgery consultation stat. Time from symptom onset to revascularization is the single biggest predictor of survival. Early intervention can be difference between a bowel resection and a full necrotic colectomy with a much higher mortality rate.
Get the Full Details

For aortic dissection, you control heart rate and blood pressure with beta-blockers first, then add vasodilators if needed. Neurology or vascular surgery gets called immediately. For DKA, you follow standard DKA protocol with fluids, insulin, and potassium replacement. Sickle cell crisis gets hydration, oxygen, and appropriate analgesia. This presentation is inherently dangerous because it's easy to underestimate. The lack of exam findings creates a false sense of security. You need to treat the pain severity as the primary signal and use objective testing to explain it, not wait for the exam to catch up. The patients who die from this are the ones who were observed too long with a reassuring abdominal exam while the pathology progressed underneath.