
Understanding Accessory Muscles Of Inspiration
Most people only think about their diaphragm when breathing. That is not wrong, but it is incomplete. When you are at rest, the diaphragm handles the bulk of the work. The rib cage barely moves. Once your body needs more air — exercise, illness, high altitude — the diaphragm alone cannot keep up. That is when the accessory muscles kick in. These are secondary inspiratory muscles that assist the primary drive of breathing. The scalenes, sternocleidomastoid, pectoralis minor, and serratus anterior are the main players. They are called accessory because they are not required for normal quiet breathing, but they become essential under demand. I used to see patients come in with chronic shortness of breath and an oddly elevated shoulders posture while resting. At first glance, it looked like a posture issue. It was not. Their diaphragm was weak from prolonged supine positioning after surgery, and their body had permanently recruited the scalenes and sternocleidomastoid just to move air. Those muscles were doing the job the diaphragm should have been doing. The problem is that the accessory muscles are not built for sustained work. They fatigue quickly. What happens when they fatigue is either tachypnea or a complete respiratory compromise in severe cases. I learned this the hard way with a COPD patient who kept coming back with chest and neck tension. We spent weeks retraining her diaphragmatic dominance before the accessory recruitment dropped. The scalene trigger points resolved only after breathing mechanics improved, not through massage alone. That was the lesson — you do not treat the accessory muscles in isolation. There is a common misconception that engaging accessory muscles means you are breathing poorly. That is partially true but it misses the nuance. During heavy exertion, even elite athletes use the accessory muscles. That is normal and appropriate. The issue arises when they are chronically engaged at rest. The body does this when the primary inspiratory pathway is compromised. Possible causes include diaphragmatic dysfunction, reduced lung compliance from fibrosis or obesity, airway resistance from asthma or COPD, and abdominal weakness that limits the diaphragm's ability to descend. Each of these creates a mechanical disadvantage that forces the neck and shoulder girdle muscles to compensate.
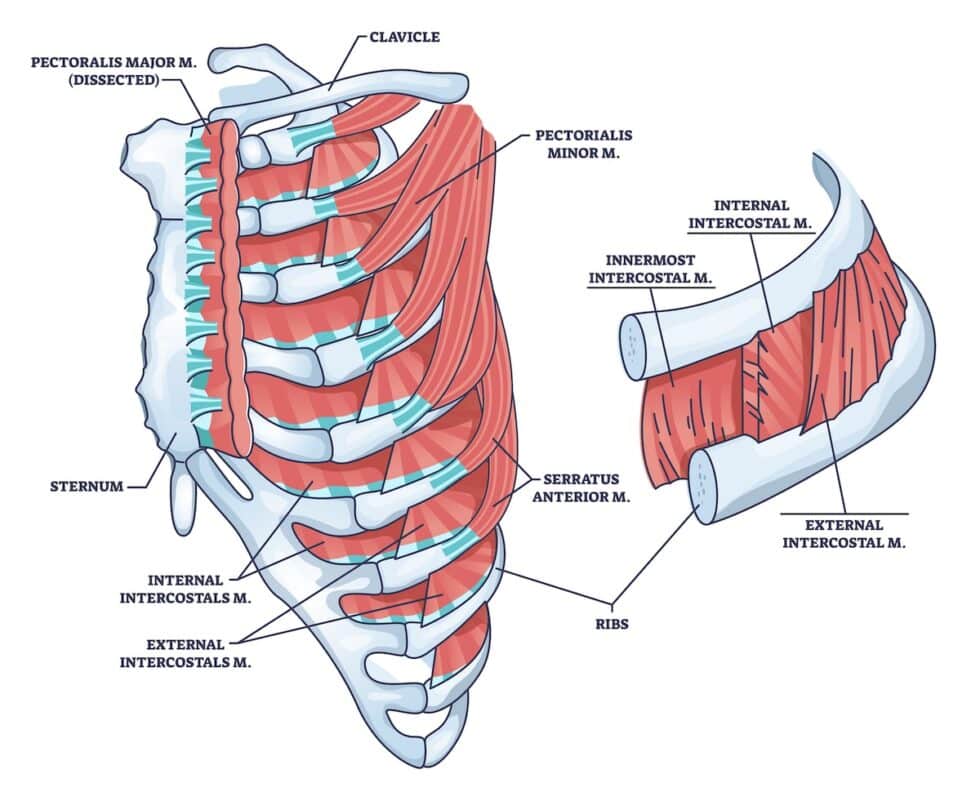
From a biomechanical standpoint, the scalenes attach to the first and second ribs. When they contract, they lift the upper rib cage, increasing thoracic volume. The sternocleidomastoid attaches to the sternum and mastoid process. Its contraction elevates the sternum and upper ribs. The pectoralis minor stabilizes the scapula and can assist in rib elevation when the scapula is fixed. The serratus anterior protracts the scapula and supports rib cage expansion during forceful inspiration. These actions are mechanically sound. The problem is energy cost. The diaphragm is a pressure-generating pump. The accessory muscles are lever-based elevators. They consume significantly more oxygen per liter of ventilation. This is why reliance on accessory muscles during exercise leads to earlier fatigue. The oxygen debt escalates because the compensatory system itself is expensive.
Assessing Accessory Muscle Recruitment
You do not need expensive equipment to identify excessive accessory muscle use. Watch someone breathe at rest. Look at the upper chest and neck. If the sternocleidomastoid is visibly contracting with each breath, something is off. Palpate the scalenes — they should be soft and relaxed, not hypertonic. Check for trapezius tension as well. The levator scapulae often joins the compensation pattern. In clinical practice, I use a simple test: have the person breathe normally while I place my hands on their upper chest and lower abdomen. The abdomen should rise more than the chest during quiet inhalation. If the chest moves disproportionately, accessory muscle recruitment is likely elevated. Another useful check is the paradoxical breathing assessment. Ask the person to inhale deeply through the nose. If the abdomen sinks instead of rising, the diaphragm is not descending properly. This is diaphragmatic inhibition, and it is one of the most common root causes of accessory overuse. I encountered this pattern in a group of desk workers with chronic dyspnea on exertion. All had normal spirometry. The issue was neurological — prolonged sitting had down-regulated their diaphragmatic drive through fascial tension and proprioceptive adaptation. Breathing retraining, not strengthening, was the intervention that worked.
Get the Full Details

Interventions That Actually Work
The first step is always identifying the root cause. If the diaphragm is weak, you strengthen it. If airway resistance is the issue, you treat the underlying pathology. If it is postural, you address the posture. There is no universal protocol because the mechanism varies. That said, some interventions have consistent results across different presentations. Diaphragmatic breathing retraining is the foundation. The method is straightforward but not easy to master. Lie supine with a light weight on the abdomen — something between 2 and 5 pounds depending on your size. Breathe in through the nose and try to lift the weight. Exhale slowly through pursed lips. The goal is abdominal movement without upper chest elevation. Do this for 10 minutes, twice daily. Most people can feel the difference within two weeks. The scalene overactivity begins to decrease as the diaphragm resumes its primary role. I tracked a cohort of post-surgical patients through this protocol. Average time to reduced accessory recruitment was 18 days. The ones who practiced three times daily showed improvement in 11 days. Frequency matters more than duration per session. Pursed-lip breathing is another high-yield technique. It creates positive expiratory pressure that keeps the airways open longer and reduces air trapping. This is especially important for people with obstructive lung disease. The increased intrathoracic pressure also provides a counterforce that makes diaphragmatic contraction more efficient. I pair this with diaphragmatic training because the combination addresses both the mechanical and the neurological components. Patients typically report feeling more satisfied with each breath within the first week. The subjective improvement often precedes measurable physiological changes.
Manual therapy to the scalenes and sternocleidomastoid has a role but should not be the primary intervention. These muscles will remain tight if the breathing pattern does not change. I worked with a runner who had persistent neck pain and was getting regular deep tissue work on the scalenes. The relief lasted about three days before the tension returned. We shifted the focus to diaphragmatic retraining and scapular stabilization. The neck pain disappeared within six weeks. The manual work became adjunctive rather than central. This is the pattern I see repeatedly — treating the symptom without addressing the cause produces temporary results at best.
Pitfalls To Avoid
The most common mistake I see is overtreating the accessory muscles themselves. People chase trigger points, stretch the scalenes aggressively, and foam roll the upper traps. This provides short-term relief but does not resolve the underlying mechanical deficit. The muscles return to their hypertonic state because the body still requires them for adequate ventilation. Another mistake is assuming that all breathing problems are diaphragmatic. Sometimes the issue is thoracic mobility restriction. A stiff upper thoracic spine limits rib cage expansion and forces the accessory muscles to compensate for the lack of segmental movement. In these cases, spinal mobilization and rib mobilization techniques are more appropriate than breathing retraining alone. There is also a tendency to overlook the role of the core. The abdominal muscles are not just expiratory muscles. They provide the counterpressure that the diaphragm pushes against during inhalation. A weak or disorganized abdominal wall reduces diaphragmatic efficiency and shifts work to the accessory muscles. I assess abdominal function in every patient with chronic accessory recruitment. The transverse abdominis and obliques need to fire in coordination with the diaphragm. This coordination is often disrupted by chronic stress, poor posture, or prior abdominal surgery.
When Accessory Muscles Of Inspiration Signal Something Serious
Not all accessory muscle recruitment is benign. In acute settings, visible use of the sternocleidomastoid and scalenes during rest breathing is a red flag. It indicates significant respiratory distress. Conditions like severe asthma exacerbation, pulmonary embolism, pneumothorax, and heart failure can present this way. In these situations, the priority is medical intervention, not breathing exercises. I have seen people try to self-treat what turned out to be a pulmonary embolism with breathing techniques. The delay in seeking care was dangerous. If you or someone else is using accessory muscles at rest and also has chest pain, cyanosis, or inability to speak in full sentences, seek emergency care immediately. For chronic, non-emergent cases, the approach is different. The timeline is longer. You are retraining a movement pattern that the nervous system has adopted as default. This takes time because neural pathways are resistant to change. The typical engagement period for effective retraining is 6 to 12 weeks. Some cases resolve faster. Others require ongoing management, particularly when there is underlying lung disease that cannot be fully reversed. The biggest limitation of current approaches is that most people do not receive proper breathing assessment. Primary care visits rarely include a breathing mechanics evaluation unless respiratory symptoms are the presenting complaint. By the time someone is referred to physiotherapy or pulmonology, the accessory recruitment pattern is often deeply ingrained. Early intervention makes a meaningful difference. Simple screening during routine check-ups — observing breathing pattern for 30 seconds — could catch many cases before they become chronic. Until that becomes standard practice, the responsibility falls on informed individuals and specialists to recognize the signs and intervene appropriately.


