Understanding Accessory Structures Of The Skin
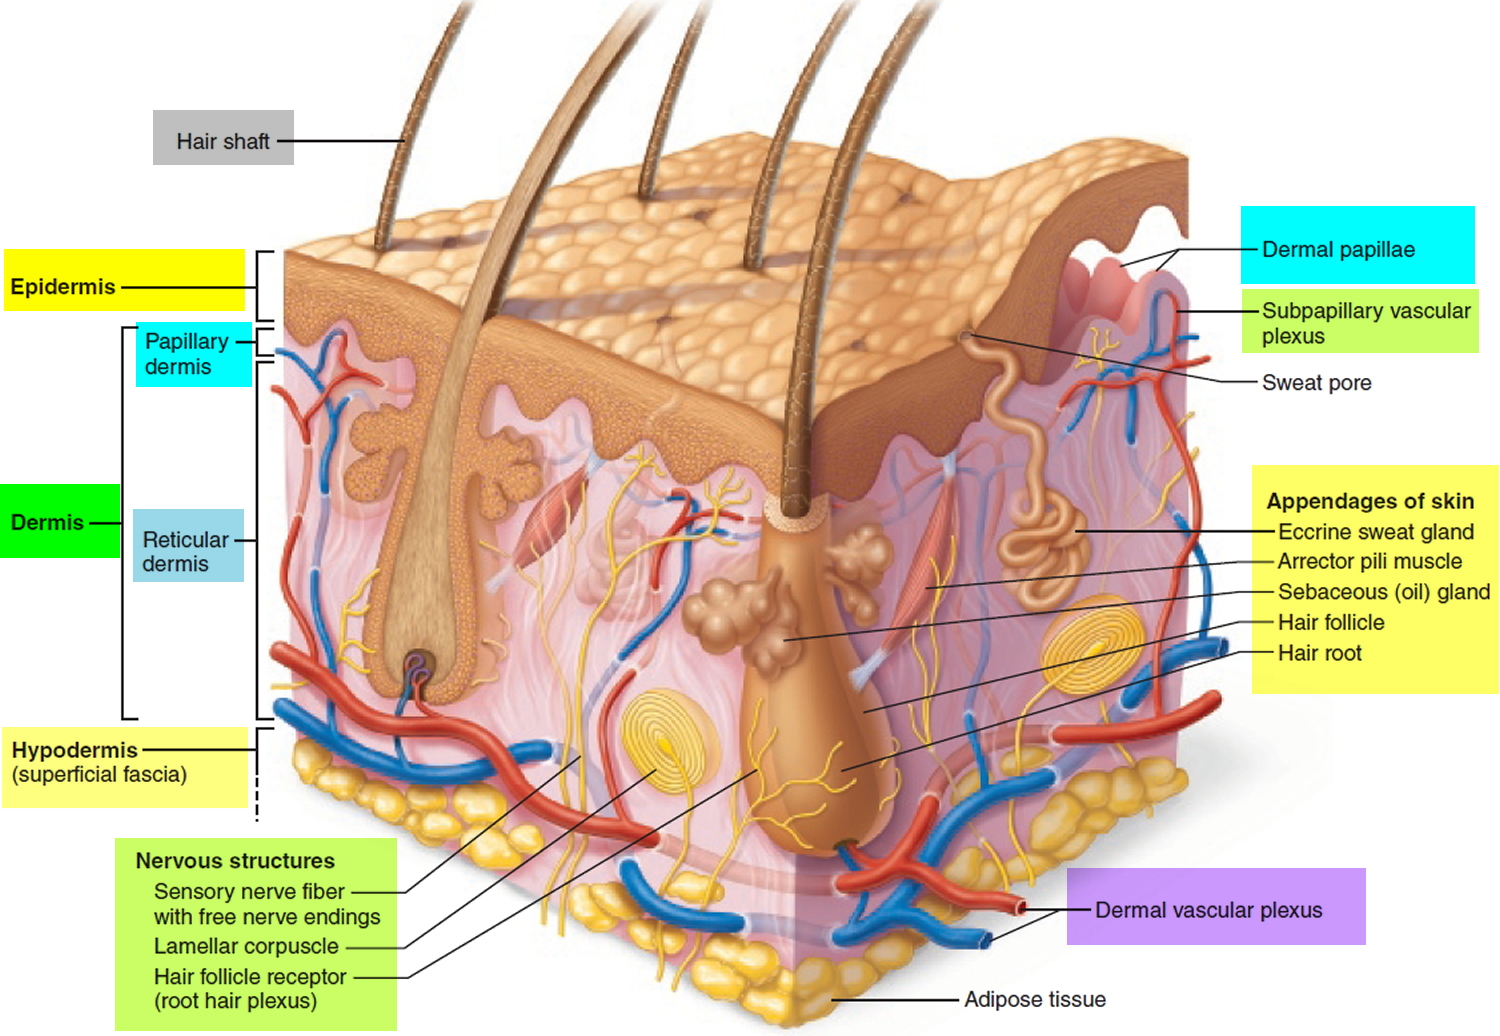
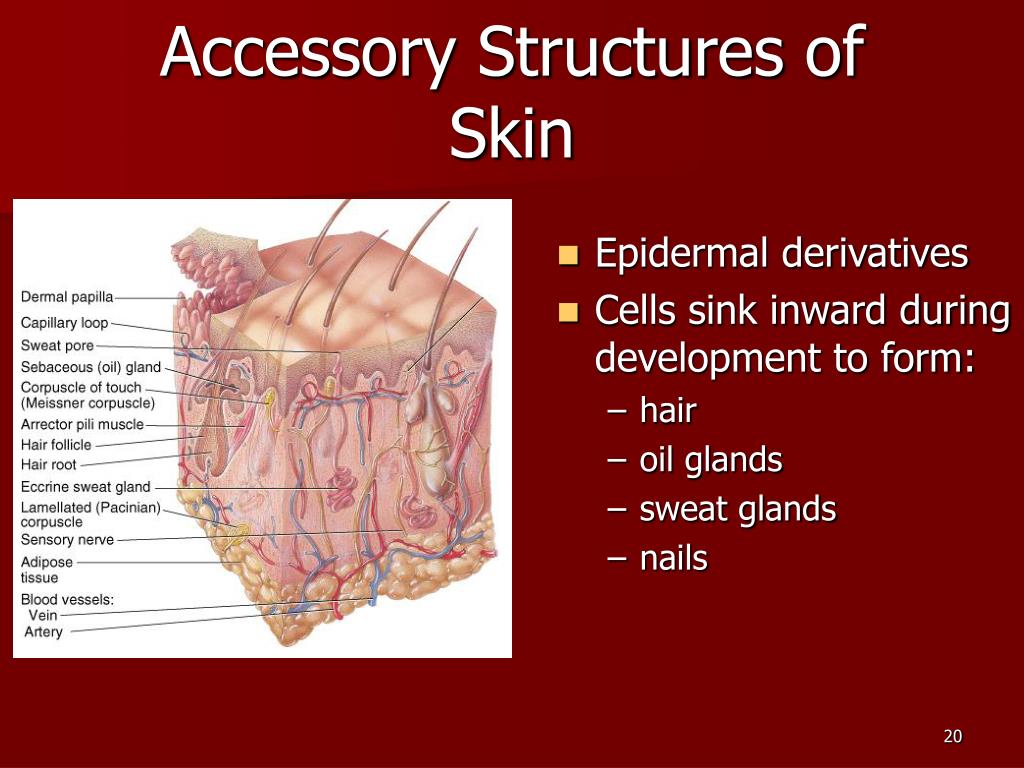
The skin isn't just a flat sheet of epithelium. Underneath the epidermis, you've got a whole supporting cast of structures that do the actual work. Hair follicles, nails, sweat glands, sebaceous glands. They're collectively called accessory structures of the skin, and they're where most clinical and cosmetic problems actually originate. If you're studying this for an anatomy exam, you need to move past the textbook diagrams and understand how these things function in a living system. Here's the thing most people miss: the skin is an organ system, not a wrapping. The accessory structures are embedded in the dermis and subcutaneous tissue, and their developmental origins matter. Hair and nails come from ectoderm. Sweat glands are modified apocrine structures. Sebaceous glands are holocrine. Knowing the embryological origin tells you something about how these things fail when they fail.
Accessory Structures Of The Skin: The Glands
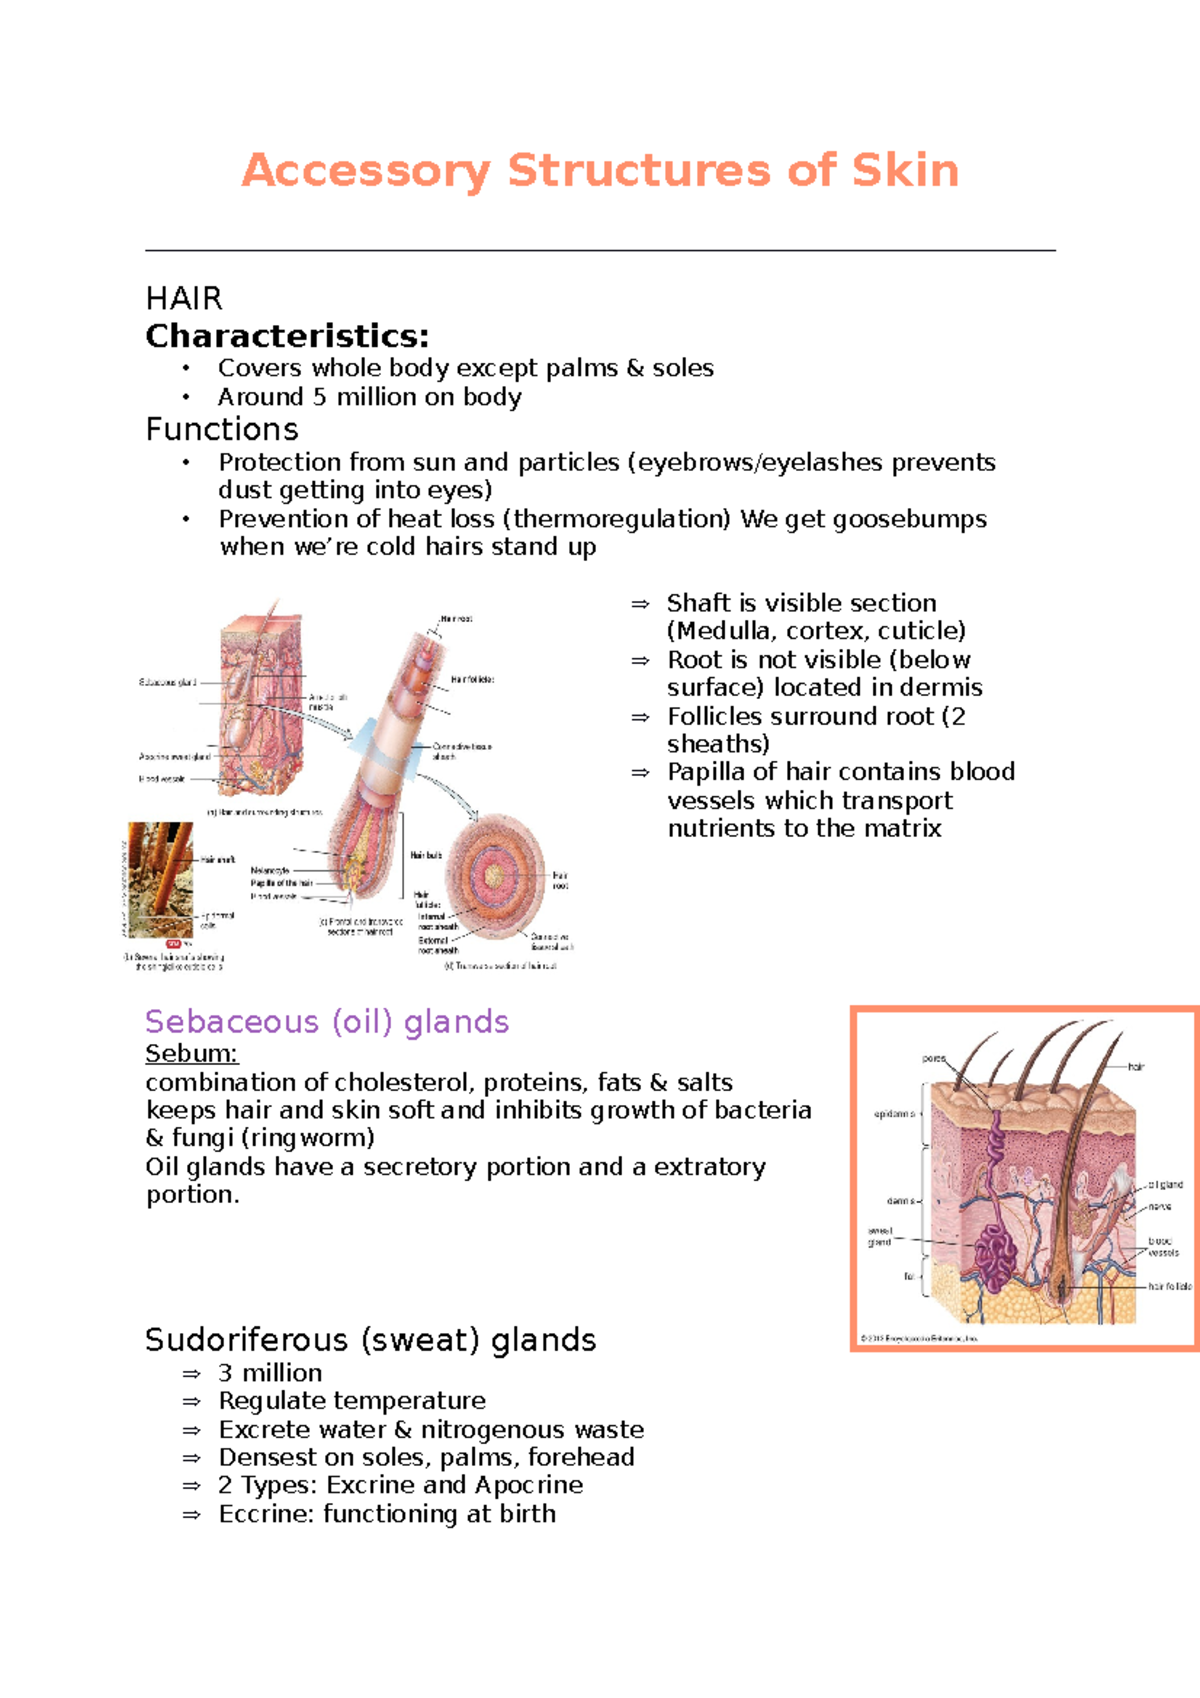
Sweat glands are split into eccrine and apocrine, and that distinction matters more than your textbook probably lets on. Eccrine glands are all over your body, started developing around the 4th month of fetal life, and they're responsible for thermoregulation through watery secretion. Apocrine glands are restricted to the axillary and anogenital regions, they activate at puberty, and their secretion is protein-rich. Bacteria eat that protein, which is where body odor actually comes from. It's not the sweat itself that smells. That misconception costs people a lot of money on deodorant marketing. Sebaceous glands are different entirely. They're holocrine, meaning the whole cell disintegrates to release its product. Sebum is a mix of triglycerides, wax esters, squalene, and cholesterol. It coats the hair shaft and the skin surface. The problem is that sebum production is driven by androgens, not just genetics or stress like some blogs will tell you. During puberty, rising androgen levels hit the sebaceous glands hard. That's why acne peaks in late adolescence, not because you're eating poorly or sleeping badly. It's endocrinology. I ran into a case a few years back with a patient who had severe hidradenitis suppurativa affecting the inguinal folds. Standard treatments — topical clindamycin, oral doxycycline, incision and drainage — weren't touching it. The issue was that I'd been treating it as a simple bacterial infection when it's actually an inflammatory follicular occlusion disease. The work around was switching to adalimumab, a TNF-alpha inhibitor, combined with surgical wide excision of the affected tracts. Took three months of biologic therapy to get it under control, but it stayed controlled. The key was recognizing that apocrine gland-bearing skin in those regions has a different pathophysiology than eccrine-dominated areas.
Hair Follicles And The Growth Cycle
A hair follicle is not a static tube. It's a cycling organelle. The three phases — anagen, catagen, telogen — operate on completely different timelines depending on where the hair is. Scalp hairs stay in anagen for two to seven years. Eyebrow hairs, maybe three to five months. That's why your scalp hair can grow long and your eyebrow hair never will. It's not a growth rate difference. It's the duration of the growth phase. Catagen is the transition. About two to three weeks. The lower follicle regresses, the dermal papilla detaches. Telogen is rest. Three months for scalp. Then the cycle restarts and the old hair is shed. You lose between 50 and 100 scalp hairs a day as part of this cycle. More than that and you should probably get your thyroid and iron levels checked, not start buying shampoos off Amazon. The dermal papilla is the command center here. It's a cluster of specialized mesenchymal cells at the base of the follicle that signals the matrix keratinocytes to proliferate. Without the papilla, the follicle does nothing. This is also why hair transplants work — you're moving follicles with their intact papillae from the donor zone, which is genetically resistant to DHT, to the recipient area. The follicles keep their resistance. They don't become sensitive just because you moved them.
Get the Full Details
Nails: Structure And Function
Nails are keratinized plates on the dorsal aspect of the distal phalanges. The nail body sits on the nail bed, and the matrix underneath produces the nail plate. The lunula you see at the base is just the visible portion of the matrix. The rest of the matrix is hidden under the proximal nail fold. Onycholysis — separation of the nail from the bed — is a common finding I see in practice. Can be fungal, can be psoriatic, can be traumatic. The trick is that distal onycholysis with a yellow-green discoloration often points to Pseudomonas aeruginosa, not dermatophytes. Telling those apart matters because the treatment is completely different. Antifungals won't touch a Pseudomonas infection. Diluted vinegar soaks and topical antibiotics will. Nail growth rates vary by digit and by age. Fingernails grow about 3 to 3.5 millimeters per month. Toenails are slower, roughly 1 to 1.4 millimeters per month. A full fingernail replacement takes about six months. A toenail takes 12 to 18 months. If you're treating onychomycosis, you need to understand that timeline. Oral terbinafine for toenail fungus is typically prescribed for 12 weeks, but you won't see the cleared nail at the base for another six months because it has to grow out. Patience is part of the protocol.
Clinical Overlap And What Beginners Miss
One thing that trips up students is understanding that these structures don't operate in isolation. A sebaceous gland empties into a hair follicle. The arrector pili muscle attaches to the follicle and the dermis. When it contracts, you get piloerection, and the hair stands up. That's the same smooth muscle response mediated by sympathetic innervation. Cold, fear, stress — it all triggers the same pathway. The goosebumps don't do anything useful for humans. We're not shedding insulation anymore. But the anatomy is still there. Another common gap: the relationship between the skin microbiome and these structures. Sebaceous glands create an anaerobic environment on the hair shaft. Cutibacterium acnes thrives there. It's not a pathogen in the traditional sense. It's a commensal that becomes opportunistic when the follicle is occluded and sebum accumulates. Most acne treatments target this dynamic, not a surface infection. Understanding that shifts how you approach the problem from the start. The limitation of this framework is that not every skin condition maps neatly onto one of these structures. Rosacea involves the pilosebaceous unit but doesn't respond to standard acne protocols. Contact dermatitis can affect any area regardless of gland density. And conditions like alopecia areata are autoimmune, not structural. You can know every detail about follicle cycling and still encounter something that doesn't fit the model. That's normal. The model is a tool, not a rulebook.