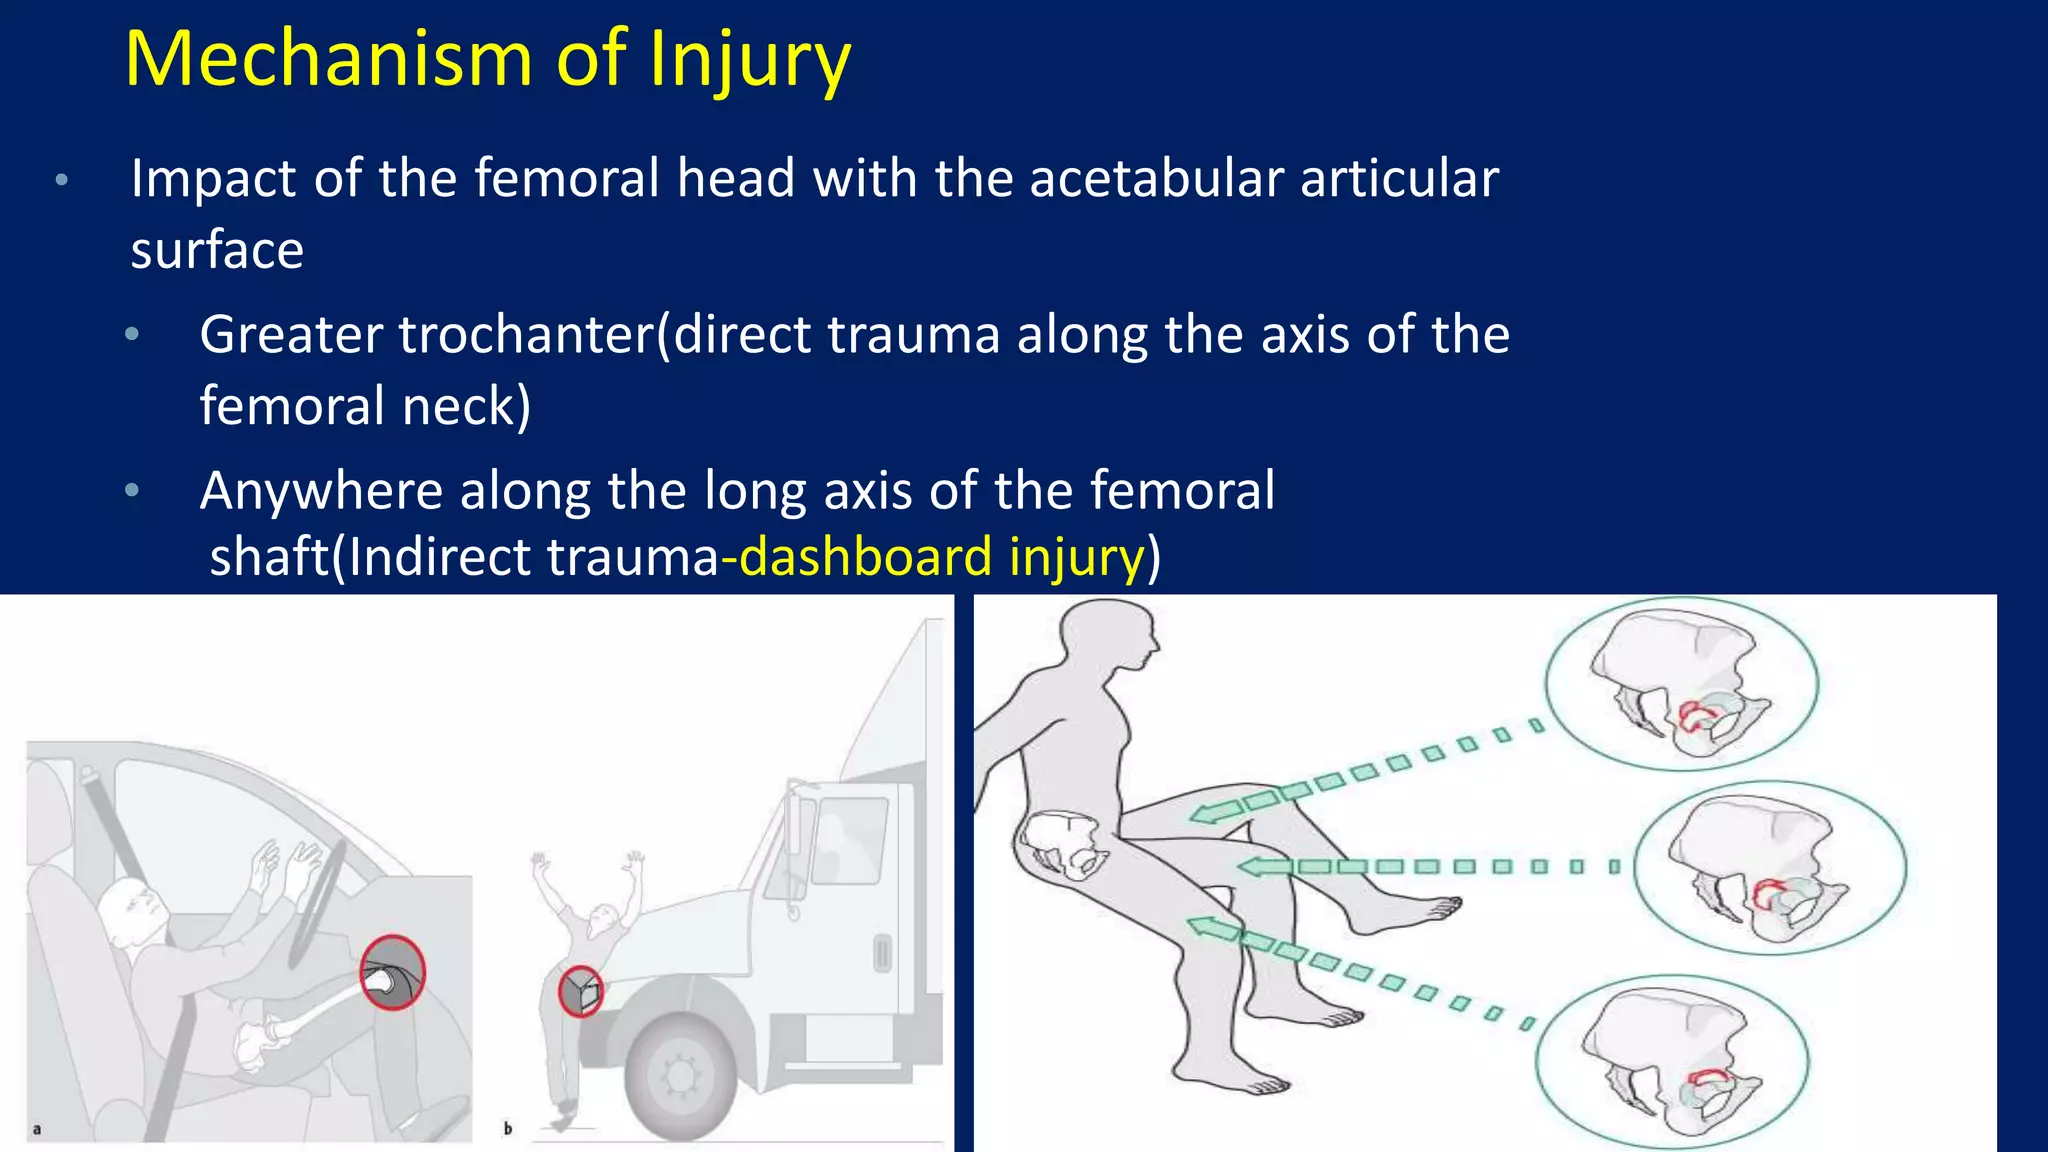
So you need a rehab plan after an acetabular fracture surgery.
Most of the protocols you find online are either too vague to be useful or written for surgeons who have never actually watched a patient try to walk again. I've worked with probably a hundred of these over the years, and the reality is messier than any textbook suggests. Here's what the stages actually look like and where people tend to go wrong. The foundation is straightforward in theory: protect the fixation, restore motion, build strength, return to function. In practice, the timing of everything depends heavily on whether the patient had a purely ligamentotactic approach, an open reduction with plates and screws, or a combined anterior and posterior approach. The surgical approach dictates your precautions more than anything else. I'm going to walk through the phases as I typically see them structured, but you need to understand that these timelines are not guarantees. They're frameworks. A 70-year-old who fell from standing is rehabilitating a completely different biological situation than a 45-year-old in a high-speed MVC with a both-column fracture and some soft tissue compromise.
Phase 1: Protection (Weeks 0-6)
This phase is defined by what you cannot do. Weight bearing is typically toe-touch or non-weight-bearing, and the exact limit depends on the quality of the fixation and the surgeon's comfort level. You'll see some surgeons clear partial weight bearing at 6 weeks if the follow-up X-rays look solid. Others won't budge from NWB for 8 to 10 weeks. Know which one you're working with and don't second-guess the imaging findings yourself. Range of motion precautions are approach-specific. Posterior approaches carry a hip flexion restriction—usually 90 degrees—and adduction and internal rotation are the movement combinations to avoid because they threaten posterior stability. Anterior approaches flip those precautions: extension and external rotation become the concerning movements. This isn't theoretical. I had a patient who was doing fine through the first three weeks, then sneezed while lying on the exam table and felt something shift in her hip. It turned out she was exceeding 90 degrees of flexion because nobody had explicitly told her what that limit was. The fracture hadn't displaced, but the lesson stuck. During this phase, the PT work is minimal by design. Ankle pumps, quad sets, glute sets, and gentle passive or active-assisted ROM within the safe ranges. The priority is swelling control and preventing DVT. I always make sure patients are using their CPM machine if prescribed, even if they hate it. The evidence supports early continuous motion for intra-articular fracture cases, and skipping it because it's uncomfortable is a mistake I see repeatedly.
Phase 2: Intermediate Rehabilitation (Weeks 6-12)
Assuming radiographic signs of healing are present, this is where weight bearing progresses. The typical sequence goes toe-touch to partial weight bearing, then gradually to full weight bearing as tolerated. The increment matters less than the patience. Advancing too quickly into full weight bearing before callus is evident is the single most common way I see hardware fail or reduction loss occur in the outpatient setting. ROM work expands during this window. Hip flexion, abduction, extension, and external rotation are all addressed, though still with caution. Strengthening remains sub-maximal and focused on the hip stabilizers and core. Closed-chain exercises are introduced carefully—mini squats, partial stands, and balance work on the uninvolved side to maintain neuromuscular control without loading the healing joint excessively. Here's something most protocols omit: gait retraining during this phase is critical and underappreciated. Patients develop antalgic patterns quickly and they are stubborn. I spend a significant portion of my sessions just re-establishing a normal heel-strike-to-toe-off pattern with the walker or cane before I worry about strength numbers. A patient who walks correctly at 80 pounds of weight bearing will transition to full weight bearing far more cleanly than one who has been limping for three weeks regardless of how strong they are.
Get the Full Details

Phase 3: Advanced Strengthening (Months 3-6)
By this point most patients are fully weight bearing if the healing has proceeded normally. The focus shifts to restoring full ROM, progressive resistance training, and functional reintegration. Hip extension and abduction strengthening becomes a larger component. Gluteus medius weakness is almost universal after these injuries and it directly affects pelvic stability during gait. I recommend starting resistance work with bands and light weights, progressing to bodyweight exercises, and eventually to more demanding functional movements. Stationary cycling is usually well tolerated by week 10 to 12 if ROM allows. Swimming can begin once incisions are fully healed, which is a convenient way to get cardiovascular work in without impact loading. One thing worth noting: heterotopic ossification can silently limit your progress. If a patient who was progressing well suddenly plateaus on ROM around month 3 or 4, check the X-rays. Even mild HO can be a mechanical block. Prophylaxis with indomethacin or a single dose of radiation is standard in many practices, but it doesn't eliminate the risk entirely. If HO is present and restrictive, surgical excision is sometimes necessary, though that's a discussion for the orthopedist.
Phase 4: Return to Activity (Months 6-12+)
This is the longest and most variable phase. Return to work, sport, and heavy activity depends on the original injury pattern, the patient's baseline fitness, and how well they've progressed through the earlier stages. Desk workers may return as early as 12 weeks. Physical laborers often need 6 months or more and some never return to the same level of demand. Impact activities and high-demand sports are approached cautiously. The acetabulum is a weight-bearing surface, and post-traumatic osteoarthritis is a real long-term concern. I don't recommend jumping into running or jumping sports before 6 months, and even then only if strength symmetrically matches the unaffected side and there are no pain or effusion concerns with moderate loading.
What the literature gets wrong about this protocol
The biggest gap in standard protocols is the treatment of proprioception and neuromuscular control. These patients have literally had the surface of their hip disrupted and rebuilt. The mechanoreceptors in the joint capsule and surrounding ligaments are altered, sometimes significantly. Standard strengthening protocols don't address this. I incorporate single-leg balance work, perturbation training, and movement pattern re-education throughout phases 2 through 4, and it makes a measurable difference in functional outcomes. Another thing: most protocols treat pain as a simple yes-or-no signal. It isn't. Some discomfort during ROM progression is expected and should not automatically halt the program. What I watch for is the quality of the pain—sharp, localized joint pain that increases with each session is a warning sign. Diffuse muscular soreness that improves between sessions is normal. Patients and some therapists conflate the two, which leads to unnecessary conservatism and prolonged rehab.

When the protocol breaks down
Avascular necrosis of the femoral head is the complication that derails everything. It can develop silently over the first 6 to 12 months. If a patient who was progressing appropriately suddenly develops increasing pain, especially with weight bearing, and ROM begins to decrease without an obvious mechanical cause, AVN should be on the differential. An MRI will confirm it. There's no PT workaround for established AVN. The conversation shifts to joint preservation strategies or eventual arthroplasty. Nonunion and malunion are less common with modern surgical techniques but they do occur. If healing isn't advancing on serial X-rays by month 4, the protocol needs to be recalibrated. Continuing to push weight bearing into a nonunion is how you create a symptomatic loose body situation. Post-traumatic arthritis is the long-game concern. It develops in a meaningful percentage of acetabular fracture patients regardless of how well the initial reduction was achieved. The rehab protocol can't prevent it, but optimizing alignment, restoring motion, and maintaining strong periarticular musculature may slow its progression. That's the best we can offer from the rehabilitation side.