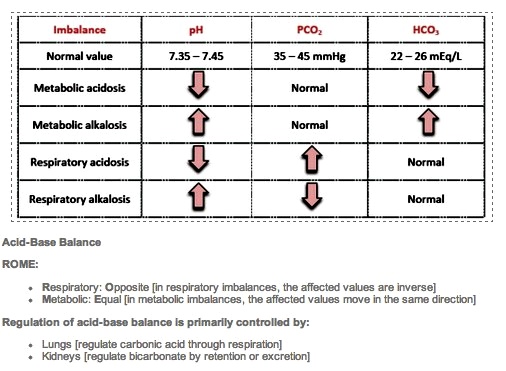
Understanding the Acid Base Balance Chart
The acid base balance chart is a diagnostic tool that maps pH against partial pressure of carbon dioxide to identify metabolic and respiratory disturbances. I use it daily in critical care settings when patients present with unexplained altered mental status or compensatory breathing patterns. The chart itself is straightforward, but applying it correctly requires understanding the physiological relationships between bicarbonate, pCO2, and hydrogen ion concentration. Start with arterial blood gas values: pH, pCO2, and bicarbonate. The normal ranges are pH 7.35 to 7.45, pCO2 35 to 45 mmHg, and bicarbonate 22 to 26 mEq/L. When pH falls below 7.35, you have acidosis. Above 7.45 indicates alkalosis. The chart plots these relationships visually, with pCO2 on the x-axis and bicarbonate on the y-axis, showing expected compensation lines for acute and chronic conditions. I remember a case last winter where a diabetic patient came in with pH 7.28, pCO2 22, and bicarbonate 8. The chart showed this fell along the acute respiratory compensation line for metabolic acidosis, confirming diabetic ketoacidosis with appropriate hyperventilation. Without the visual reference, I might have overcompensated with bicarbonate therapy initially, which would have worsened intracellular acidosis.
Practical Application in Clinical Settings
Most clinicians learn the Henderson-Hasselbalch equation early: pH = 6.1 + log(HCO3 / 0.03 × pCO2). This mathematical relationship underlies the entire chart system. The formula reveals why certain compensation patterns occur and predicts expected values when disorders coexist. Winter acidosis cases present unique challenges. Cold temperatures affect blood gas analyzer calibration and can shift measured values by 0.015 pH units per degree Celsius below 37. I adjust my interpretations accordingly, often running temperature-corrected values alongside uncorrected results for surgical patients in hypothermic conditions. The chart helps visualize these adjustments without manual recalculation each time. Common pitfalls include misinterpreting mixed disorders. A patient might have normal pH but abnormal pCO2 and bicarbonate values indicating combined respiratory and metabolic disturbances. The chart's compensation curves reveal these situations when values fall outside expected ranges. For instance, chronic obstructive pulmonary disease patients with metabolic alkalosis from diuretic therapy often show pCO2 values higher than expected for their bicarbonate level.
Limitations and When the Chart Fails
The acid base balance chart assumes steady-state conditions and doesn't account for acute changes during resuscitation. In trauma cases with ongoing hemorrhage, sequential blood gases may show shifting patterns that the static chart cannot capture accurately. I supplement chart analysis with clinical assessment and trend monitoring rather than relying solely on single measurements. Some laboratories report standard base excess instead of bicarbonate, requiring conversion for chart plotting. The formula converts base excess to bicarbonate: HCO3 = 0.3 × BE + 24.7. Without proper conversion, plotted values may misrepresent the true acid-base status. I verify which parameter the lab reports before referencing the chart. Advanced applications involve calculating the anion gap to distinguish high-gap from normal-gap metabolic acidosis. The formula is: AG = Na - Cl - HCO3. Normal anion gap ranges from 8 to 12 mEq/L depending on laboratory methods. High anion gap acidosis suggests unmeasured anions like lactate or ketones, while normal gap acidosis indicates bicarbonate loss or chloride retention. The chart shows these patterns differently, with high-gap acidosis shifting the bicarbonate line independently of chloride changes.
Get the Full Details
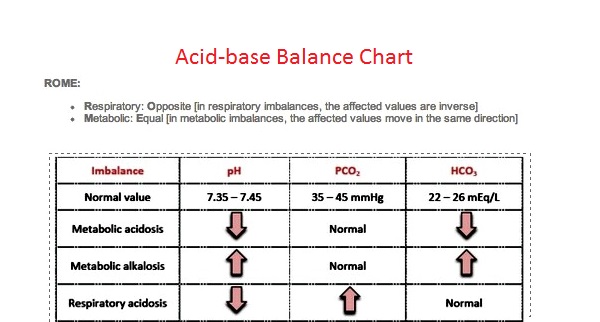
I recommend using the chart alongside clinical judgment and serial measurements rather than as a standalone diagnostic tool. The visual representation helps communicate complex acid-base relationships to colleagues and trainees, but physiological understanding remains essential for accurate interpretation in ambiguous cases.


