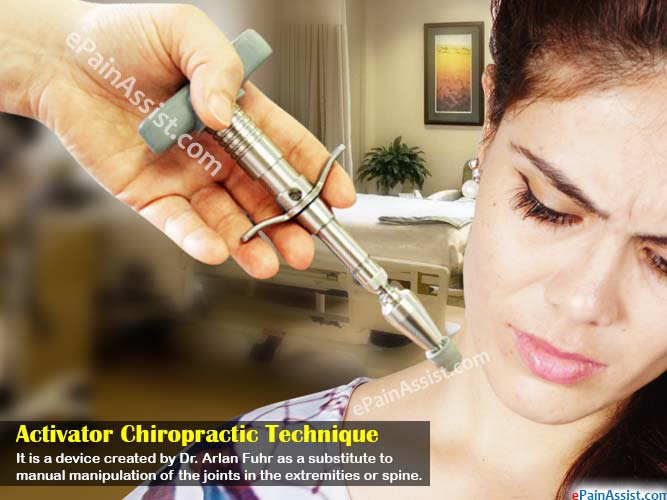
What the Activator Actually Is
The Activator is a hand-held spring-loaded instrument that delivers a quick, low-force impulse to specific points on the spine or extremities. It's not a drill, it's not a manual adjustment tool, and it doesn't use high-velocity thrust. The device fires a controlled mechanical impulse typically between 0.3 and 1.8 joules of energy, depending on the spring tension setting you select. Practitioners use it to assess and treat joint dysfunction in the vertebrae, pelvis, and sometimes peripheral joints. The method was developed in the late 1960s by Dr. H.L. "Roy" Hagestuen, who was an engineer as well as a chiropractor, and it grew out of his frustration with the variability inherent in manual adjusting. What makes it different from standard manipulation is the consistency of force delivery. Every click of the instrument produces the same impulse. There's no variation from practitioner to day-to-day mood. That repeatability is the main selling point and it matters when you're tracking progress over multiple visits or comparing one patient's response to another's.
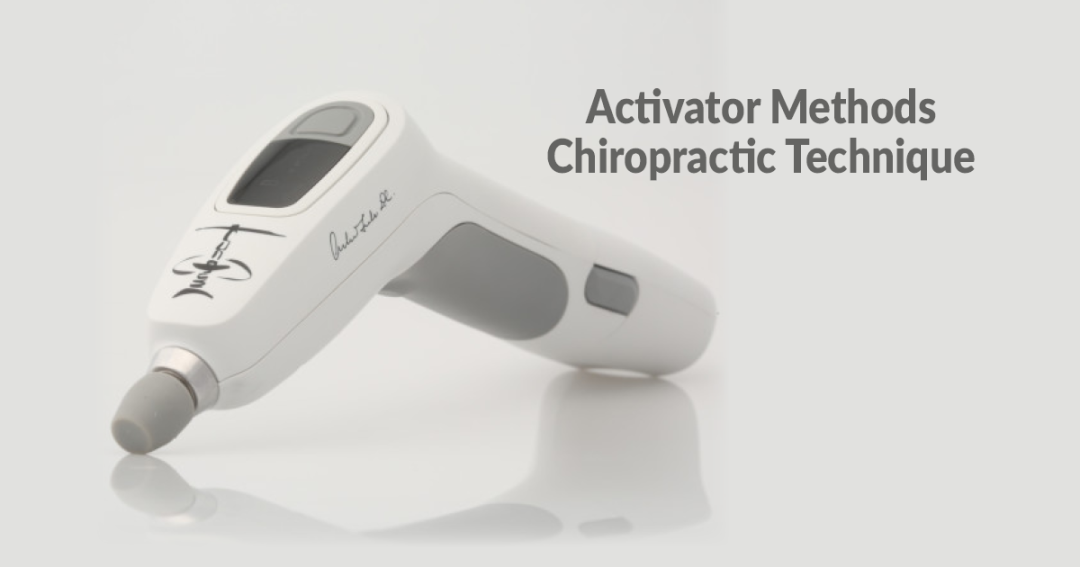
Activator Methods Chiropractic Technique: How It Works in Practice
The technique follows a specific assessment protocol before any impulse is delivered. You begin with leg length analysis to detect pelvic asymmetry, then use the Activator's tip to palpate specific spinous processes or transverse processes while observing the leg for changes in length. When a process is found to be posteriorly rotated or misaligned, the leg will typically shorten in response to pressure. That's your indicator. You then set the spring tension on the Activator and position the tip at approximately 90 degrees to the targeted vertebral surface. A quick, short impulse follows. The whole adjustment takes less than two seconds per segment. I've used this on everything from acute lumbar restrictions to chronic sacroiliac dysfunction. The most common error I see new practitioners make is rushing the leg check. They skip the bilateral comparison and just fire away at whatever looks off on palpation alone. That approach produces inconsistent results. The leg length response is the feedback mechanism. Without it you're guessing instead of measuring. Take the time to confirm the side and level before committing to an impulse.
Equipment and Setup
The standard Activator IV or V model is the most widely used. The IV has adjustable spring tension with four settings, marked A through D, where D delivers the strongest impulse. The V model adds a digital readout and a few refinements to the trigger mechanism but the fundamental technique doesn't change. You'll need a standard chiropractic treatment table with a face cradle and pelvic drop if you plan to combine it with manual adjustments later, though the Activator itself doesn't require drops. Keep the instrument clean between patients. Wipe the tip and housing with an EPA-approved hospital-grade disinfectant. The rubber tip is replaceable and should be swapped out when you see any cracking or flattening. A worn tip changes the contact surface area and can alter force transmission in unpredictable ways. Store the device in its case when not in use. The spring mechanism degrades faster if left exposed to temperature extremes or dropped, which happens more often than you'd think in a busy clinic.
Get the Full Details

Step-by-Step Technique for Lumbar Segments
Start with the patient prone. Remove any pillows from under the abdomen unless the patient specifically needs one for comfort, as excessive lordosis can mask sacral motion. Perform a standing postural assessment first if possible, noting any shoulder or pelvic tilt before you even have the patient lie down. Then move to leg length analysis with the patient supine. Note the apparent difference between medial malleoli. This is your baseline. Next, have the patient return to prone. Using the palm of your hand or the Activator tip in palpation mode, scan from L1 down through S1. Press firmly but not painfully on each spinous process and observe the leg for length changes. Mark the level where the leg shortens. That's your adjustment target. Set the Activator to the appropriate tension. For a typical adult lumbar segment, setting B or C works for most cases. Start conservative and increase only if the leg response doesn't normalize after the first pass. Position the tip centered on the posterior aspect of the targeted spinous process or the inferior lateral corner if you're targeting the articular pillar. Maintain a perpendicular angle. A 45-degree angle transfers significantly less force into the joint and more into the surrounding soft tissue, which defeats the purpose. Deliver the impulse with a smooth, steady trigger pull. Do not hold the trigger down. Each press should be a single short burst. Recheck leg length immediately after the impulse. If the legs are still unequal, reassess. You may have missed a level or the spring tension may need adjustment.
Common Pitfalls and What I Learned the Hard Way
One thing that caught me early in my career was the assumption that a positive leg response always meant a structural subluxation. It doesn't. Muscle guarding, hamstring tightness, and even recent exercise can alter leg length independently of joint position. I once treated a patient for three consecutive visits targeting L5 based on repeated leg shortening, only to discover the real issue was a hypertonic piriformis compressing the sciatic nerve. The leg was responding to soft tissue tension, not articular misalignment. The workaround was straightforward but easy to overlook. Before relying solely on the Activator assessment, I started incorporating seated flexion tests, prone leg lift tests, and direct palpation of the piriformis and hamstrings. When the leg response didn't match the clinical picture, I treated the soft tissue first and rechecked before firing the instrument again. This took longer initially but reduced unnecessary spinal impulses and improved overall outcomes significantly. If you're using the Activator exclusively without correlating findings through other orthopedic and palpation tests, you're working blind half the time. Another pitfall involves pediatric and geriatric patients. The standard spring settings that work for a healthy 35-year-old adult are far too aggressive for a frail elderly patient or a toddler. I've seen practitioners use the same tension setting across all age groups and then wonder why some patients experience post-adjustment soreness that lasts two to three days. Start at setting A for anyone under 12 or over 65, or for patients with osteoporosis or connective tissue disorders. The impulse is still effective at lower tension when applied to the correct segment.
Contraindications and Limitations
The Activator is not appropriate for every condition. Fractures, tumors, infections, and acute inflammatory conditions in the targeted area are absolute contraindications. I also avoid using it over areas of known osteopenia or osteoporosis without first reviewing imaging, because even low-force impulses can theoretically contribute to vertebral compression in severely demineralized bone. Pregnancy is not an absolute contraindication, but I modify the approach entirely, avoiding lumbar and sacral impulses in the third trimester and focusing instead on extremity and cervical work when needed. The method has a well-documented limitation in cases of severe facet joint ankylosis or advanced degenerative joint disease with significant osteophyte formation. The impulse simply cannot move a fused segment and may irritate surrounding inflamed tissue instead. In these situations, manual mobilization at graded ranges or referral for medical evaluation is more appropriate. The Activator excels at functional restrictions, not structural ones. Understanding that distinction prevents frustration and wasted treatment time.
Evidence Base and Clinical Considerations
The research on Activator Methods is mixed but generally supportive for specific conditions. Systematic reviews have shown modest but statistically significant improvements in patients with acute low back pain compared to sham intervention, and the method appears comparable to manual manipulation for certain types of chronic spinal dysfunction. The Cochrane reviews have been cautious, citing small sample sizes and methodological limitations across most studies. That doesn't mean the technique lacks value, it means the evidence hasn't reached the strength we'd need for blanket recommendations. What the literature does consistently support is the low-force nature of the impulse. For patients who are anxious about manual cracking or who have previously had adverse reactions to high-velocity adjustments, the Activator provides a viable alternative. Patient compliance tends to be higher because the procedure is quick and generally painless during execution. Post-treatment soreness rates are lower than with manual manipulation, though not zero. Expect some patients to report mild tenderness at the application site for 24 to 48 hours, particularly if the targeted segment had been dysfunctional for an extended period.
Integration with Other Techniques
The Activator rarely operates in isolation in a competent practice. I commonly use it alongside McKenzie directional preference assessment, Mulligan mobilizations with movement, and standard palpatory diagnostics. A typical session might begin with assessment and leg checks, proceed with Activator impulses on identified segments, follow with soft tissue work on associated myofascial restrictions, and conclude with patient-specific therapeutic exercise. This sequence usually takes between 20 and 35 minutes depending on the complexity of the case. Combining the Activator with drop-piece table adjustments can be effective but requires careful sequencing. If you're using both modalities on the same region, I prefer to complete the Activator work first while the tissues are still in their baseline state, then transition to drop adjustments for any remaining restriction. Doing it the other way around can mask the leg length responses you need for accurate Activator targeting.
Training and Certification Pathway
Formal training in Activator Methods is administered through the Activator Methods Chiropractic Institute, which offers tiered certification levels. Level 1 covers the basic assessment protocol and lumbar, pelvic, and cervical techniques. Level 2 introduces thoracic, extremity, and pediatric applications. Level 3 focuses on advanced case management and integration with other diagnostic systems. Most practicing chiropractors complete Level 1 within a single weekend workshop, though the hands-on practice time is limited. I'd recommend supplementing the workshop with additional self-study and supervised clinical hours before relying on the technique independently. Continuing education through the institute includes updated protocols for new research findings and technique refinements. The curriculum has evolved over the decades, particularly around the role of inflammation and the neurophysiological effects of low-force impulses. Staying current matters because the evidence base continues to shift, and outdated protocols can lead to overtreating or undertreating specific presentations.

Practical Tips for Daily Use
Keep a treatment log that records the spring tension setting, the specific segments treated, and the pre- and post-leg length measurements. This data becomes invaluable when tracking whether a patient is responding positively or a change in approach. I've found that reviewing these logs quarterly reveals patterns that individual sessions can obscure. Patients who appear stable on the surface often show gradual regression in the numbers if you're not recording them. Maintain your instrument. Inspect the tip before every patient. Check the trigger mechanism for consistency. A sluggish trigger or a tip that doesn't seat properly will produce variable impulses and compromise your assessment accuracy. Replacement parts are inexpensive compared to the cost of misdiagnosing a segment because of equipment failure. Keep spare tips, the cleaning solution, and the charging cable accessible at all times during clinic hours. Know when not to use it. The Activator is a tool, not a diagnosis. If a patient presents with neurological deficits, progressive symptoms, or red flag findings, send them for imaging and medical evaluation regardless of how clean the Activator assessment looks. No adjustment method overrides a serious underlying pathology. The instrument won't fix a herniated disc with cauda equina involvement and pretending otherwise is the fastest way to lose patients and credibility.