Why You Can't Fully Flex Your Fingers When Your Wrist Is Already Bent
You've probably noticed this without giving it much thought. Try making a tight fist with your wrist completely extended — your fingers close easily. Now bend your wrist forward and try again. Your fingers can't come all the way through. That's active insufficiency showing up in real time. It's not some abstract textbook concept. It's a mechanical limit happening inside your hand right now. The reason it matters extends well beyond curiosity. If you're programming training, rehabilitating an injury, or just trying to understand why a certain position feels weak or restricted, knowing which muscles are reaching their limit changes everything about how you approach the problem. Most people treat muscle tightness as a stretching issue. Often it's not. It's insufficiency, and the solution requires changing the joint geometry instead of forcing range of motion.
Active Vs Passive Insufficiency: The Core Difference
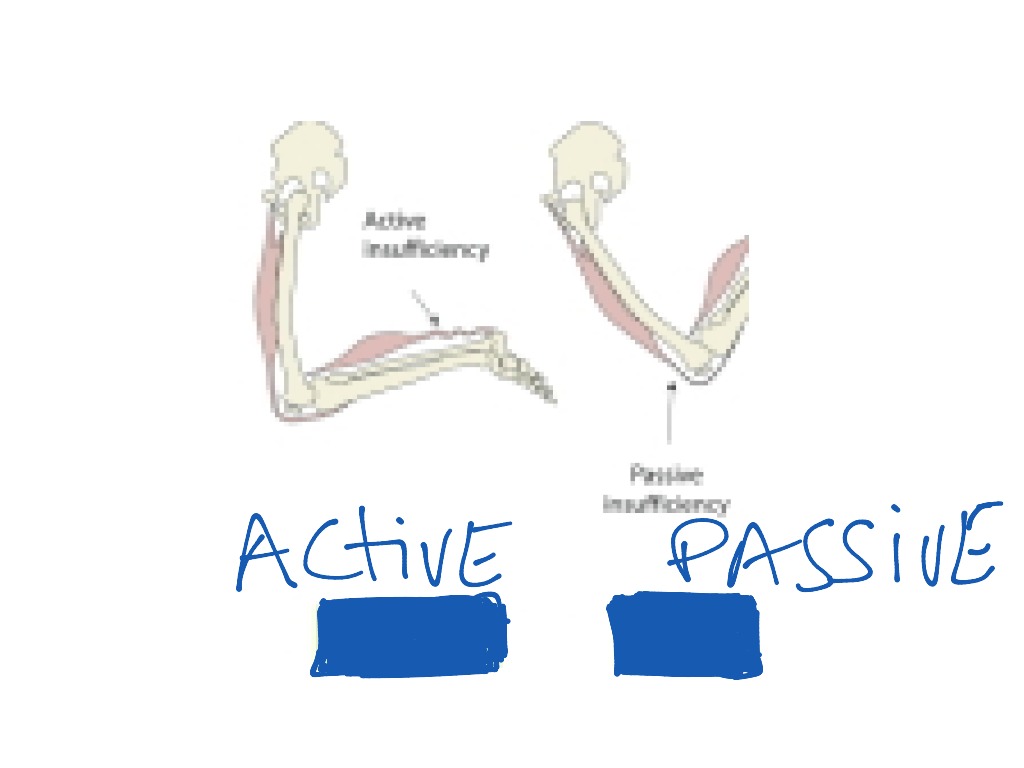
Active insufficiency occurs when a multi-joint muscle can no longer generate meaningful tension because it has shortened too much across all the joints it crosses. The muscle is contractually maxed out. Think of the biceps brachii during a full elbow flexion combined with a fully bent wrist. The muscle is so short that it literally cannot pull any harder. That's active insufficiency. Passive insufficiency is the mirror image. It happens when a multi-joint muscle gets stretched too far across multiple joints and reaches its elastic limit. You can't extend further not because of weakness, but because the tissue itself is now blocking the movement. The hamstrings are a classic example. Try touching your toes while someone straightens your knee — your hamstrings will fight you on both the hip flexion and the knee extension simultaneously. The muscle is passively shortened at the hip and passively lengthened at the knee, and somewhere in that combination it simply won't go further. Both concepts apply to any muscle crossing two or more joints. Single-joint muscles like the brachialis don't have this problem. The gastrocnemius, rectus femoris, and biceps brachii all do, and you'll see the effects constantly in athletic movement and clinical assessment.
How to Identify Which Type You're Dealing With
The practical test is straightforward. Have the person assume a position that challenges the muscle at all its crossed joints, then ask them to either contract or stretch through the end range. If they can't produce force through the movement but the joint itself moves freely through its available range, you're looking at active insufficiency. The muscle is too short to contribute. If they can contract fine but can't stretch further into the position, that's passive insufficiency. The tissue is too taut to yield. I ran into a genuine edge case with a client who was a competitive rock climber. She had persistent discomfort in her finger flexors during crimp holds, and every stretching protocol I tried failed to improve her grip endurance. The issue wasn't tightness in the traditional sense. She was routinely gripping with her wrist in extreme extension, which placed her finger flexors in a state of chronic active insufficiency. The muscle was already shortened across the wrist joint before her fingers even engaged the hold. I switched her to a hangboard protocol with a neutral wrist position and had her focus on maintaining slight wrist extension only during the actual grip phase. Her endurance improved noticeably within three weeks. The fix wasn't more stretching. It was changing the pre-load position so the muscle wasn't already compromised before the work began. Another common pitfall I see constantly is misidentifying passive insufficiency as tightness that needs aggressive foam rolling or PNF stretching. The lumbar spine often gets caught in this. A client comes in with limited forward fold range, and the instinct is to hammer the hamstrings. But if the limitation is actually the erector spinae or the latissimus dorsi reaching their passive length across both the hip and shoulder, then stretching the hamstrings alone produces minimal change. The restriction lives elsewhere in the kinetic chain.
Get the Full Details

Practical Workarounds for Active Insufficiency
The main workaround for active insufficiency is simple: change the position of one of the joints so the muscle isn't shortened across all of them at once. In the bench press, for instance, the pectoralis major crosses both the shoulder and the sternum. At the bottom of the press with the arm fully abducted and externally rotated, the pec is actively insufficient — it can't generate full force. Narrowing the grip slightly or keeping the elbows closer to the torso shifts the load onto the triceps and anterior deltoid, reducing the pec's involvement at that weak point. That's not a hack. That's biomechanics working exactly as designed. In rehabilitation, active insufficiency matters enormously for anyone recovering from a stroke or neurological injury where voluntary muscle activation is already reduced. Asking a patient with weakened wrist extensors to also extend their fingers against resistance often fails because the extensor digitorum is actively insufficient when the wrist is already extended. The solution is to keep the wrist in slight flexion during finger extension drills. The muscle operates from a better length-tension relationship and can actually produce force. This detail separates programs that show real progress from ones that stall out completely.
Where These Concepts Break Down or Mislead
Here's what most guides won't tell you. Active and passive insufficiency are useful frameworks, but they're not precise enough for every situation. The length-tension relationship of a muscle doesn't change at a single joint angle. It shifts gradually, and individual anatomy varies significantly. Two people with identical range of motion will experience insufficiency at different joint positions because of differences in muscle belly placement, tendon length, and fascial connections. Also, insufficiency isn't always a problem. In some movements, it's the entire point. The snatch in Olympic weightlifting deliberately uses active insufficiency in the triceps at the top position to lock out the bar. The muscle is shortened, but the skeletal structure takes over the load transfer. You're not fighting insufficiency there. You're using it. Finally, there's a blind spot in how these concepts are taught. People memorize the definitions and then apply them rigidly. They assume any limitation in a multi-joint position is insufficiency-related, when often it's joint capsule restriction, neural tension, or bone-on-bone contact. The finger flexor example from the climbing client is one thing. But if someone can't do a deep squat because their tibial plateau contacts the femoral condyle, no amount of hamstring stretching or wrist positioning will fix it. Insufficiency explains soft tissue limits. It doesn't explain structural ones. Knowing the difference saves a lot of wasted effort.
The takeaway is practical. Watch the movement. Identify which joints are involved. Test whether the limitation is contractile or elastic. Adjust one joint position at a time and observe the change. If the range or force improves, you've found the insufficiency factor. If it doesn't, you're dealing with something else entirely, and continuing to treat it as insufficiency will only delay the actual solution.


