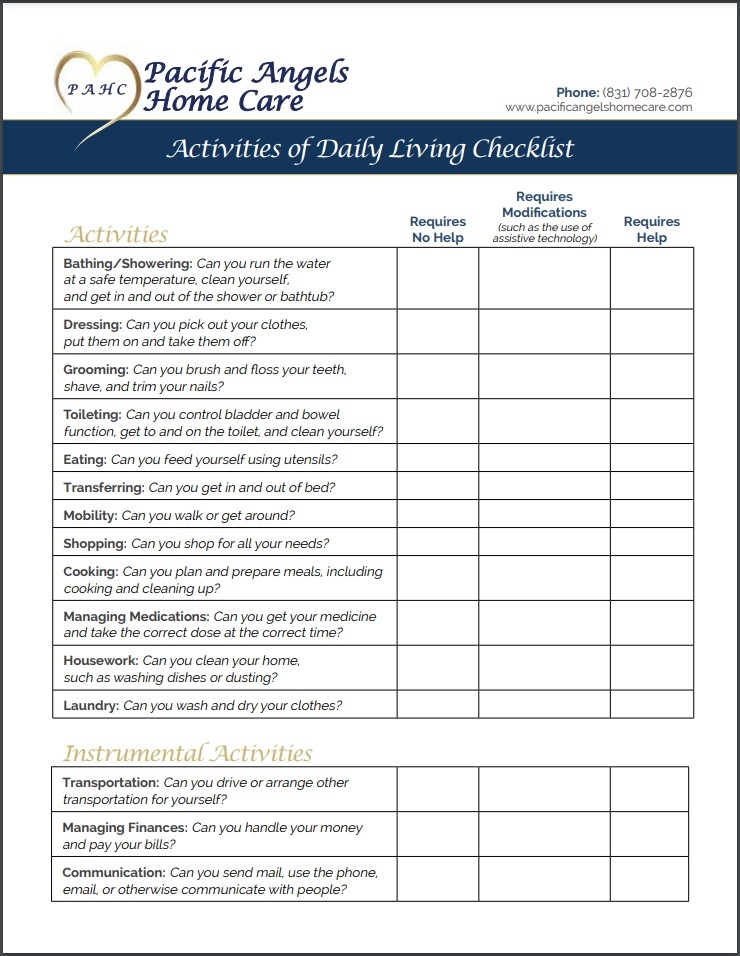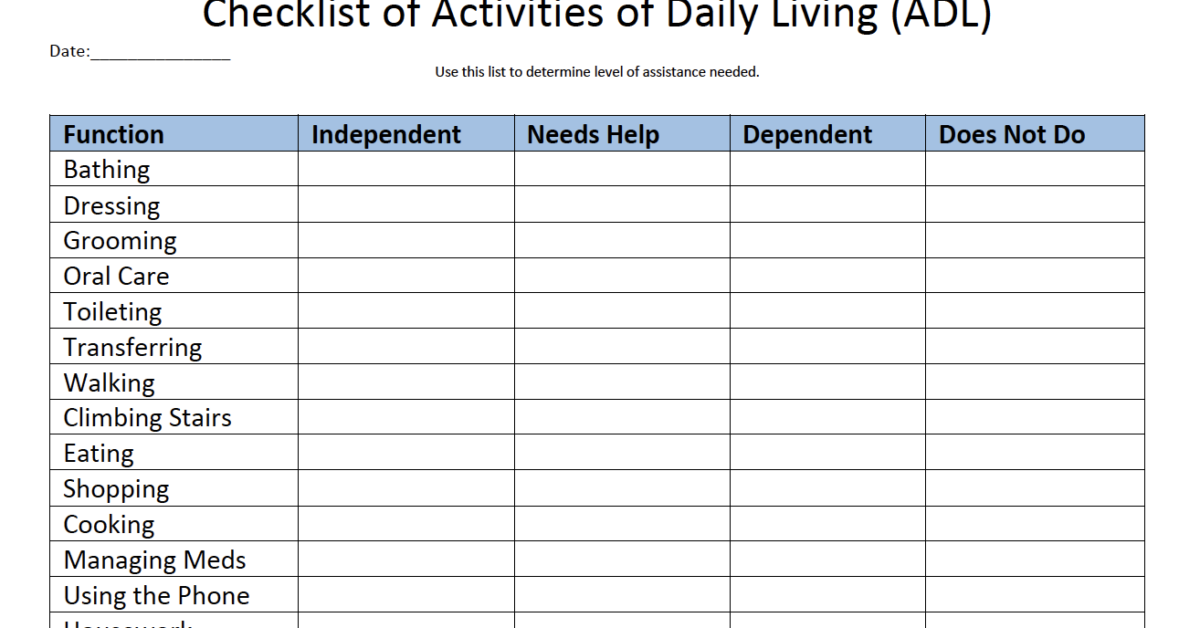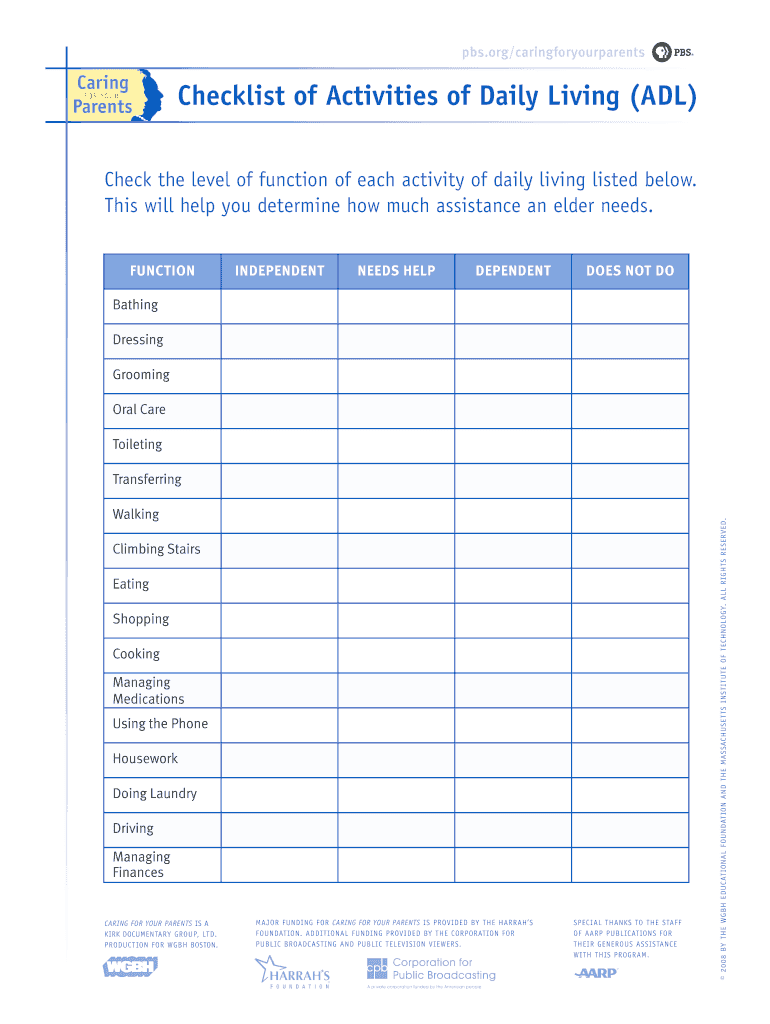
What ADL Worksheets Actually Are
They're structured forms that track whether someone can perform basic self-care tasks independently, with assistance, or not at all. Most people encounter them through occupational therapy evaluations, disability applications, or long-term care intake paperwork. The standard ones cover bathing, dressing, eating, toileting, transferring, and continence. Sometimes mobility gets added as a seventh item. The raw concept is simple. The execution is where things get messy.
Activities Of Daily Living Worksheets: How to Actually Use Them
Here's the thing nobody tells you upfront: the way you score the worksheet changes everything depending on who's filling it out and why. A therapist doing a formal assessment uses one framework. A family member filling something out for an insurance claim uses another. Mixing those up produces inconsistent results, and inconsistency is what gets claims denied. I worked with a case where a geriatric rehab facility was using a 1987 Katz Index worksheet for a 2023 VA disability claim. The scoring criteria had been updated three times since then. The patient got scored as partially dependent in toileting, but under current criteria, that same level of function would've been rated independently with supervision. One checkmark difference on a piece of paper changed the entire benefit calculation. The fix was straightforward but not obvious: pull the current version from a recognized source, verify the scoring key matches the date of assessment, and make sure every rater on your team is using the identical form. I started running a quick comparison sheet — old form versus new form side by side — and flagged any scoring gaps before submission. Saved us from at least three rejections in a single quarter.
To actually fill one out properly, you need to do an observational assessment, not just ask questions. People will tell you they can bathe themselves when they can't. They'll say they're fine dressing alone when they're missing buttons and putting shoes on the wrong feet. Watch them do it, or watch video evidence if you can't be there in person. Score each domain with clear behavioral anchors. Instead of writing "needs help," specify what kind of help: verbal cueing, partial physical assistance, or total dependence. That detail matters when someone disputes the rating later.
Get the Full Details

Where This Breaks Down
ADL worksheets have real limitations that most people overlook. They don't capture instrumental activities — meal prep, medication management, financial tasks, transportation. Someone might score independent in all six basic ADLs and still be completely unable to live alone because they can't manage their prescriptions or cook without burning the kitchen down. Those are IADLs, and they deserve their own separate assessment. Another issue: the cognitive component is almost invisible on most standard forms. A patient who can physically feed themselves but forgets to eat until they're dehydrated still scores as independent on the eating domain. That's not a flaw in the worksheet necessarily, but it's a flaw in how people use them without pairing the assessment with a cognitive screen. For that gap, pair your ADL worksheet with something like the Functional Independence Measure or the Lawton IADL Scale. Neither is perfect, but together they give you something closer to a real picture. The FIM adds motor and cognitive subscores. The Lawton covers ten instrumental tasks with clear dependency levels.
Getting the Right Forms
The Katz Index is public domain. You can download it from most hospital system websites or the CDC's public health repositories. The Barthel Index has more restrictive licensing through some publishers, so check before you distribute it commercially. The FIM is owned by URSI and requires a license for widespread use, though individual clinicians often get it through their employer's subscription. If you're building your own worksheet from scratch, stick to the six core domains: bathing, dressing, eating, toileting, transferring, and continence. Use a three-point scale: independent, needs assistance, dependent. Add a notes column for qualitative detail. Keep it to one page. Nobody fills out a ten-page ADL assessment honestly, and even if they do, the data quality drops off after the first section. The practical version I ended up using for years was a laminated one-page sheet with a dry-erase marker pocket. The patient or caregiver marks their level for each activity, and the clinician adds observations in the notes column during the visit. It takes about twelve minutes to complete. Paper forms in clipboards in waiting rooms average twenty-five to forty minutes depending on literacy level and comprehension issues. Time savings there are real and noticeable.