Breaking Down Tasks Before You Throw Them at Patients
I spent three weeks trying to figure out why my stroke rehab patient kept failing at washing dishes, and it turned out the problem had nothing to do with his hand function. He could grip, he could reach, he could follow three-step directions. What he couldn't do was stand long enough to rinse while also monitoring the water temperature and remembering which side of the sink held the soap versus the rinse water. The dish itself was never the issue. This is what activity analysis looks like when it actually matters in a clinic instead of a textbook. The method is straightforward in theory but easy to botch in practice. You take a daily task and systematically break it into component demands — physical, cognitive, sensory, social, and environmental — then match those demands against what the patient can realistically handle. The goal isn't to simplify the task for them immediately. It's to understand exactly where the breakdown happens so you can intervene precisely.
Activity Analysis Occupational Therapy Method
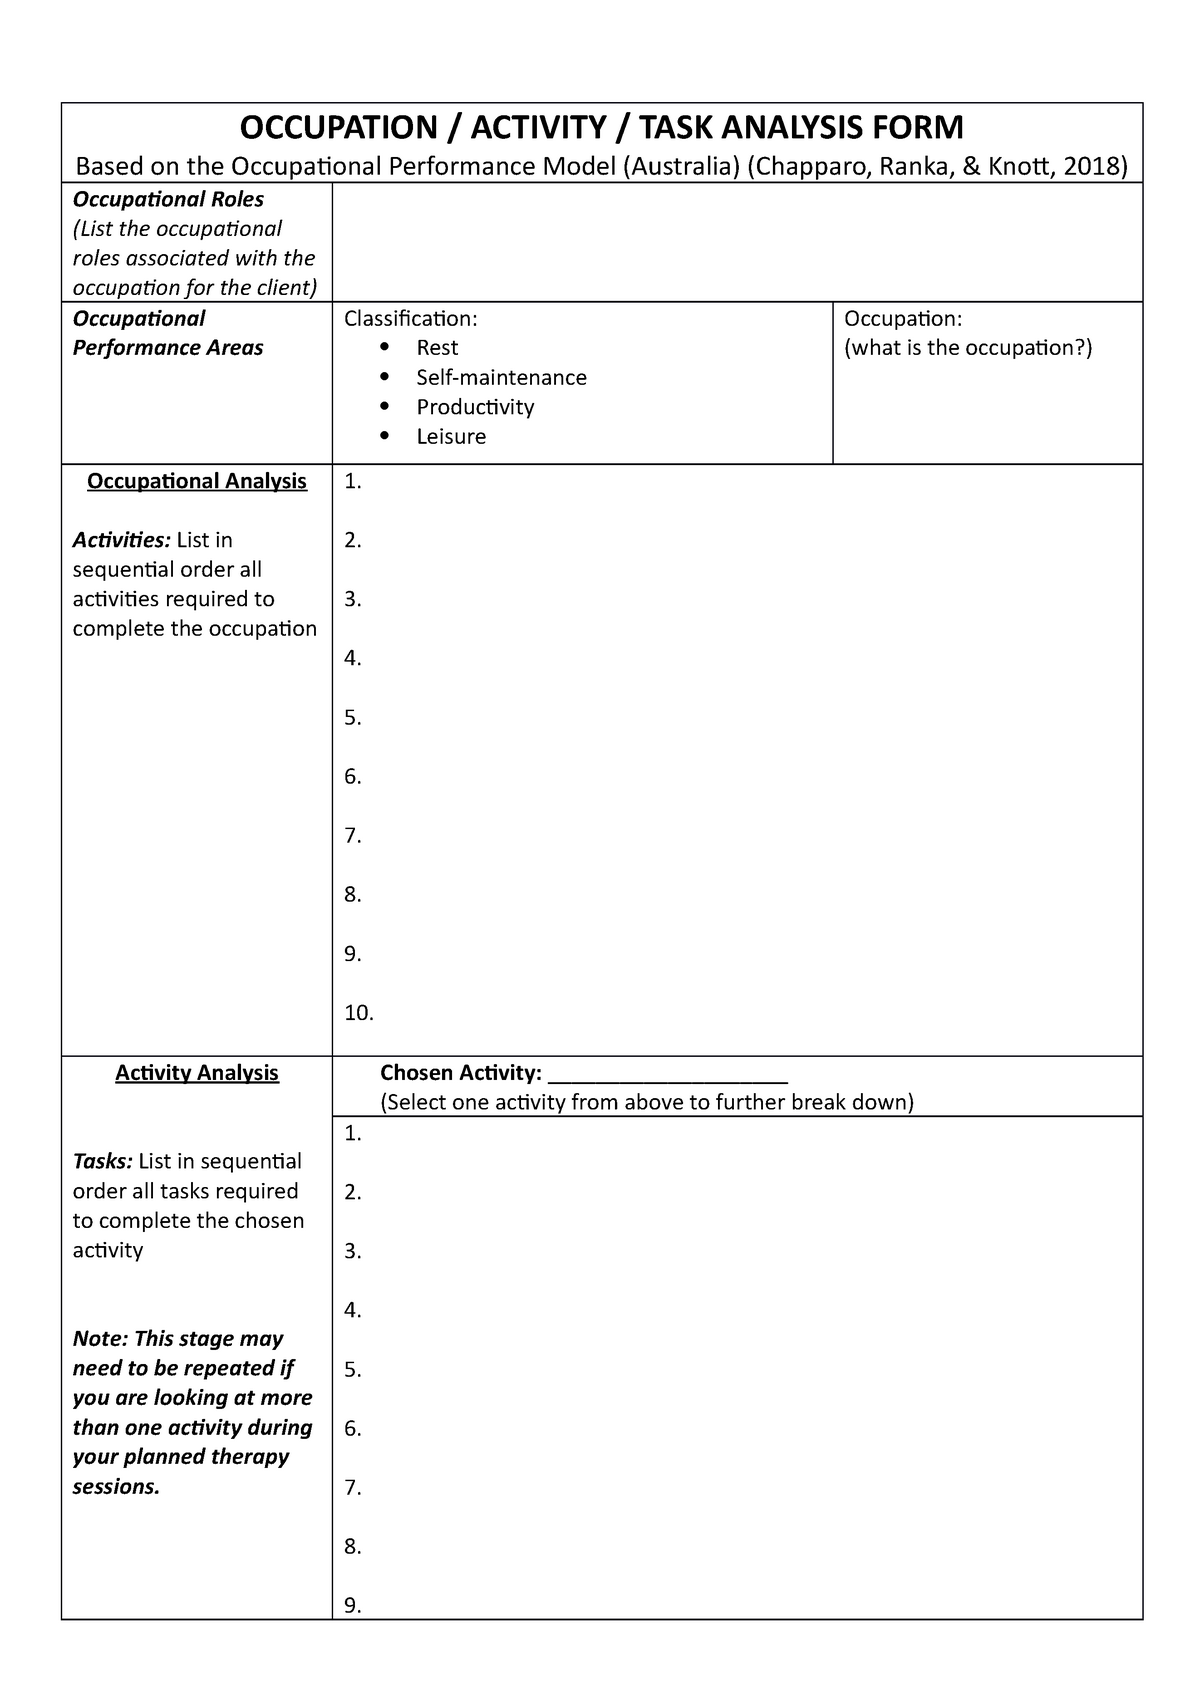
Here's how I actually do it without wasting the entire session. First, I identify the specific activity. Not "dressing" but "putting on a button-down shirt while standing." Specificity matters because a patient might manage one but not the other, and lumping them together gives you garbage data. Next, I map the demands. Physical demands include posture requirements, duration of sustained effort, strength needed, range of motion, balance, and fine or gross motor control. Cognitive demands cover sequencing, memory, attention, judgment, problem-solving, and processing speed. Sensory demands involve vision, proprioception, tactile feedback, and hearing. Environmental demands are usually the part people skip — lighting conditions, surface stability, temperature, noise, spatial constraints, and the tools available. Then I compare those demands against the patient's baseline assessment data. If there's a gap, I don't just modify the activity. I determine which specific demand is causing the failure and whether it's fixable through adaptation, equipment, or graded exposure. This usually cuts the process down from about two hours of fumbling to roughly twenty minutes if you've got a solid template already set up in your notes system.
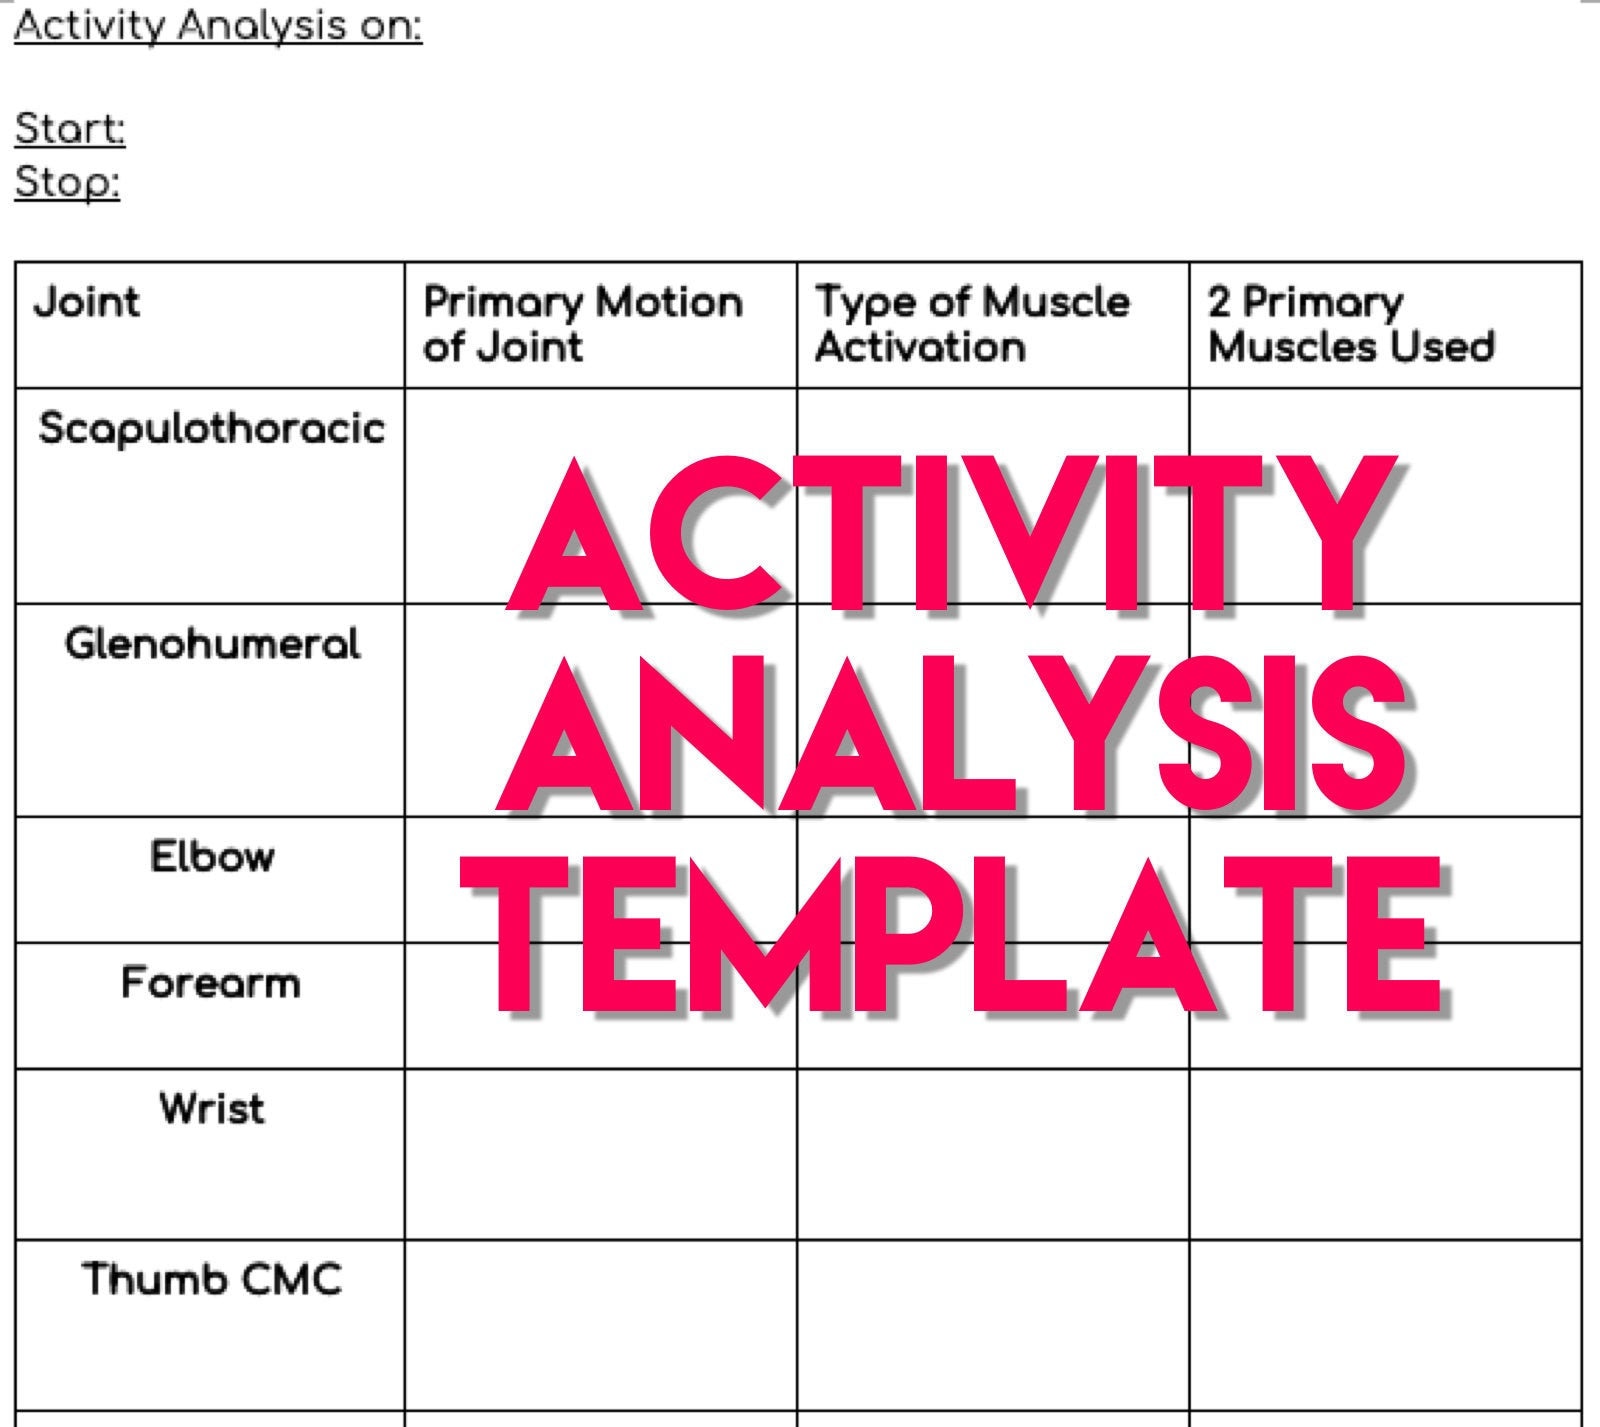
For a kitchen sink activity, which is one of the more common ones I analyze, the demand profile looks like this: standing for 10 to 15 minutes, bilateral coordination for scrubbing, weight shifting to reach the drying rack, working memory to track dirty-to-clean sequencing, heat perception to avoid scalding, visual discrimination to check cleanliness, and environmental awareness around wet floors and sharp utensils. A patient with right-sided hemiparesis and mild spasticity might manage the physical portion but fail on the bilateral coordination and the sequential memory demands simultaneously. That's the compounding effect nobody warns you about in grad school.
Get the Full Details
Common Frameworks and Tools
You'll run into the Canadian Occupational Performance Measure, the Occupational Therapy Practice Framework, and sometimes the Activity Card Sort depending on your setting. I use a modified version of the OTRF-4 task analysis sheet for most outpatient work. It forces you to list every sub-component rather than glossing over it, which catches things you'd otherwise miss. The AMPS is more comprehensive but requires certification and takes considerably longer to administer properly. For acute care or short-term outpatient, it's usually overkill. One thing that trips people up consistently is treating activity analysis as a one-time event. It isn't. A patient's ability to perform the same activity can change dramatically between Tuesday and Thursday during rehab. I re-analyze at minimum every two weeks for acute cases, and whenever there's a noticeable shift in performance pattern. Documentation burden is real, but skipping it means you're guessing instead of treating. The biggest blind spot I see in beginners is analyzing the activity in isolation from the context. A task that fails in a cluttered, noisy shared kitchen might succeed in a quiet, organized space with adapted tools. The activity itself hasn't changed. The environment has. If you only look at the patient's deficits without accounting for environmental modifiers, your analysis will point you toward unnecessary compensation strategies when the actual solution might be rearranging the workspace or changing the sequence of steps.
Another counter-intuitive finding: higher-complexity activities don't always benefit from more analysis. Sometimes a 50-item breakdown paralyzes both the therapist and the patient. For routine ADLs like brushing teeth or using a microwave, a streamlined checklist with just the critical failure points identified is faster and more useful than a full demanbd profile. Reserve the deep analysis for activities where the patient has already demonstrated consistent difficulty despite basic modifications.
When It Breaks Down
Activity analysis isn't a universal fix. It struggles significantly with patients who have severe cognitive impairments or fluctuating conditions like MS or traumatic brain injury, where performance isn't consistent enough to map reliably. In those cases, direct observation over multiple sessions with standardized measures like the Wolf Motor Function Test or the Action Research Arm Test tends to give you more actionable data than a paper-based task breakdown ever will. The method also assumes you have access to the actual environment where the activity takes place. If a patient lives in a shared group home with unpredictable scheduling and limited kitchen access, analyzing the "ideal" kitchen activity won't predict their real-world performance at all. I learned this the hard way with a patient who passed every simulated kitchen task in the therapy gym but couldn't manage the same steps at home because the layout was completely different and the lighting was poor. We ended up doing a home visit modification instead, which turned out to be far more valuable than another round of simulated analysis. Cultural considerations also matter and are frequently overlooked. An activity analysis built around a standard American kitchen won't translate to someone whose cooking methods, tools, and meal preparation patterns are culturally different. I had a patient whose family prepared food using a floor-level cooking setup that looked nothing like the standard kitchen model. My initial analysis was completely irrelevant until we observed the actual setup and rebuilt the breakdown from there.
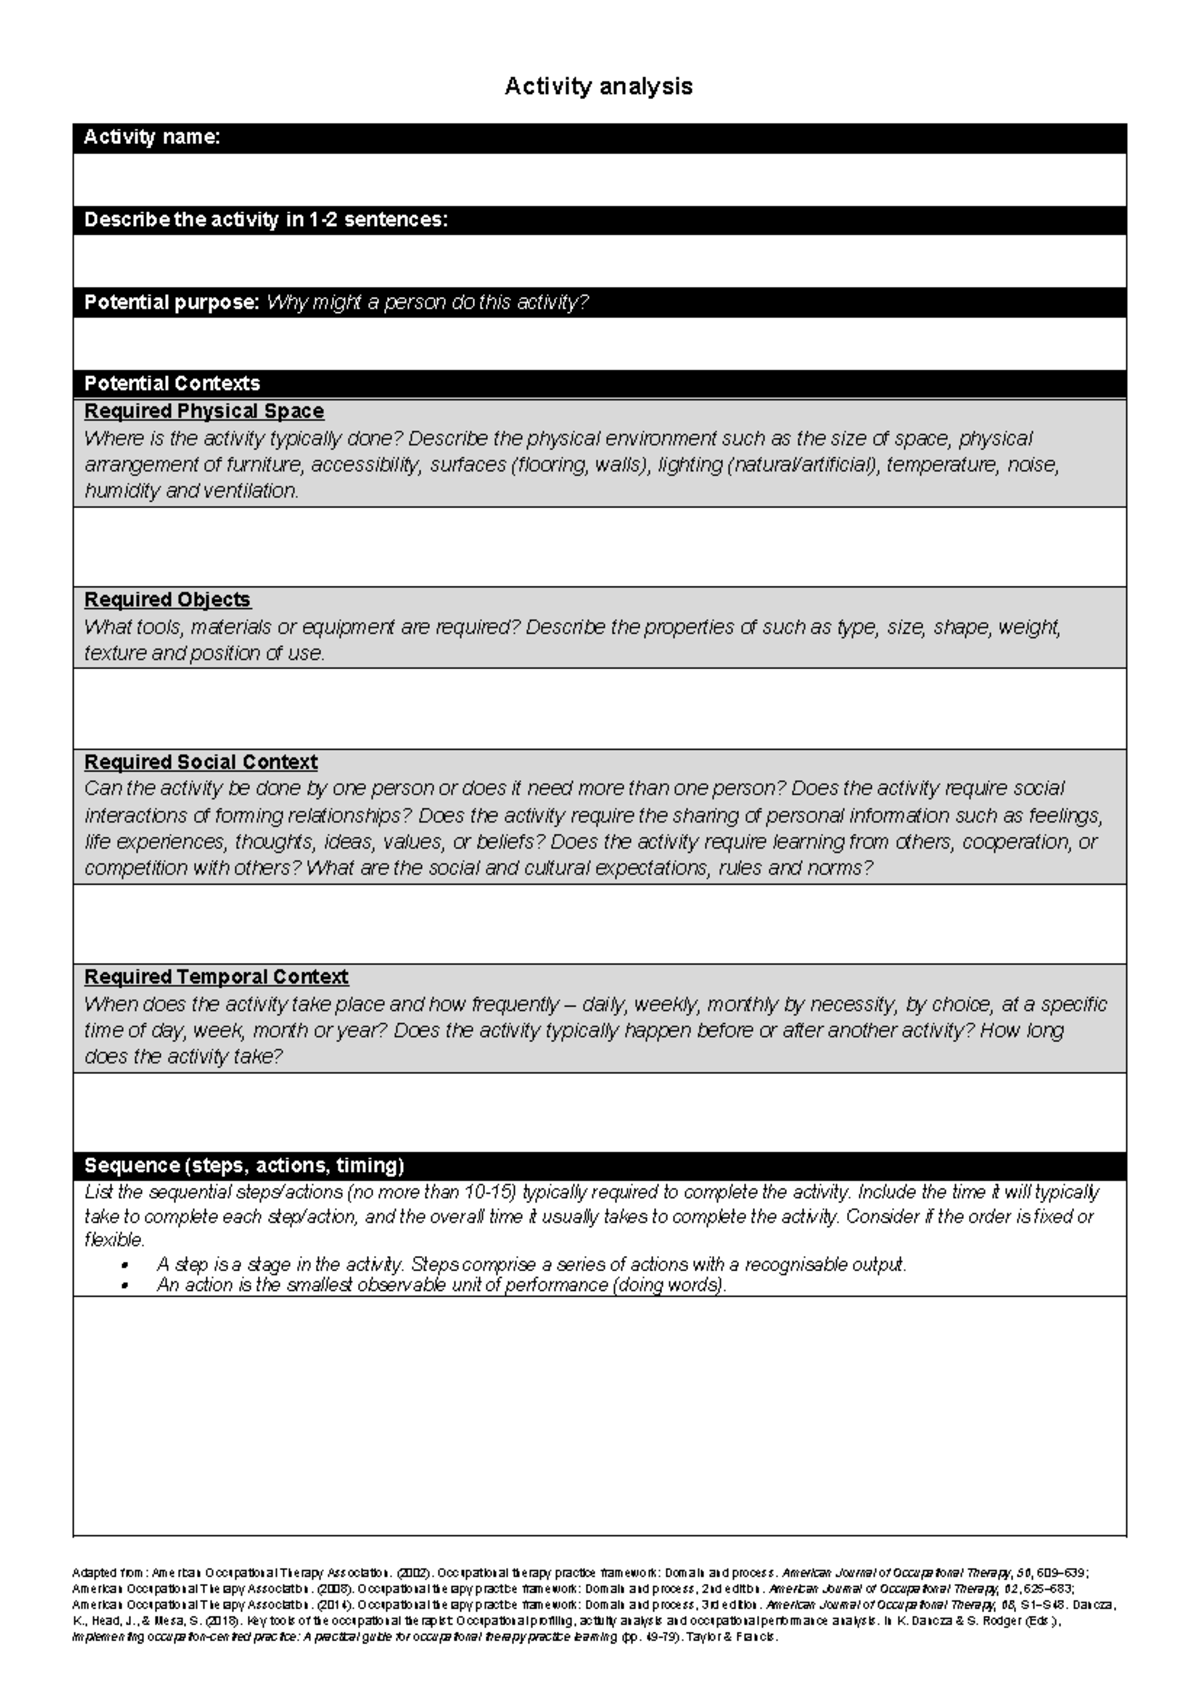
If you're looking for structured templates to get started, the AOTA website has downloadable activity analysis worksheets based on the OTPF-4, and the OTRF-4 manual includes standardized scoring sheets that work well for documentation. The AMPS has its own proprietary scoring system that requires training. For quick clinical reference without the administrative overhead, I keep a simplified demand-mapping table in my notes app that covers the main categories — physical, cognitive, sensory, environmental — with checkboxes for common patient limitations. Takes about five minutes to fill out per activity and captures enough detail to make meaningful intervention decisions without drowning in paperwork.