What Actually Happens When You Practice As An ACNP
Most people think scope of practice is just a set of rules you read in a handbook and follow. It isn't. It's a constantly shifting conversation between your state board, your employer, your attending physicians, and occasionally a hospital legal team that didn't sleep last night. I've been working in acute care for a while now. I started as an RN, went back for my DNP, and have since practiced across multiple states with different regulations. Here's what you actually need to know, without the brochure version.
Acute Care Nurse Practitioner Scope Of Practice
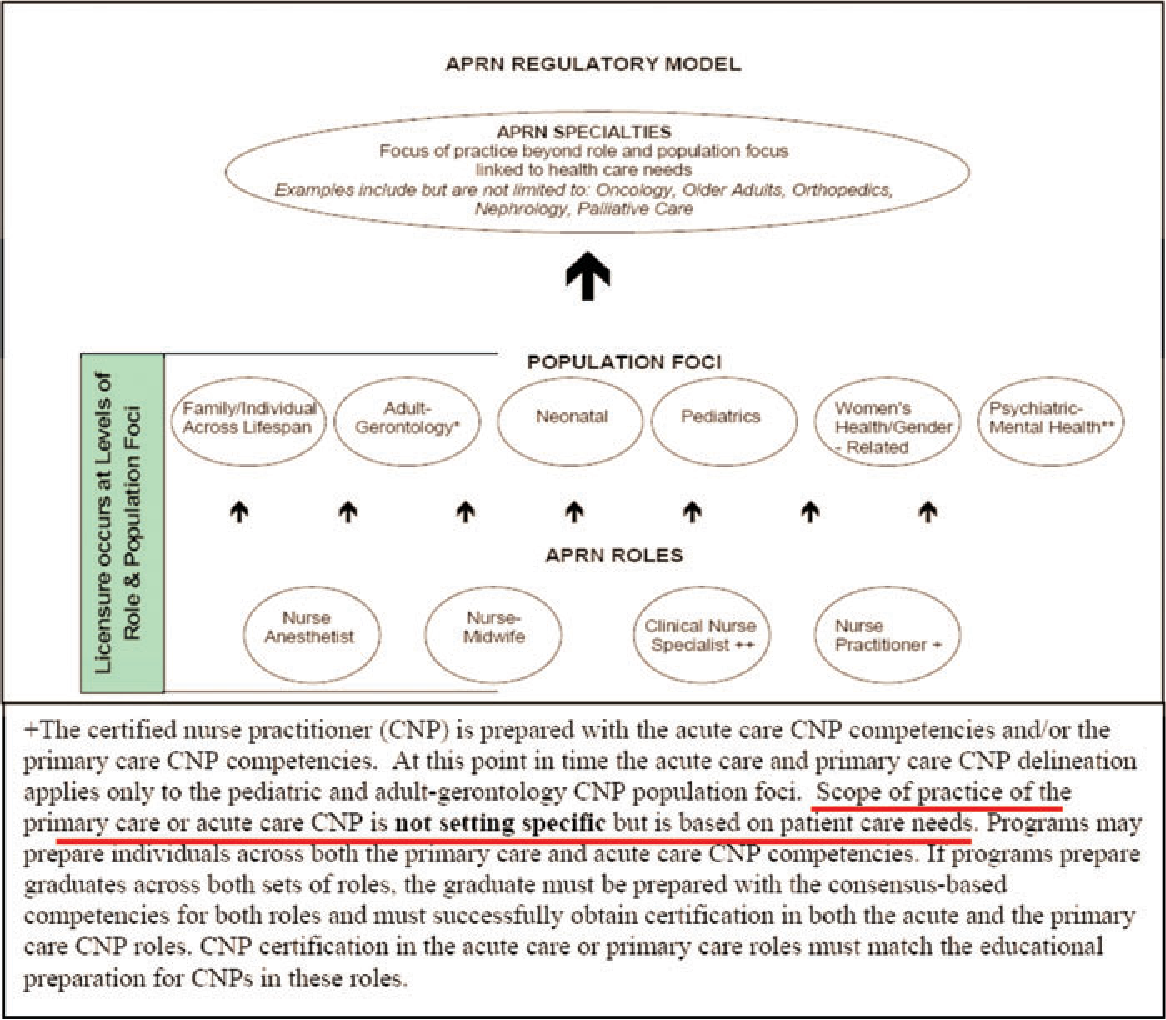
Your formal scope comes from two places: your state's Nurse Practice Act and your national certification body (AANP or ANCC). The state determines what you can legally do. The certifying body determines what you're educated to do. When these two conflict, the state always wins, and it usually wins by being more restrictive. In full-practice-authority states, you can evaluate, diagnose, order diagnostics, interpret results, initiate and manage treatment, and prescribe medications including controlled substances without physician oversight. That's the baseline. In restricted states, you need a collaborative agreement with an MD or DO. Some states require monthly chart review. Some require a certain percentage of charts to be co-signed. Some require physical presence in the same building. The requirements range from mildly annoying to functionally impossible depending on where your job is located.
One thing nobody tells you before you graduate: your scope also includes the responsibility to know when something falls outside your scope. That sounds obvious until you're at 3 AM in the ICU and a patient decompensates and your attending is in another state and you're the only licensed provider physically present. You don't need to do everything yourself. You need to know what you can stabilize and what requires immediate escalation. I'll give you a specific example because this matters more than any textbook definition. Early in my practice, I had a post-cardiac surgery patient who developed sudden atrial fibrillation with rapid ventricular response. Blood pressure was stable but trending down. My protocol said to notify the surgeon. The surgeon was in surgery. The hospital's on-call coverage structure was unclear. I ended up starting a diltiazem drip and calling hospitalist coverage because I realized the surgical team wasn't going to be available for two more hours. The workaround I developed and now use universally: before taking any position, I get a written copy of the hospital's advanced practice provider (APP) protocol for post-operative complications. I then verify exactly who covers what shift, how to reach them after hours, and whether there's a standing order set I can activate independently. This took me about twenty minutes during orientation and has saved me from approximately four serious problems since. Not exaggerating.
Get the Full Details

Prescriptive Authority Is Where Things Get Messy
Controlled substance prescribing varies dramatically by state and requires a DEA registration in addition to your state NP license. Some states require a separate state-controlled substance registration. Some states limit which schedules you can prescribe. Some states require a specific number of CME credits in pharmacology or pain management before you can prescribe Schedule II medications. Common pitfall: your DEA license is federal. Your state prescription monitoring program (PMP) access might not automatically extend to your electronic health record system. I once prescribed a legitimate opioid medication and almost got flagged because the PMP query didn't populate in my clinical workflow. I now run a manual PMP check every time I prescribe any controlled substance regardless of what the system shows. Takes ninety seconds. Another counter-intuitive detail: many hospitals credential APPs for formulary privileges separately from prescriptive authority. You can have the legal right to prescribe an antibiotic but not have hospital formulary access to it. I learned this the hard way when I tried to order a specific antifungal for an immunocompromised patient and my order got blocked by the pharmacy because my privileges didn't include it. Solution: get your formulary restriction list during orientation and keep it somewhere accessible.
Procedural Scope Varies More Than You'd Expect
ICU procedures like central line placement, arterial line placement, chest tube insertion, and intubation are within typical ACNP scope, but individual hospital privileges determine whether you can actually perform them. Some hospitals require competency verification through a structured program with procedural logs. Others rely on your training documentation alone. I've worked at hospitals where my central line insertion privileges were limited to subclavian access only, while other APPs had femoral privileges. I've also worked at places where we couldn't place central lines at all and had to request a physician. The variation is real and it's not always written down anywhere obvious. Downside of this system: you may graduate fully trained in fifteen procedures and only be credentialed for three at your first job. This doesn't mean you're incompetent. It means credentialing committees are often risk-averse and their standards don't necessarily align with your actual training. The workaround is carrying your competency documentation from your DNP program and being willing to repeat skills validation even when you've already done it elsewhere.
Supervision Requirements Aren't Always What You Think
"Collaborative agreement" doesn't mean the same thing in every state. In some states it's a signed document you file with the board. In others it requires monthly chart review with specific documentation. A few states recently moved to "physician availability" models where the physician doesn't need to review charts but must be immediately available for consultation. The practical implication: your collaborative agreement should be reviewed annually, not just when your license renewal comes up. I've seen agreements that lapsed without anyone noticing because the hospital's credentialing office handled it differently than the state required. One state required renewal every two years with CE documentation. Another required annual renewal with no additional documentation. Mixing these up created a gap period where I was technically practicing without a valid agreement. Honest assessment of limitations: the current scope-of-practice framework has a structural problem. It was designed for a model of healthcare delivery that assumed NPs would primarily work alongside physicians in clinic settings. Acute care doesn't fit that model well. ICUs, EDs, and step-down units operate on different timelines with different decision-making structures. You'll find yourself navigating situations where the letter of your scope doesn't address the reality of the clinical scenario, and you're left to make judgment calls without clear institutional guidance.

This is why experienced ACNPs develop a habit of documenting their clinical reasoning thoroughly. Not because they expect to get in trouble, but because when questions arise about whether a decision fell within appropriate scope, having a clear paper trail of your thought process protects everyone involved. The best resource I found for understanding where the actual boundaries are wasn't a textbook or a state board document. It was talking to other APPs who'd been practicing in the same system for five or more years. They knew which policies were enforced, which were suggestions, and which ones the administration had quietly stopped caring about. That informal knowledge network is worth more than any formal scope document.