Getting Started With Acute Care PT Evaluations
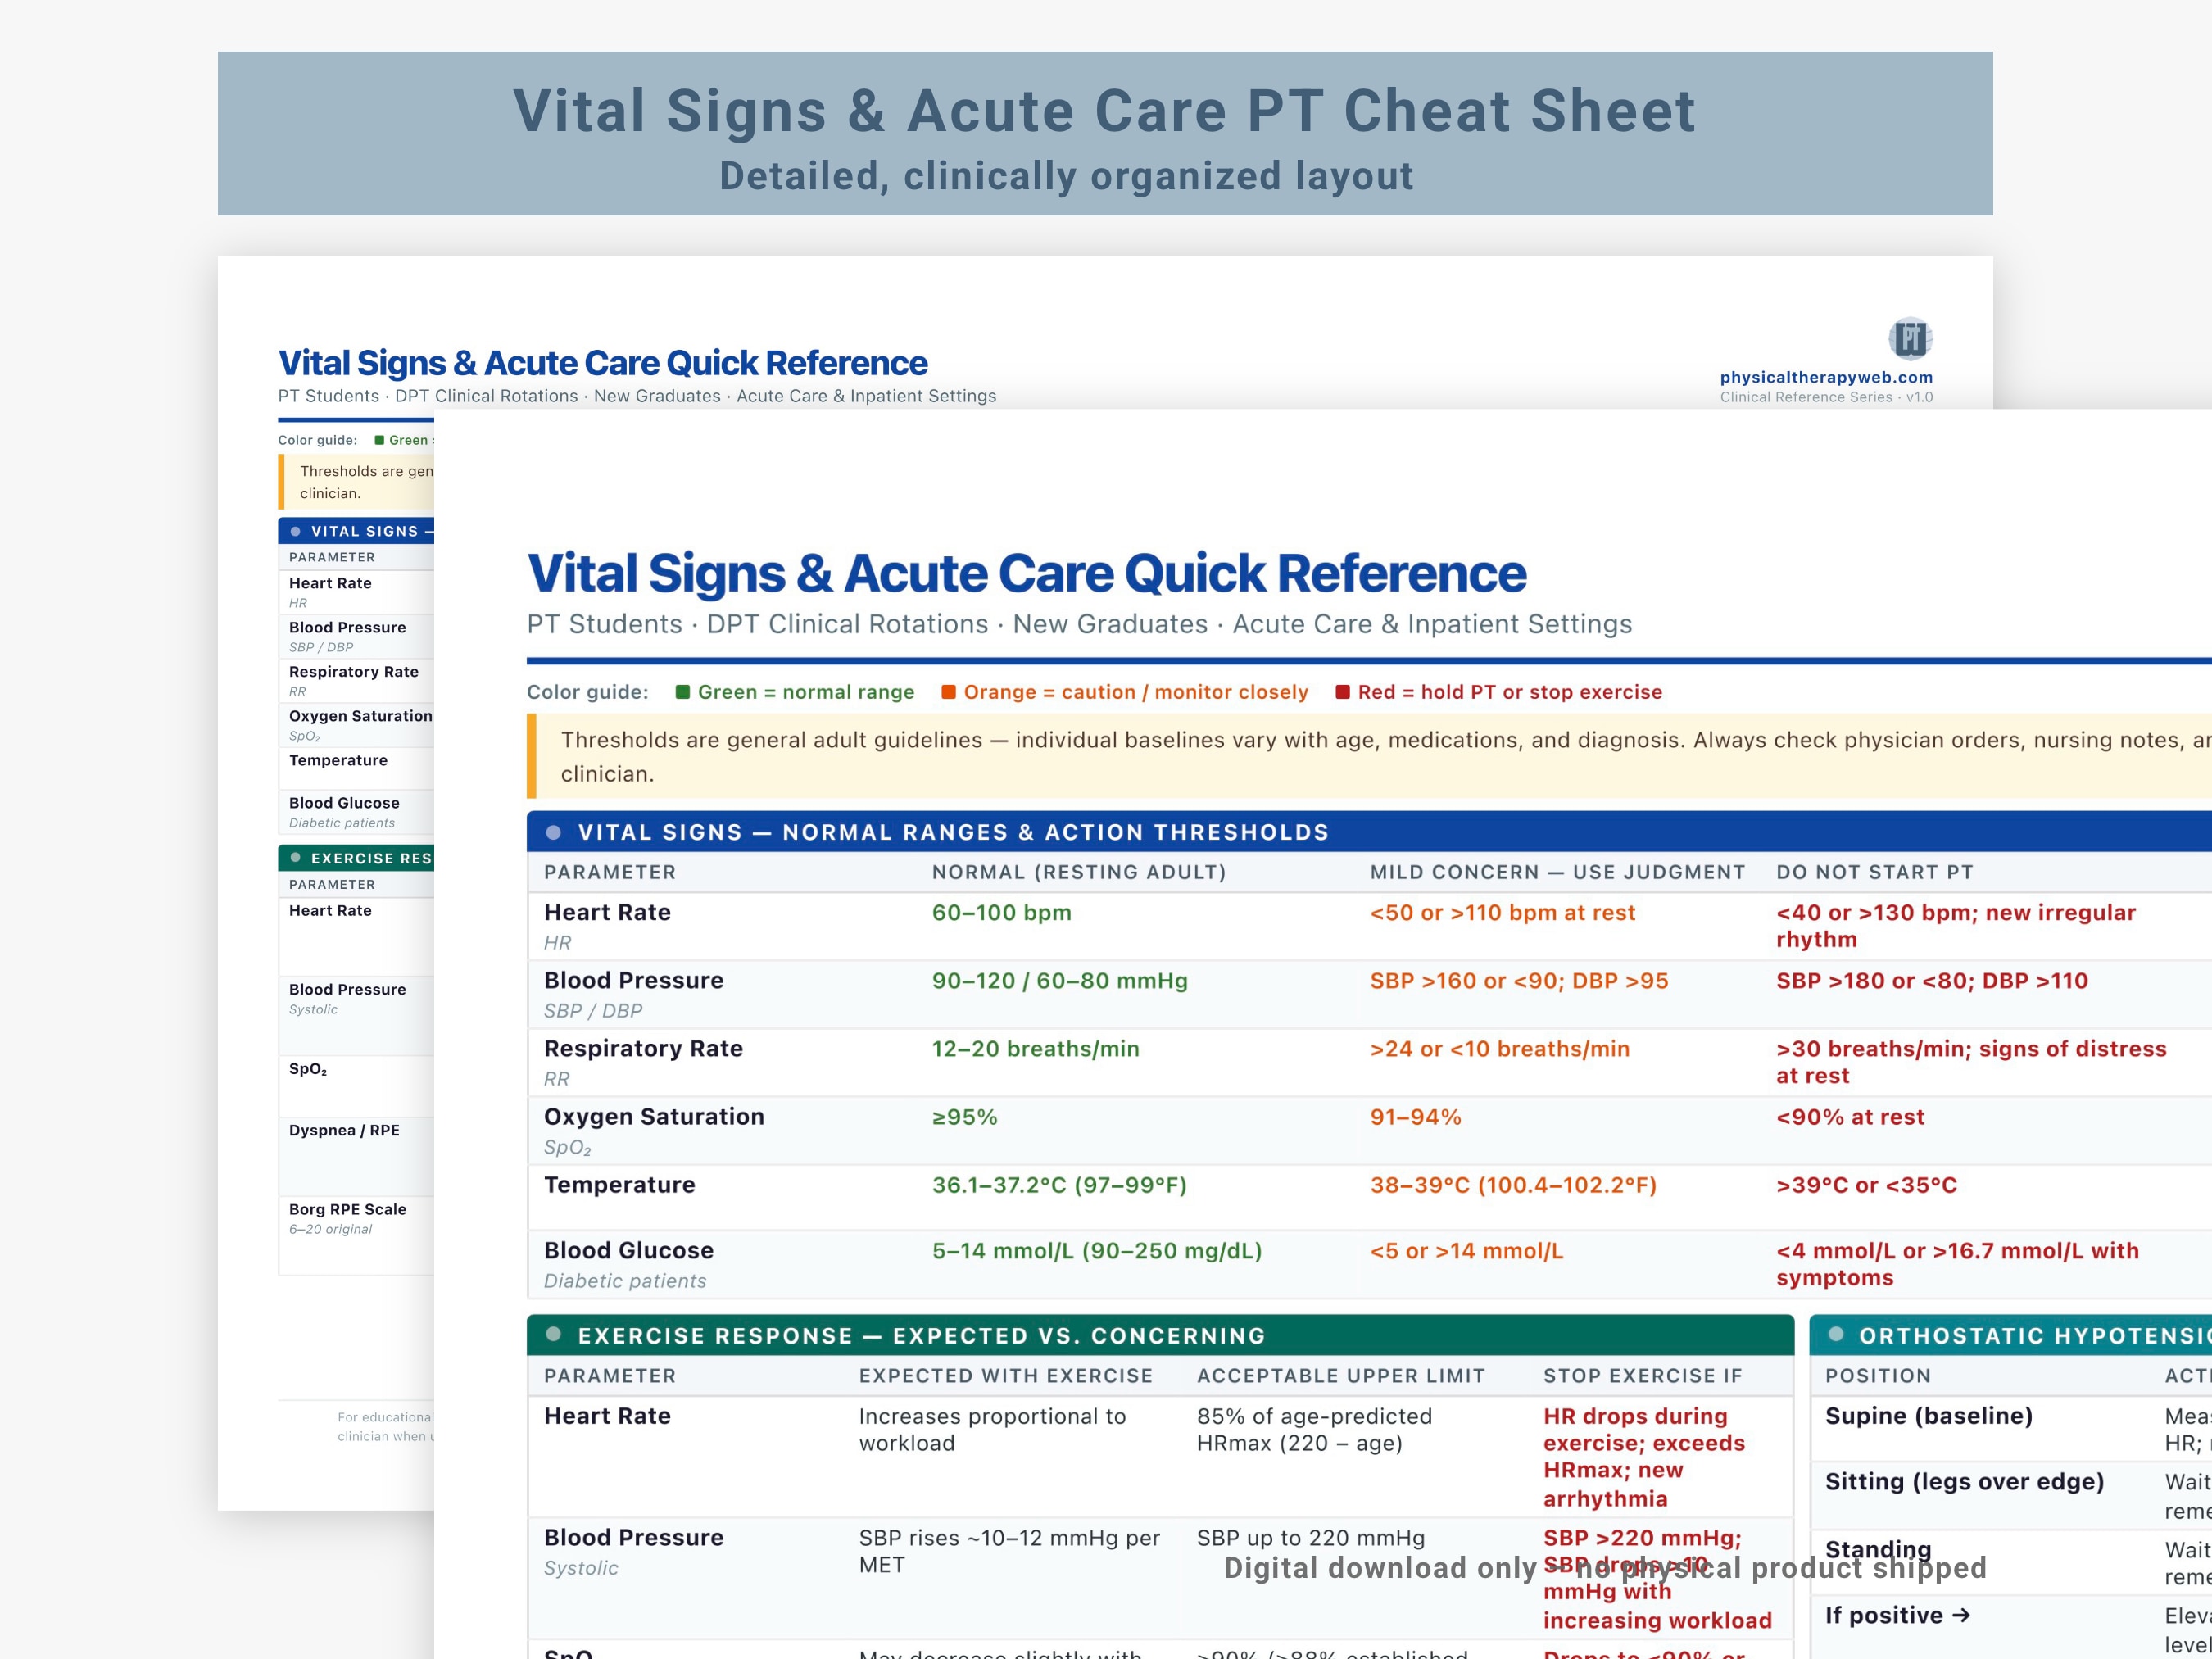
Most acute care physical therapy work happens in hospitals where patients are sick, unstable, and surrounded by machines that beep at random intervals. The job isn't about fancy techniques or treatment protocols. It is about figuring out whether a patient can safely move, who they need to move with, and where they go next. That is it. Everything else is secondary. I have spent years doing this work across trauma units, cardiology wards, and medical-surgical floors. The biggest mistake I see new therapists make is treating every patient the same. They pull out the same evaluation checklist and run through it like a script. Some patients tolerate that fine. Others become confused, fatigued, or drop their blood pressure halfway through because the therapist did not adjust for their actual clinical status.Acute Care Physical Therapy Cheat Sheet materials are useful when they are actually useful. Too many of them out there are generic templates copied from a textbook that have never been tested on a real floor. The ones that work are the ones you build yourself based on what you actually encounter day to day.
Core Components of an Acute Care Physical Therapy Cheat Sheet
Every effective cheat sheet I have used over the years contains roughly the same sections. The first section is always cardiovascular and respiratory status. This includes heart rate ranges, blood pressure baselines, oxygen requirements, and any ventilator or noninvasive support the patient is on. You need to know your stop criteria before you even enter the room. The second section covers mobility and functional status. This is not about standardized outcome measures like the FIM. It is about a quick snapshot. Can they roll? Sit at the edge of the bed with support? Stand with minimal contact guard? Transfer with a slide board or Hoyer lift? The level of assistance required tells you more than any score. The third section addresses cognitive and perceptual status. Acute care patients frequently have delirium, aphasia, or visual field cuts. These affect safety more than muscle strength ever will. A patient who cannot follow one-step commands or has hemineglect should not be doing stand transfers without significant support, regardless of how strong their legs are. The fourth section documents lines, tubes, and precautions. This is the part most people skip. Central lines, arterial lines, chest tubes, drain tubes, feeding tubes, catheters, surgical sites, and orthopedic hardware all matter. You need a quick reference for weight-bearing restrictions, incision precautions, and line placement sites. Pulling on a central line during a transfer is not something you recover from quickly.How to Build One That Actually Works
I started building my own cheat sheet about five years ago after realizing the printed hospital protocols were never up to date and often contradicted each other. I created a single-page document that I kept in my pocket clip. It contains the essential information I need within thirty seconds of reading it. Here is how I structure it. The top third is patient identifiers and clinical context. Name, age, admitting diagnosis, and the reason for PT referral. Then the cardiac and respiratory parameters in a small table format with color-coded stop thresholds. Green means continue, yellow means modify intensity, red means stop immediately. This removes guesswork when you are tired or interrupted. The middle third is mobility and functional data. I list the highest level of function observed on the last visit and what changed since then. Did they tolerate sitting better? Can they bear weight now? Any new pain or fatigue? This section is updated after every encounter so the next therapist walking in knows exactly where to pick up. The bottom third is precautions and recommendations for discharge planning. Weight-bearing status, line and tube precautions, cognitive considerations, and the level of care needed at discharge. This section is critical because it directly influences whether the patient goes home with services, to a skilled nursing facility, or to inpatient rehabilitation.I had a specific incident that shaped how I approach this. A patient on my floor had a peripherally inserted central catheter, or PICC line, in his right arm. The chart notation said "precautions: avoid BP on right arm" but did not mention the line itself. During a transfer assessment, I had him hold onto the parallel bars with both hands. His right arm pulled against the PICC line and he experienced significant resistance and discomfort. I stopped immediately. The workaround was straightforward: I documented the PICC line site and type prominently on the cheat sheet, restricted weight bearing through that arm, and communicated this to the nursing staff before the next session. Since then, I include a dedicated lines and tubes subsection on every sheet and verify each line's location and type during the initial evaluation. This takes two minutes and prevents serious complications.
Common Pitfalls and What to Avoid
One common error is relying solely on vital signs without considering the patient's medication regimen. Beta blockers blunt heart rate responses. Pain medications suppress respiratory drive and alertness. Steroids affect glucose levels and muscle weakness. A normal heart rate on a beta-blocked patient might actually represent tachycardia relative to their medication-adjusted baseline. Always check the medication list and adjust your expectations accordingly. Another issue is assuming that standard outcome measures translate directly to acute care settings. The Six-Minute Walk Test is not appropriate for most med-surg patients. Berg Balance Scale requires standing for extended periods that many acutely ill patients cannot tolerate. Select measures that fit the population. The Functional Independence Measure is more practical. The Bed Mobility subscale of the FIM alone gives you useful data without overstressing the patient. There is also the problem of documentation overload. Hospitals require extensive paperwork and therapists sometimes spend more time documenting than treating. A well-designed cheat sheet reduces documentation time because the key clinical decisions are already organized. You fill in the blanks instead of writing paragraphs from scratch. This usually cuts documentation time from forty-five minutes to fifteen minutes per encounter.When a Cheat Sheet Fails You
No cheat sheet covers every scenario. A patient with multi-system organ failure, active hemodynamic instability, or complex post-surgical restrictions may require input from multiple specialists before you can safely proceed. In those cases, the cheat sheet is a starting point, not a decision-making tool. Collaborate with the medical team. Consult wound care for dressing changes that affect positioning. Work with respiratory therapy on ventilator weaning protocols that influence endurance. If you are working in a facility that does not support ongoing education or does not provide access to current clinical guidelines, the cheat sheet becomes even more important as your primary reference. But do not treat it as a substitute for clinical reasoning. It is a tool, nothing more. The reasoning stays with you.I recommend downloading a blank template and filling it in with your own clinical experience. Start with the sections that matter most to you. Add to it as you encounter new patient populations. Remove anything that does not get used within the first month. An unused section clutters the document and slows you down. A tight, functional cheat sheet is worth more than a comprehensive one you never reference.
Get the Full Details