Writing Notes That Actually Hold Up in Acute Care
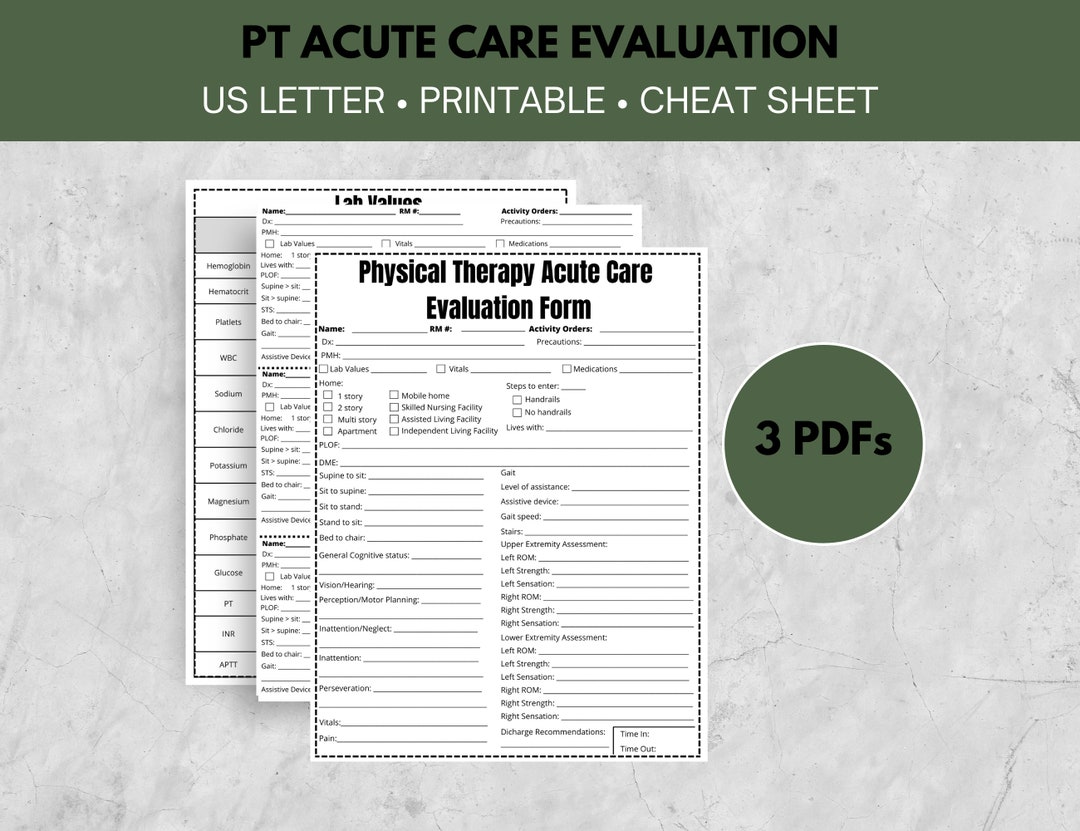
Acute care physical therapy documentation is where most therapists get tripped up. Not because the clinical reasoning is hard, but because the paperwork has to satisfy two different audiences at once: the physician who ordered the consult, and the utilization review nurse who decides whether the patient stays another day. These two readers want completely different things. The physician wants a quick snapshot of function and plan. The reviewer wants a bulletproof justification for continued inpatient-level care. I keep a running template in my head that I modify for each patient. The structure isn't rigid, but hitting the right elements in the right order saves time and keeps auditors off your back. Here is how a solid evaluation note typically breaks down. The opening line states the diagnosis, the reason for referral, and the current medical status in one sentence. Something like: Eval for PT per Dr. Ramirez re: deconditioning r/t status post right total hip arthroplomy, D1. PMH: HTN, DM2. Status post open reduction internal fixation x3 days ago. This sets the stage immediately. You do not need a separate subjective section if your system uses free-text SOAP notes. Just weave the relevant history into the opening.
For the objective portion, functional independence is the critical element. Document the actual task, the patient's performance level, and the type of assistance required. Use standardized language like "modified independent," "contact guard assist," "minimal assist," and so on. Specific numbers matter more than vague descriptions. Instead of writing "transfers with assistance," write "bed to chair transfer requiring minimal assist for lower extremity weight bearing, 2-person assist for safety due to recent right TKA." That tells the reviewer exactly what is happening. When I worked in a Level 1 trauma center, I had a patient who was medically stable but kept failing transfers because of severe anxiety around movement post-spinal surgery. The documentation needed to capture that this was a psychological barrier, not a physical one, because it affected the discharge planning decision. I wrote: "Patient demonstrates significant fear-avoidance behavior during mobility trials. Physiological parameters stable throughout. Recommend psychosocial support and repeated low-intensity exposure to mobility tasks before considering skilled nursing placement." That note directly influenced the case manager's decision to hold discharge while addressing the anxiety component. Without that specific language, the reviewer would have just seen a patient who couldn't transfer safely and approved a SNF placement without understanding why. Balance testing in acute care rarely involves formal scores like the Berg Balance Scale. Most patients are too unstable or too acute. Use functional balance descriptors instead: "sits at edge of bed with dynamic balance maintained for 2 minutes with contact guard assist for lower extremities during weight shifts." That is more useful to the next provider than a number they cannot apply to a subacute population.
Gait training documentation follows the same principle. Document surface, distance, assistive device, and level of assistance. "Ambulated 50 feet in hallway with rolling walker, minimum assist for upper extremity guidance and cueing for step-to pattern, 3 sets total." If the patient did not ambulate that session, say why. "Pt declined gait training today due to fatigue; tolerating only 5 minutes of sitting at edge of bed before reporting lightheadedness. Held MD for orthostatic vitals." That last sentence is critical. It shows you did not skip the intervention. It showed medical clearance was needed and obtained. The assessment section is where most notes fail under audit. It needs to connect the objective findings to the prognosis and the plan. Use language that addresses complexity and risk. "Patient demonstrates decreased endurance and balance, limiting community mobility potential. Presenting functional deficits require skilled intervention given acute medical complexity including controlled hypotension and insulin-dependent diabetes. Prognosis for functional improvement to baseline pre-morbid level fair given age 78 and lack of home support system." That prognostic statement justifies the continued inpatient stay far more effectively than any functional score. InterQual criteria specifically look for documented functional impairment combined with medical complexity. If your note only lists dysfunction without linking it to medical factors, the review comes back as insufficient. This is a mistake I see constantly. Therapists document what the patient can do but forget to explain why the patient cannot do it safely in a lower level of care. That gap is what triggers denials.
Get the Full Details

Re-evaluation and Discharge Note Requirements
Re-evaluations in acute care happen less frequently than in outpatient settings, usually every five to seven treatment days or when there is a significant clinical change. The re-eval note must show progression or lack thereof, update the prognosis, and justify continued inpatient stay. CMS requires that the re-evaluation include current functional status, comparison to previous evaluation, response to treatment, and revised plan of care. Include all four elements explicitly. Discharge notes are the most scrutinized documents in acute care PT. They must include the final functional status, the discharge diagnosis, the plan after discharge, and the patient's and family's understanding of the plan. Do not skip the last element. A discharge note without documented patient education is a red flag for auditors. Write: "Pt and daughter educated on home exercise program, fall precautions, and weight-bearing status. Verbal return demonstration provided. Daughter verbalized understanding of signs to report to MD including increased swelling, drainage, and fever greater than 101.5." If the patient has no family present, document that separately. "No family available for education. Education provided to patient alone. Patient verbalized understanding." One specific edge case I run into regularly involves patients who are being discharged to home alone. The documentation needs to reflect that the therapist assessed the safety of that placement. I write: "Patient will discharge to home alone. No live-in support available. Home environment assessed via patient report: 2-story home with staircase, bathroom on main floor, no grab bars present. Patient ambulates with walker indoors. Recommend home health PT continuation and PT evaluation for home modification equipment prior to discharge." This protects the therapist and the facility. It also creates a paper trail that case management acted on.
There is a common misconception that acute care documentation requires more detail than other settings. It does not. It requires different detail. The level of detail is actually comparable to outpatient. What changes is the focus. Outpatient notes emphasize progression and goals. Acute care notes emphasize medical necessity and safe disposition. Swap the emphasis and the notes read correctly. Documentation templates from your facility should never be followed blindly. Some EMR systems default to outpatient-style flow sheets that do not include fields for medical stability parameters or risk of falls upon discharge. If your system lacks those fields, add them as free-text elements. I added a "medical stability screening" box to my evaluation notes that asks me to explicitly state heart rate range, blood pressure stability, oxygen saturation on room air or with supplemental oxygen, and any recent medication changes affecting mobility. This takes thirty seconds to complete and has saved my notes during audits multiple times. The biggest waste of time in acute care documentation is rewriting the same subjective information for every note. Once you have the relevant history for a diagnosis category, create a library of commonly used phrases. "Status post left total knee arthroplomy, D5, NPO clear liquids, Vitals within normal limits, pain controlled with oral medication, cleared by MD for PT intervention." Copy paste that block and modify the side and day. Then add the unique elements for that specific session. This reduces average note completion time from approximately twelve minutes to five minutes per encounter.
Another practical shortcut involves the plan of care section. Instead of writing a new plan for every note, reference the existing plan and note any modifications. "Continue plan of care as established 11/3. Increase ambulation distance from 75 feet to 100 feet. Progress from minimal assist to contact guard assist for transfers." This satisfies documentation requirements without redundant text. Some facilities require a full plan rewrite at each encounter. Check your policy. If yours does, the reference method is still faster once you are comfortable with it.
Pitfalls That Get You in Trouble
Certain documentation errors are almost guaranteed to cause problems. The first is using the same functional level across multiple days without justification. If a patient is documented as "minimal assist for transfers" on Monday and the same phrase appears on Friday with no indication of progress or regression, the reviewer assumes the note was copy-pasted. Add a progression statement even if the level did not change. "Transfers continue at minimal assist. No improvement noted in lower extremity strength but patient demonstrating improved confidence and decreased verbal cueing. Continue current plan." The second major pitfall is failing to document contraindications or precautions. If a patient has a DVT history, a recent fall, or a wound vac, these must appear in the note. Not as an afterthought. In the objective or assessment section where they belong. "Pt with history of DVT in left leg 2 weeks ago. Compression stockings in place during all mobility sessions. No signs of swelling or discoloration noted. Precautions discussed with patient and case management." Time-based documentation is the third area where acute care therapists lose audits. If you document thirty minutes of treatment, you need to account for all thirty minutes. Direct patient contact time plus concurrent activities. Bed positioning, patient education, and equipment setup count toward treatment time. "Thirty minutes of skilled PT services: gait training 15 minutes, transfer training 10 minutes, upper extremity strengthening 5 minutes." Break it down if the note reviewer asks. Better yet, include the breakdown in the original note.
One limitation of the current documentation landscape is that some EMR systems still force therapists into outdated frameworks. I work with a system that requires a separate goals section before the plan of care. The goals section pulls from an old template that assumes inpatient stays of two weeks minimum. Most acute care patients are discharged in three to five days. Forcing goals into that framework creates unrealistic expectations and inflates documentation without adding clinical value. I workaround this by entering a brief note in the goals field stating "Goals revised per short length of stay. Focus on safe discharge disposition and immediate post-discharge mobility." It is not ideal. But it gets through review. Another honest limitation: documentation quality does not always correlate with patient outcomes in acute care. You can write a perfect note and the patient still deteriorates clinically. Conversely, a rushed note does not mean the care was substandard. The system punishes bad documentation regardless of actual clinical quality. This is frustrating but it is the reality. The best approach is to treat documentation as a separate skill from clinical reasoning and invest time in getting better at both independently. If your facility does not provide structured documentation training, seek out resources from the APTA acute care section or the Academy of Orthopedic Physical Therapy. Their documentation guides are more current than most hospital policies and address the specific language utilization reviewers expect. Even thirty minutes of reading their materials will improve your note quality more than any internal in-service you will attend this year.