Targeted Therapy in AML: What Actually Works and How to Use It
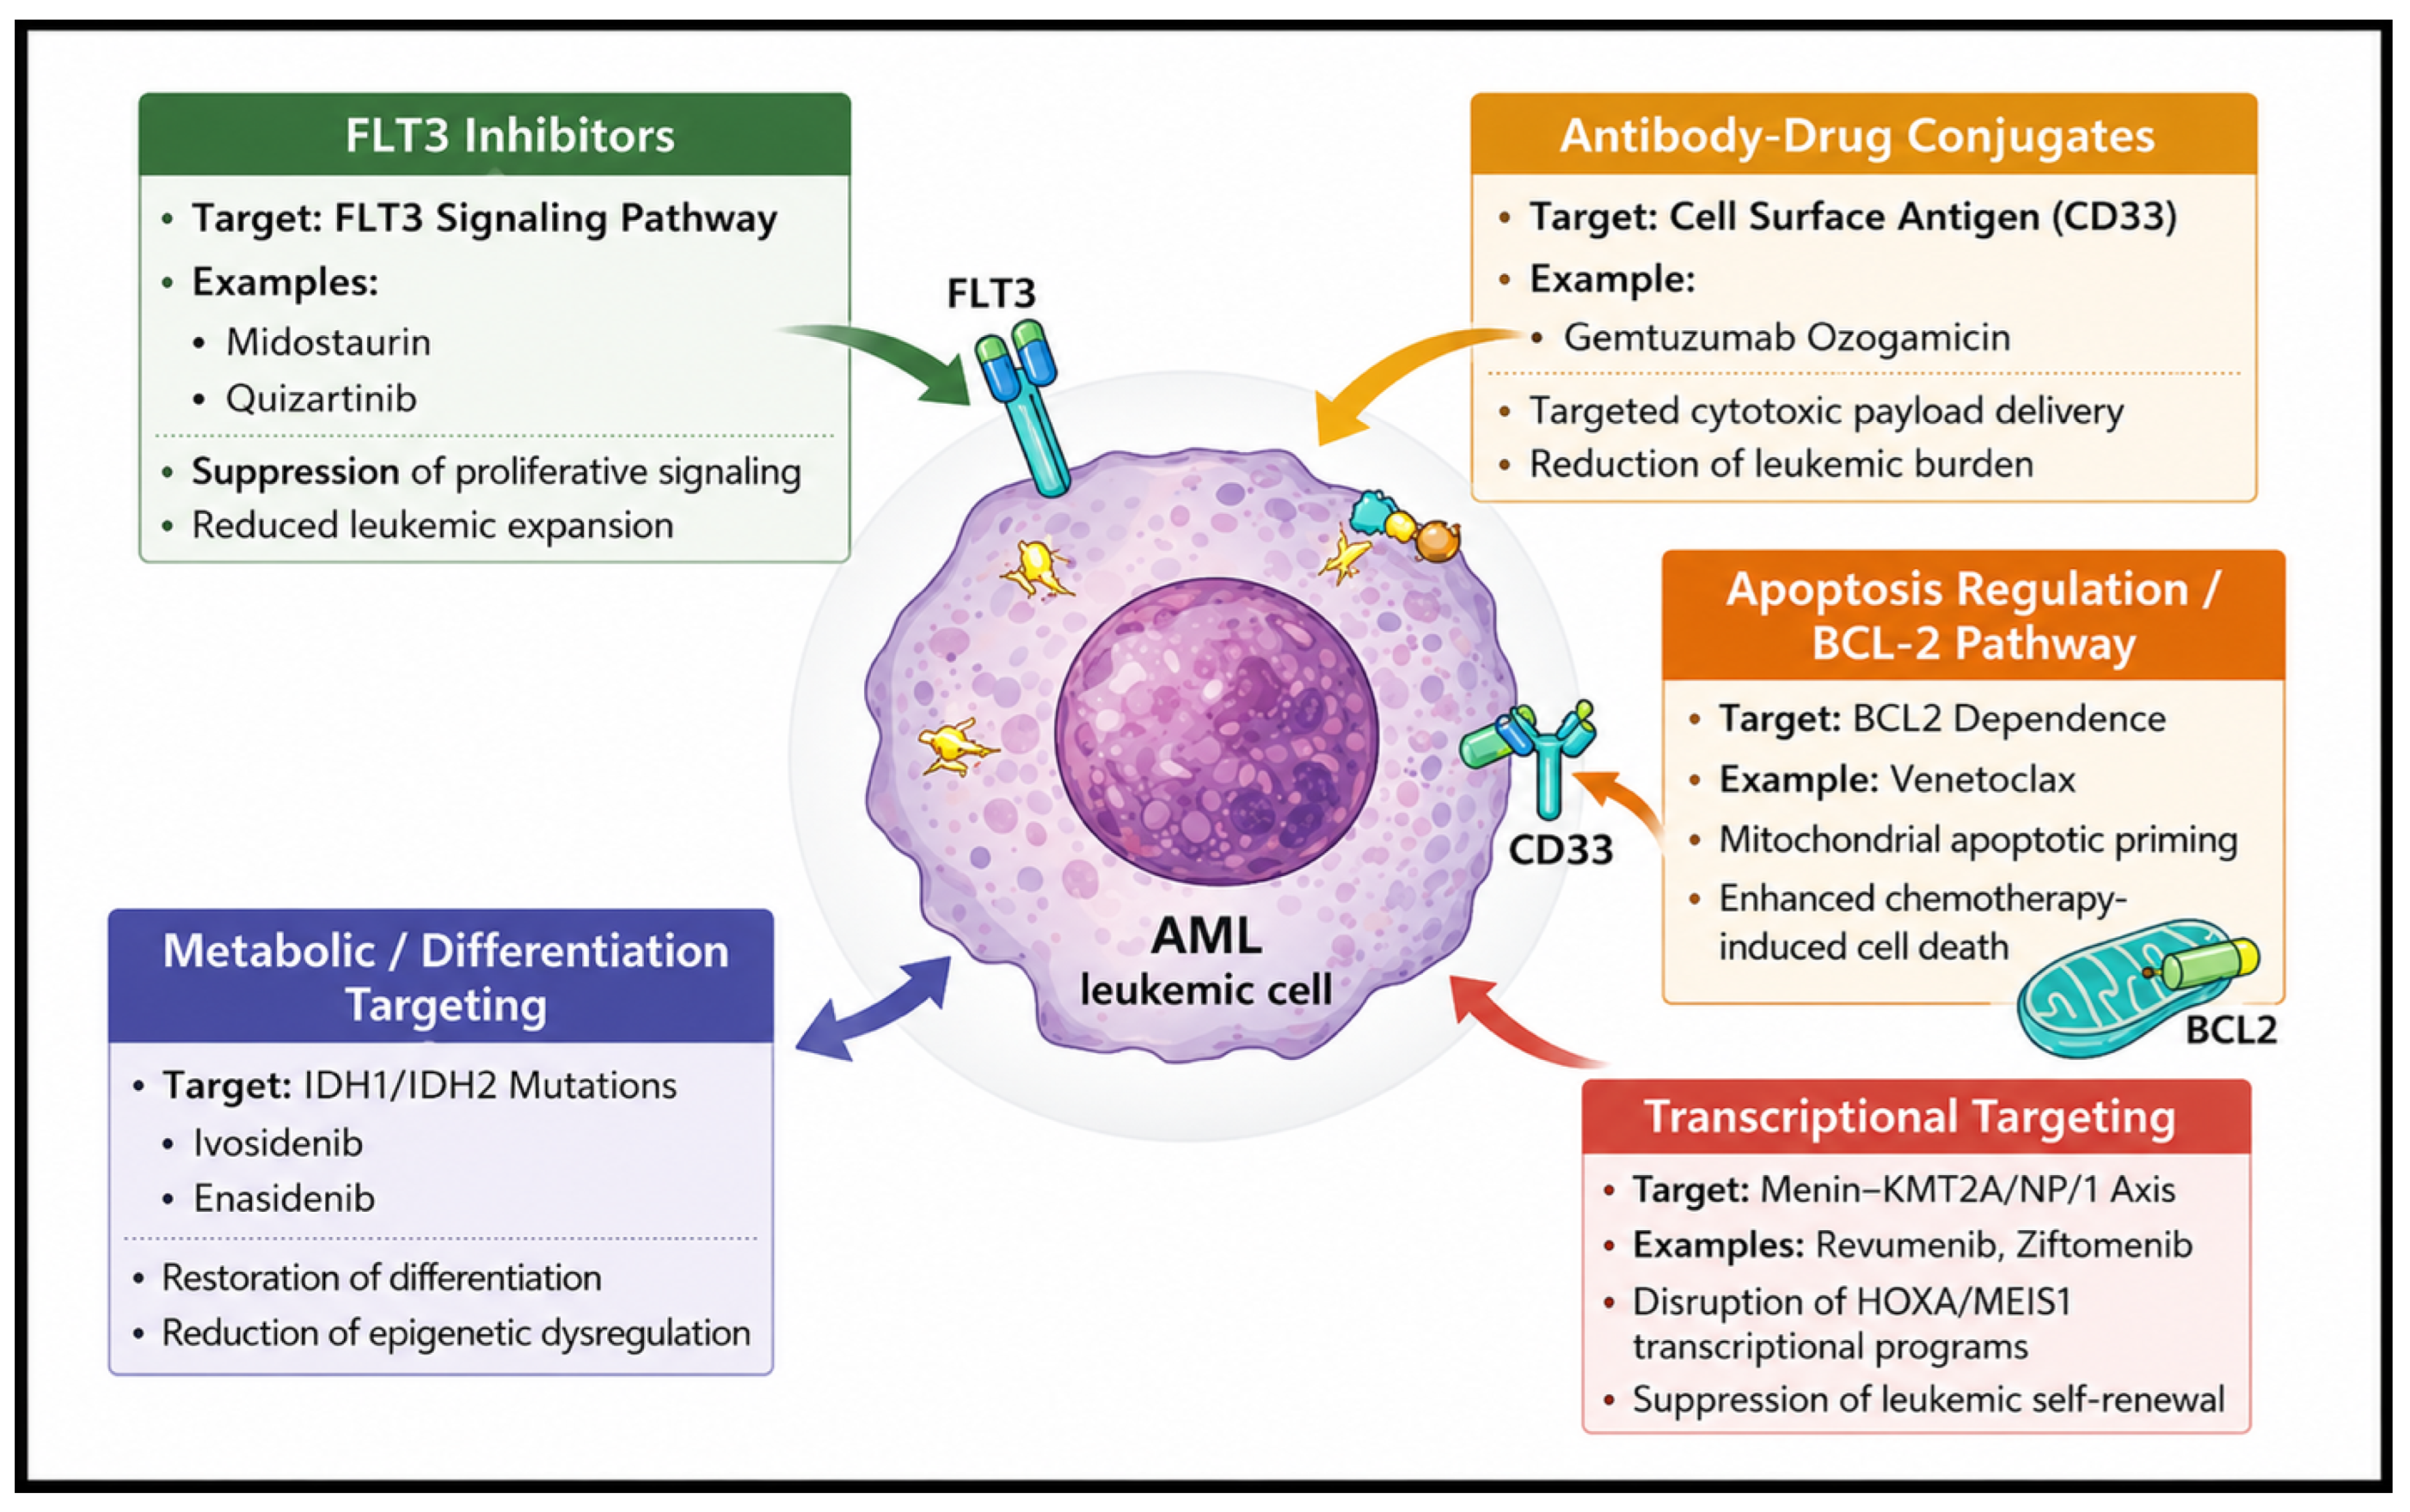
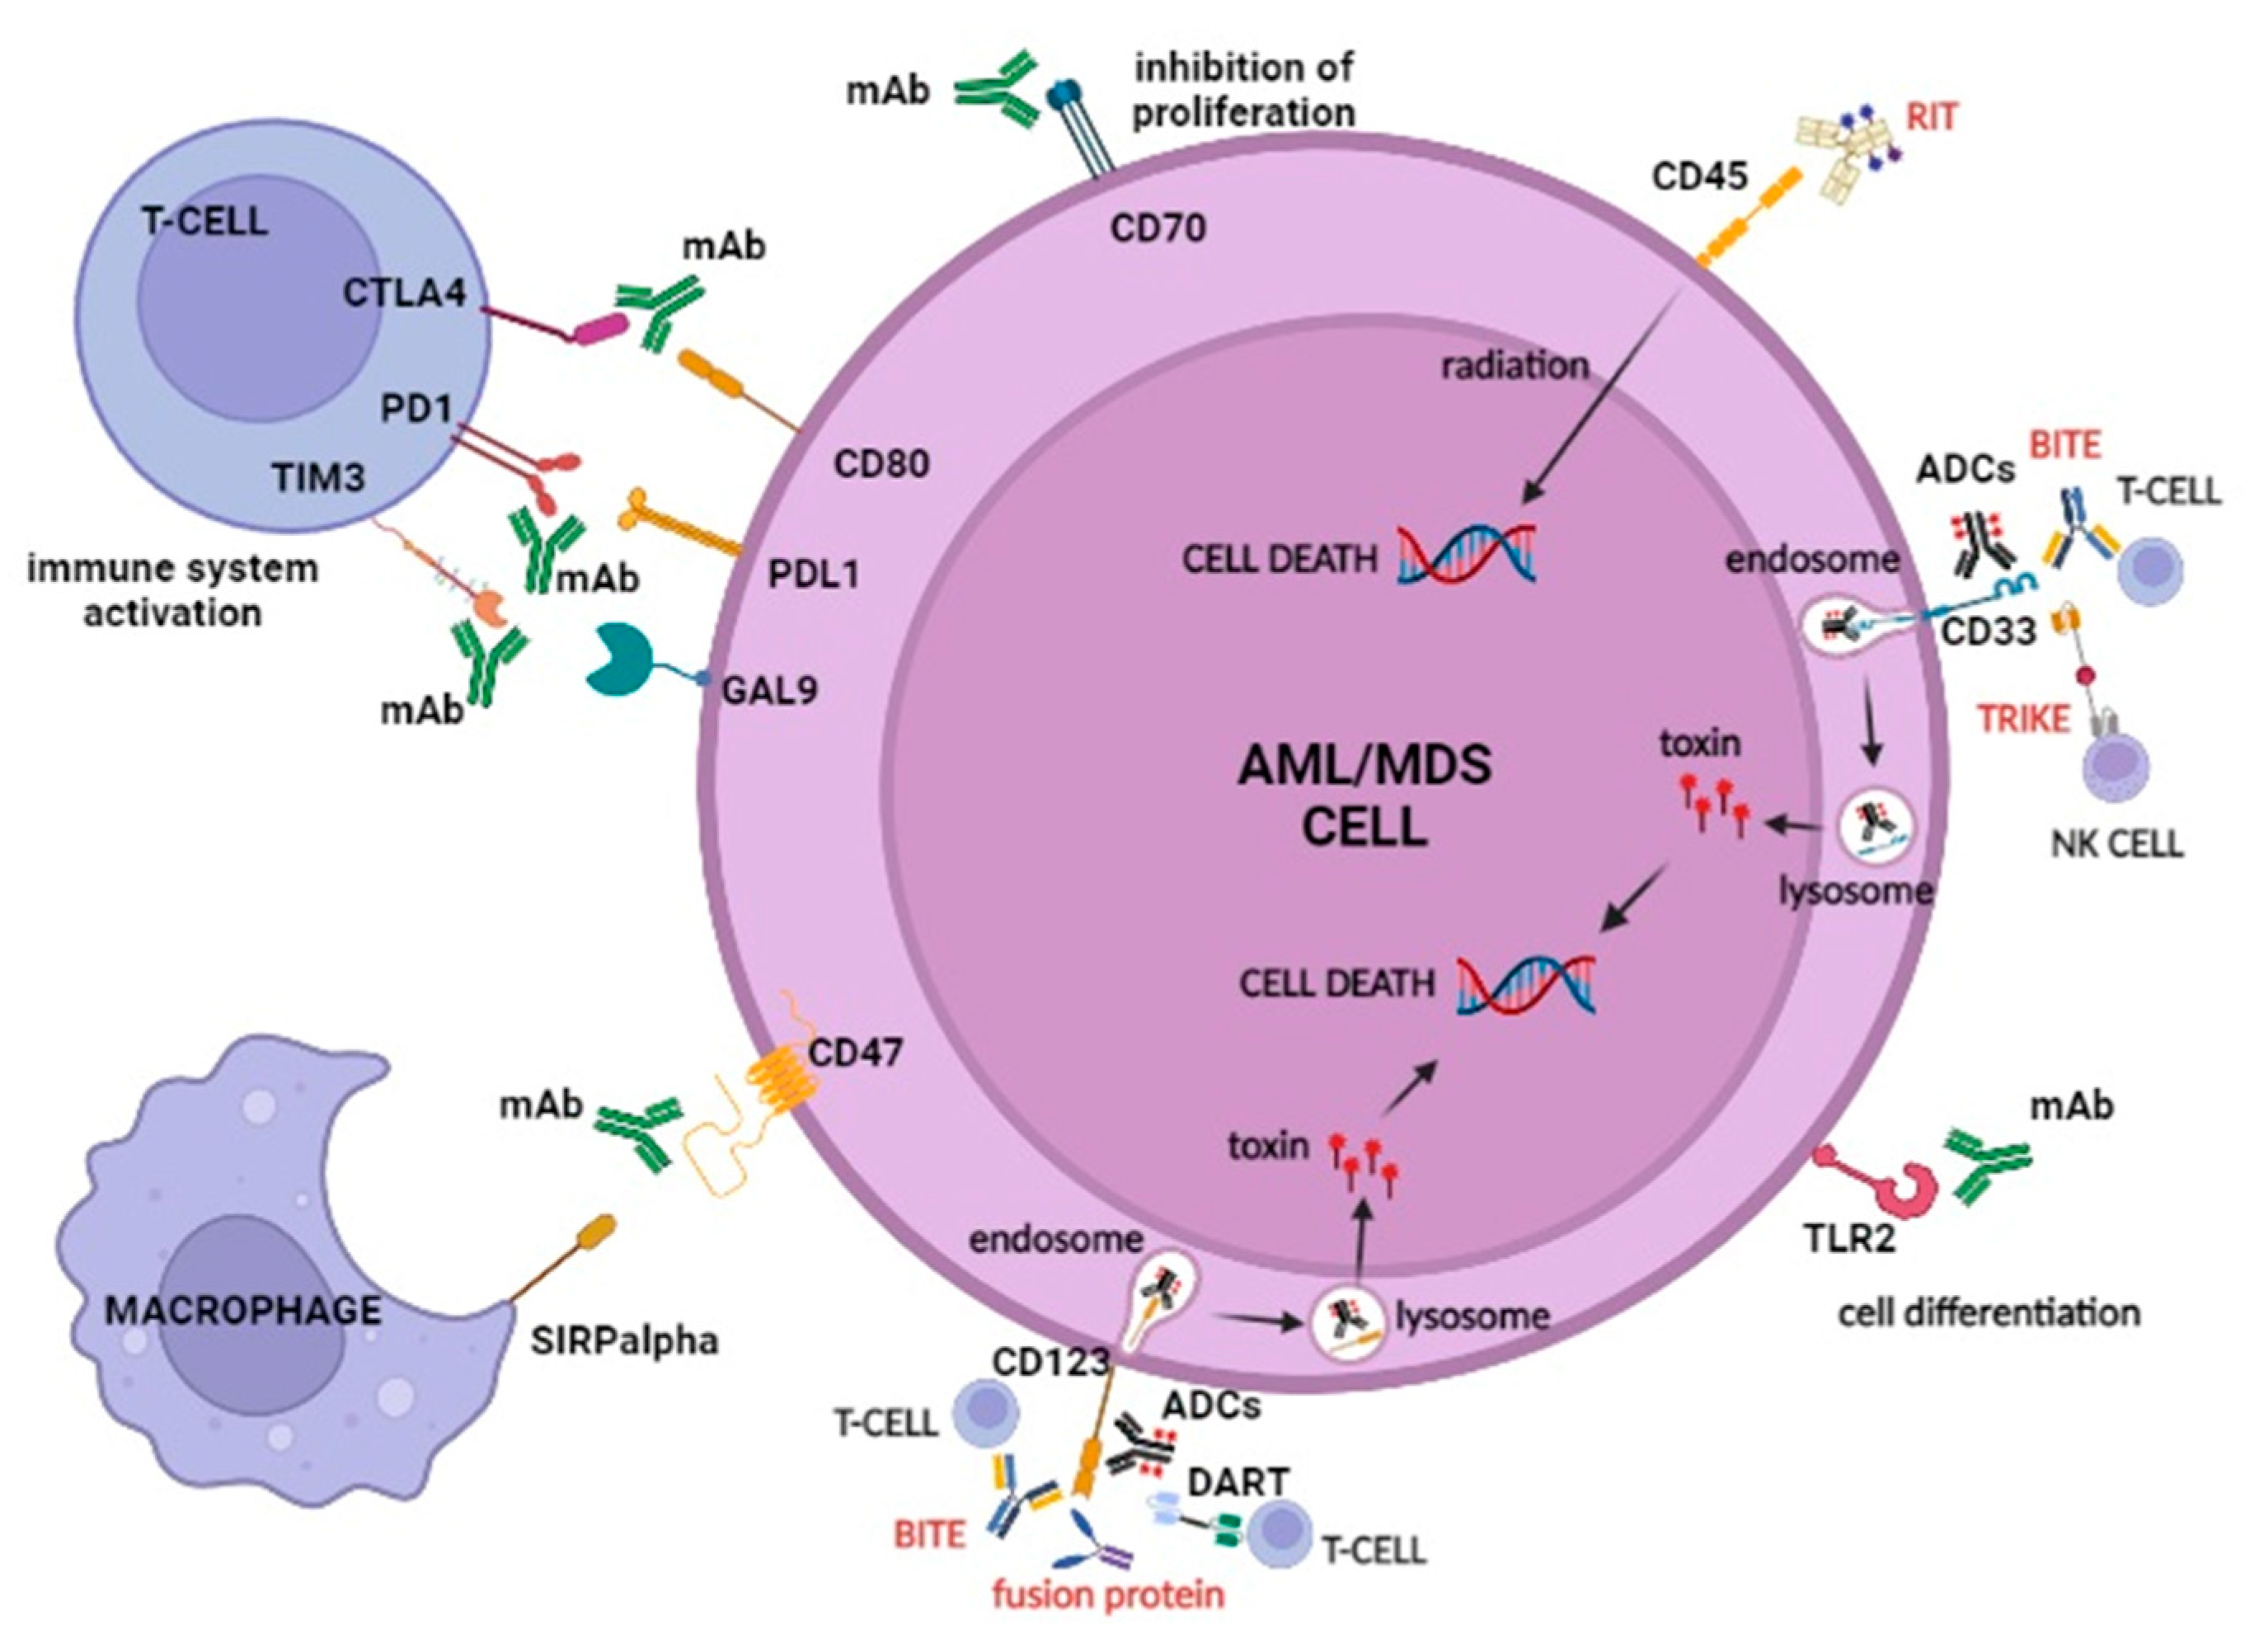
Acute Myeloid Leukemia Targeted Therapy has changed pretty dramatically over the last few years, and not always in the obvious ways. If you are looking at this from a clinical standpoint, the first thing to understand is that we do not have a single unified approach anymore. The field has fractured into genotype-driven decision trees, and being familiar with the individual agent profiles matters more than memorizing every trial. The backbone of modern targeted treatment really comes down to three categories: venetoclax-based combinations, FLT3 inhibition, and IDH inhibition. Each one has its own handling requirements, toxicity profile, and patient population where it makes the most sense. Everything else is either adjunctive or niche. Venetoclax paired with azacitidine or decitabine is now first-line standard for patients who are not candidates for intensive chemotherapy. This was established by the VITALITY and other Phase III trials. The regimen works because venetoclax inhibits BCL-2, forcing apoptosis in leukemia cells that depend on that survival pathway. Most patients need the full ramp-up schedule to avoid tumor lysis syndrome, and I cannot stress this enough — skipping or compressing the ramp-up is one of the most common mistakes I see. Start at 20 mg day one, go to 50 mg by day eight, and only start the HMA on day seven. The risk of TLS in an elderly AML population with high leukemic burden is real, and the renal complications that follow are unpleasant to manage.
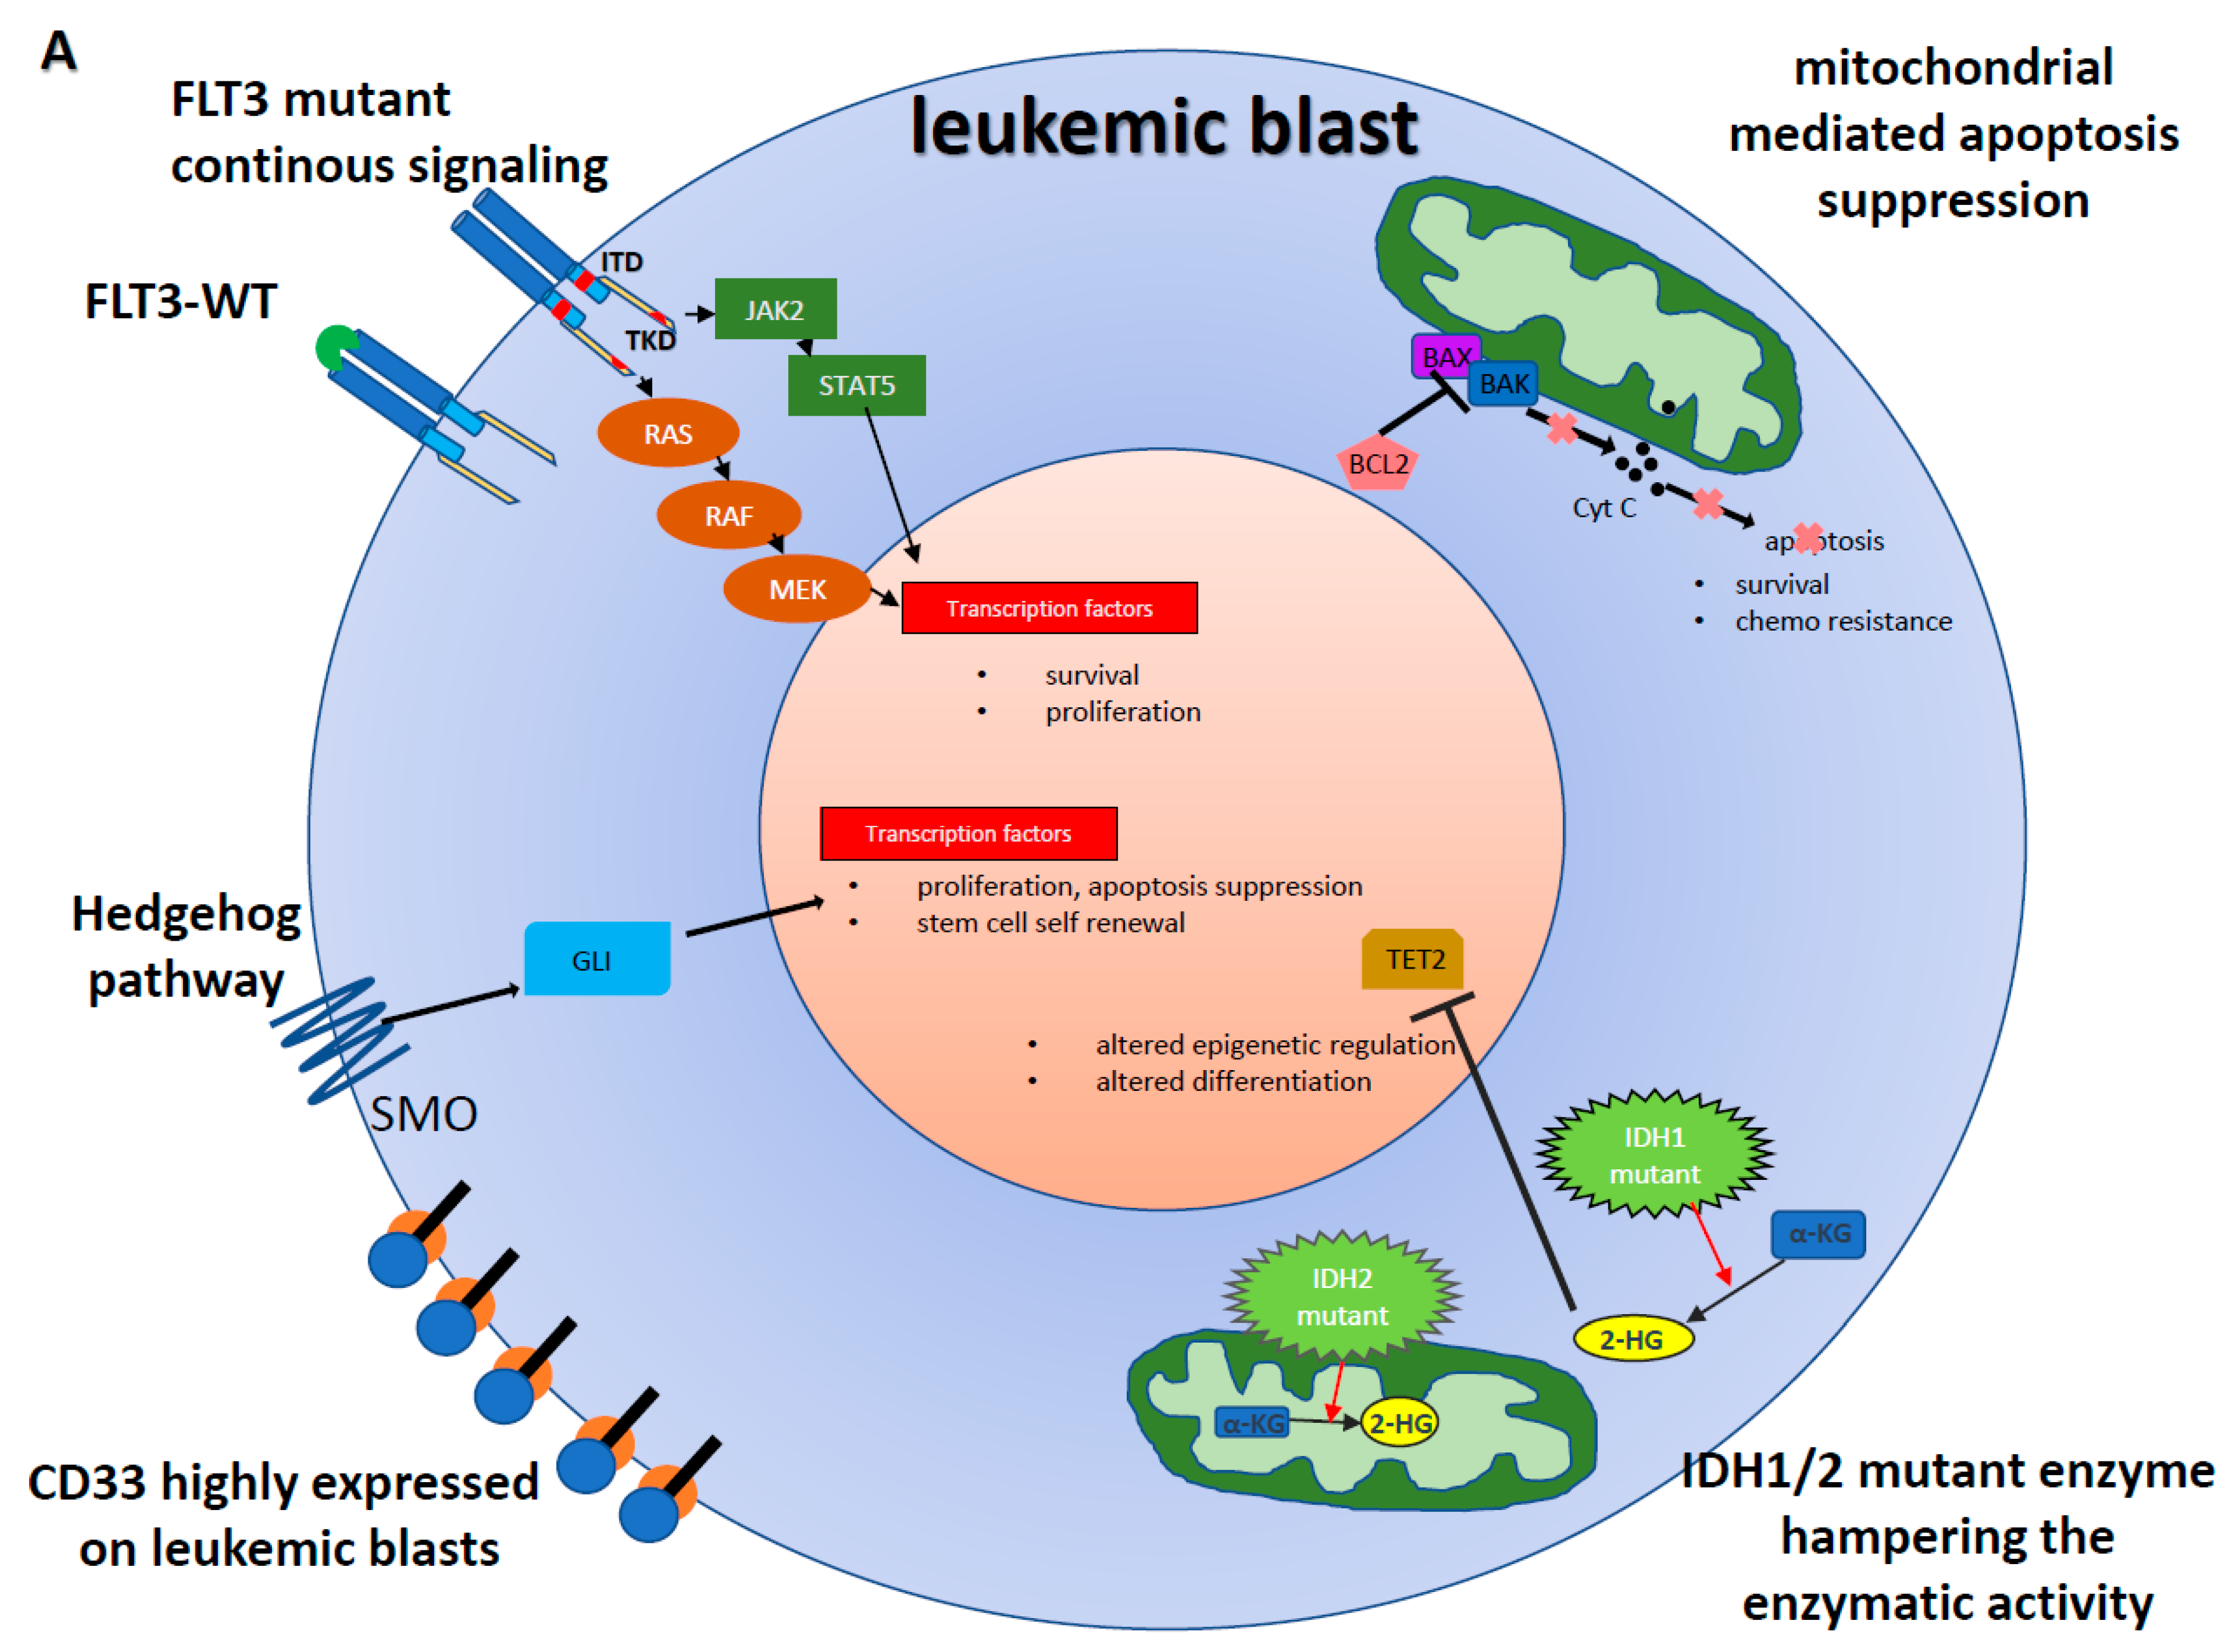
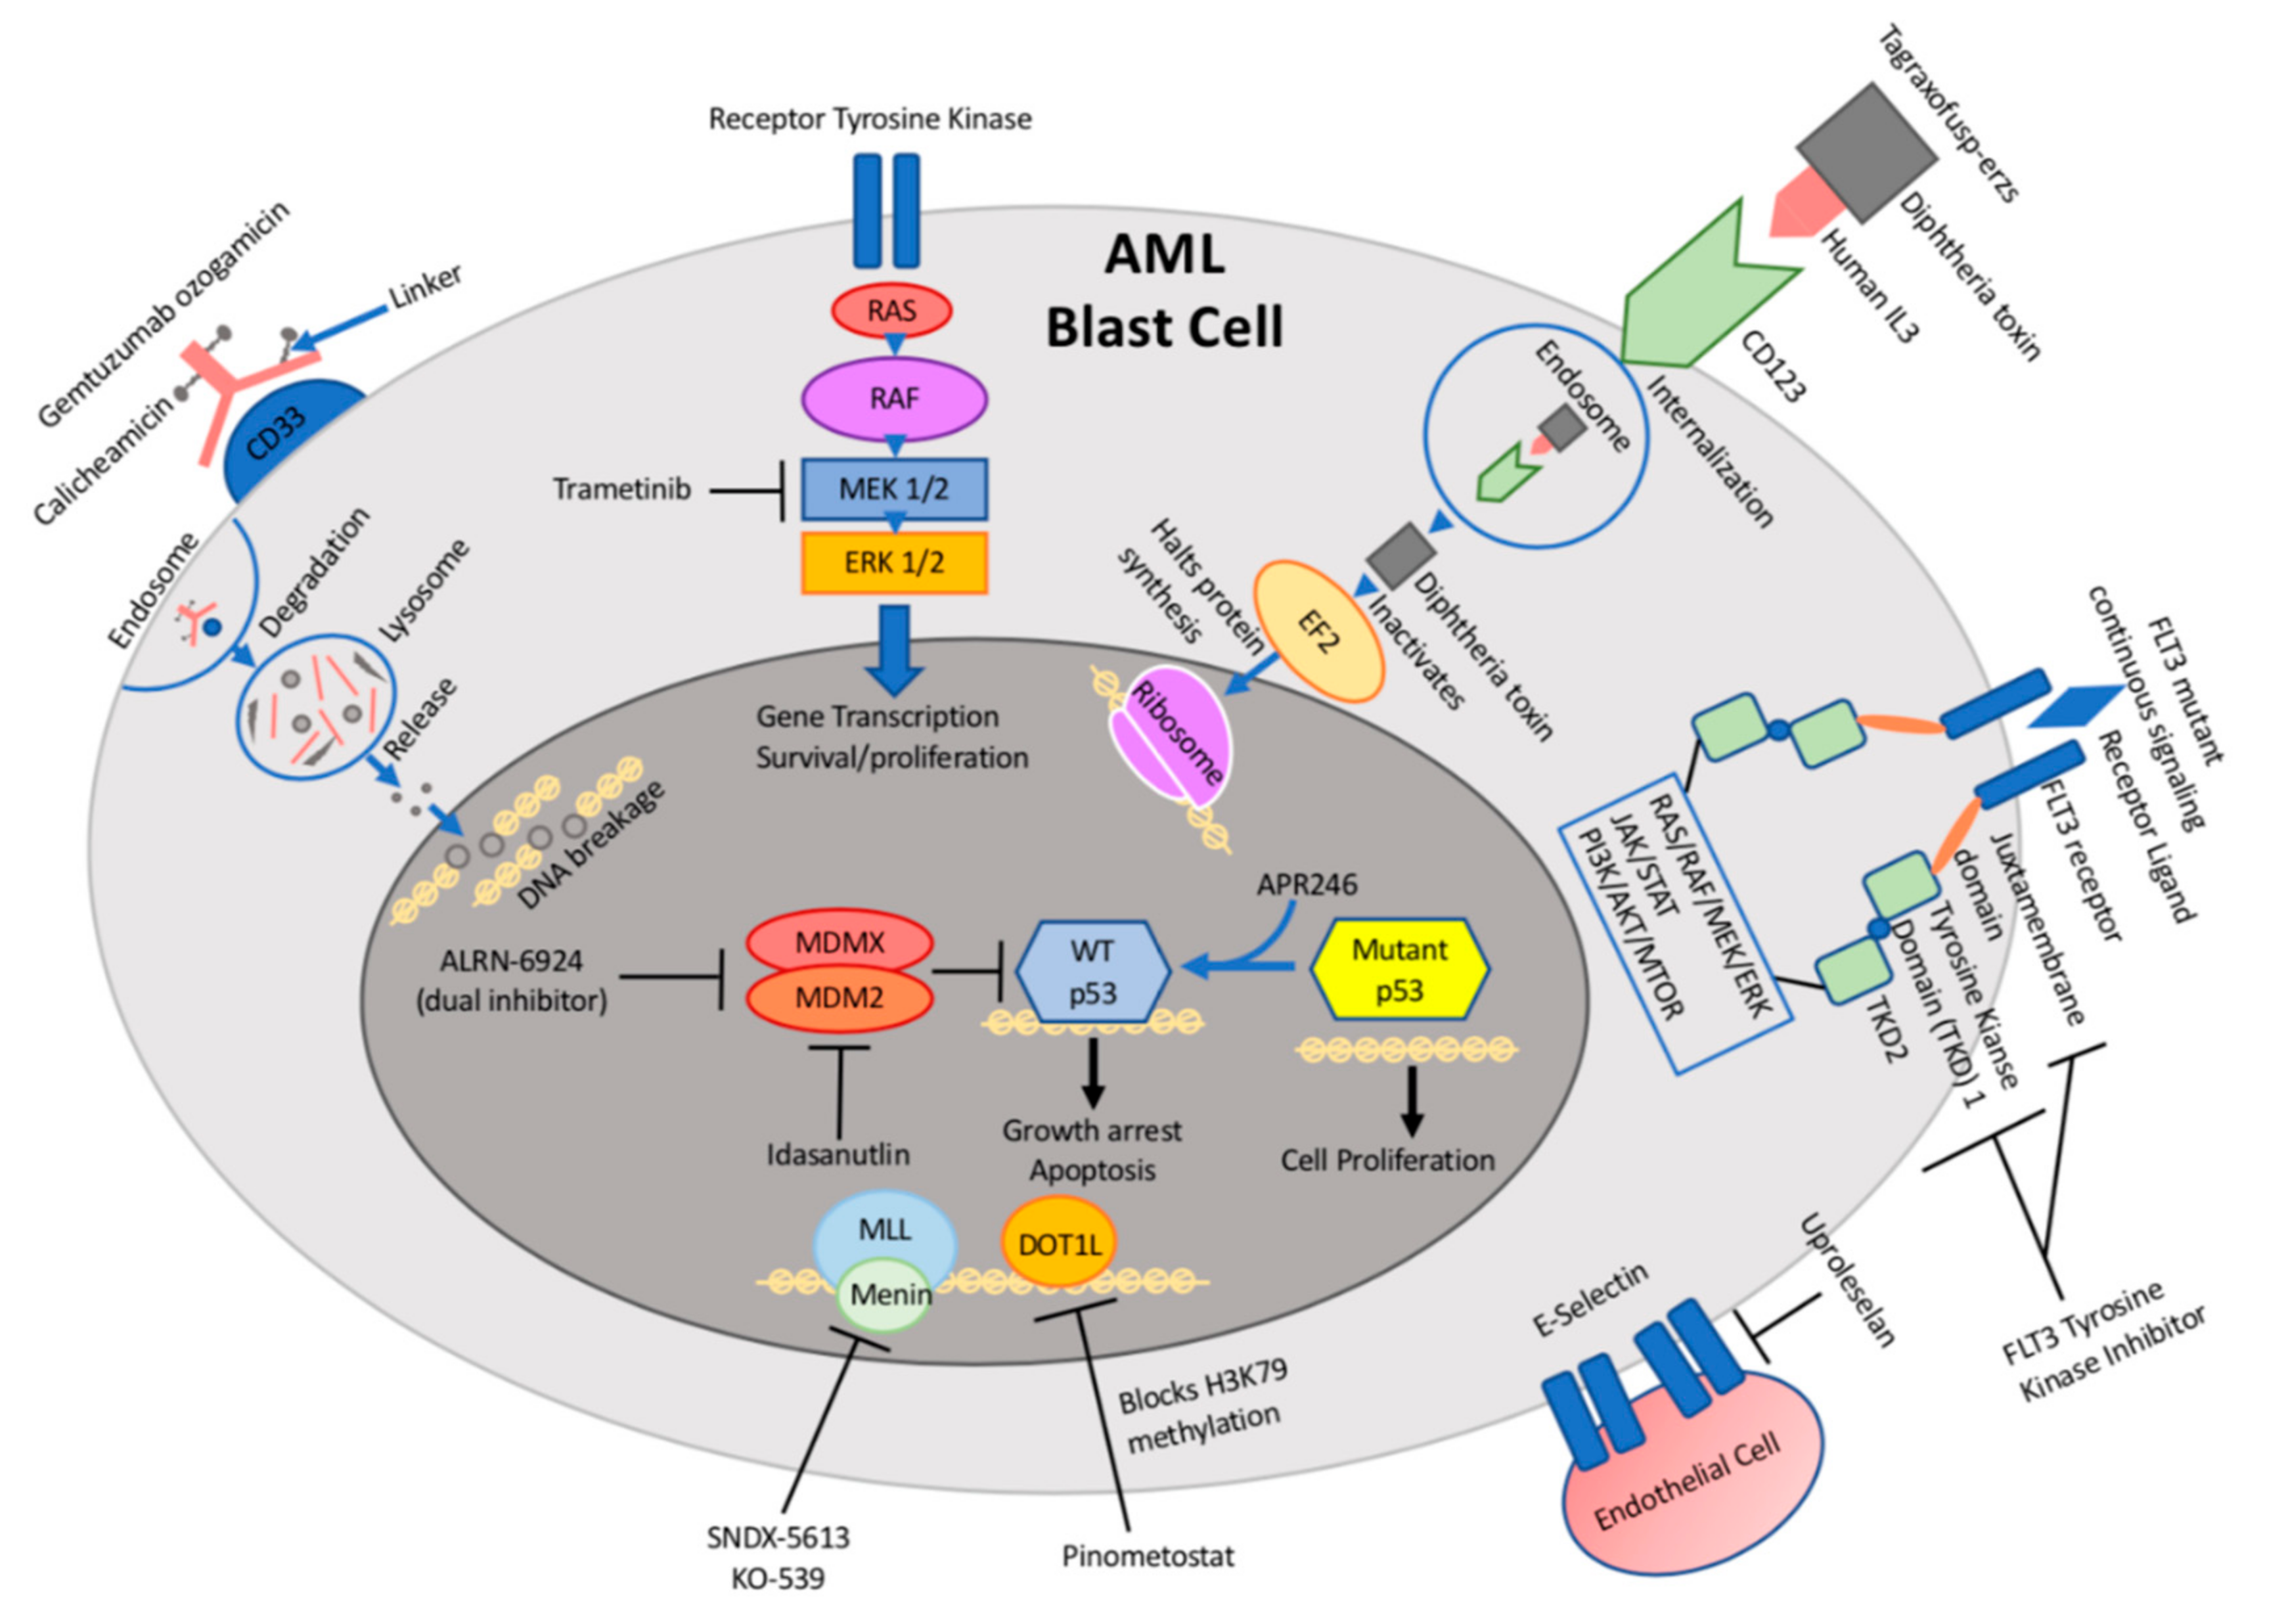
FLT3 mutations are present in roughly 25 to 30 percent of AML cases. Midostaurin is added to standard 7+3 induction for newly diagnosed FLT3-mutated patients, based on the RATIFY trial. The dosing is 50 mg twice daily on days 8 through 21, which overlaps poorly with the neutropenic phase. I have seen multiple instances where midostaurin was held during severe mucositis and the patient lost a meaningful chunk of cumulative exposure without anyone noticing it mattered. Track the days actually administered. Gilteritinib is the go-to for relapsed/refractory setting, and quizartinib recently got approval for FLT3-ITD positive AML in the frontline space. The key distinction with quizartinib is that it is essentially inactive against FLT3-TKD mutations, so genotyping matters before you commit. IDH1 and IDH2 mutations occur in about 10 to 15 percent of AML cases combined. Ivosidenib for IDH1 and enasidenib for IDH2 are approved as monotherapy in the relapsed/refractory setting. Differentiation syndrome is the major acute concern here, occurring in roughly 10 to 15 percent of patients on ivosidenib and slightly less on enasidenib. Dexamethasone at 10 mg IV every 12 hours preemptively is standard practice once you see signs. I learned this the hard way with a 68-year-old patient whose creatinine spiked to 2.8 on day four of ivosidenib because we had not yet connected the oliguria with early differentiation syndrome. We started dexamethasone then, but the delay cost us two days of renal recovery time. Menin inhibitors like koadostomib are the newest entry, targeting KMT2A-rearranged and NPM1-mutated AML. These show quite high response rates in early-phase data, but they are still largely available through clinical trials or expanded access at this point. The pharmacokinetics are tricky — food increases absorption significantly, so dose timing around meals needs to be consistent.
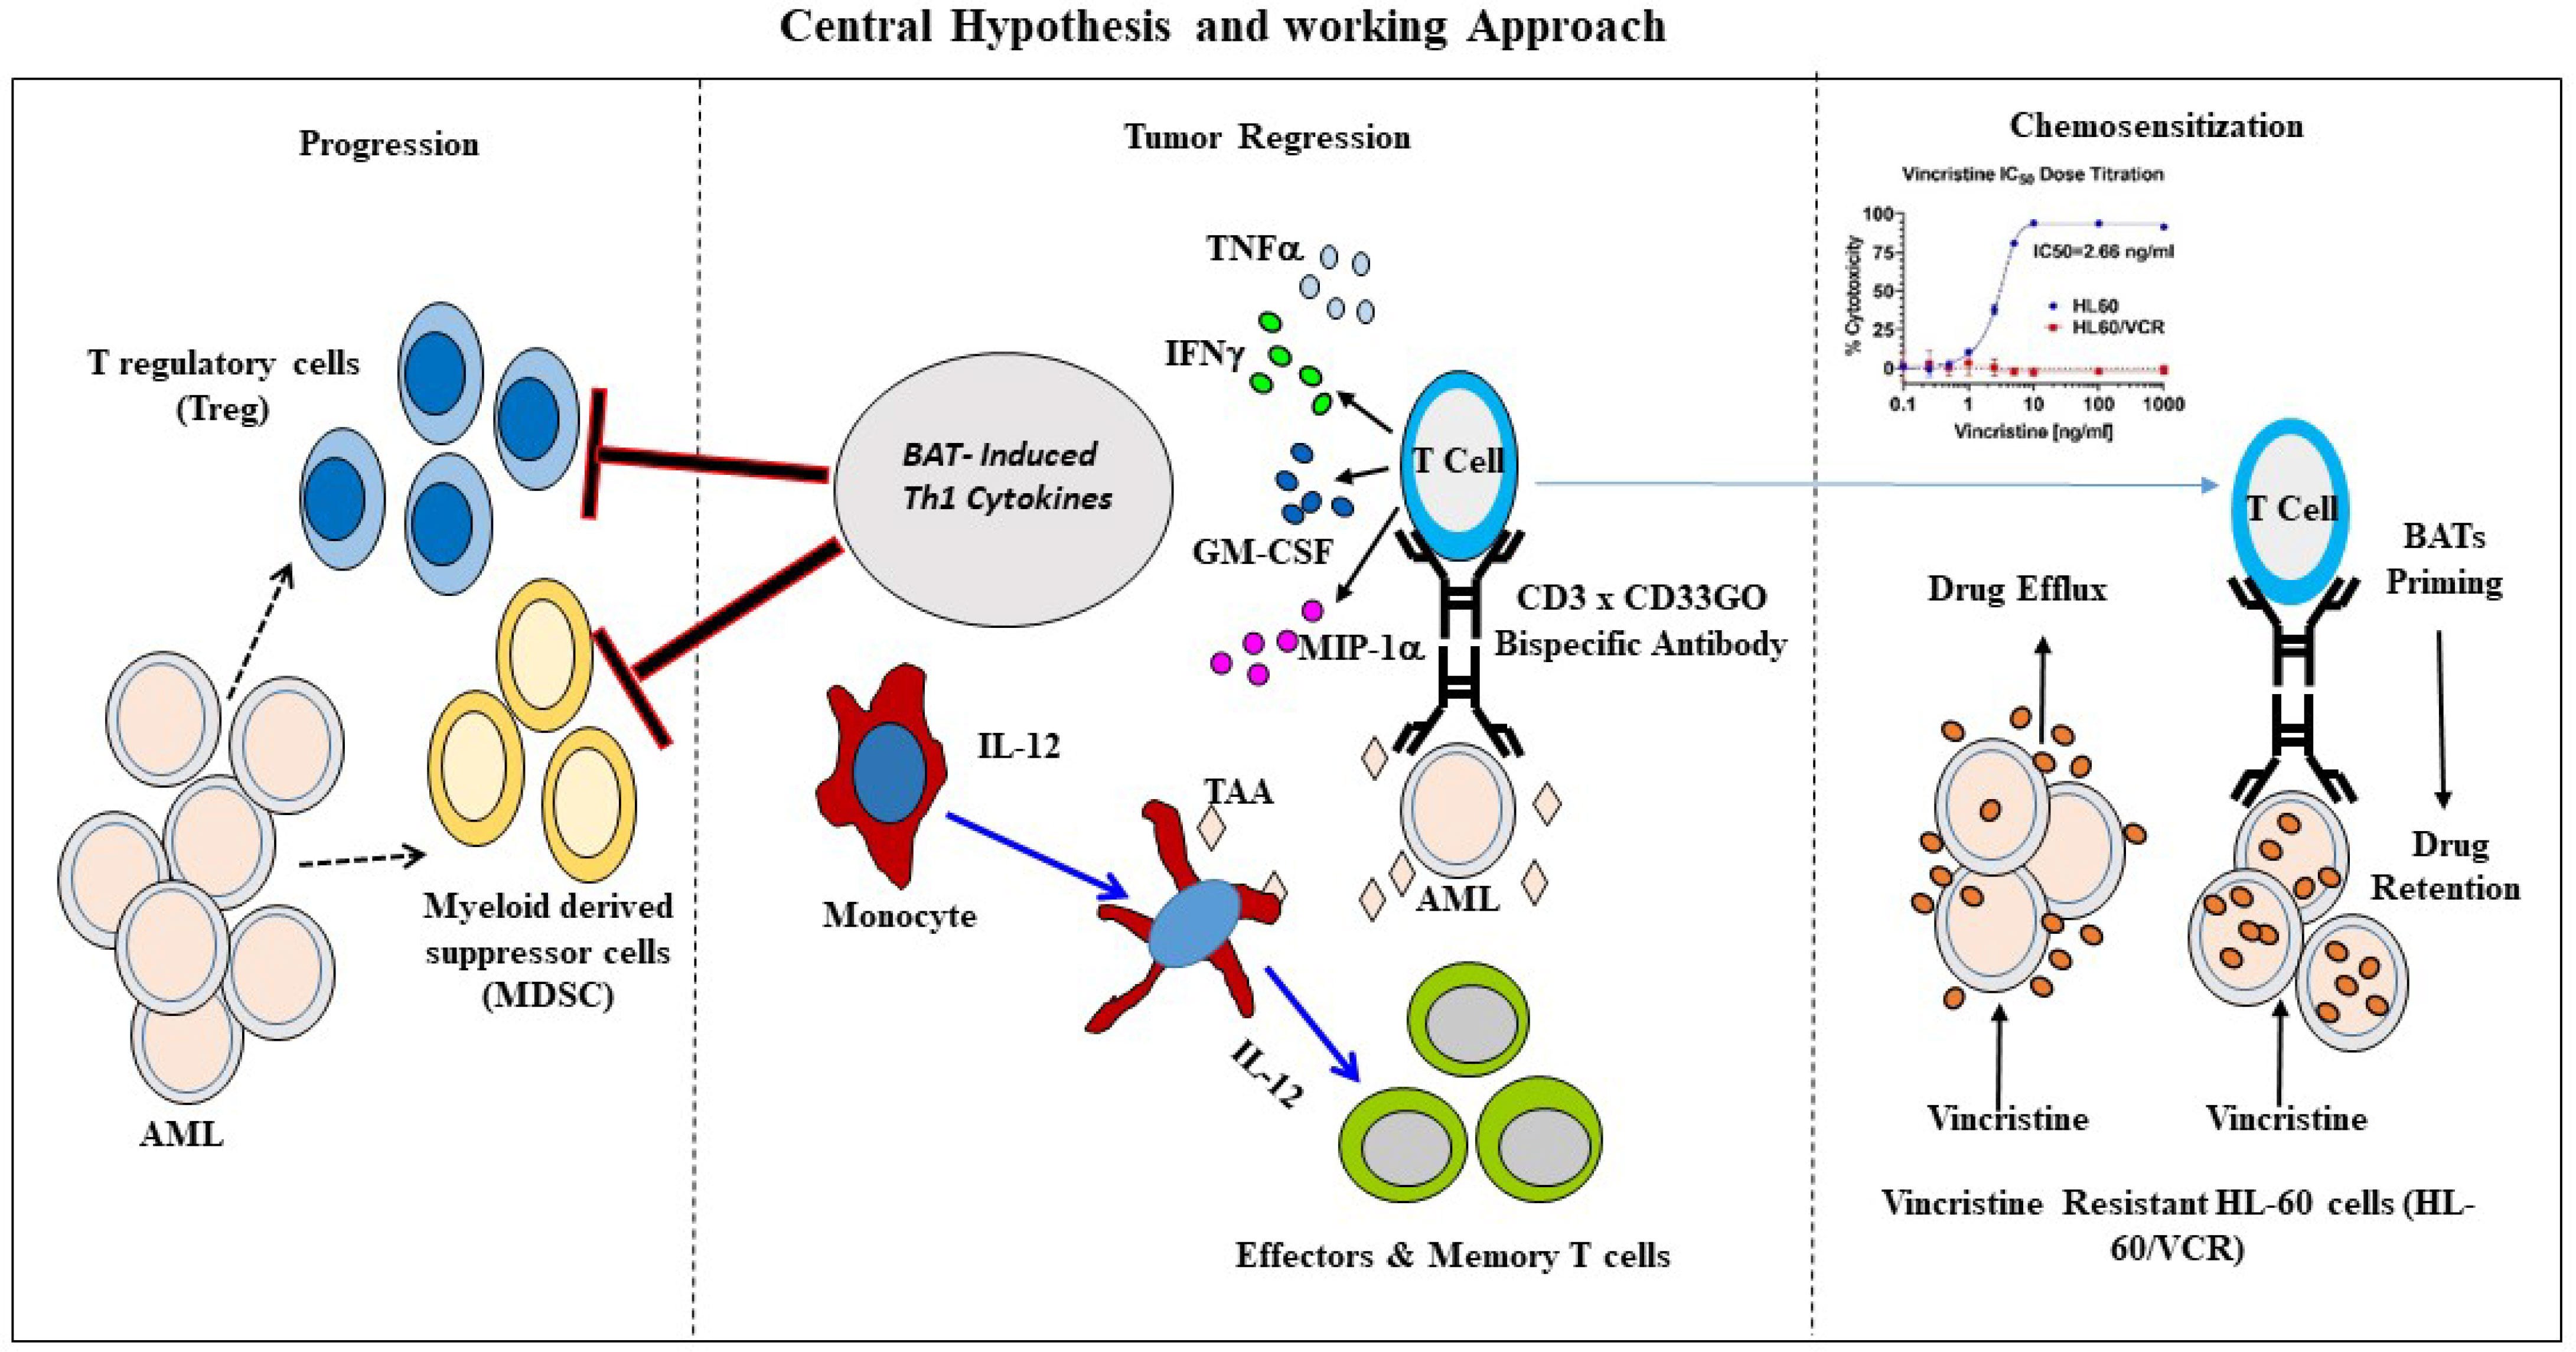
Gemtuzumab ozogamicin deserves a mention for favorable-risk core-binding factor AML, particularly acute promyelocytic leukemia variants. The Vercelty trial reinforced its place in intermediate-risk AML as well. Hepatic veno-occlusive disease remains the dose-limiting toxicity, especially if you give it concurrently with or immediately after high-dose cytarabine. Space it out. CPX-351, the liposomal formulation of cytarabine and daunorubicin, is approved specifically for therapy-related AML and AML with myelodysplasia-related changes. It is not interchangeable with standard 7+3. The liposomal delivery changes the pharmacokinetic profile entirely, and the data only support its use in those two specific subgroups. Using it in de novo AML without those features is off-label with no evidence base behind it. One counter-intuitive thing about AML targeted therapy that people miss: response assessment by standard blast count alone underestimates what is happening. With venetoclax combinations and IDH inhibitors, you often see a delayed marrow recovery with persistent cytopenias even as the leukemia is clearing. A day 14 or day 28 marrow showing 20 percent blasts does not automatically mean treatment failure on venetoclax + HMA. Flow cytometry minimal residual disease and molecular monitoring tell you more. I routinely check NPM1 mutation allele burden via digital PCR at days 14, 28, and then monthly rather than relying solely on morphology.
Get the Full Details
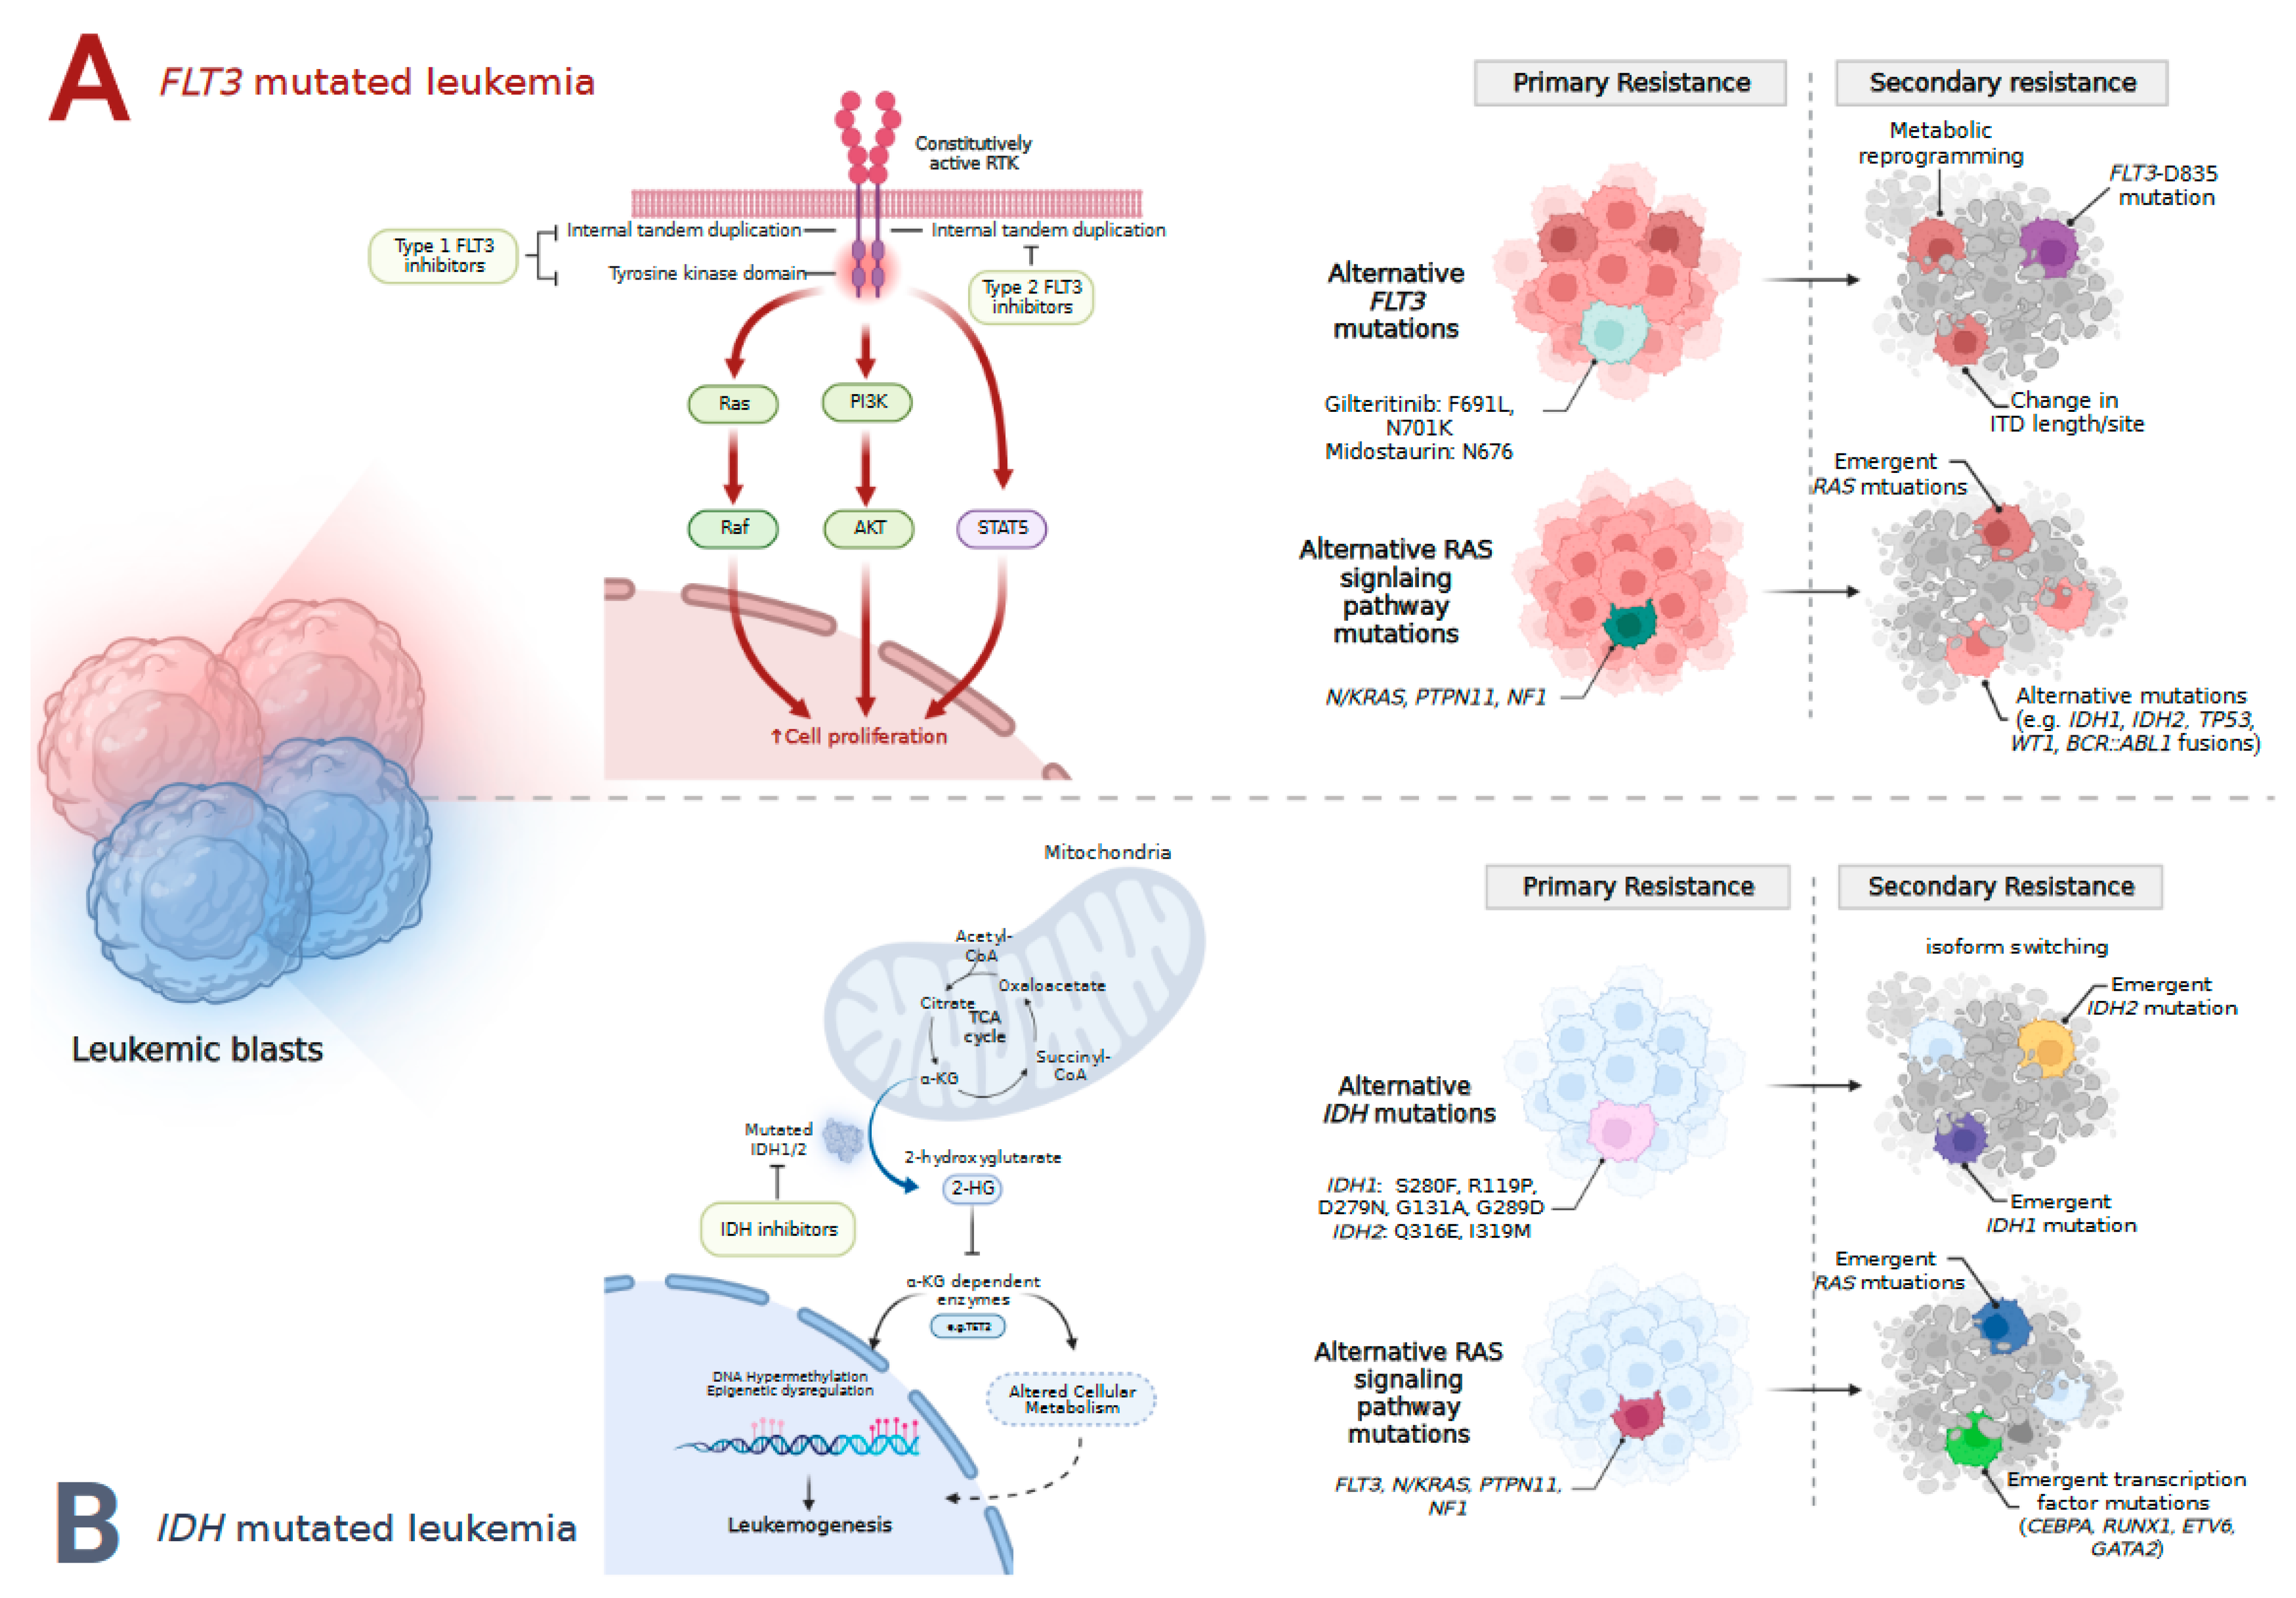
Another nuance that is easy to overlook: drug-drug interactions with azole antifungals. Fluconazole, voriconazole, and posaconazole all inhibit CYP3A4, which metabolizes venetoclax, midostaurin, gilteritinib, and enasidenib. When you need prophylactic antifungal coverage in a neutropenic patient, you typically reduce the venetoclax dose by approximately 50 to 75 percent depending on the specific azole. I keep a quick reference card at my desk because this changes between agents and the package inserts do not always align with each other. Posaconazole requires the most aggressive dose reduction of the three. The limitations are worth stating plainly. Targeted therapies in AML are not curative for most patients outside of transplant-eligible favorable-risk cases. Venetoclax combinations produce remission rates around 60 to 70 percent in unfit patients, but the median duration of response is measured in months for many. Relapse is the norm, not the exception, and resistance mechanisms accumulate — BCL-2 mutations, upregulation of MDM2, altered metabolism pathways. FLT3 inhibitors face similar resistance issues, with FLT3 re-mutation being common. We do not have good predictive biomarkers for resistance yet, which means we are largely flying blind when a patient stops responding. If you are evaluating a patient for targeted therapy, the practical workflow is: comprehensive NGS panel including FLT3-ITD allelic ratio, IDH1/2, NPM1, and KMT2A status before starting anything unless the patient is unstable. Then map the mutations to the approved and guideline-recommended options. For fit patients with FLT3-ITD, consider transplant sooner rather than later since targeted therapy alone will not sustain remission. For unfit patients, venetoclax + HMA is the default starting point with appropriate TLS prophylaxis and dose adjustments for concomitant medications.
The field moves fast enough that any specific detail you read here will be outdated within a year or two. The decision framework remains fairly stable, though. Genotype first, choose the targeted agent that matches, manage the toxicities proactively, and monitor with molecular tools rather than morphology alone. That is where the actual clinical value lies right now.