Breaking Down Ad Prefix Medical Terms Without Losing Your Mind
Medical documentation is littered with these constructions, and if you are typing them into any system, chart, or coding tool, you need to know what you are actually writing rather than blindly copying phrases you saw on a discharge summary from three years ago. The pattern is straightforward: a prefix modifies a root to describe location, condition, quantity, or time. That is it. But the way these combine creates massive ambiguity when you are working with clinical data or trying to map terms to ICD or CPT codes. Here is the order I use when I encounter something I have not seen before, and honestly, it saves more time than any flashcard app ever did. I start by isolating the suffix first because that usually tells me whether the word is describing a procedure, a condition, or a body part. Once I have the suffix locked in, I look at the root. Then and only then do I read the prefix. Reading left to right like a normal person will often send you down the wrong semantic path. For example, "subhepatic" does not mean "below the liver" in every context—it can mean an anatomical region descriptor in radiology reports versus a surgical approach descriptor in operative notes, and the distinction matters when you are billing or analyzing outcomes data.
Understanding Ad Prefix Medical Term Constructions in Practice
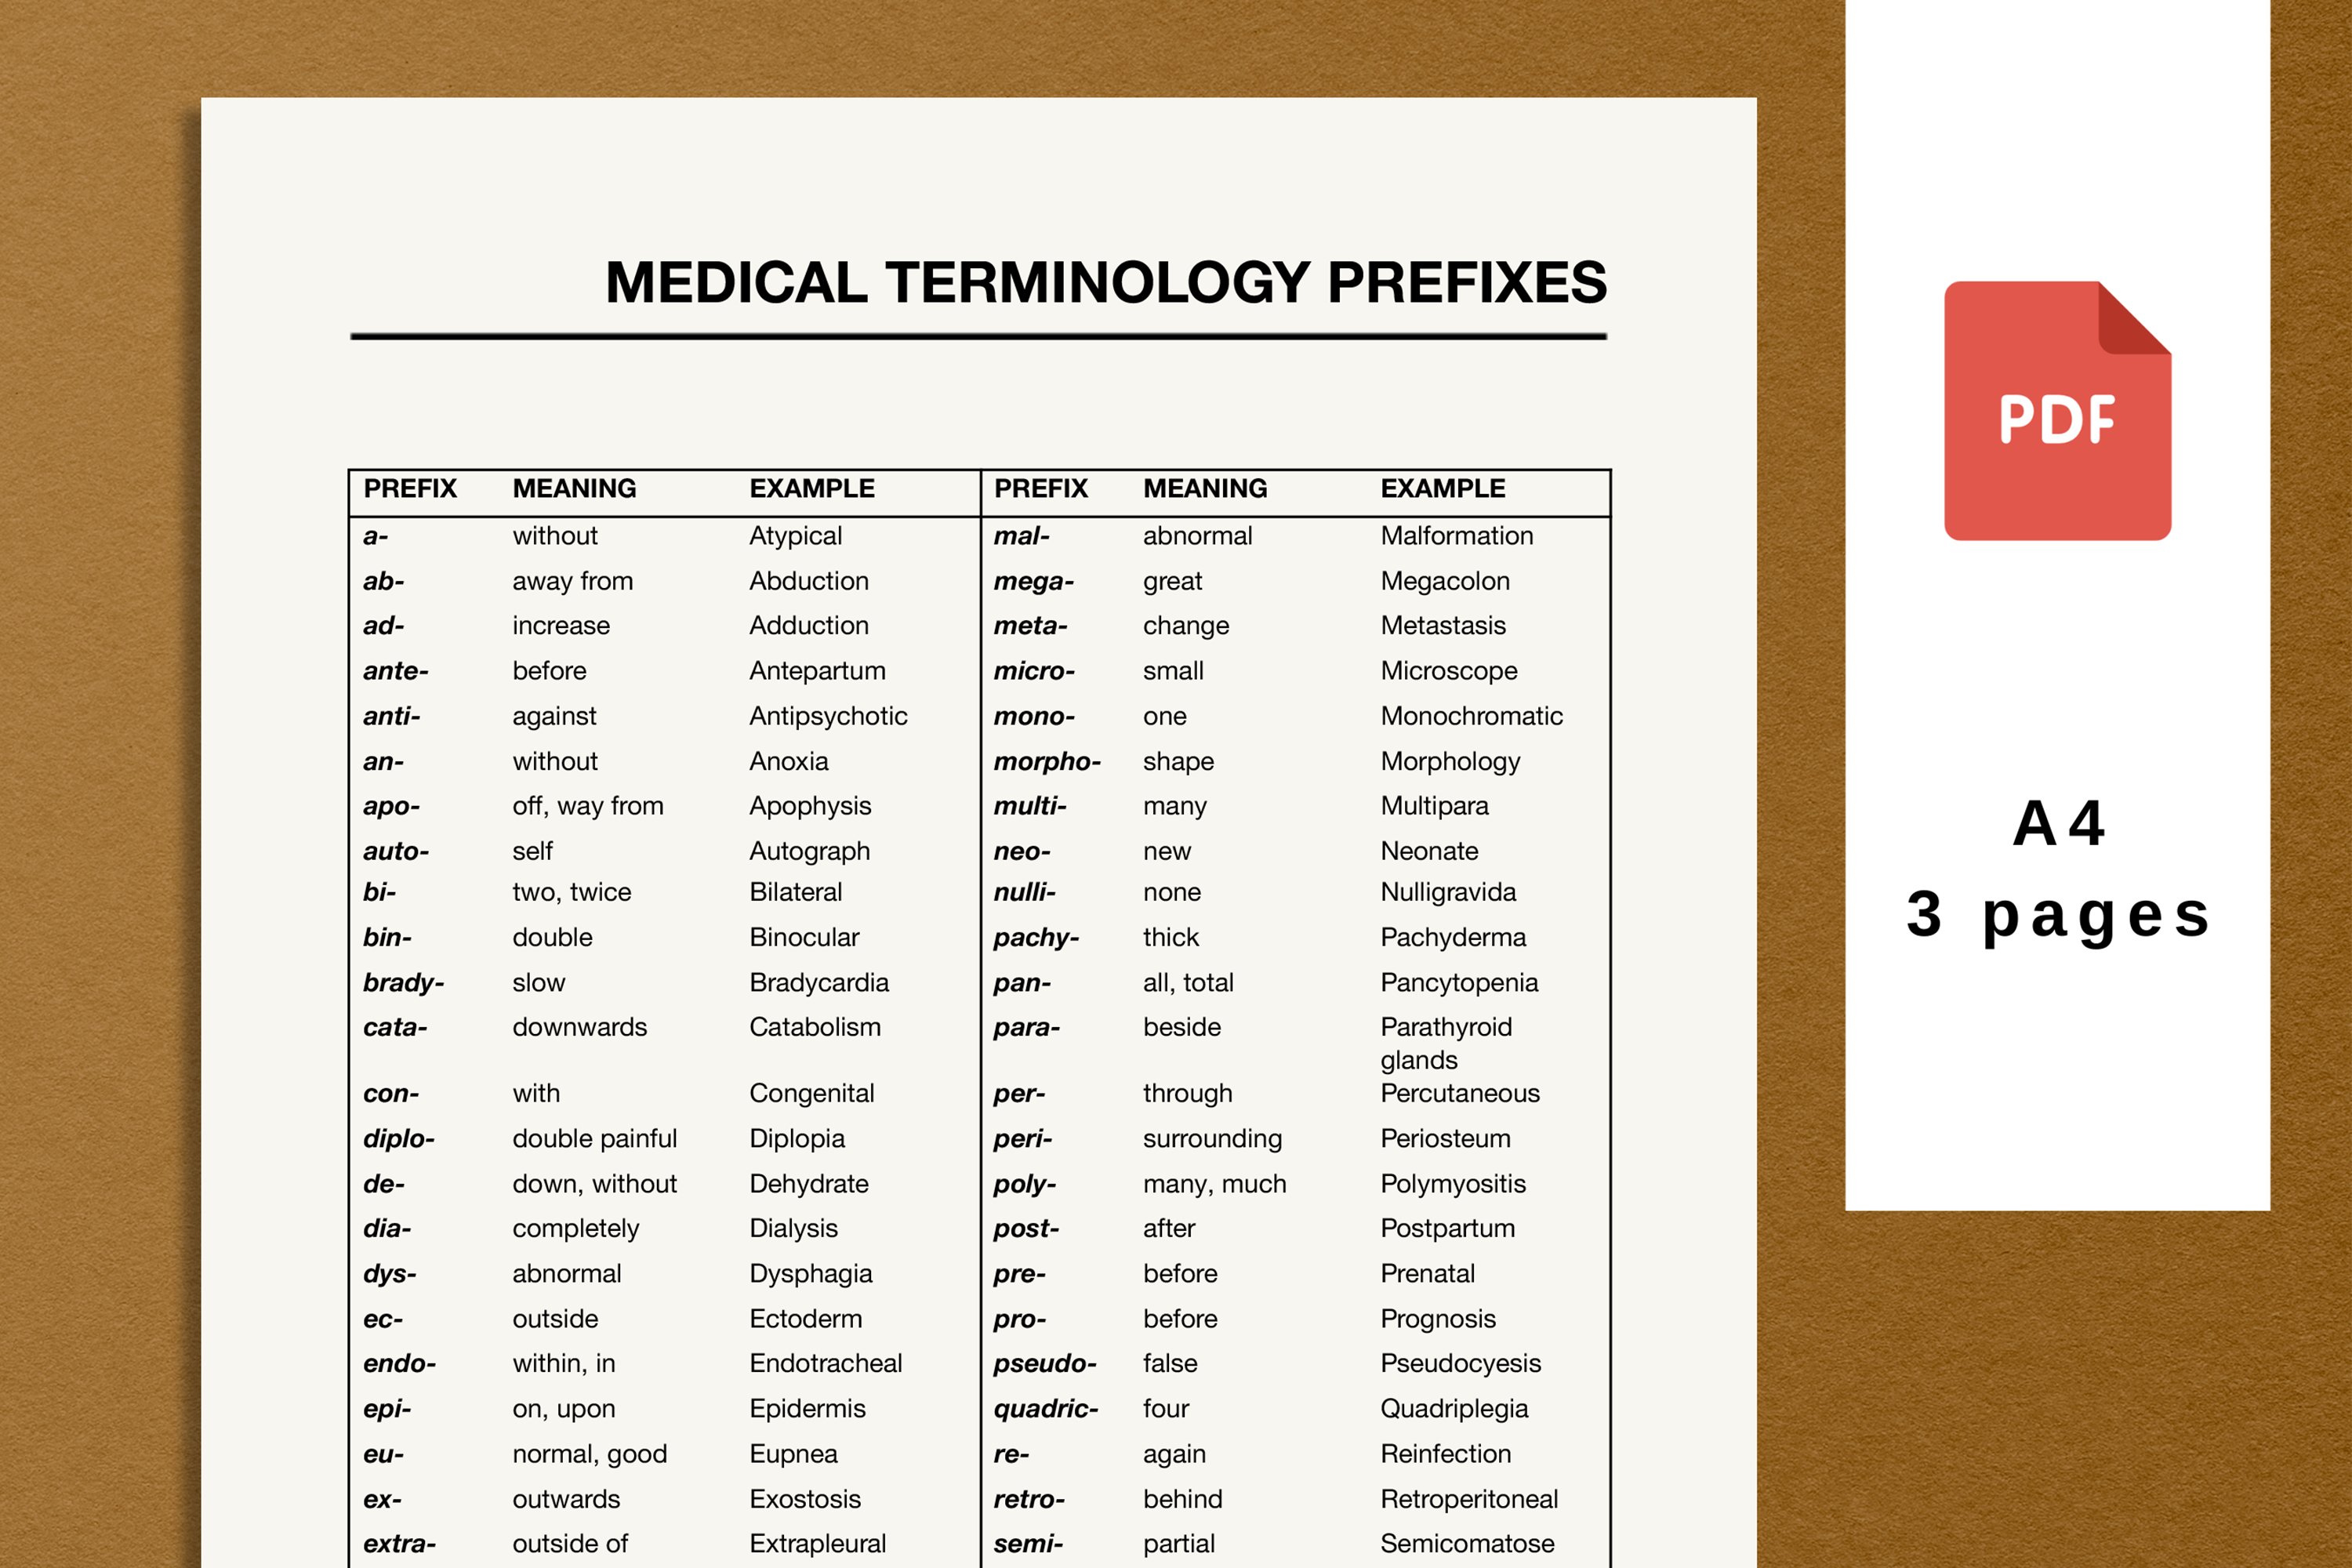
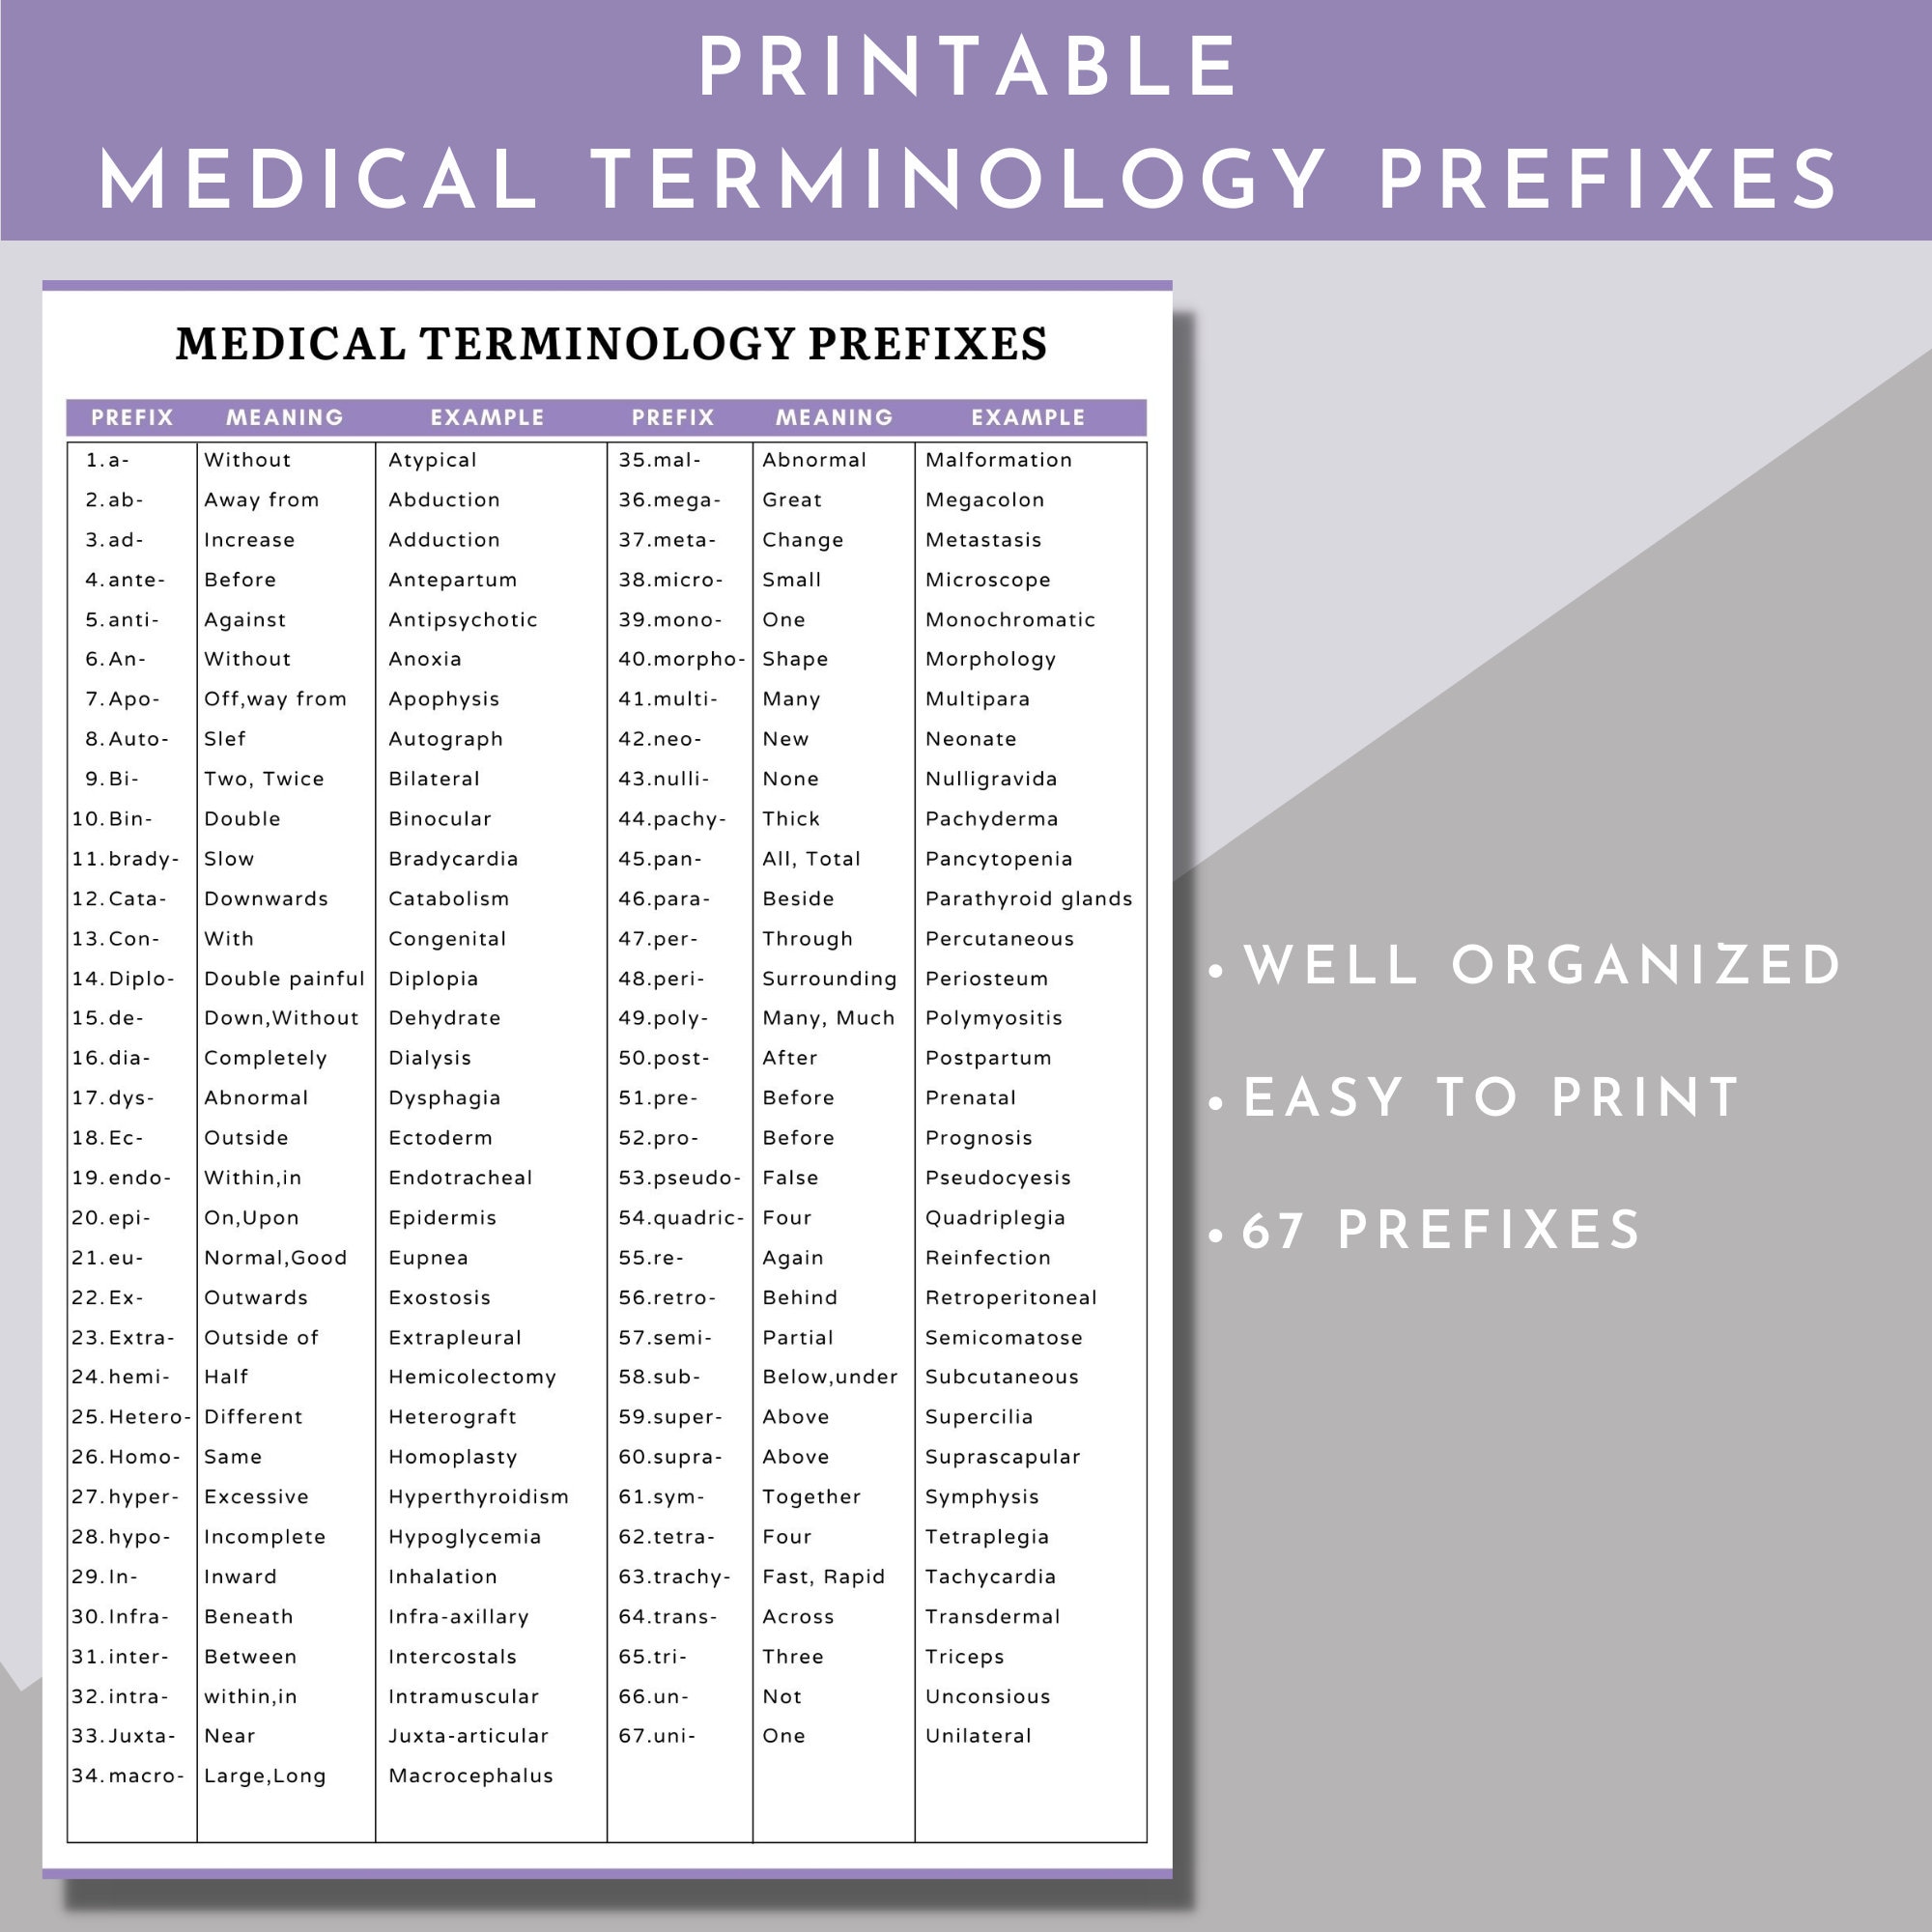
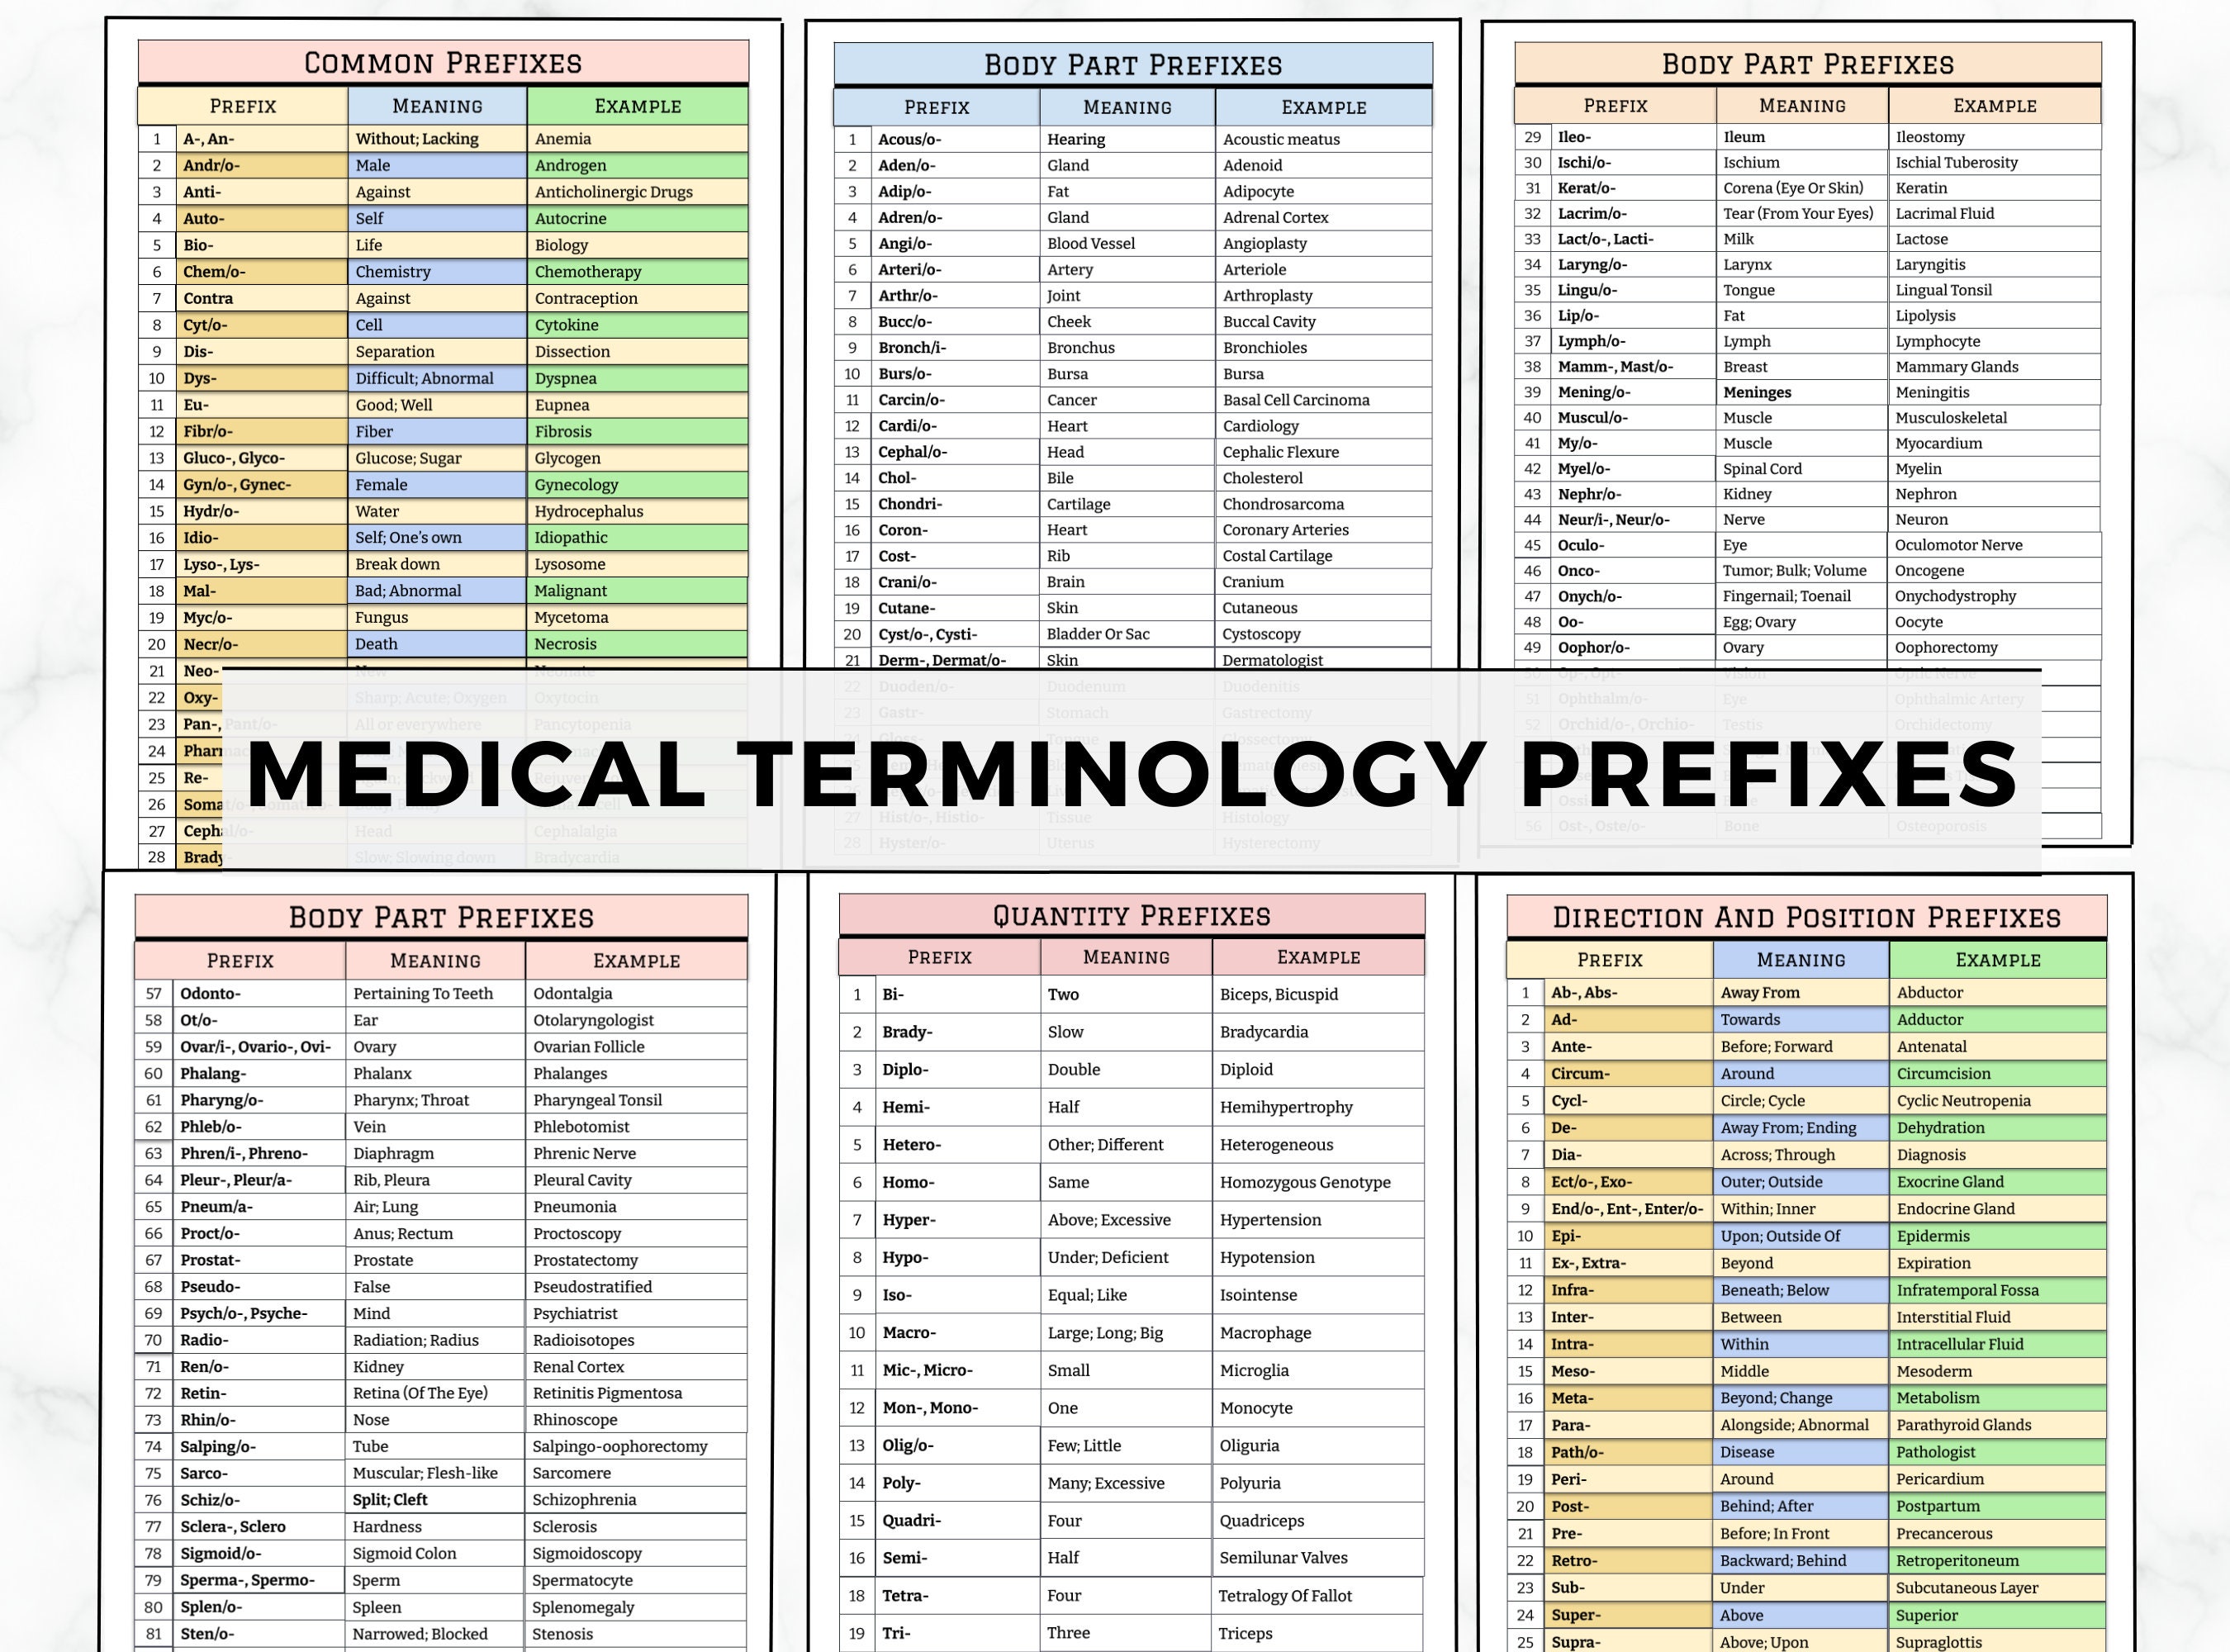
I spent roughly six months trying to clean up a dataset where every variant of "dys-" was coded as a single diagnosis. Dysphagia, dyspnea, dystonia, dysplasia, dysuria—they all share the prefix but map to wildly different conditions across completely different organ systems. The fix was not a regex. I built a lookup table that cross-referenced the full constructed term against SNOMED CT preferred terms instead of parsing individual morphemes. That cut my false-positive rate from about forty percent down to under four. The common prefixes you will run into repeatedly are sub- (below or beneath), peri- (around), epi- (upon or above), ante- (before), post- (after), para- (beside or near), trans- (across), intra- (within), extra- (outside), endo- (within), hyper- (excessive), hypo- (deficient), anti- (against), dys- (difficult or abnormal), mal- (bad or poor), poly- (many), oligo- (few), brady- (slow), tachy- (fast), pan- (all), and the negators a- and an- (without). Each one behaves differently depending on the root it attaches to, and some roots change meaning entirely when paired with certain prefixes. One thing nobody warns you about is that the same prefix can flip its interpretation between specialties. "Trans" means something very different in "transbronchial" versus "transplant." In the first case it means across a tissue plane, an anatomical descriptor for a biopsy approach. In the second it describes the act of moving an organ from one location to another. If your parsing logic treats them identically because they share the prefix, you will miscode procedures. I learned that the hard way when a hospital's automation layer was bundling transbronchial biopsies and transplants into the same DRG group and the finance team came knocking about a fifty-thousand-dollar discrepancy.
Another edge case that comes up constantly involves "pre-" and "ante-" being used interchangeably in some records but not others. "Preoperative" and "antepartum" are not synonyms just because both prefixes suggest "before." Mixing those up in a clinical NLP pipeline will break your temporal reasoning entirely. The workaround I settled on was building a prefix disambiguation layer that checked the root context against a specialty-tagged reference corpus before committing to a mapping. It added about two seconds of latency per term but eliminated the systematic errors that were slipping through rule-based parsers. If you are working with unstructured clinical text and need to extract these terms systematically, the most reliable path is not writing your own tokenizer. Use a library like MedSpaCy or the BCIP-MedNLP tools and layer your prefix logic on top of their entity recognition output. Building from scratch tends to produce results that look correct on small test sets but collapse under real clinical documentation noise. The tools handle the irregularities—misspellings, abbreviations, non-standard capitalization—so you can focus on the actual prefix-root relationships rather than debugging why your parser choked on "perihepatitis" with a missing letter. The biggest practical limitation of relying on prefix-root decomposition is that medical language is full of eponyms and brand names that will never match any morphological pattern. "Parkinson's disease" and "Adson's test" contain no useful prefixes to parse. You need a fallback dictionary for those, ideally sourced from a maintained ontology rather than a scraped webpage. I keep a custom supplement of eponyms and proprietary terms mapped to their standard terminology equivalents, and I merge it with any automated extraction before pushing results into downstream systems.
Get the Full Details

For reference material, the AAMA's Medical Terminology textbooks and the NLM's MeSH vocabulary remain the most consistent sources for understanding how these constructed terms are meant to work. The Merriam-Webster Medical Dictionary online is also decent for quick lookups when you are uncertain whether a combination is standard or a clinician's idiosyncratic shorthand. I keep all three bookmarked and reach for them regularly because even after years of this work, I still encounter term constructions that are technically grammatical but clinically unusual.
Download and Tooling Notes
There is no single downloadable file that will handle all of this for you out of the box because the problem space is too dependent on your specific data source and target encoding system. What I do distribute is a Python utility that loads a prefix-root-suffix decomposition table and outputs normalized term mappings in both SNOMED CT and ICD-10-CM format. You can find it on GitHub under the repository name med-prefix-parser along with installation instructions and a sample clinical corpus for testing. The license is MIT, so you can modify it for your own pipelines without restriction. The utility depends on spaCy with the en_core_med_mentions model, and the setup typically takes about ten minutes on a standard machine. If you are pulling terms from EHR exports with inconsistent formatting, I recommend running a normalization pass through the tool before attempting any bulk coding or analysis. The difference between raw and normalized term sets in my experience has been substantial enough to change reporting outcomes on quarterly quality metrics.