ADA Caries Risk Assessment: What Actually Happens in the Chair
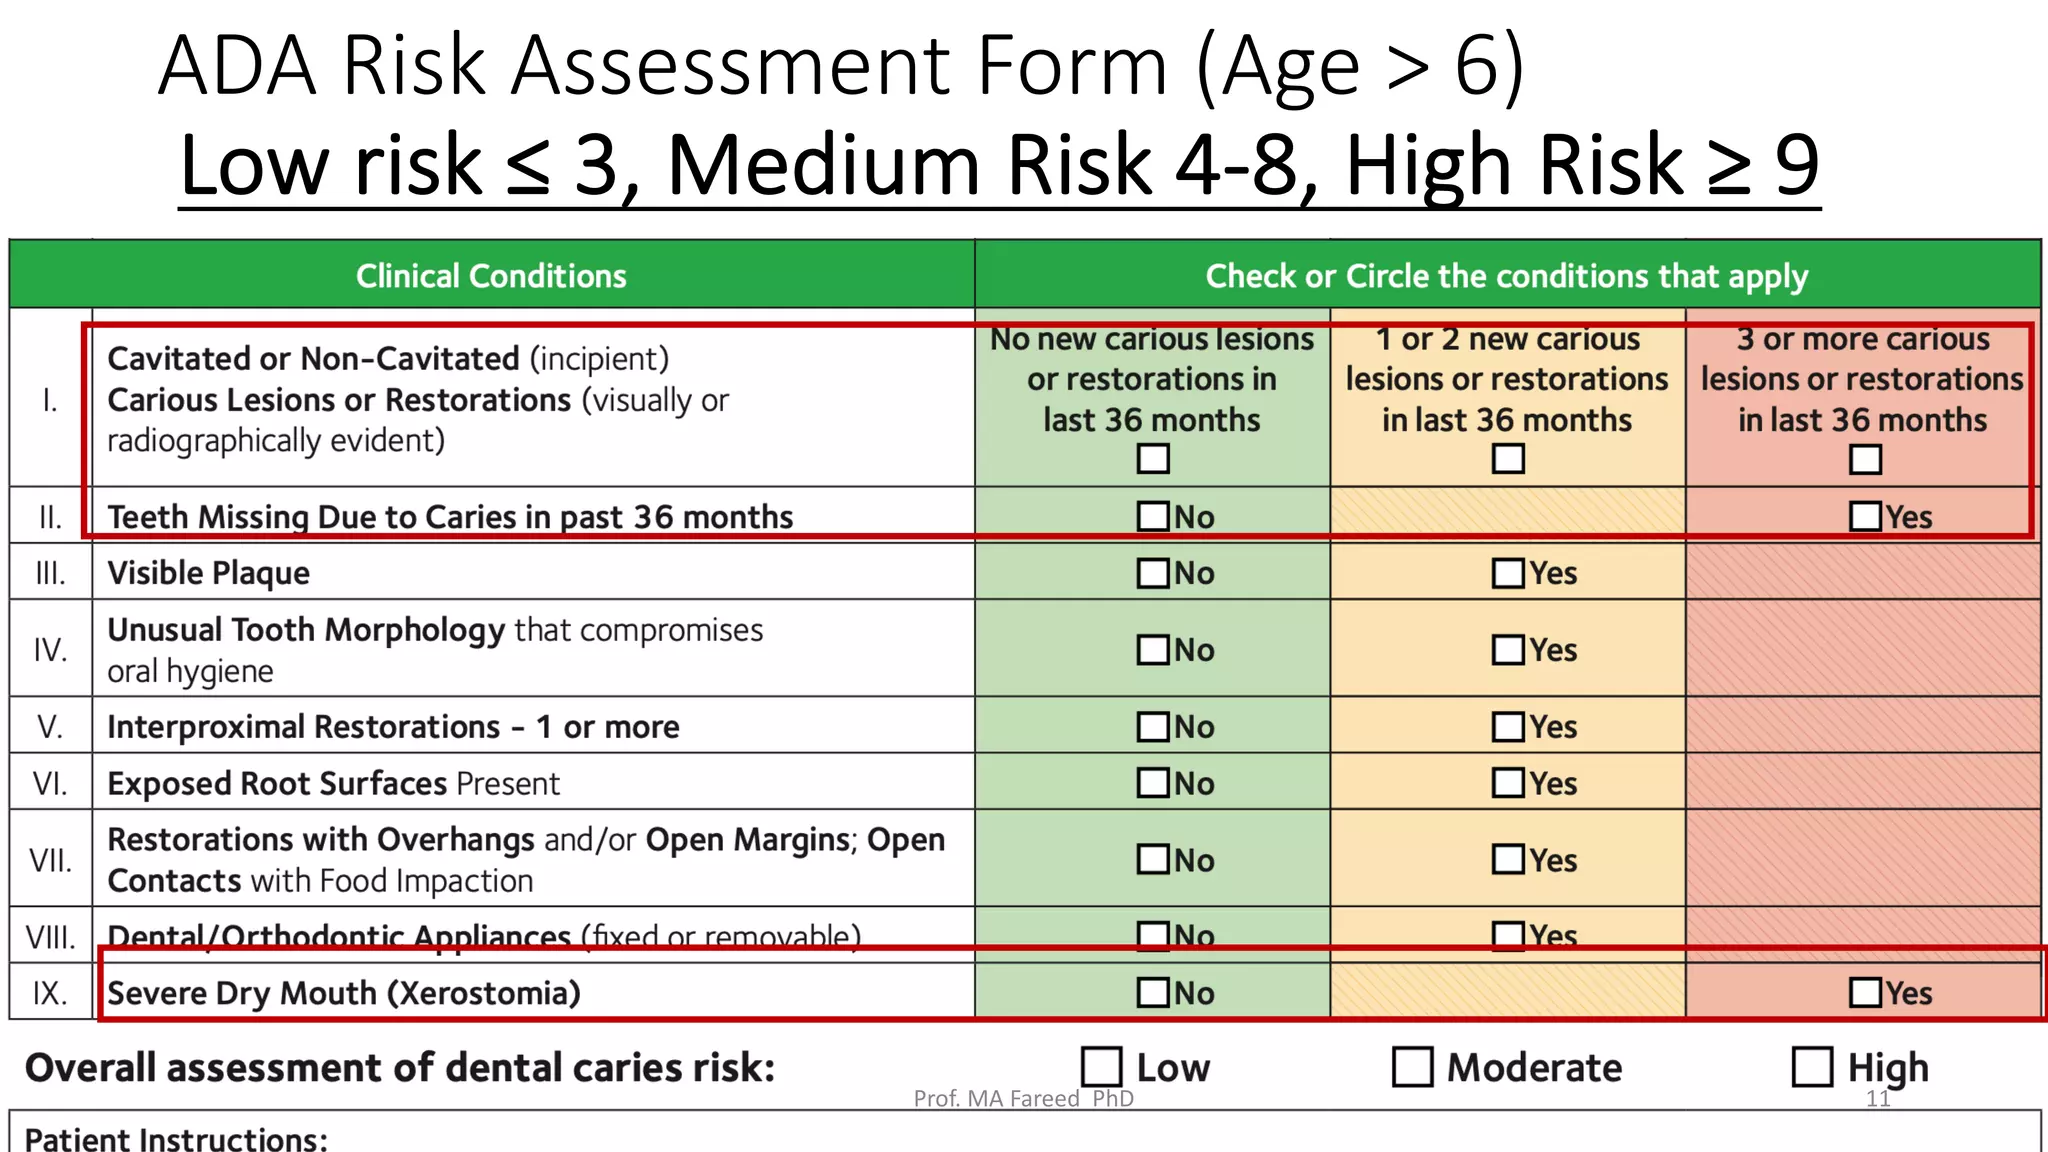
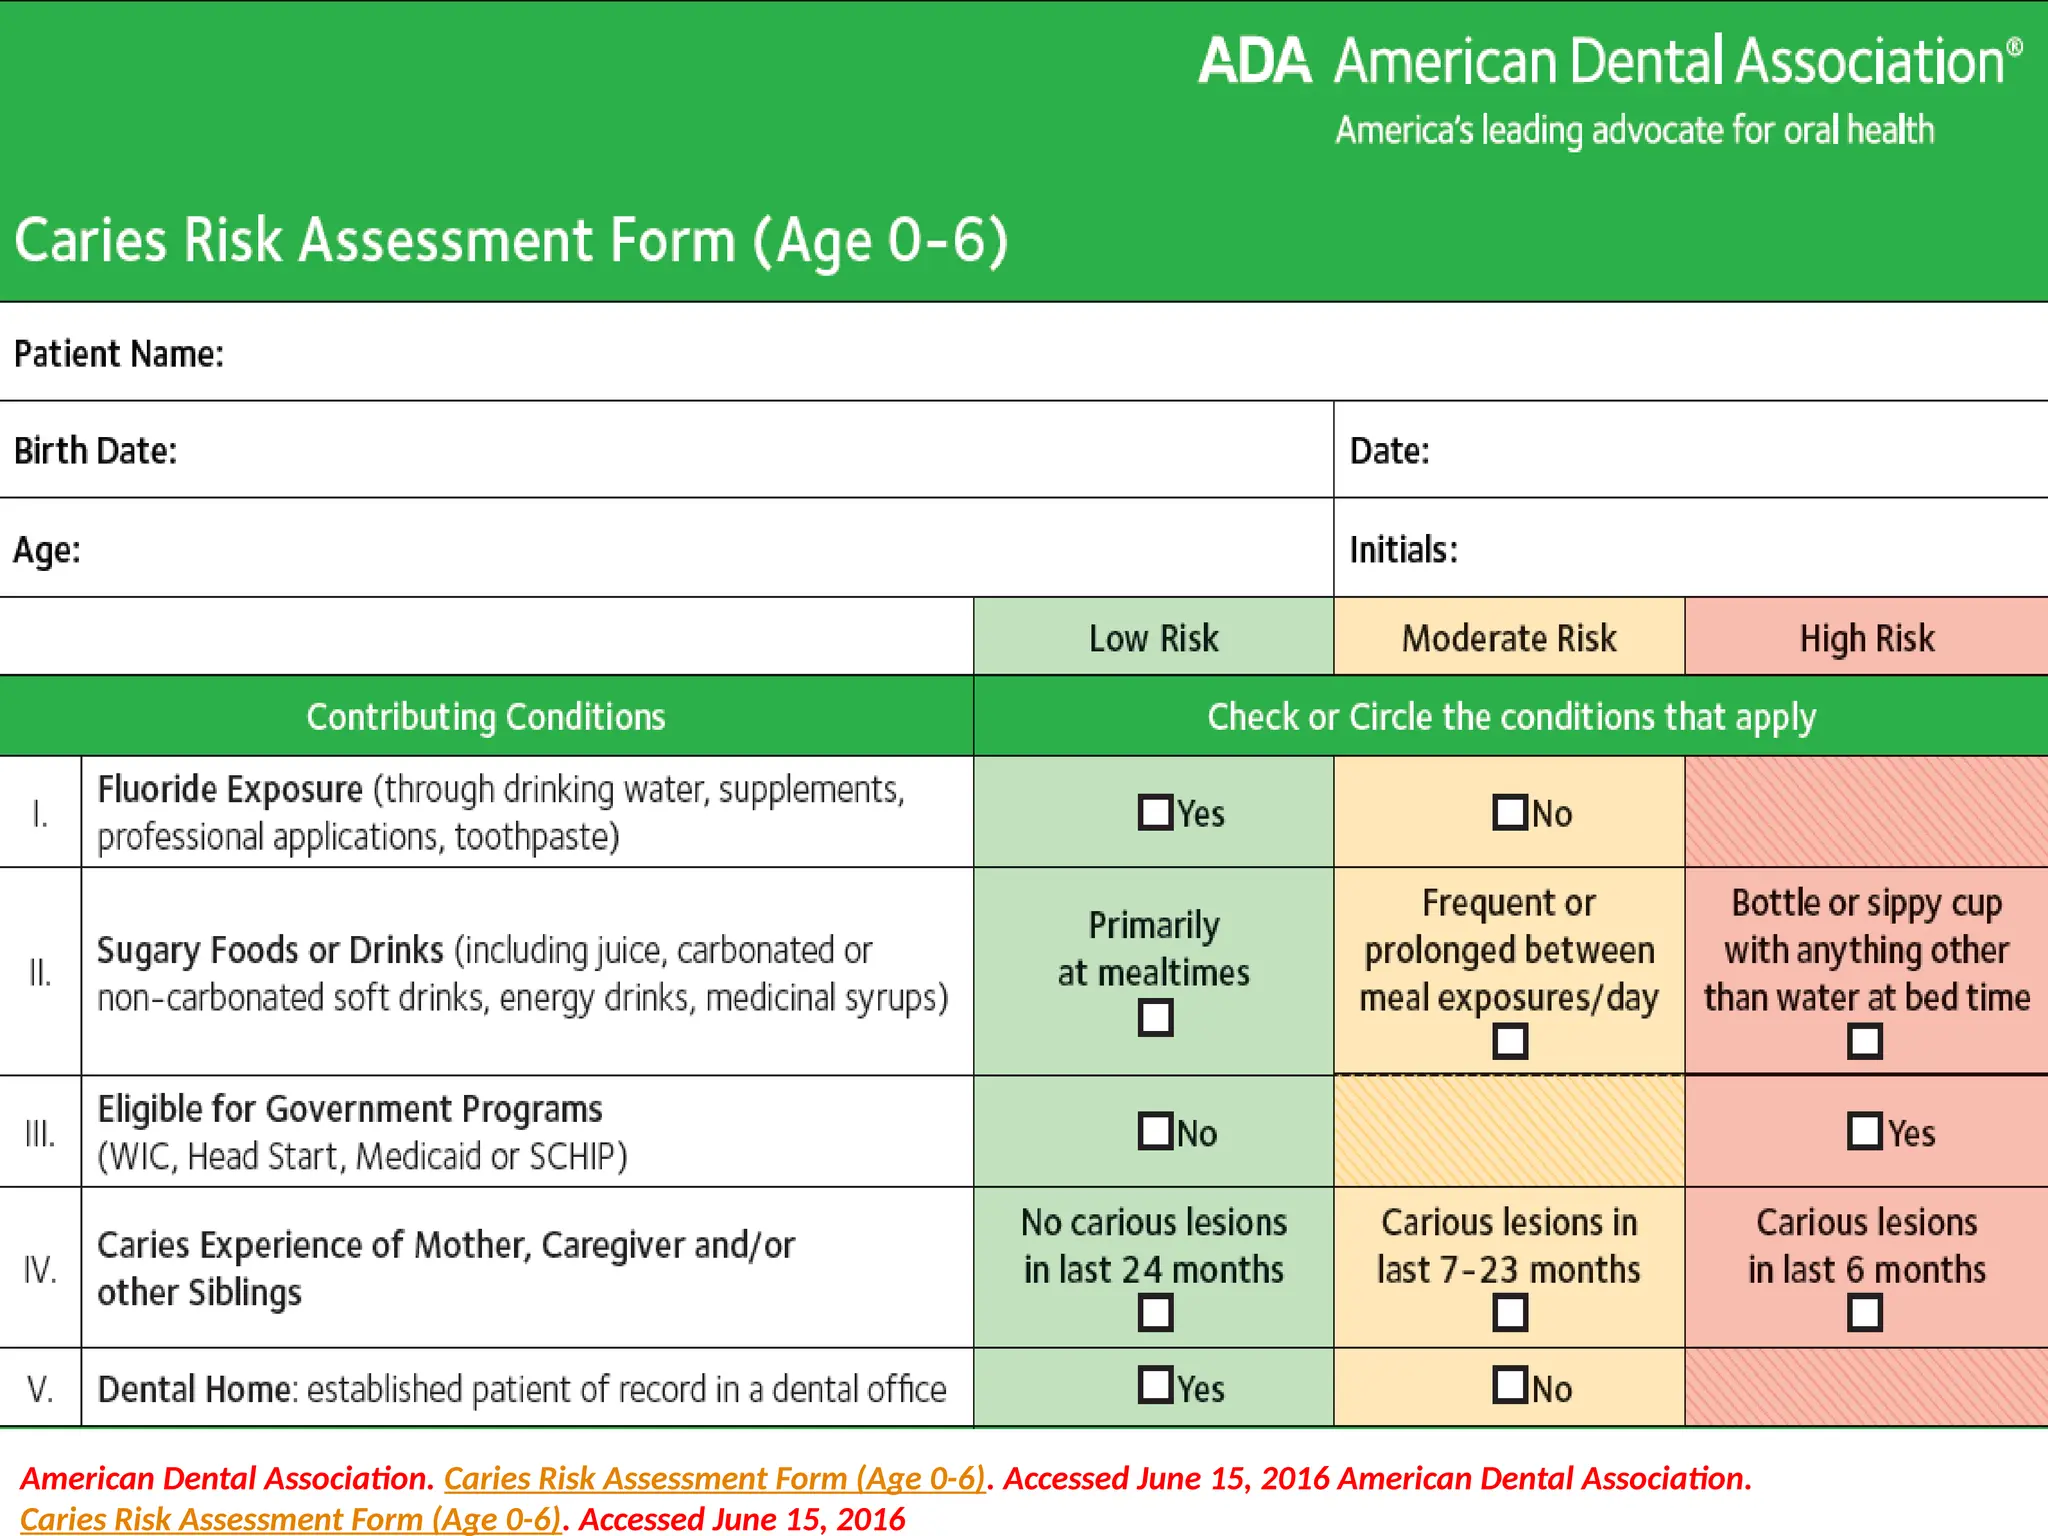
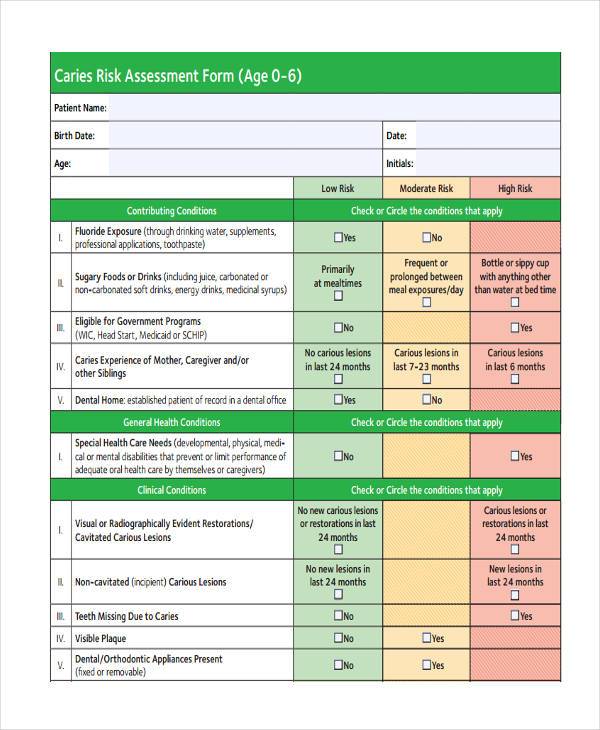
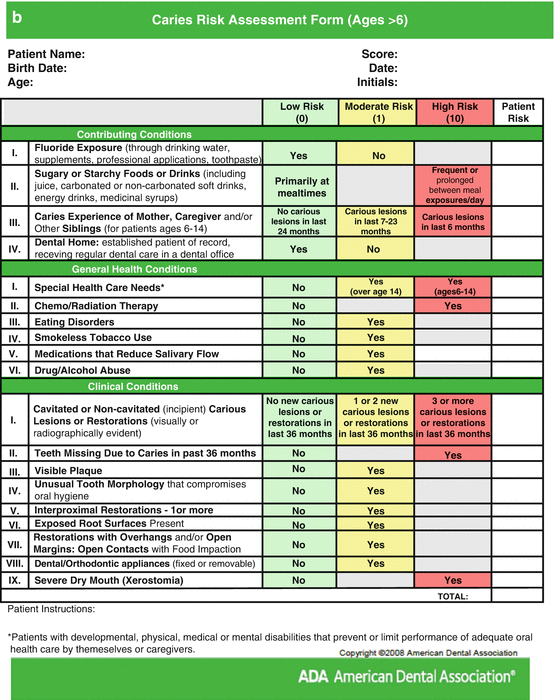
The ADA doesn't have a single unified tool called "Ada Caries Risk Assessment." It has a few separate guidelines and a risk assessment form that gets updated periodically. The most commonly referenced one is the ADA Council on Scientific Affairs document from 2008, which lays out criteria for low, moderate, and high caries risk. There's also a pediatric version. These are clinical decision aids, not algorithms that spit out a number on their own. What people usually mean when they say "Ada Caries Risk Assessment" is the process of taking a patient's history and clinical findings and matching them against the ADA's risk factor checklist. Diet frequency. Saliva flow. Prior restorations. Fluoride exposure. Plaque levels. Those are the variables. You score them, categorize the patient, and then you decide on recall interval and preventive strategy.
Ada Caries Risk Assessment in Practice
I'll walk through how this actually works, because the published guidelines are thin on the operational details. Here's the form structure, the scoring logic, and where it breaks down. You start by checking for medical conditions that affect caries risk. Diabetes, xerostomia from medication, head and neck radiation therapy, GERD. Each of these shifts the baseline. A patient on antihypertensives that cause dry mouth is already in a higher bracket before you look at anything else. That's point one. Next you look at sociobehavioral factors. Diet frequency is the big one here. The ADA counts eating or drinking anything with available carbohydrates more than three times a day as elevated risk. This includes sugar-free but acidic beverages. People miss that one constantly. Soda water with lemon, unsweetened iced tea that's been sitting out, even gum with sugar alcohols — frequent exposure matters more than the sugar content itself.
Then you tally visible plaque. You're not doing a full periodontal chart here. You're looking at whether plaque is regularly present on smooth surfaces. If the patient can't keep plaque off their teeth with normal brushing, that's a risk marker regardless of how much fluoride they get. Prior caries experience is the strongest single predictor. Adults with two or more restorations in the past three years are high risk. Children follow slightly different thresholds. One new cavity in a high-risk environment is a different conversation than three fillings replaced in eighteen months.
Get the Full Details

How to Actually Run the Assessment
Print the ADA caries risk assessment form or pull it up digitally. Go through each domain in order. Don't skip the medication review — that's where most assessments go wrong. I've seen dentists miss xerostomia risk because they didn't ask about the full med list and the patient assumed their blood pressure pill was irrelevant. For each criterion, mark present or absent. Then cross-reference with the ADA's categorical guidance. Low risk means zero or one risk factor and no active decay. Moderate risk has two or three factors or a history of early childhood caries in pediatric patients. High risk is four plus factors, active lesions visible, or xerostomia with poor oral hygiene. These aren't hard mathematical boundaries. They're clinical judgment zones. Once you've categorized the patient, the recall interval follows. Low risk gets six to twelve months. Moderate gets six months. High risk gets three to four months with supplementary fluoride and possibly silver diamine fluoride if they have active lesions. The ADA document doesn't mandate these intervals — it recommends them based on the evidence available at the time of publication.
Where the ADA Model Falls Apart
The 2008 guidelines are now significantly outdated in terms of the evidence base. Newer research on the microbiome, on salivary diagnostics, and on minimally invasive intervention isn't reflected. The risk factor list is still useful as a starting framework, but treating it as complete is a mistake. I ran into this explicitly last year with a patient who tested low risk by every ADA criterion. No prior restorations, good fluoride exposure, low sugar frequency. But she had a deep pit on her lower first molar that was already cavitated. The assessment missed it because it's focused on risk factors, not on individual tooth morphology and early lesion detection. I added a bitewing schedule and pit and fissure sealant recommendation that the risk category alone wouldn't have triggered. That's a known limitation of the model — it's population-level guidance applied to individuals. Another gap is the handling of orthodontic patients. Fixed appliances change the risk calculus dramatically, and the ADA form doesn't have a specific checkbox for that. Braces create plaque retention zones that no amount of daily flossing eliminates. These patients need adjusted intervals regardless of their baseline score.
Tools and Forms
The ADA doesn't publish a free downloadable form on their website anymore. The original 2008 document is behind a paywall or buried in their clinical resources section. Most practices use modified versions from dental supply companies or state dental association templates. The CDC also has a simplified caries risk assessment tool that's closer to the ADA framework but more accessible. Some practices build their own based on the ADA criteria and run it through their practice management software. If you need the actual ADA Caries Risk Assessment form, check with your state dental association or look through older editions of the Journal of the American Dental Association. The criteria themselves are widely reproduced in dental hygiene and assistant textbooks. The specific formatting varies between sources but the underlying factors remain consistent.
Common Mistakes That Ruin the Assessment
Skipping the dietary history is the most common error. Patients will tell you they don't eat much sugar and mean it, but they're sipping flavored sparkling water all day. The pH impact is real. You need to ask specifically about frequency, not just content. "What do you drink between meals?" gets you closer to the truth than "Do you drink soda?" Another mistake is treating the risk category as final. It's a snapshot. A patient who's high risk today can drop to moderate in six months if you intervene properly. The reassessment should happen at each recall visit, not once a year. I track my high-risk patients on a separate log so I catch score changes early. The third error is documentation. If you didn't write down the assessment, it didn't happen. Insurance companies and legal reviews don't care that you mentally ran through the criteria. Your chart needs to show which factors were present, the category assigned, and the plan that followed. That's it. Three lines that save you from a lot of headaches.
The ADA Caries Risk Assessment remains a useful clinical tool even with its age and gaps. It forces you to think systematically about caries rather than reacting to cavities after they appear. Use it as a starting framework, not a finish line. Add your own clinical observations on top of it and reassess regularly. The patients who benefit most from this are the ones you'd otherwise miss until they're in pain.