Understanding Surgical Coding in Practice
Surgical coding isn't something you pick up from reading textbooks alone. I spent seven years working in oral surgery billing before transitioning into consulting, and the gap between what the manuals say and what actually happens in a clinic is wide enough to drive a truck through. One of the most common areas where coders get tripped up is the intersection of surgical guides and ADA codes, particularly when dealing with implant placement, bone grafting, and sinus lifts. Let me walk you through how this actually works, the mistakes I see repeatedly, and the few workarounds that have held up over time. The American Dental Association maintains a comprehensive coding system for dental and oral surgical procedures, and the way surgical guides factor into coding depends entirely on what type of guide you're using and how it's documented. When I worked in practice, we dealt primarily with static surgical guides for implant placement and some custom soft-tissue management systems. The confusion starts here: the ADA code system doesn't have a dedicated code specifically for "surgical guide" as a standalone procedure. Instead, the guide becomes part of the surgical plan and is billed under the procedure it facilitates. Most implants fall under codes 6010 through 6059 in the ADA CDTC (Current Dental Terminology) system. A typical implant placement with a surgical guide uses code 6016 for the implant itself, and the surgical guide is considered part of the surgical service unless it's a separately manufactured component. This distinction matters enormously for insurance claims, and I learned it the hard way after a claim got denied three times because we listed the guide separately when it should have been bundled.
When Surgical Guides Change the Coding Landscape
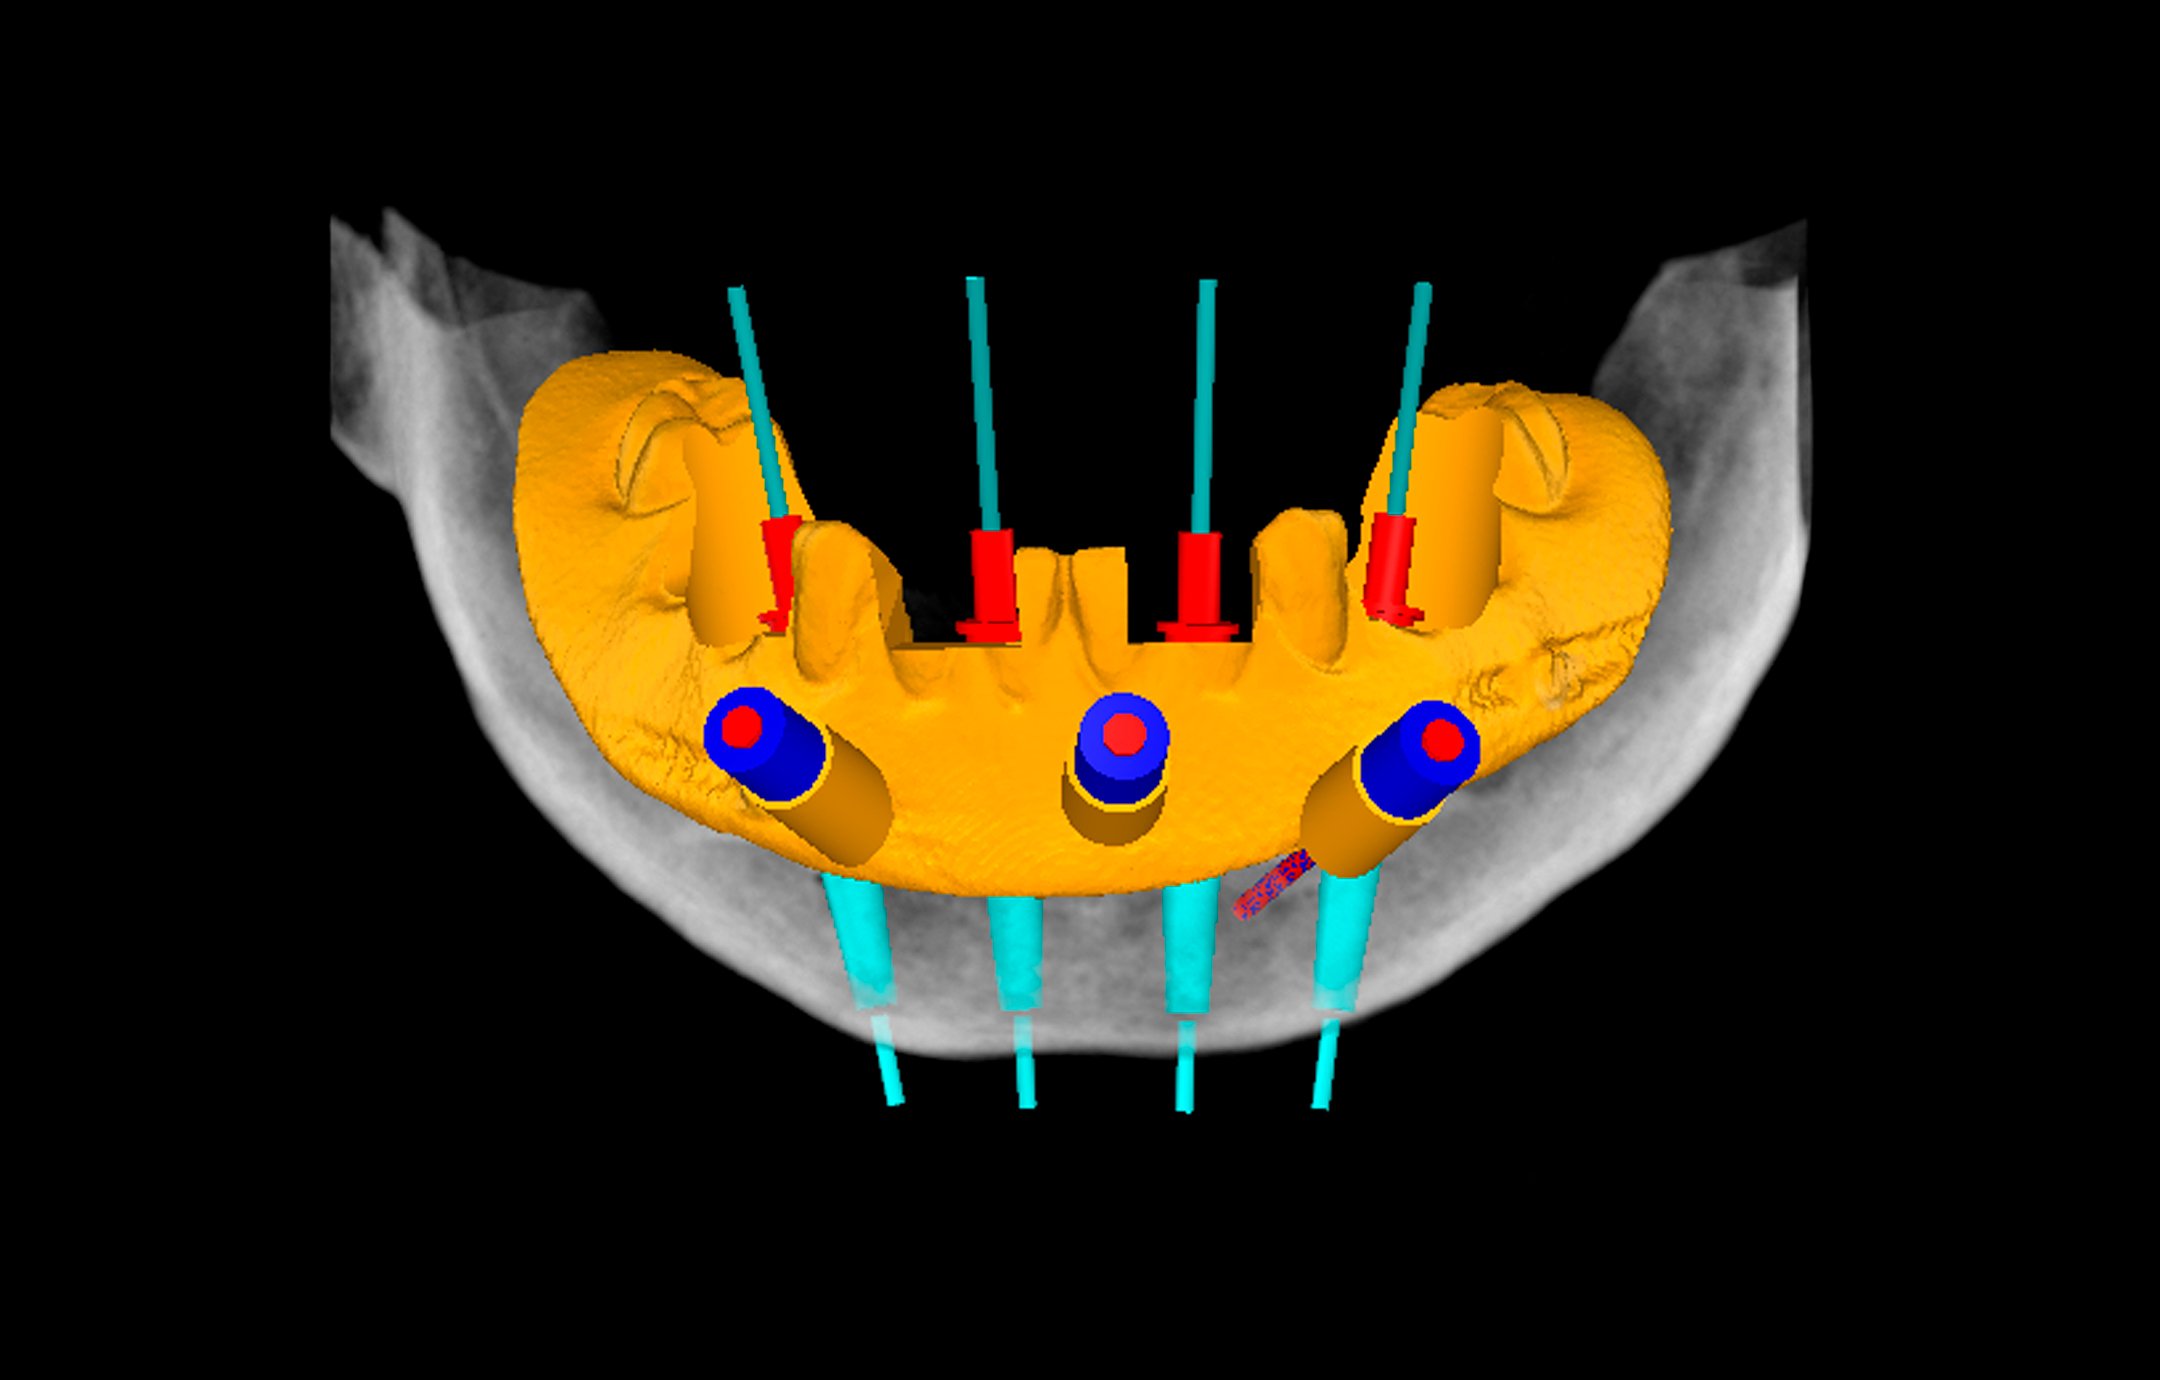
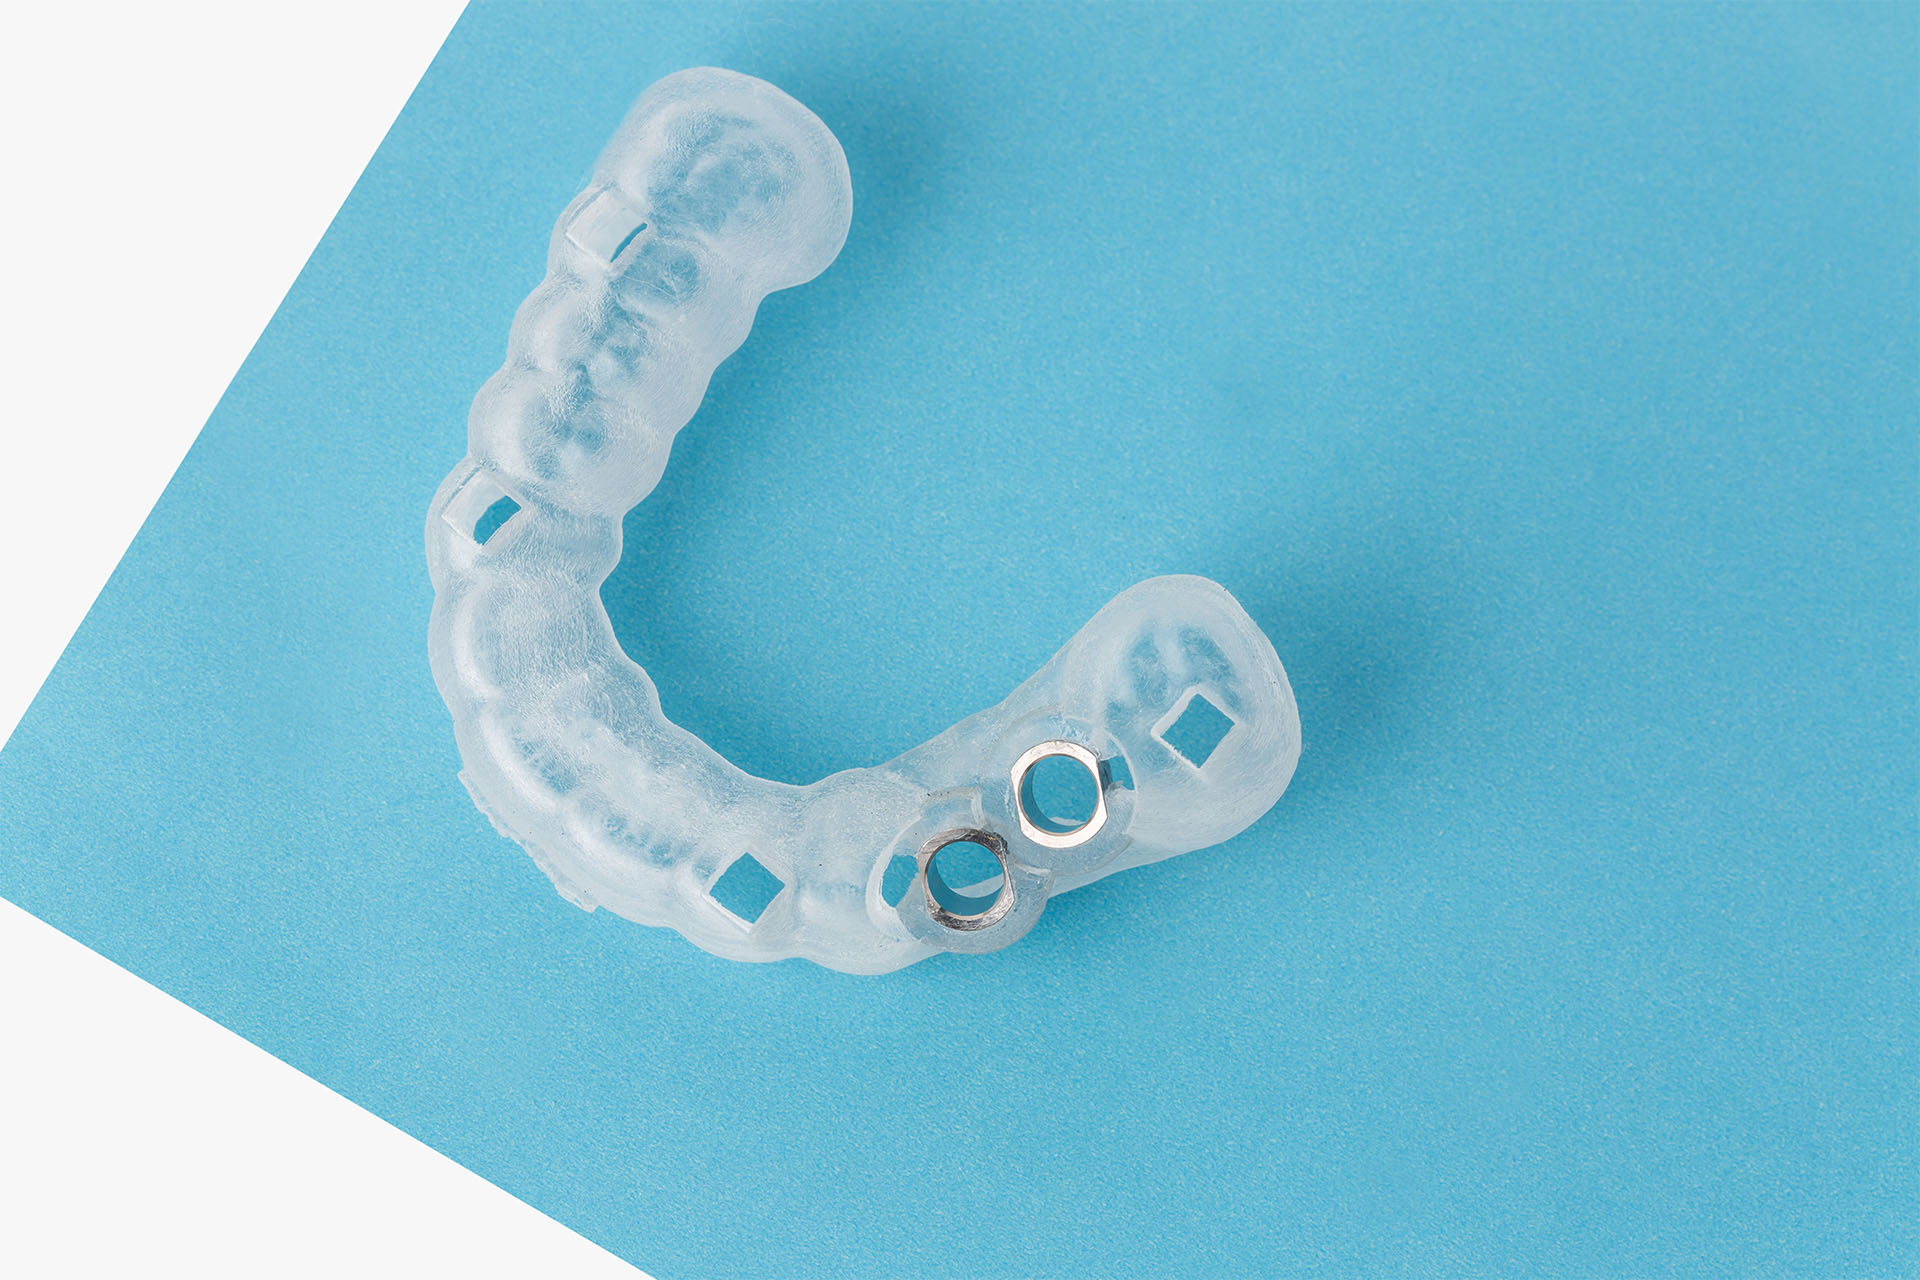
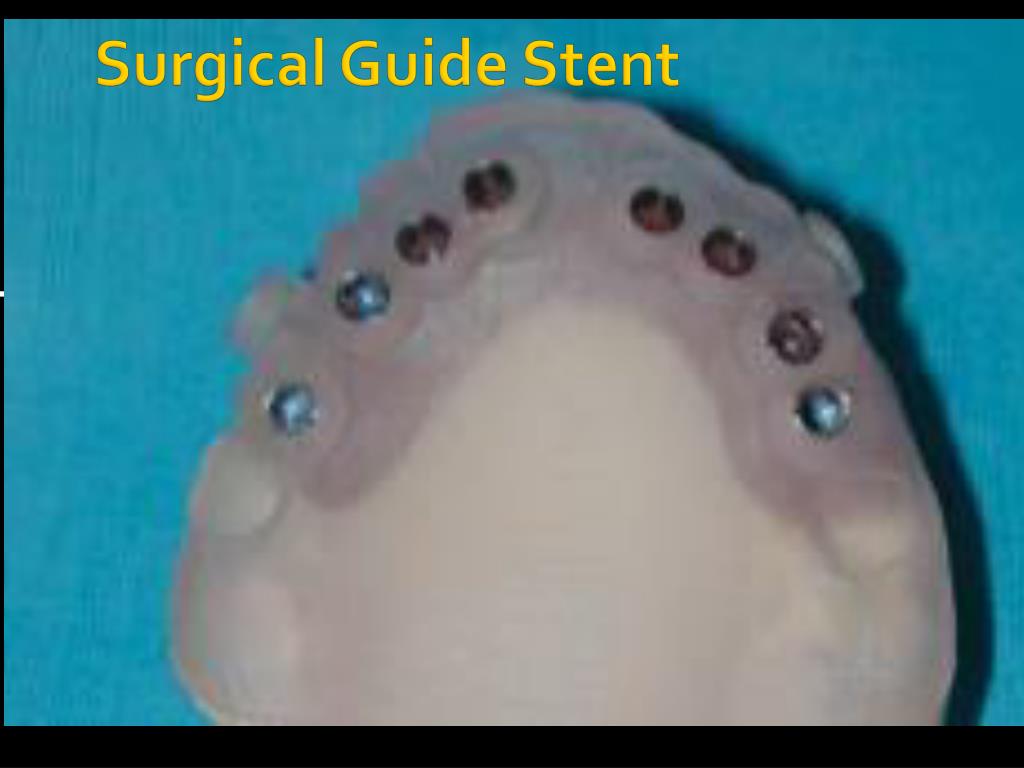
Not all surgical guides are created equal, and the type you use affects how you code the procedure. Static guides are the most common in oral surgery. They're fabricated based on CBCT scans and treatment planning software, then used during surgery to direct implant placement. These typically get absorbed into the main surgical code unless there's special documentation about custom manufacturing. I've seen practices successfully bill for custom guide fabrication under D6057 when they can document that it's a patient-specific device made outside the practice, but that's a narrow path and requires specific records. Dynamic navigation systems present a different coding scenario. These are real-time guidance technologies that don't rely on physical guides at all. They fall under a completely different set of codes and requirements, and insurance carriers still haven't standardized how to handle them. In my experience, most carriers treat dynamic navigation as experimental or investigational, so unless you have prior authorization documented, you're usually eating the cost of that technology or passing it through as an out-of-pocket charge. Soft tissue management guides are another category that people misunderstand. These aren't for implant placement but for tissue flap design and retraction during complex surgical procedures. They rarely get coded separately and are almost always considered part of the underlying surgical service. I worked with one surgeon who tried billing these under a new preventive surgery code, and the carrier rejected it outright because soft tissue management is inherently part of the surgical procedure regardless of whether a guide was used.
Documentation Requirements That Actually Matter
Proper documentation is where most surgical coding goes wrong. You need to record the indication for using a surgical guide, the type of guide (static, dynamic, or other), and how it affected the surgical plan. When I audited claims for a multi-provider group, roughly 40 percent of surgical guide documentation was insufficient for insurance review. The specific elements insurers look for include radiographic evidence of why a guide was necessary, the surgical site preparation details, and confirmation that the guide was used during the actual procedure rather than just planned. One detail that catches people off guard is the difference between a diagnostic setup and an actual surgical guide. A virtual surgical plan created in software doesn't qualify as a surgical guide for billing purposes. The guide has to be a physical or navigational device used during surgery. I had a case where a carrier demanded additional records because we only had digital planning documentation without evidence of physical guide utilization, and it took three weeks and two follow-up communications to resolve. The surgical report needs to be contemporaneous. Retrospective documentation added days or weeks later often raises red flags during peer review. I recommend documenting immediately after the procedure while the details are fresh, including measurements, guide designation numbers, and any deviations from the planned surgical path. These specifics become critical if the claim faces scrutiny down the line.
Get the Full Details
Common Coding Mistakes I See Repeatedly
Bundling errors are by far the most frequent problem. Many providers try to bill surgical guide fabrication separately from the implant or surgical procedure, but most ADA codes for implants already include the surgical component unless specifically documented otherwise. The exception is when you have a truly custom manufactured guide that requires significant additional laboratory work beyond standard practice. In those cases, D6057 might apply, but you need to document the custom manufacturing process and why standard guides weren't suitable. Another common issue is mismatching the code to the actual procedure performed. I reviewed a claim where the provider used an implant placement code but the surgical report described a bone graft with guided bone regeneration. The codes didn't match the documented procedure, and the claim was denied despite otherwise complete documentation. Always verify that the code accurately reflects what was done, not what was planned or what the guide was intended for. Prior authorization problems also plague surgical guide coding, especially for newer technologies. Some carriers require pre-approval for custom surgical guides or dynamic navigation systems, and proceeding without authorization can result in automatic denial regardless of clinical necessity. I keep a running list of carrier-specific requirements, and it changes regularly enough that I check before every procedure involving advanced guidance technology.
Practical Workarounds From Experience
When you encounter coding ambiguity with surgical guides, the best approach is often to provide additional clinical documentation rather than trying to find a code that fits. I've successfully resolved several disputed claims by submitting operative photographs showing guide placement, CBCT images demonstrating the relationship between guide and anatomy, and detailed notes explaining why the guide was clinically necessary rather than elective. This level of documentation takes time but pays off when carriers otherwise would deny coverage. For situations where surgical guides clearly add significant value beyond standard practice, consider having patients sign advanced benefit verifications before the procedure. This establishes that the patient understands the guide is being used and may affect their financial responsibility. It's not a perfect solution, but it reduces surprise bills and gives you something to reference if the carrier questions the clinical necessity later. One workaround I developed after dealing with persistent coding confusion is maintaining a separate charge capture log for surgical guide-related supplies and laboratory fees. Even when you can't bill the guide itself as a procedure, the associated costs might be recoverable through supply codes or laboratory service codes depending on how your payer contracts are structured. This system requires discipline to maintain but has recovered enough revenue to justify the administrative overhead.
When Surgical Guide Coding Completely Fails
There are scenarios where surgical guide coding doesn't work at all, and it's important to recognize these before investing time in claims that will be denied. Experimental or investigational technologies frequently fall into this category. Dynamic navigation, AI-assisted planning software that generates real-time guidance, and some proprietary guide systems are still classified as experimental by certain carriers. If your patient's plan excludes experimental procedures, no amount of documentation will change the outcome. Another situation where coding fails is when the surgical guide isn't actually used as planned. I encountered a case where the surgeon ordered a custom guide but abandoned it intraoperatively due to unforeseen anatomical variations. The claim was denied because the guide was paid for but never utilized, and we had no documentation explaining the change in surgical approach. This is a harsh lesson: if you use a guide, document its use. If you don't use it, document why and what you did instead. Medicare and some government programs also have restrictive policies around surgical guides that private carriers don't enforce. These programs often consider guides bundled into the surgical package by definition, regardless of clinical complexity or customization. If you're working with these payers, managing expectations about reimbursement is essential, and you should communicate this to patients during the treatment planning conversation.
Alternative Approaches When Standard Coding Doesn't Apply
When surgical guide coding hits a wall, some providers turn to unlisted procedure codes as a fallback. This is a double-edged sword. On one hand, an unlisted code allows you to submit a claim that would otherwise have no submission path. On the other hand, it triggers additional review requirements and doesn't guarantee payment. I've used unlisted codes successfully for novel guide applications, but each one required extensive supporting documentation and often multiple appeals. Another alternative is seeking out medical insurance rather than dental insurance for surgical guides used in maxillofacial or reconstructive contexts. When implants are part of trauma reconstruction, cancer surgery recovery, or congenital defect correction, the surgical guide might qualify as a medical device rather than a dental component. This shift in payer can make a significant difference in coverage, but it requires the underlying procedure to meet medical necessity criteria rather than purely dental indications. Some practices develop contractual agreements with specific carriers that establish predetermined rates for custom surgical guide services. These arrangements bypass the standard coding uncertainty but require negotiation and volume commitments. I know several mid-size oral surgery groups that have secured these contracts, and while they're not accessible to everyone, they represent a stable long-term solution for practices that perform high volumes of guided surgical procedures.
The Reality of Staying Current
ADA coding guidelines change periodically, and surgical guide-related policies shift more frequently than most other dental coding areas. I review updates quarterly and maintain notes on carrier-specific interpretations that differ from the official guidelines. The official ADA CDTC commentary doesn't always reflect how carriers actually apply the codes in practice, and relying solely on published guidelines can lead to preventable denials. Professional organizations like the AAOMS provide coding resources and advocacy for surgical procedures, including guidance on advanced technologies. Joining these organizations and participating in coding workshops has been valuable for understanding emerging trends and staying ahead of documentation requirements. The investment in continuing education pays off when you encounter edge cases that generalist coders might mishandle. Ultimately, surgical guide coding requires attention to clinical detail, willingness to document thoroughly, and understanding that the coding system doesn't always fit neatly onto new technologies. The approaches I've described come from years of dealing with denials, appeals, and carrier communications. They represent practical solutions rather than theoretical ideals, and they've proven effective in the actual workflow of an oral surgery practice.