What Add Back Therapy Actually Does
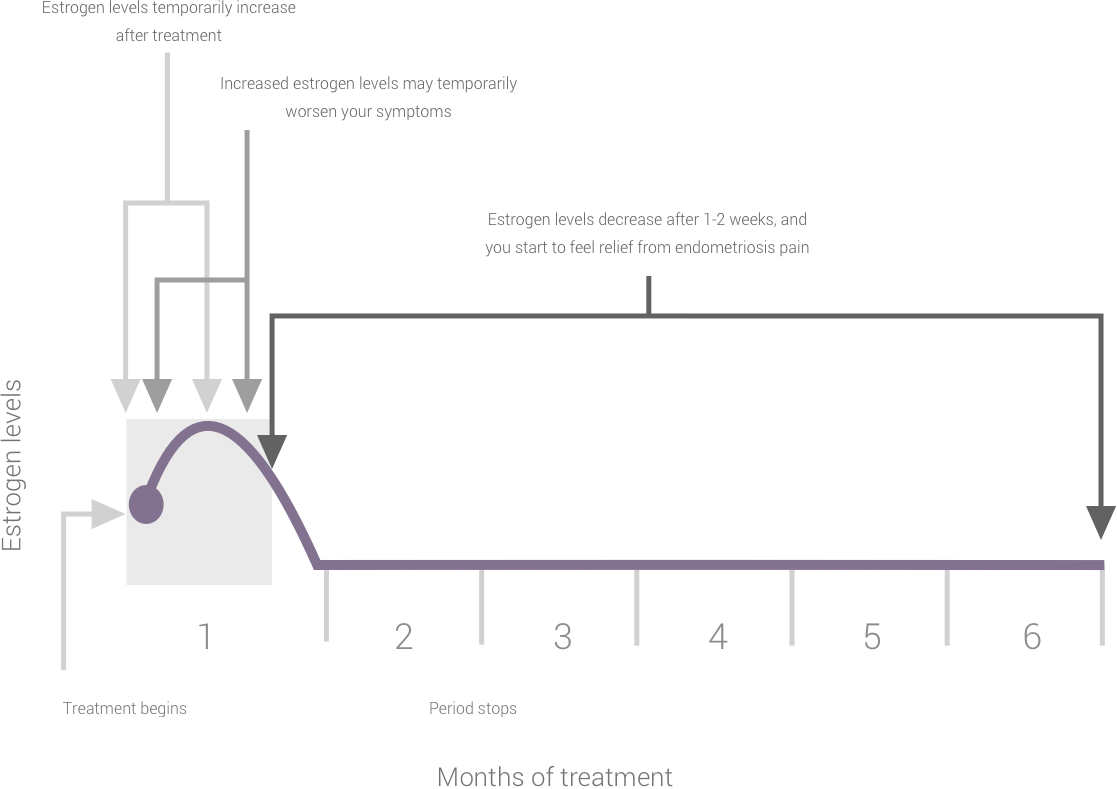
Lupron suppresses your pituitary gland. That drops estrogen down to menopausal levels, which is the whole point during IVF or when treating endometriosis. But sticking with near-zero estrogen for months makes most people miserable. Add Back Therapy For Lupron exists to keep you functional without undoing the therapeutic suppression. Here is the mechanism. The drug works at the pituitary level by downregulating GnRH receptors. Add-back hormones bypass the pituitary entirely. They act peripherally, providing relief from hypoestrogenic symptoms while the Lupron does its job upstream. You are not canceling out the treatment. You are treating the side effects.
Add Back Therapy For Lupron
I remember a patient who was put on leuprolide acetate for endometriosis and asked to start norethindrone 0.15 mg daily along with conjugated equine estrogens 0.625 mg. She called two weeks later saying her hot flashes were gone but she was bloated to the point where her normal pants did not fit and she had breakthrough spotting. The workaround was straightforward. We switched her to transdermal estradiol at 0.05 mg twice weekly instead of oral estrogen. The lower first-pass metabolism through the liver cut the bloating significantly, and we spaced the norethindrone dose differently. Spotting resolved within a cycle. The standard protocols I see most commonly use either norethindrone acetate at 5 mg daily or medroxyprogesterone acetate at 10 mg daily combined with transdermal estradiol patches delivering 25 to 50 micrograms per day, or oral estradiol valerate in the 1 to 2 milligram range. There is no single right answer. The choice depends on what symptom is dominating, whether the patient has a history of migraine with aura, and how sensitive their liver is to oral hormones.
When to Start and What to Watch For
Most clinicians begin add-back around two weeks after the first Lupron injection. Starting it too early can interfere with the initial suppression phase. Starting it too late means the patient suffers through a month of severe vasomotor symptoms, poor sleep, and mood changes that could have been mitigated. I typically schedule a check-in at the two-week mark and adjust based on symptom severity rather than following a rigid timeline. Bone mineral density is the real concern with prolonged Lupron use without add-back. Studies show that after six months of GnRH agonist monotherapy, patients lose approximately 3 to 5 percent bone density. Add-back therapy largely prevents this loss. The protection is not perfect. Some studies show a small residual deficit even with combined add-back, but it is far better than nothing. If your treatment plan extends beyond six months, baseline DEXA scanning is reasonable, and repeating it at the six-month mark gives you a data point rather than guessing. One counter-intuitive thing most people miss is that add-back does not reliably prevent ovarian cyst formation during Lupron stimulation cycles. I have seen patients on full add-back who still developed functional cysts because the underlying hypothalamic-pituitary axis was still showing intermittent fluctuations. Adding a brief course of a GnRH antagonist or adjusting the Lupron dose in those cases was the actual fix, not cranking up the add-back hormones.
Get the Full Details
Common Pitfalls
The most common mistake I see is using too much estrogen in the add-back. When patients complain about persistent symptoms, the instinct is to increase the dose. But pushing estradiol too high can partially reverse the therapeutic suppression you are trying to maintain. In IVF contexts, this can interfere with follicular development planning. In endometriosis treatment, it can allow residual disease to become active again. The goal is the lowest effective dose, not the maximum tolerated one. Another issue is the route of administration. Oral estrogen goes through the liver and increases sex hormone-binding globulin, which binds free estrogen and makes the dosing less predictable. Transdermal delivery avoids this. Patients on oral add-back often report more mood swings and irregular breakthrough bleeding compared to those on patches, and it is not always obvious why unless you think about the SHBG effect. Progestin-only add-back regimens can cause depression or anxiety in a subset of patients. Norethindrone is more androgenic than other progestins and some people are sensitive to that. If mood symptoms emerge after starting add-back, switching to a different progestin or adding a low-dose SSRI while maintaining the same estrogen dose can help. I have also seen patients whose libidos dropped off a cliff on progestin-heavy regimens. Lowering the progestin component and relying more on the estrogen side sometimes restored function without losing symptom control.
Practical Dosing Notes
For IVF patients, add-back is usually short-term, spanning the stimulation phase. The typical duration is four to six weeks. For endometriosis patients, add-back may continue for three to six months or longer depending on the protocol. Long-term add-back beyond six months without monitoring is where things get risky. You need periodic assessment of lipid panels, liver function, and bone density if you are going beyond the standard treatment window. Drug interactions are minimal but worth checking. Aromatase inhibitors like letrozole can interact with add-back estrogen in ways that create unpredictable hormone levels. If a patient is on both, you need closer monitoring of estradiol levels rather than relying on fixed dosing schedules. Tamoxifen also has complex interactions with progestin add-back that are not well studied. Those cases usually require specialist oversight. If add-back therapy is not an option for a particular patient, alternative approaches include using a GnRH antagonist instead of an agonist, which has a faster onset and offset and fewer long-term hypoestrogenic effects, or scheduling regular breaks in Lupron therapy with careful symptom monitoring. Neither option is universally better. They serve different clinical situations.
The bottom line is that add-back therapy is a standard part of managing Lupron treatment, but it requires individualization. The protocols are well established. The nuances are in the dosing, the route, and knowing when a patient needs a different approach entirely. Most people tolerate it well when it is started at the right time with the right combination. A minority need adjustments that take a cycle or two to get right.