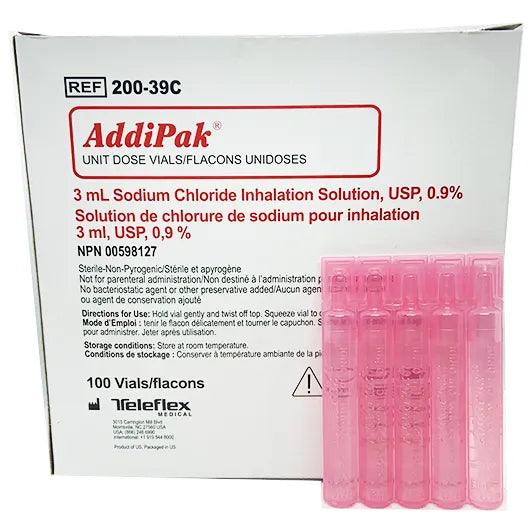
Using Addipak Sterile Saline Solution in Practice
Most people grab a bottle of normal saline and assume they know what they are doing. The reality is that the way you handle this liquid depends entirely on what you are trying to accomplish with it. I have seen too many complications from people treating all saline the same way. It is 0.9% sodium chloride in water, isotonic with blood. That means it will not draw water out of your cells or push water into them. It is the baseline fluid for IV access, wound irrigation, and diluting medications that cannot go in straight. The Addipak brand is one of the more widely available versions, especially in veterinary settings, but the chemistry does not change based on the label. The first thing most people get wrong is assuming the bottle is just "water with salt." It is not. It has a very tight pH range and osmolarity specification. Open that bottle and you are fighting contamination from day one. The preservative situation matters more than people realize.
I had a case last year where a clinic was using open multi-dose saline vials for wound flushes over several days. They thought they were being economical. Two weeks later, patients were developing localized infections that traced back to Pseudomonas growing in the bottle. The solution was not contaminated when they opened it. It became contaminated through repeated needle access and sitting at room temperature. I told them to switch to single-use packets for anything that stays open longer than a few hours. It cost more per unit but eliminated the whole problem.
How to Actually Use It Correctly
Pick the right container size for the job. A 500 milliliter bag is overkill for simple irrigation and just creates waste. A 10 milliliter syringe or single-use packet is better for small wound cleaning. The container you choose affects how long the solution stays viable once opened. When using saline for dilution, always check compatibility first. Normal saline is not compatible with everything. Some medications precipitate or degrade when mixed with sodium chloride. There are specific cases where D5W or sterile water is the required diluent instead. I spent an afternoon figuring out why a particular antibiotic batch kept crystallizing in the IV line. It was not the rate of infusion. It was the saline itself. Switching to the recommended diluent fixed it immediately. For wound irrigation, do not pour saline directly from the bottle onto an open wound. Use a syringe with an angiocath or irrigation tip to create controlled pressure. The pressure matters because you need enough force to dislodge debris without driving contaminants deeper into tissue. About 35 milliliters per kilogram of body weight is the typical volume people aim for in larger animals. Smaller patients need far less. I learned that the hard way when I watched someone flood a small wound with an entire liter bottle and then wonder why the tissue was macerated.
Get the Full Details

When using saline for IV access, the goal is to establish patency and flush the line. Do not use it as a free fluid source without calculating volume, especially in patients with cardiac or renal compromise. Even isotonic saline adds volume to the system. In a dehydrated patient it helps. In a patient with congestive heart failure, even a few hundred milliliters can push them into trouble.
Limitations and Where It Fails
Saline is not a universal solution. It has real limitations that people ignore at their own risk. The biggest one is chloride load. Large volumes of 0.9% sodium chloride deliver a significant chloride burden. Over time, this can cause a hyperchloremic metabolic acidosis. I have seen this happen in cases where dogs and humans alike received several liters of saline during prolonged procedures. The blood gas results show a dropped bicarbonate and elevated chloride. It is not dramatic in small amounts, but it adds up fast. Another limitation is that saline does not provide any nutritional value or electrolyte balance beyond sodium and chloride. If you are relying on it as a primary fluid therapy, you are missing a lot. Balanced crystalloids like lactated Ringer's are usually a better choice for resuscitation and maintenance because their electrolyte profile physiological values. Saline is also not suitable for nebulization in all cases. Some patients, particularly those with reactive airway disease, will cough or spasm when exposed to the tonicity of normal saline. Hypertonic saline at 3% or 7% is sometimes used intentionally for mucolytic effects, but that requires specific indication and monitoring. Regular saline in a nebulizer is mostly just wasting medication and irritating the airways.
Storage and Handling
Once you pierce a multi-dose container, the clock starts. Use it within the timeframe recommended by the manufacturer, which is typically 24 hours for most open systems. Discard anything that has been open longer than that, even if it looks fine. Cloudiness, discoloration, or particulate matter are obvious red flags, but the absence of visible contamination does not mean the solution is safe. Do not pre-fill syringes days in advance and store them at the bench. I know some people do this to save time between cases. It is a contamination vector. Prep what you need when you need it. If you are working in a surgical or procedural setting, treat every opened container as a potential source. Label it with the time and date when you opened it. Most compliance audits only require this, but it also keeps you honest about when something should be thrown away.

Common Mistakes to Avoid
People regularly use saline when they should be using something else. Cleaning a dry, crusted wound with saline alone does not remove debris effectively. You need mechanical action, which means a syringe and irrigation technique, not just pouring fluid over the area. Saline softens crusts but does not substitute for physical debridement. Another mistake is assuming that because saline is sterile in the bottle, it is safe for any injection. It is not meant for intravitreal or intrathecal use unless specifically formulated and approved for those routes. The route of administration changes everything about what the solution needs to meet pharmacopeial standards for. Do not mix medications in the same syringe as saline and then draw up another drug. Cross-contamination between syringes is how you introduce organisms or incompatible compounds into patients. Draw up each medication separately and flush the line between them if you are running multiple drugs through the same IV catheter.
There is also a persistent myth that saline is the best option for cleaning eyes. It is not irritating, which is true, but it is also not isotonic with tear film. Balanced ophthalmic solutions exist for a reason. For a one-time flush it is fine. For repeated use, it is not ideal.
When to Look Elsewhere
If you need prolonged fluid therapy, balanced crystalloids are generally superior. If you are dealing with significant dehydration and electrolyte abnormalities, normal saline alone will not correct the underlying problem. If you are irrigating a heavily contaminated wound, you may need additional antiseptic agents or surgical debridement rather than relying on saline by itself. And if you are using it for nebulization in a patient with airway reactivity, consider a different approach entirely. Addipak Sterile Saline Solution is a reliable product when used correctly. It is not a cure-all. Understanding what it does and what it does not do separates competent practice from routine mistakes. The difference between a clean case and a complicated one often comes down to whether you picked the right fluid for the right situation.



