What You're Actually Looking At
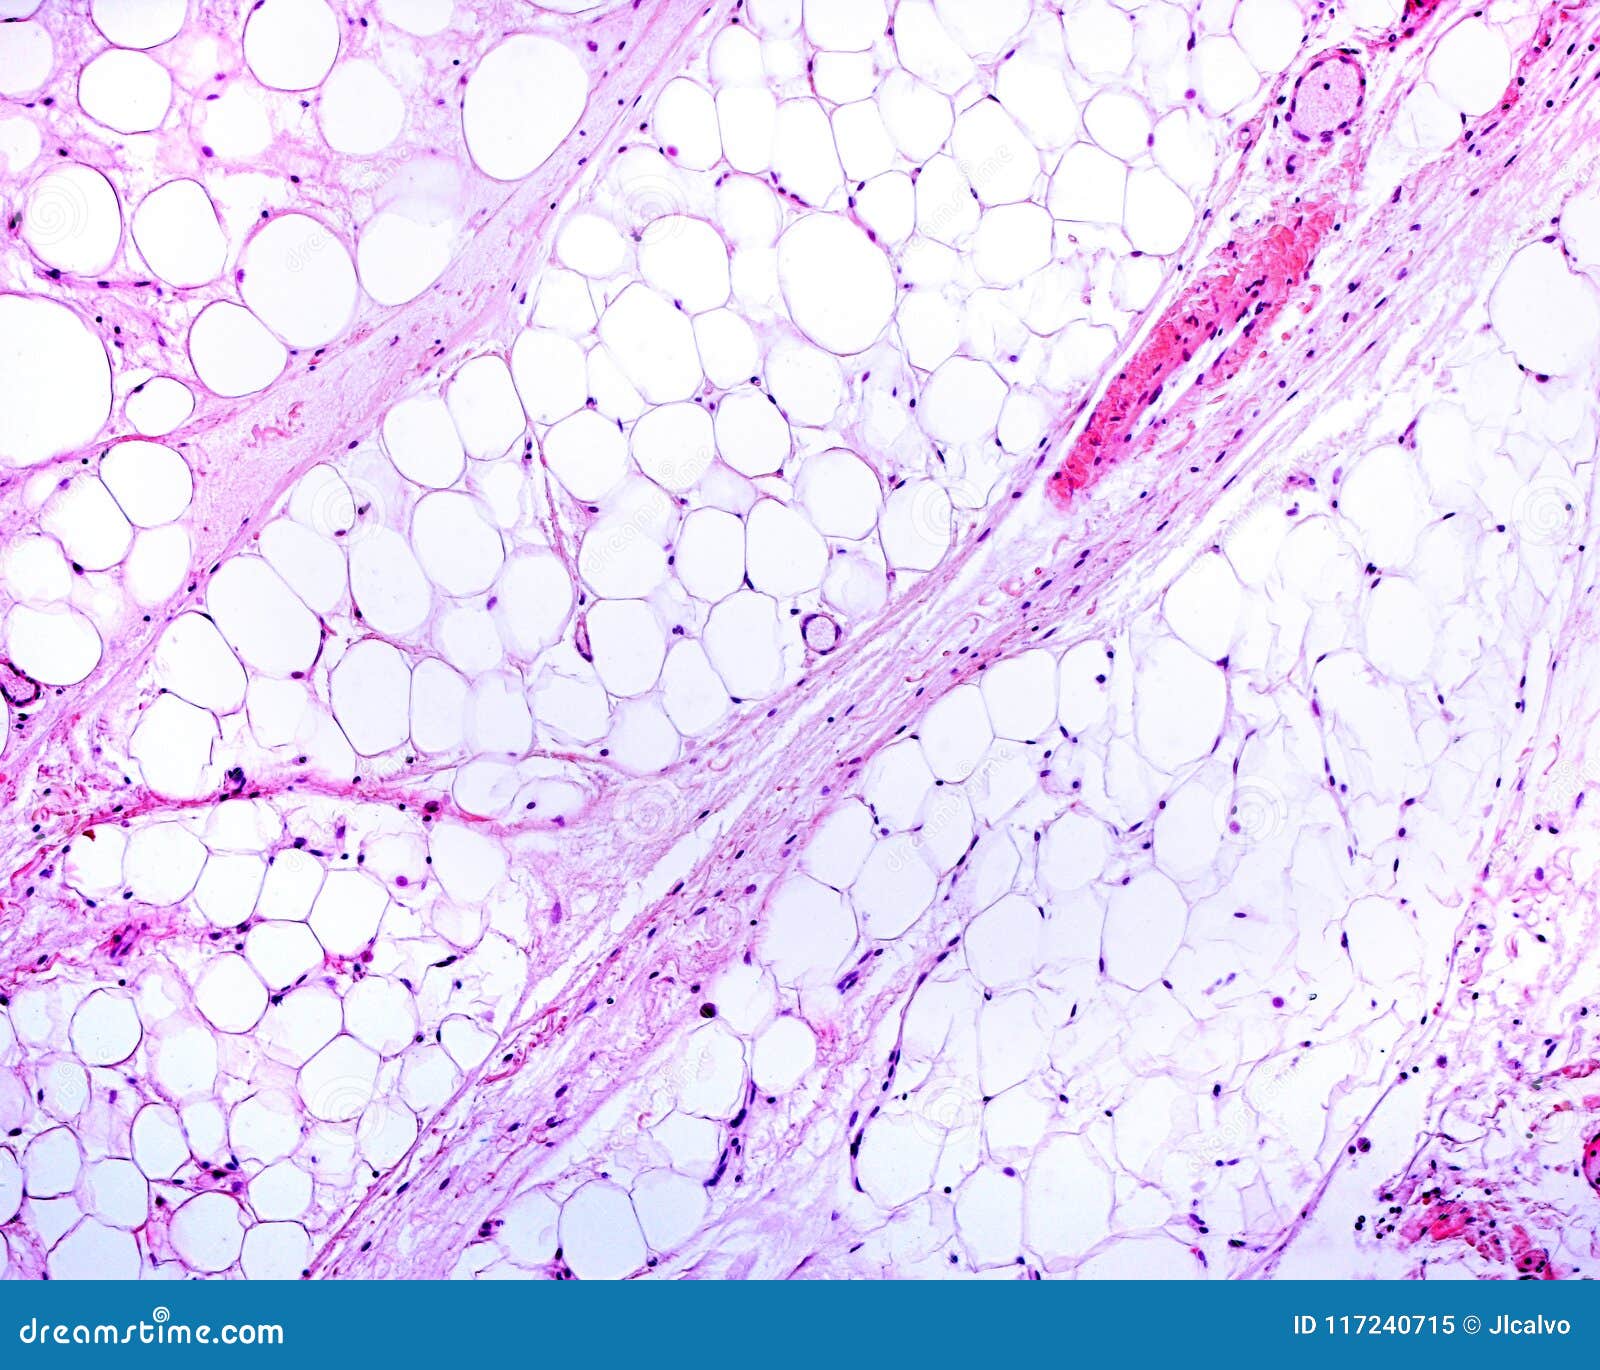
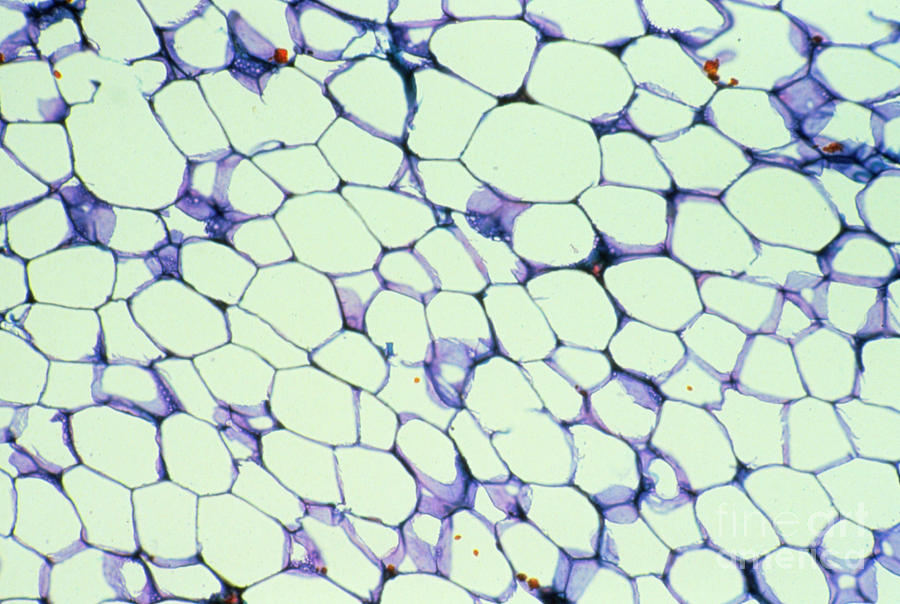
When you put a section of adipose tissue on the microscope slide and focus up, you're looking at a field that's mostly empty space surrounded by thin cell membranes. That's not an artifact. White adipose tissue is essentially a bag of lipid that gets dissolved during routine processing, leaving that characteristic signet-ring or chandelier appearance. The nucleus gets pushed to the periphery and flattens against the membrane. It looks almost dead because, for all practical purposes in a histology lab, it is. The cytoplasm is so thin you barely see it. I've spent years going over frozen sections and paraffin-embedded fat, and the first thing most people miss is that adipose tissue isn't one thing. There are at least three types that look nothing alike, and your staining protocol needs to account for that before you even cut the block.
Adipose Tissue Under Microscope: The Basics of Recognition
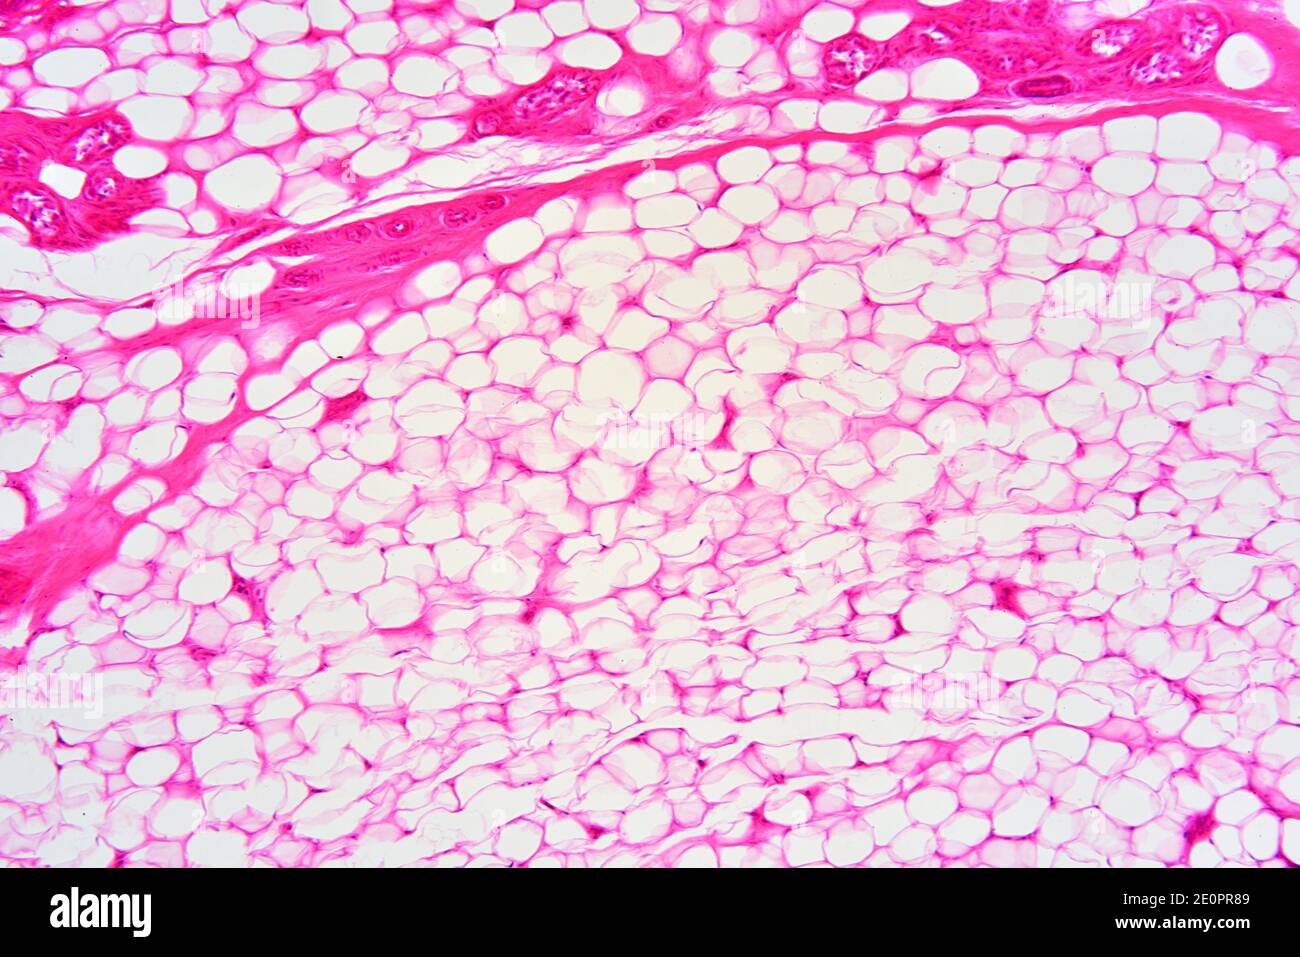
White adipose tissue (WAT) shows up as large, unilocular cells — one big lipid droplet per cell, roughly 50 to 150 micrometers in diameter. Under H&E, the lipid is cleared during xylene and alcohol dehydration, so the cells appear as empty circles with a thin rim of pink cytoplasm and a flattened purple nucleus pressed against the edge. In a well-prepared section, they look like a honeycomb or a pack of bubbles. Brown adipose tissue (BAT) is completely different. Multilocular cells, smaller lipid droplets scattered throughout the cytoplasm, and a central round nucleus that stays in the middle instead of getting shoved to the side. The cytoplasm stains deeply basophilic because of all those mitochondria. It's richly vascularized too, so you'll see capillaries woven between the cells. Found mainly in newborns and certain adult depots in humans — supraclavicular, paravertebral, around the kidneys. Beige or brite fat sits somewhere in between. It's not a separate anatomical structure so much as a functional state that white fat can adopt under certain conditions like chronic cold exposure. The cells are smaller than typical WAT, have multiple droplets, and can stain more like brown fat depending on how activated they are. This distinction matters clinically but often gets glossed over in basic pathology courses.
Here's where things get messy in practice. Processing adipose tissue for paraffin embedding is one of the most finicky things in a routine histology lab. The lipid doesn't stick around through standard alcohol dehydration and xylene clearing unless you control the schedule carefully. I've seen blocks come back looking like Swiss cheese — not because of the tissue, but because the xylene pulled the lipid clean out during an extended clearing step. One lab I worked with was getting sections that looked like abstract art. Just blank circles with nothing inside. They'd been clearing for 45 minutes in xylene. Twenty minutes was the sweet spot for that particular processing schedule.
Get the Full Details

The Staining Problem Nobody Warns You About
Osmium tetroxide is the only reliable way to actually visualize lipid in situ without losing it to solvents. It fixes and stains fat black. But it's also a potent toxic hazard that requires a fume hood and proper PPE, and it darkens everything — not just the lipid. Collagen, connective tissue, the works. So you're making a trade-off between artifact-free lipid visualization and dealing with a non-specific black background that can make nuclei hard to read. For routine diagnosis, H&E is usually fine because pathologists don't actually need to see the lipid inside the cell. The morphology is diagnostic from the empty-space-with-peripheral-nucleus pattern alone. Osmium staining becomes necessary when you're doing research on lipid metabolism, doing quantitative fat measurements, or studying conditions like lipodystrophy where you need to document actual lipid content rather than relying on the indirect signet-ring appearance. I ran into a case last year where a pathology resident was convinced a section showed abnormal microvesicular steatosis in subcutaneous fat. Under 40x, it looked like the cells were full of tiny droplets — classic for brown fat or beige recruitment. But the H&E staining had been slightly off, over-differentiated in alcohol, and the cell membranes were collapsing inward during mounting. The resident thought it was a pathological finding. I re-processed a duplicate block with shortened dehydration times and used a slower xylene clear, and the "microvesicles" disappeared. The cells were just normal white adipocytes that had shrunk unevenly because the alcohol grades had been contaminated with water over time. Takes about ten minutes to run a quick water test on your alcohol — add anhydrous sodium sulfate to a small sample, let it sit for a minute, and if it clumps, your ethanol is too wet for proper dehydration.
Frozen Sections vs. Paraffin: When to Use Which
Frozen sections preserve lipid naturally. You cut fresh tissue, mount it, fix briefly in formalin or freeze in OCT, and your lipid droplets stay exactly where they are. The downside is that frozen sections are thicker, less crisp, and more prone to ice crystal artifacts. Ice crystals create fake vacuoles that look pathological but aren't. You'll see them as irregular, angular clear spaces that cut across multiple cells — WAT cells are round and uniform, ice crystals are jagged and random. Paraffin sections give you cleaner morphology overall but lose the lipid unless you use oil red O or a similar fat-soluble dye on frozen alternatives. Oil red O is the standard for staining neutral lipids in frozen sections. It requires isopropanol to differentiate, and that differentiation step is where most people screw it up. Stain too long and you lose the lipid signal. Stain too short and you get diffuse red background across the whole section. The practical rule is: if you need architecture detail — looking for inflammation, fibrosis, tumor margins within fat — go paraffin. If you need to show that lipid is actually present and quantify it, frozen plus Oil Red O. Combine both on serial sections when you're writing a paper or presenting a difficult case. It's an extra day of work but eliminates half the questions reviewers will ask.
A Counter-Intuitive Thing About Adipose Tissue Morphology
Most people assume that enlarged adipocytes always mean obesity. That's wrong in a meaningful number of cases. In lipodystrophy, the adipocytes that remain can actually be larger than normal because they're trying to compensate for the loss of neighboring fat cells. The tissue looks hypocellular with massive individual cells, which superficially resembles hypertrophic obesity under low power. You need to zoom in and look at the stromal vascular fraction — the space between cells. In true obesity, there's more connective tissue and more cells. In lipodystrophy, the interstitial space is relatively empty and the remaining adipocytes are stretched thin over large lipid volumes. Another thing that trips people up: adipose tissue undergoes rimming fibrosis in metabolic disease. Early in the process, you see collagen deposition around individual adipocytes — pericellular fibrosis. It's subtle. You need trichrome or picrosirius red to pick it up clearly. H&E will just show slightly more pink between cells. By the time you see band-like fibrosis separating lobules, the disease is already established. I've seen biopsy reports that call a section "normal adipose tissue" when pericellular fibrosis was present but invisible on H&E. If you're evaluating this tissue from a metabolic or endocrine context, ask for a trichrome stain. It takes two extra minutes on the autostainer and adds information that changes the interpretation significantly.

Common Pitfalls That Waste Your Time
Crust artifact is the biggest one. When you're cutting paraffin sections of pure adipose tissue, the block surface can dry out at the edges during microtomy and you get hard, torn material that won't flatten in the water bath. It looks like a burn injury on the section — dark, wrinkled, useless. The fix is straightforward: keep your block cold, cut at a slower rate, and float sections immediately. Don't let them sit on the bench. I use a brush to transfer sections directly from the water bath to slides rather than letting them air-dry first. Cuts the artifact rate from roughly one in four sections to maybe one in twelve. Another issue is fat necrosis mimicking pathology. Trauma, pancreatitis, surgery — any of these can cause enzymatic or mechanical fat necrosis, and the resulting saponification creates ghost cells with shadowy outlines and calcium deposits. Under H&E, this looks alarming. You can see calcification as deep blue-purple granular deposits. Clients and junior staff often flag this as "malignant" or "inflammatory" on first glance. It's not. Fat necrosis has a very specific timeline — acute necrosis shows inflammatory infiltrate, later stages show foamy macrophages and multinucleated giant cells, and chronic lesions become fibrotic with dystrophic calcification. If you see a mix of these stages in one section, it's almost certainly fat necrosis rather than a neoplastic process. Tissue folding during sectioning is especially common with fat because it's soft and compressible. You'll get wrinkles that look like folds in the paraffin rather than in the tissue. The trick is to cut thinner — 4 micrometers instead of the usual 5 — and use a sharper blade. A dull scalpel smears fat tissue. A new blade at the right angle produces clean cuts. I replace my blade after every eight to ten blocks when cutting primarily adipose specimens. It's more expensive but saves far more time in not having to re-cut failed sections.
What the Staining Protocol Actually Needs
For a standard H&E on paraffin-embedded adipose tissue, your critical parameters are dehydration time and clearing time. Ethanol should be 70 percent for 30 minutes, 95 percent for 20 minutes, two changes of 100 percent for 15 minutes each. Xylene clearing: 15 to 20 minutes, two changes. Over-clearing is the most common mistake. If your processor runs a standard cycle and you're seeing excessive lipid loss, bump the xylene time down and the 100 percent ethanol stays the same. The alcohol dehydrates; the xylene makes the tissue transparent and compatible with paraffin infiltration. You need less xylene than people think. Paraffin infiltration at 58 to 60 degrees Celsius for 30 to 45 minutes is adequate. Going longer doesn't improve section quality and can actually make the tissue more brittle, which increases cracking during microtomy. Embedding temperature matters too — if your embedding station is too hot, the fat softens and cells collapse. Keep it at the lowest temperature that still allows good adhesion to the cassette, usually around 4 to 5 degrees below the paraffin melt point.
Electron Microscopy Adds a Different Layer
If you need ultrastructural detail — the actual lipid droplet membrane, the mitochondrial architecture in brown fat, the caveolae density on the plasma membrane — light microscopy won't cut it. EM reveals that white adipocytes have extensive caveolae covering their surface, which relates to insulin signaling and lipid exchange. Brown fat mitochondria show densely packed cristae because of the high oxidative capacity needed for thermogenesis. These details matter for research but add significant cost and time. Sample fixation in glutaraldehyde, osmium postfixation, resin embedding, ultrathin sectioning — the whole process takes about five days from fresh tissue to viewable section. Not something you do on a routine diagnostic turn-around. I should note that electron microscopy has a real limitation here: adipose tissue is extremely fragile during processing. The lipid solvent extraction in EM prep (usually acetone or ethanol series) can cause droplet coalescence and artifact if the fixation isn't thorough. If your glutaraldehyde fixation is less than 90 minutes or the concentration is below 2.5 percent, you'll see droplet rupture artifacts that look like the cell lost its structural integrity. It's a processing artifact, not a biological one. Proper fixation anchors the lipid droplet membrane before any solvent touchdown.
Practical Takeaway
Adipose tissue under the microscope is deceptively simple. The morphology is straightforward once you know what to look for, but the preparation variables are numerous and unforgiving. The single highest-impact adjustment most labs can make is reducing xylene clearing time and checking their alcohol grades regularly. Most problems trace back to over-clearing or wet alcohol, not to anything fundamentally wrong with the tissue itself. If you're evaluating pathology reports on fat, remember that the empty appearance under H&E is normal for white adipose tissue. Don't read lipid depletion into a standard stain — the lipid is gone by design, not by disease. When in doubt about a questionable finding, request a frozen section with Oil Red O or a trichrome stain on the paraffin. Two quick add-on tests that resolve more ambiguity than another round of H&E review ever will.