How This Actually Works in Practice
Most people come at this from the wrong angle. They think Advanced Correction Chiropractic Physical Therapy is just a fancy branding exercise where you slap the words together and charge more. It isn't. It's a real clinical framework that blends targeted spinal correction principles with physical therapy modalities, but the integration is where 90% of practitioners fumble it. At its core, this approach combines structural realignment work—think drop-table adjustments, flexion-distraction sequences, and specific mobilization techniques—with rehabilitative movement patterns, myofascial release, and progressive loading. The "advanced correction" part refers to using detailed biomechanical assessment to identify the primary lesion, then treating it first before layering in PT-specific strengthening and mobility work. I've seen too many clinics skip straight to the strengthening phase without establishing the structural baseline. Patients plateau because the underlying joint dysfunction was never addressed. It's like building a foundation on cracked concrete and wondering why the walls look wrong six months later.
The Assessment Phase Most People Rush
Here's where the method actually earns its keep. Before any hands-on work, you need a proper orthopedic and neurological screening, followed by postural analysis and segmental motion testing. Palpation alone won't cut it at the advanced level. You need to know which segments are hypomobile versus hypermobile, and in what plane of motion. I worked a case last year where a patient had been coming in for neck pain for eight months across three different practitioners. Every one of them was treating upper cervical as the primary issue. The segmental analysis showed C5-C6 on the right was the actual hypomobile joint restricting motion, and the upper cervical tension was compensatory. Once we corrected C5-C6 with a specific lateral decubitus adjustment and paired it with cervical retraction exercises, the referral pattern stopped entirely. That's the difference a proper assessment makes.
The Treatment Protocol
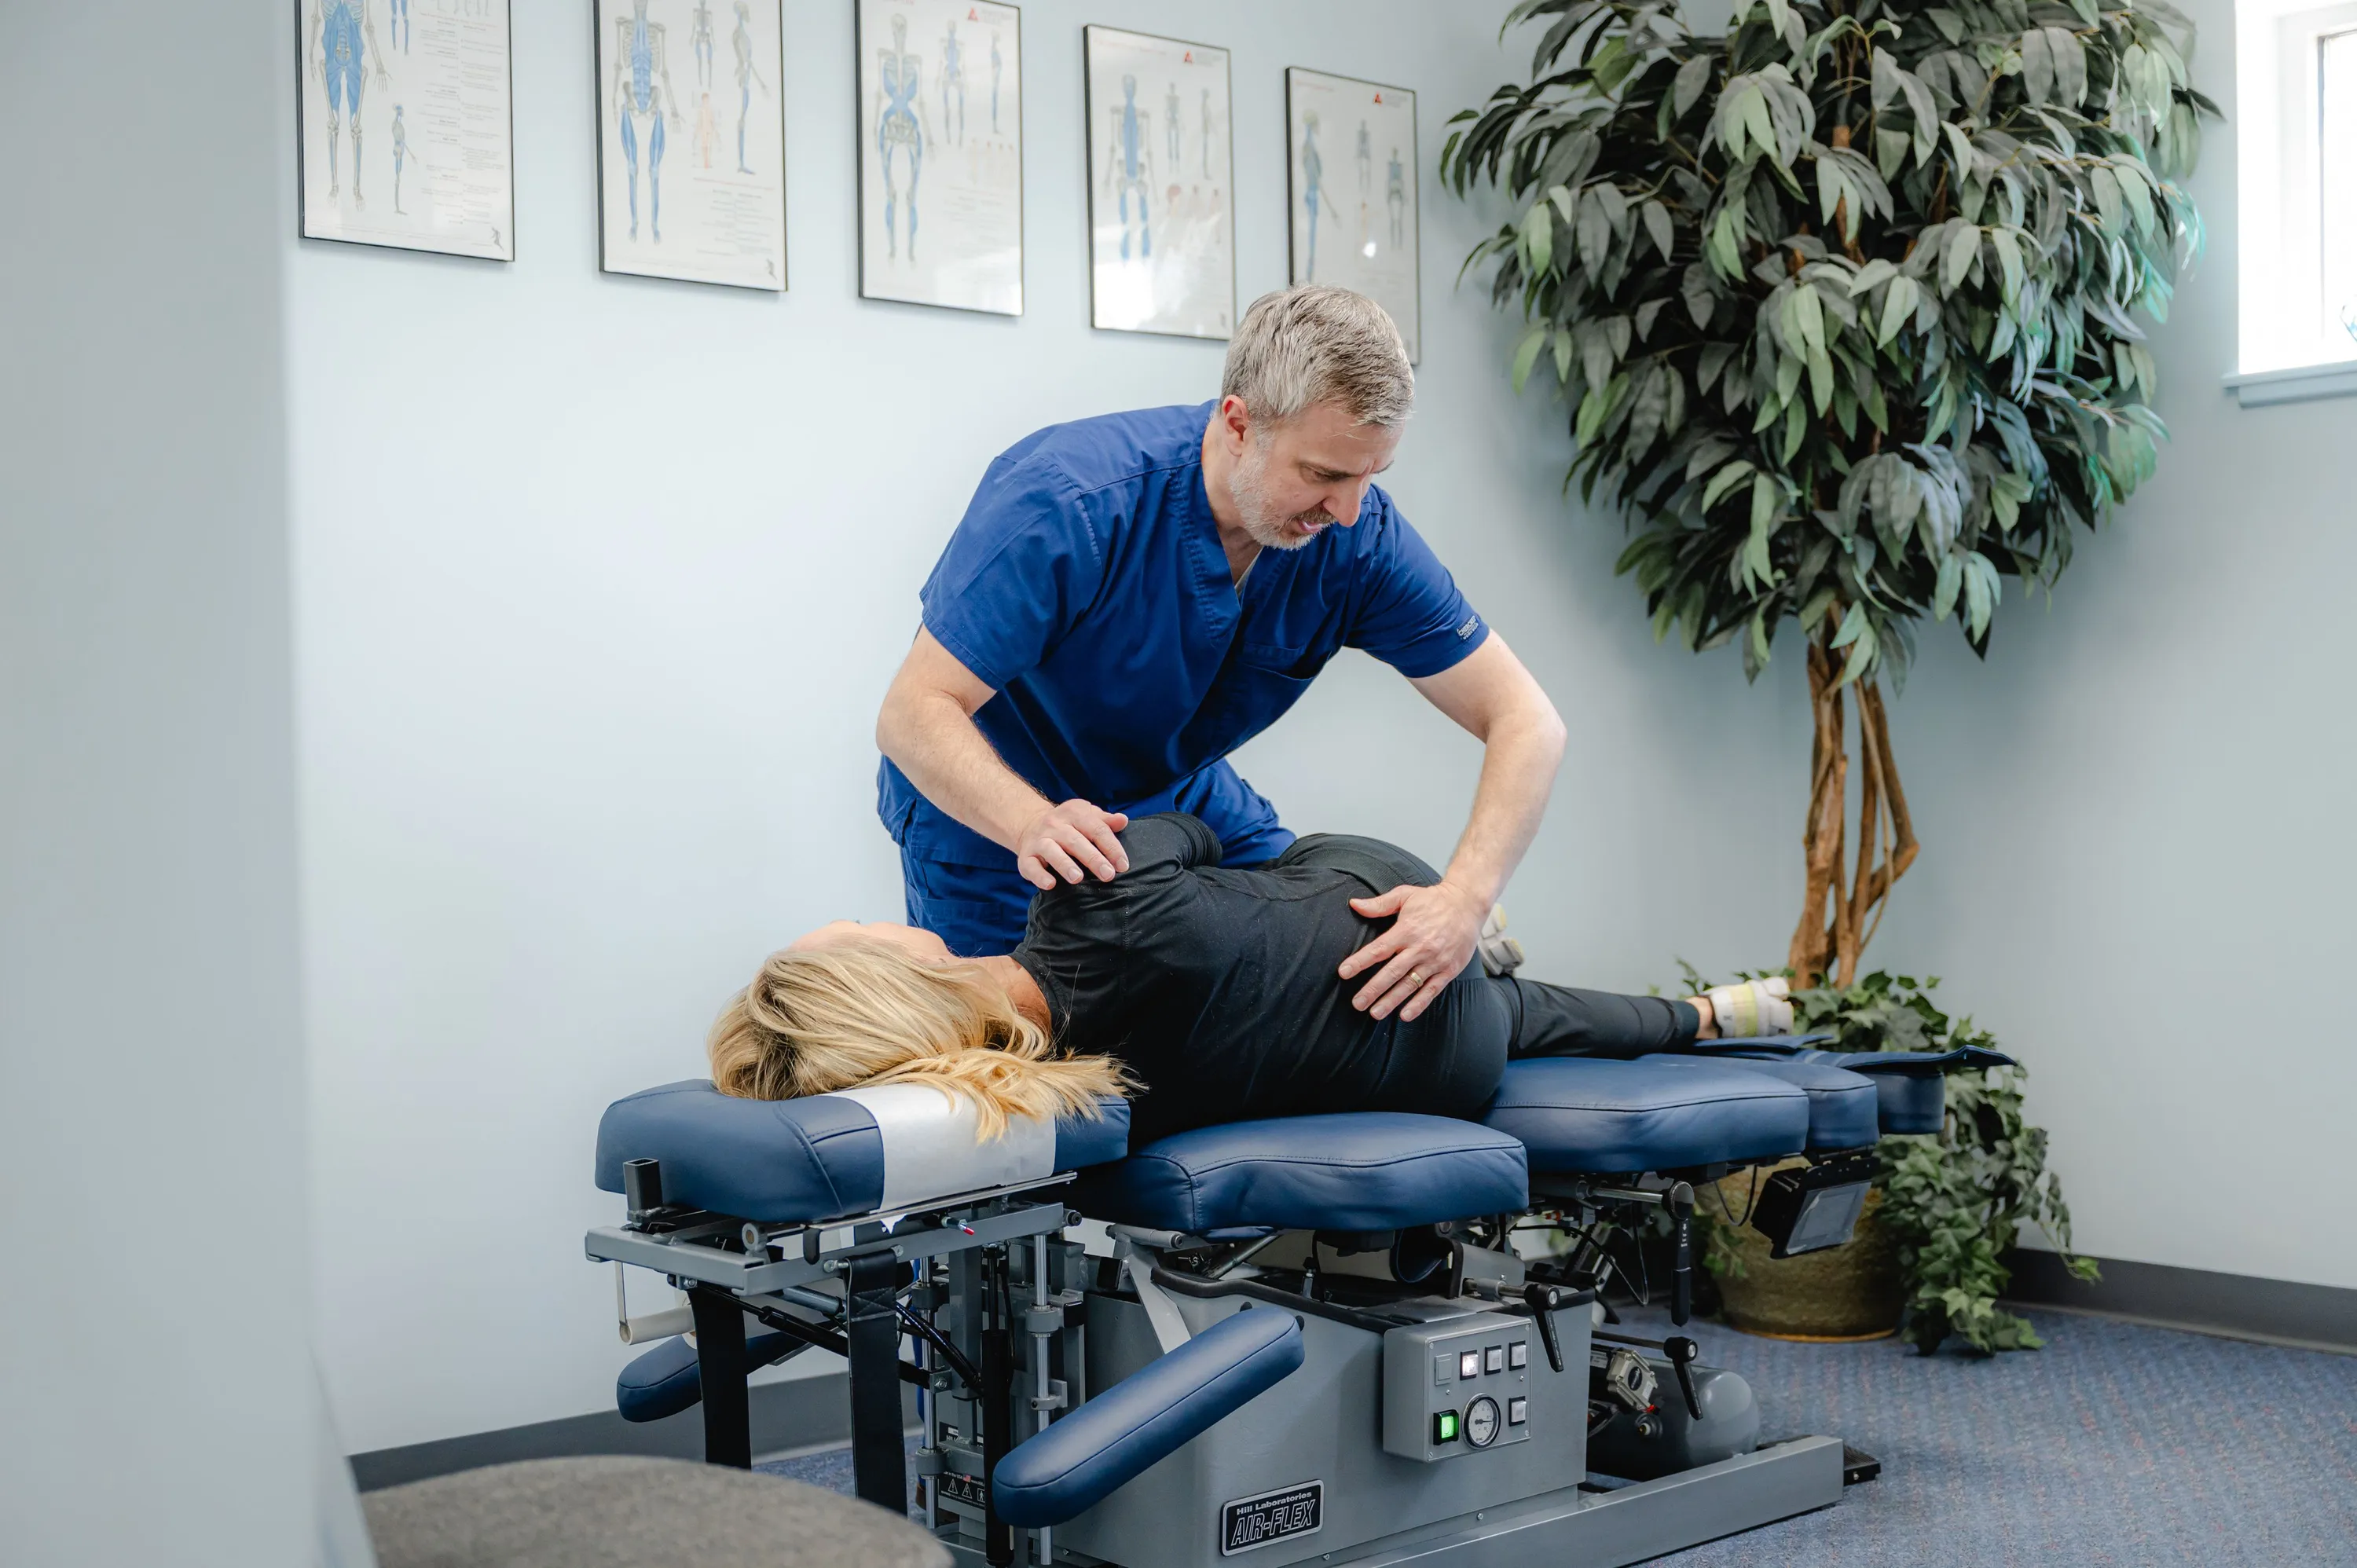
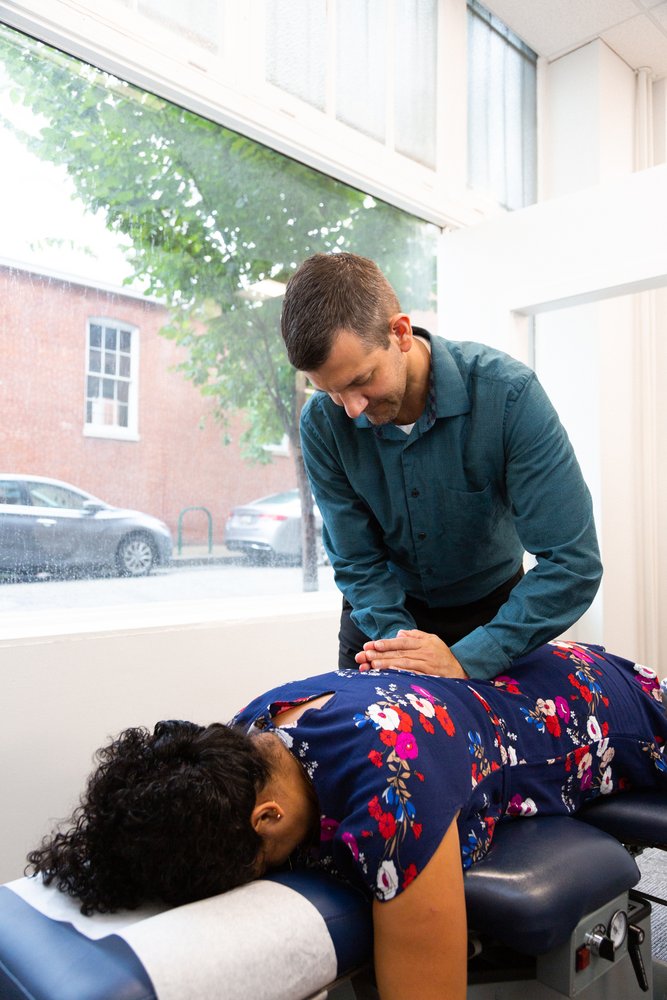
The typical session structure runs like this: First, you establish or restore segmental motion through correction techniques. This could be a diversified adjustment, an activator method application, or a specific mobilization depending on your training and the patient's presentation. The key is precision—you're targeting one or two segments, not spraying adjustments across the whole spine. Then immediately after, you move into the physical therapy component. This isn't a separate appointment. While the tissues are still primed from the correction, you introduce neuromuscular re-education exercises. Hold mechanisms, scapular stabilization work, or cervical isometrics depending on the area treated. The window between correction and activation matters. You want that segment to hold the new position while the surrounding musculature learns to support it.
Get the Full Details
From there, you progress into loaded movement patterns. Bird dogs, dead bugs, split squats, farmer carries—all tailored to the patient's specific dysfunctions. The goal is building the kind of global stability that prevents the correction from backing out within a week.
Where Advanced Correction Chiropractic Physical Therapy Falls Apart
I'm not going to pretend this approach works universally. It breaks down pretty quickly with patients who have undiagnosed pathology. Red flags like unexplained weight loss, fever, history of cancer, progressive neurological deficits—these don't get better with spinal correction and exercise. They get referred. Period. I've had two patients in the last two years who presented with seemingly routine back pain but failed to improve after four sessions. Both turned out to have sacral tumors that were missed because someone was too eager to start adjusting. You have to know when to stop and send them up the chain. Another limitation: insurance coverage. Most plans don't reimburse well for combined chiropractic-physical therapy sessions. You're often coding for either the adjustment or the therapeutic exercise, rarely both in the same visit without flagging reviews. That's a business reality most practitioners hate dealing with but can't ignore if they want to stay open. Patient compliance is the third bottleneck. The correction itself is fast—usually 10 to 15 minutes per area. But the strengthening phase requires homework. I'd estimate that 60% of patients either forget the exercises or skip them because they feel better after the adjustment and assume they're cured. They aren't. The correction holds for about 72 hours on average before muscular deconditioning starts pulling things back. The exercises close that gap.
Setting Up a Practice That Actually Uses This Model
If you're considering integrating this into your practice, here's the practical side. You'll need at minimum a drop-piece table or an activator instrument. Flexion-distraction is ideal but not mandatory. For the PT side, you need a clear exercise progression system—start with isometric holds, move to resisted patterns, then integrate functional loaded movements. Don't just pull random exercises from Pinterest. There needs to be a logical sequence tied to the corrections you're performing. Documentation is another area where people get sloppy. If you're doing both adjustments and therapeutic procedures, your notes need to reflect both separately. A single note saying "chiro PT eval" isn't going to survive an audit. Break it out: what segment was adjusted, what technique, what was the pre and post motion change, what exercises were prescribed, and how the patient tolerated it. Takes an extra three minutes per chart. Worth it. The biggest mistake I see is therapists trying to retrofit this onto their existing model without adjusting the treatment room flow. Correction work requires a specific table setup and positioning. Exercise work needs floor space and equipment. If your clinic is one cramped room with a treatment table and nothing else, you're going to struggle with throughput. I reorganized my treatment area specifically around this—adjustment zone, then a five-foot transition space, then the exercise zone with bands and light weights. Cut my average session time from 45 minutes to about 30, and patient outcomes improved because there was less friction between phases.

Quick Reference for Getting Started
If you're a chiropractor looking to add the physical therapy component, start with cervical and lumbar corrections paired with deep neck flexor endurance and prone instability exercises. Those two areas have the strongest evidence base and the highest patient volume. Don't branch out to thoracic and extremities until you've got that workflow dialed in. If you're a physical therapist considering the correction side, take a certified course in Diversified or activator technique. The hands-on component isn't something you pick up from a YouTube video. I wasted about six months trying to self-teach from online material before it clicked during a proper workshop. The adjustment mechanics matter more than the theory. Patient education materials help tremendously. Most people have no idea what a hypomobile segment is or why they need to do exercises after getting adjusted. A simple handout explaining the correction-stabilization-progression model cuts down on the repetitive questions and gets patients more invested in the exercise program.
The approach works when you respect the full sequence. Cut corners on the assessment, rush the correction, or skip the strengthening, and you'll end up with patients cycling through your door every few weeks with the same complaint. The model isn't complicated. It's just work, and not everyone wants to do the work.



