Understanding Aerospace Physiology as an Academic Path
Aerospace Physiology Degree programs don't really exist as a single standalone major at the undergraduate level. What you're actually looking at is a specialization that branches off from broader fields like biomedical engineering, exercise science, or human factors. The curriculum pulls from respiratory physiology, cardiovascular adaptation, thermoregulation under stress, and the effects of hypobaric environments on the human body. Most people encounter it either through a dedicated aerospace physiology elective sequence within an aerospace engineering program or later during residency in aerospace/flight medicine. I spent several years coordinating a human factors curriculum for a defense contractor, and one thing that consistently trips people up is that aerospace physiology isn't just about studying pilots in fighter jets. It covers civilian aviation, spaceflight, high-altitude operations, and increasingly, commercial spaceflight where the physiological parameters differ substantially from military contexts. The overlap with space medicine has grown dramatically since the early 2020s when multiple private companies started running suborbital and orbital flights.
What an Aerospace Physiology Degree Actually Covers
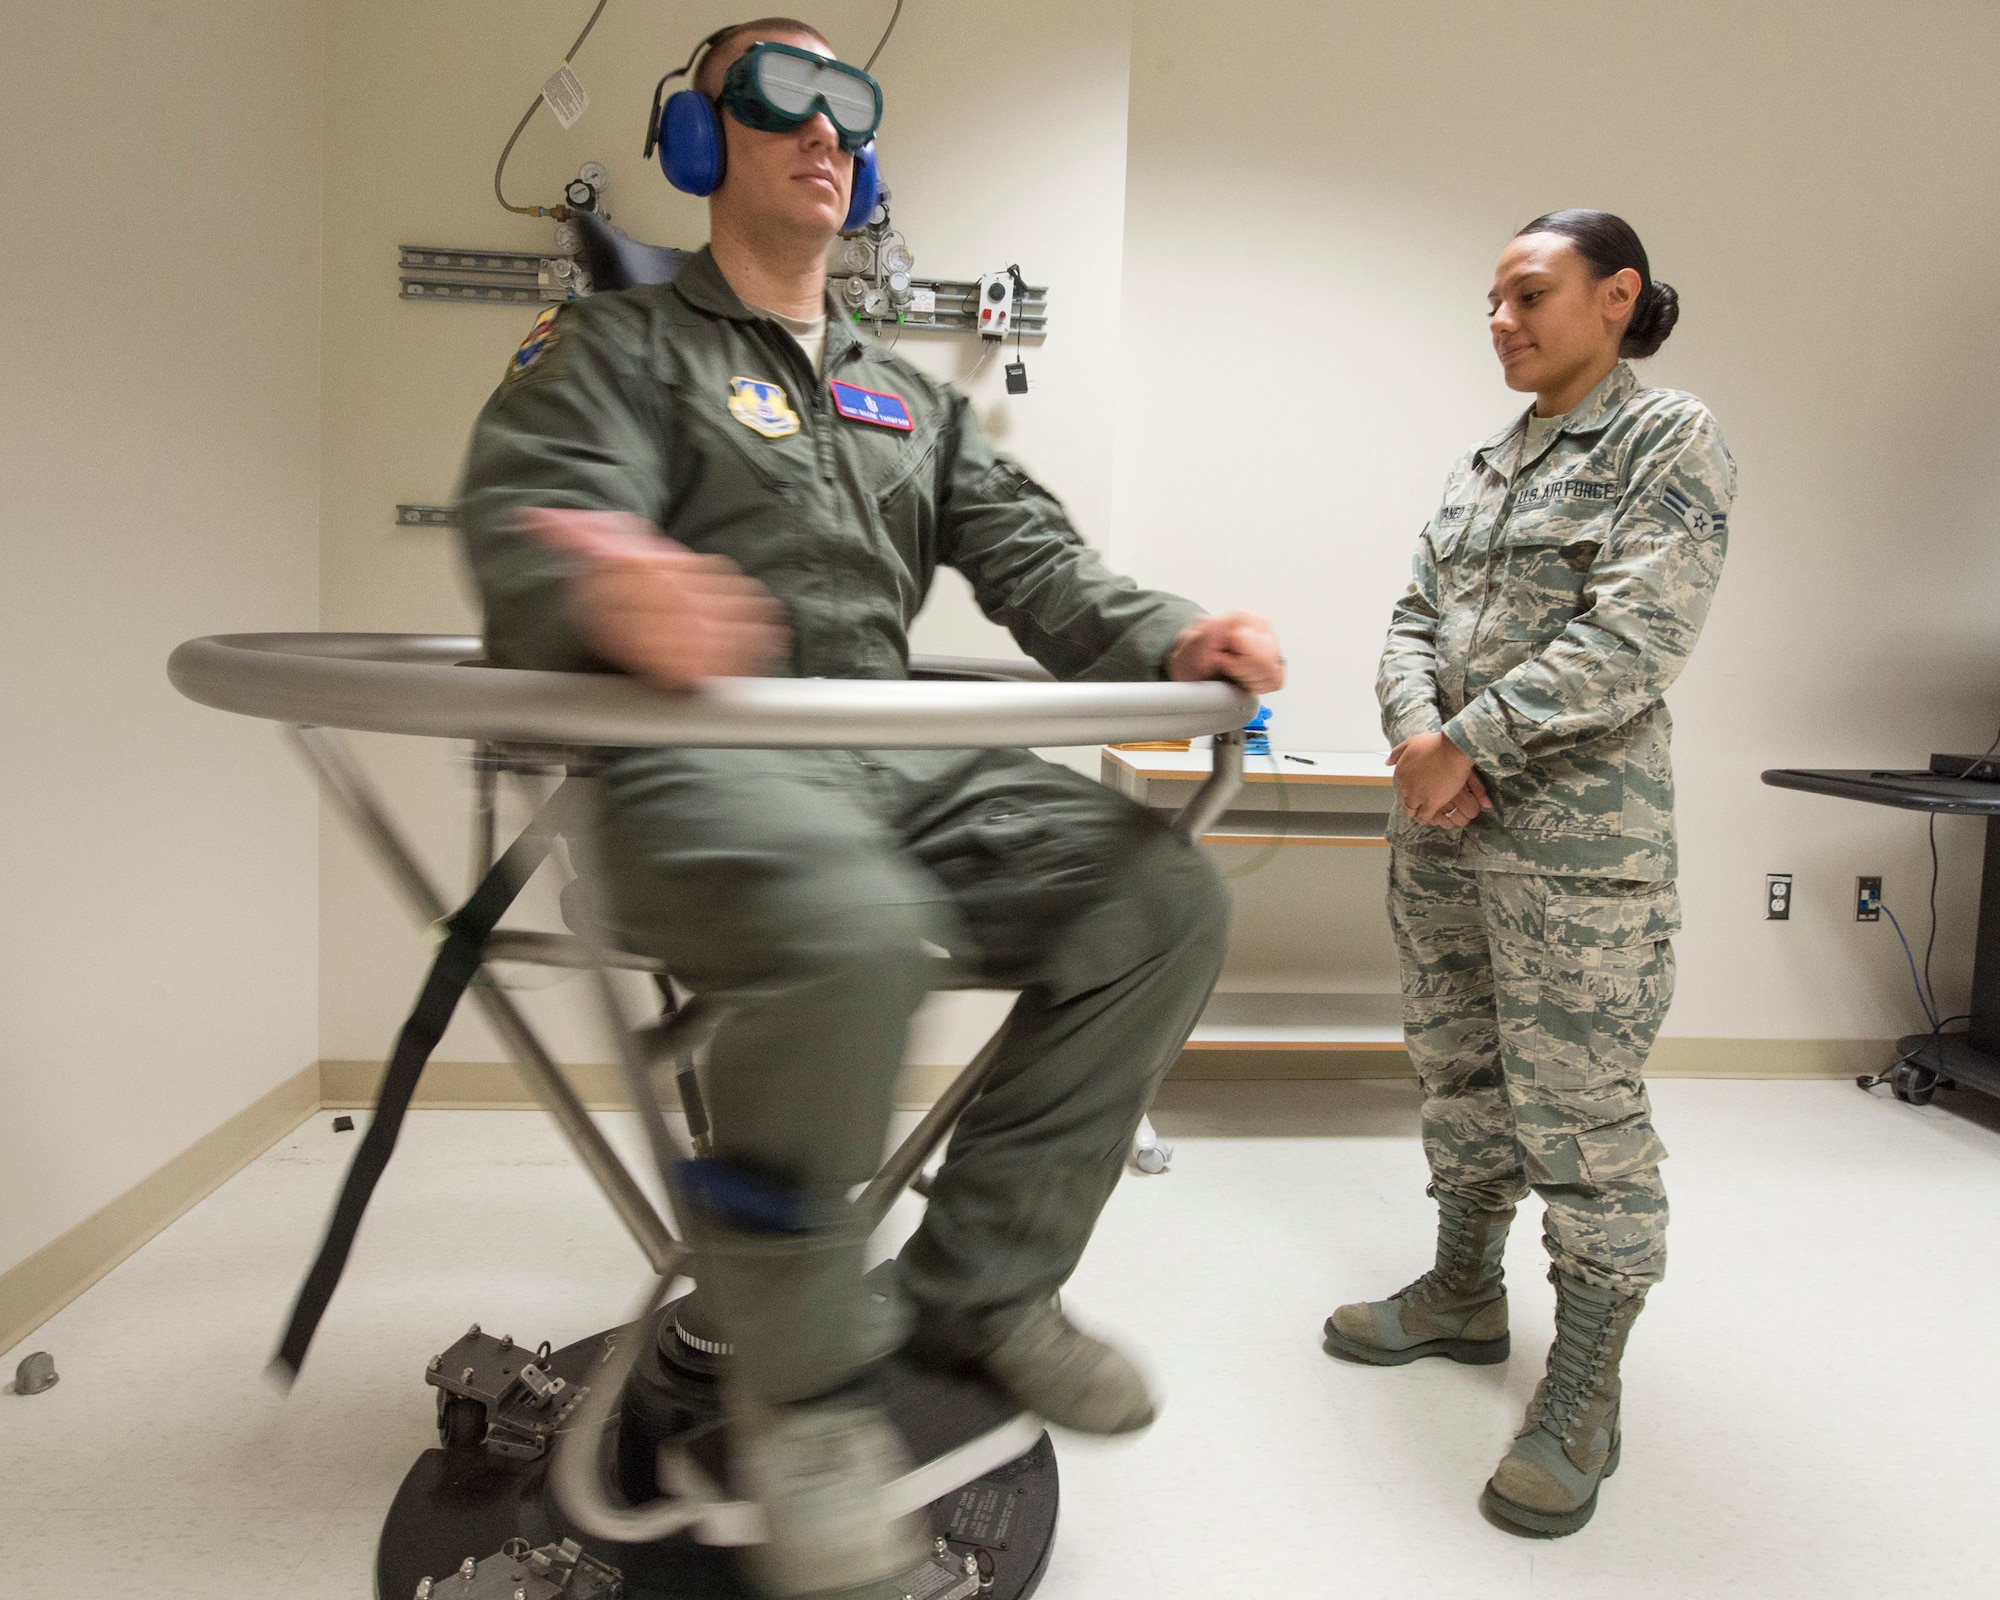
The core material hits several domains. Cardiovascular deconditioning during prolonged microgravity exposure is a major topic—bone density loss, fluid shift complications, and the orthostatic intolerance that follows re-entry. Respiratory physiology under varying partial pressures of oxygen and the mechanisms behind decompression sickness. Vestibular function and spatial disorientation, which remains one of the leading contributors to aviation accidents even with modern instrumentation. Thermal regulation in extreme environments where convection, radiation, and evaporation all behave differently than at sea level. Beyond the foundational science, you work with monitoring systems. I've calibrated and Troubleshot capnometers, pulse oximetry systems, and intraosseous pressure monitoring setups used in hyperbaric chambers. One practical issue I ran into repeatedly involved pulse oximetry readings during simulated high-altitude exposure. The devices tend to overestimate oxygen saturation below 70mmHg because of the way the light wavelengths interact with the altered hemoglobin saturation curve in hypoxic conditions. The workaround was to supplement oximetry with transcutaneous CO2 monitoring and calculate expected SpO2 values using the Severinghaus equation rather than relying on the display alone. This typically improved accuracy by about 4 to 6 percentage points in the critical range. There are also courses in radiation biology relevant to spaceflight. Background cosmic radiation exposure, solar particle events, and the shielding calculations that determine how much mass you need to protect crew during transit. The dosimetry component alone requires understanding linear energy transfer, relative biological effectiveness, and how different tissue types respond to different radiation qualities. This is not theoretical—it directly affects mission architecture for anything beyond low Earth orbit.
How to Actually Enter the Field
If you want a structured path, here's how it typically works. Complete a bachelor's in biomechanical engineering, physiology, or a related life science. Take every elective you can find in aerospace, human factors, or environmental physiology. The key courses that matter most are gas laws and their physiological implications, cardiopulmonary exercise testing, and any lab work involving altitude chambers or hypoxic tents. For graduate study, you have two main routes. The first is a master's or PhD in aerospace biomedical sciences, often housed within engineering schools or dedicated aerospace medicine departments. Programs at institutions with strong NASA partnerships or defense contracts will give you access to centrifuges, altitude chambers, and hypobaric labs. The second route is through medical school followed by a residency in aerospace or flight medicine, which is the path taken by military flight surgeons and some civilian specialists. This takes considerably longer but provides full clinical privileges. One thing most programs gloss over is the certification side. If you're working in an operational context—whether that's air medical services, astronaut selection support, or commercial spaceflight—having credentials from the American Board of Preventive Medicine in aerospace medicine or the Federation of Aerospace Medicine certification adds substantial weight. These aren't optional extras. They're the difference between being a consultant and being the person whose signature goes on a pre-flight medical clearance.
Get the Full Details

Common Pitfalls and What Beginners Miss
The biggest mistake I see is treating aerospace physiology as purely academic. The field is applied by default. A researcher who can model pulmonary gas exchange but has never configured a portable altitude chamber or troubleshooted a failing oxygen delivery system during a live test won't last long in operational roles. I've seen doctoral candidates get passed over for positions simply because they couldn't calibrate a spirometer under time pressure. Another overlooked area is the regulatory environment. FAA medical certification standards, NASA physical requirements, and the emerging commercial spaceflight regulations each have different thresholds for what constitutes acceptable cardiovascular, visual, and neurological function. Understanding these differences matters when you're advising on crew selection or designing protocols for a new vehicle. The FAA Part 67 standards and NASA's anthropometric and physiological requirements for astronauts are not interchangeable, and conflating them in a design review can lead to real problems. There are also limits to what aerospace physiology can tell you. Human performance models break down at the extremes. G-tolerance prediction equations, for instance, have a margin of error that's too large for individual pilot assessment. The standard models account for age, fitness, and G-suit performance, but they can't predict acute susceptibility to G-LOC (G-induced loss of consciousness) for a specific individual in a given moment. The workaround used in most operational settings is a combination of continuous monitoring, proven G-straining maneuvers, and conservative threshold limits rather than relying on predictive formulas. This reduces incident rates but doesn't eliminate them entirely.
Similarly, current countermeasures for microgravity bone loss—resistive exercise, bisphosphonates, vibration therapy—slow degradation but haven't stopped it. Long-duration missions beyond six months still face unacceptable skeletal risk with today's protocols. Any program that presents these countermeasures as a solved problem is oversimplifying. The data from the International Space Station and parabolic flight studies show measurable BMD loss of 1 to 2 percent per month in weight-bearing bones despite intervention. For Mars transit, where a mission could last seven to nine months one way, this remains an open challenge.
Skills That Actually Translate to Employment
Data analysis in this field requires familiarity with specific tools. MATLAB and Python are standard for signal processing of physiological waveforms—ECG, EEG, respiratory traces. You'll also need proficiency with statistical packages like R or SPSS for experimental design analysis. Learning to work with physiological data acquisition systems like Biopac or LabChart gives you hands-on experience that employers notice immediately. Technical writing is another underestimated skill. Reports on physiological responses to hypoxia or G-load need to be clear enough for both engineers and clinicians to act on. I've rewritten documentation that was technically accurate but operationally useless because it described phenomena without specifying actionable thresholds. A proper report will state that orthostatic tolerance decreased by a certain percentage post-flight, what monitoring method detected it, and what intervention brought it back to baseline. That structure saves time in decision-making and reduces misinterpretation. Lab safety training specific to hypobaric and hyperbaric environments is non-negotiable. Altitude chambers operate at pressures that can cause barotrauma if equipment fails. Understanding the emergency procedures, the fail-safes, and the physiological signs of rapid decompression in yourself and others is part of the training. I once worked a test where a seal degraded on a chamber door during a 35,000-foot altitude simulation. The automated system caught it within three seconds, but the initial hypoxic symptoms in the subject—increased respiratory rate, mild tachycardia—were subtle enough that a less-trained observer might have missed them until more serious signs appeared. Having trained personnel watch for early indicators like these is what separates safe operations from incidents.

Networking in this field happens through specific organizations. The Aerospace Medical Association holds an annual scientific assembly that's the primary gathering point for researchers and practitioners. Regional chapters and specialized interest groups around space physiology, aviation psychology, and tactical aeromedical evacuation provide more targeted connections. Membership isn't required to benefit from their publications and conferences, but it does make it easier to find mentors and learn about job openings before they're publicly posted. The field is expanding, particularly with the growth of commercial spaceflight and the increasing number of private companies developing vehicles and protocols for orbital and suborbital operations. This creates demand for professionals who understand both the physiological theory and the practical application. The compensation varies widely depending on whether you're in academia, government contracting, or commercial space, but operational roles in industry tend to pay significantly above the academic equivalent for comparable experience levels. The tradeoff is less publication freedom and more focus on deliverables tied to specific programs.



