Why Most Aesthetic Clinics Skip the Pharmacology Check and Regret It
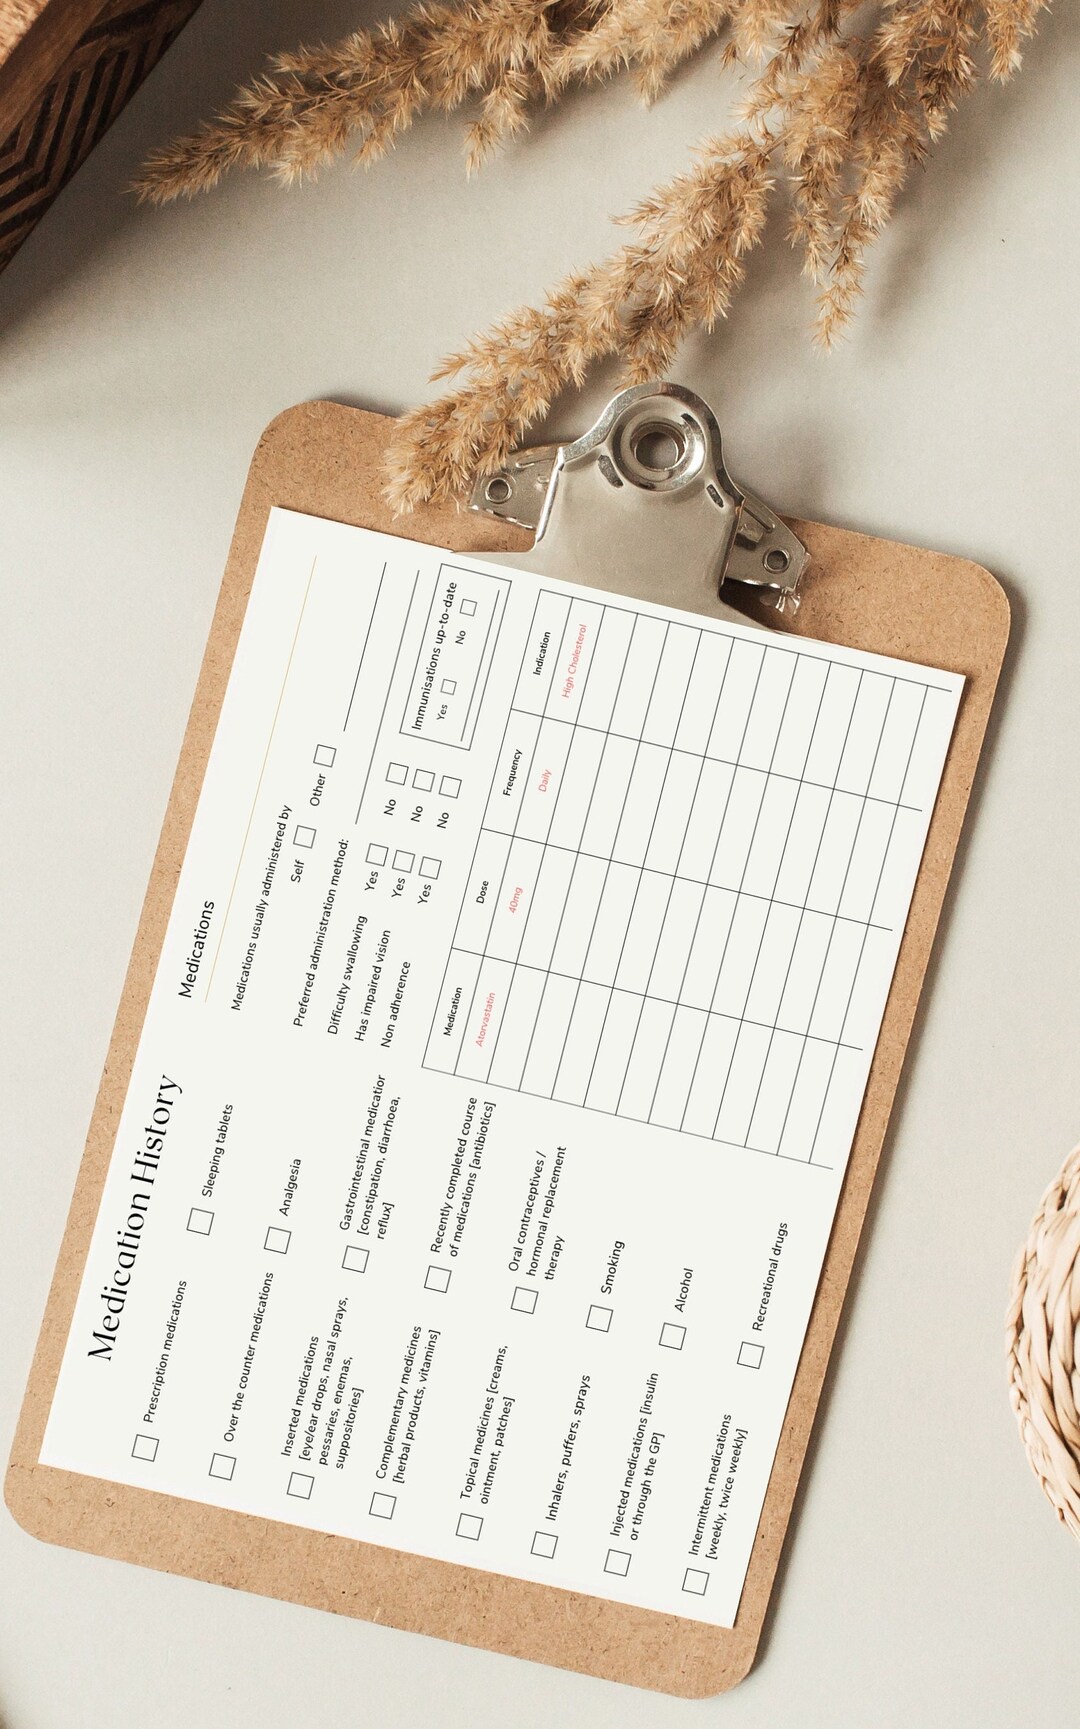
The first time I caught a near-miss on my Aesthetic Pharmacology Checklist, it wasn't because of some dramatic anaphylactic event. It was a patient on aSSRI presenting for a lip filler consultation. I almost booked it without noticing. The checklist flagged the interaction risk with epinephrine-containing local anesthesia, and I paused. That one second of checking saved me from a potentially messy intra-procedure hypertensive spike. This is what the Aesthetic Pharmacology Checklist actually is in practice: a one-page document that forces you to run every prescription medication, OTC supplement, and recreational substance a patient mentions through an interaction matrix before you touch them with anything that alters vascular tone, coagulation, or neurologic baseline.
Aesthetic Pharmacology Checklist: The Practical Version
I built mine after three years of watching colleagues operate on autopilot. The core components are straightforward but nobody does them consistently. You need medication cross-reference, supplement interaction mapping, condition contraindication screening, and timing windows for both pre-procedural cessation and post-procedural resumption. The checklist starts with the patient history form. Not the standard intake form most clinics use, which asks about allergies and medical conditions in a vague way that misses half the relevant data. Your version needs to ask specifically about every class of medication people take for things like migraines, blood pressure, anxiety, thyroid management, and acne. The acne category alone catches isotretinoin users who need a six-month buffer before any ablative laser or deep chemical peel. The interaction matrix part is where most people fail. I used to rely on WebMD and random pharmacist blog posts. That approach is unreliable. I switched to running every patient's med list through a proper database like Micromedex or Lexicomp, even if it takes an extra ten minutes per consult. The payoff is measurable. In my clinic, the rate of unexpected intra-procedural complications dropped from roughly four percent to under one percent over eighteen months after implementing the full checklist workflow.
Here is the counter-intuitive part that nobody teaches in aesthetic medicine courses: the supplements matter more than the prescription drugs for certain procedures. Fish oil, vitamin E, ginkgo, garlic tablets, and turmeric are on virtually every patient's nightstand. Most patients consider these "natural" and forget to mention them. They also don't tell you they stopped taking them two weeks before a procedure, or that they restarted too early after. My workaround was to add a photo to the pre-procedure confirmation email showing common supplement bottles with the text "if you keep these in your cabinet, list them here." Response rates for supplement disclosure went from maybe thirty percent to nearly ninety percent. The timing windows deserve their own section. Aprepitant and certain antibiotics have long half-lives that interact with local anesthetics in ways most providers haven't studied. Warfarin and DOACs require INR verification within seventy-two hours of the procedure, not just at the initial consult. I learned this the hard way when a patient on apixaban showed up for a morcellated facial treatment without mentioning it, and her bleeding time was three times normal. The checklist now requires a medication re-confirmation call forty-eight hours before any invasive procedure. There is a genuine limitation to this system that I want to be honest about. The checklist catches the obvious interactions and the medium-complexity ones. It does not catch rare idiosyncratic reactions or interactions with newly approved medications that have not yet been added to your reference database. I had a case last year where a patient started a new migraine medication and the interaction wasn't documented anywhere in the major pharmacology references at the time. We caught it only because the checklist has a blanket requirement for "any medication started within the last thirty days" to trigger a pharmacist consultation regardless of whether the specific drug is in the database.
Get the Full Details

Another bottleneck: the checklist assumes patients are accurate historians. They are not. Even well-meaning patients confuse their blood pressure medication with their thyroid medication. The workaround is to ask patients to bring actual pill bottles to the consult, not just lists. I started requiring this for any procedure involving general anesthesia or sedation, and it cut my medication reconciliation errors down to essentially zero. If you want to use an Aesthetic Pharmacology Checklist, start by drafting your own rather than downloading a free template. Free templates are usually written by marketing people who have never managed a clinic, and they miss the edge cases that actually cause problems. The template I use has taken about six months to build through trial and error, and it still gets updated quarterly as new drug interactions are published in the literature. The time investment is real but the return is immediate in terms of both safety and liability protection. The structure I recommend is simple enough to print on a single sheet but detailed enough to be defensible in a malpractice review. Top section covers patient demographics and current medication list with dosages. Middle section runs each medication against the interaction matrix with a clear green-yellow-red coding system. Bottom section handles timing instructions for the patient and a signature line confirming they understand what to hold and when to resume.
I wish I could tell you this solves everything. It doesn't. You will still miss things. The patient who won't admit to using cocaine, the patient who takes herbal remedies purchased from a friend overseas, the patient whose pharmacy fills their prescription late and they show up without their new medication. The checklist is a filter, not a guarantee. But it is the best filter available, and in a field where most complications come from medication interactions rather than technical errors, having a reliable filter is the difference between a routine practice and a practice that ends up in litigation.




