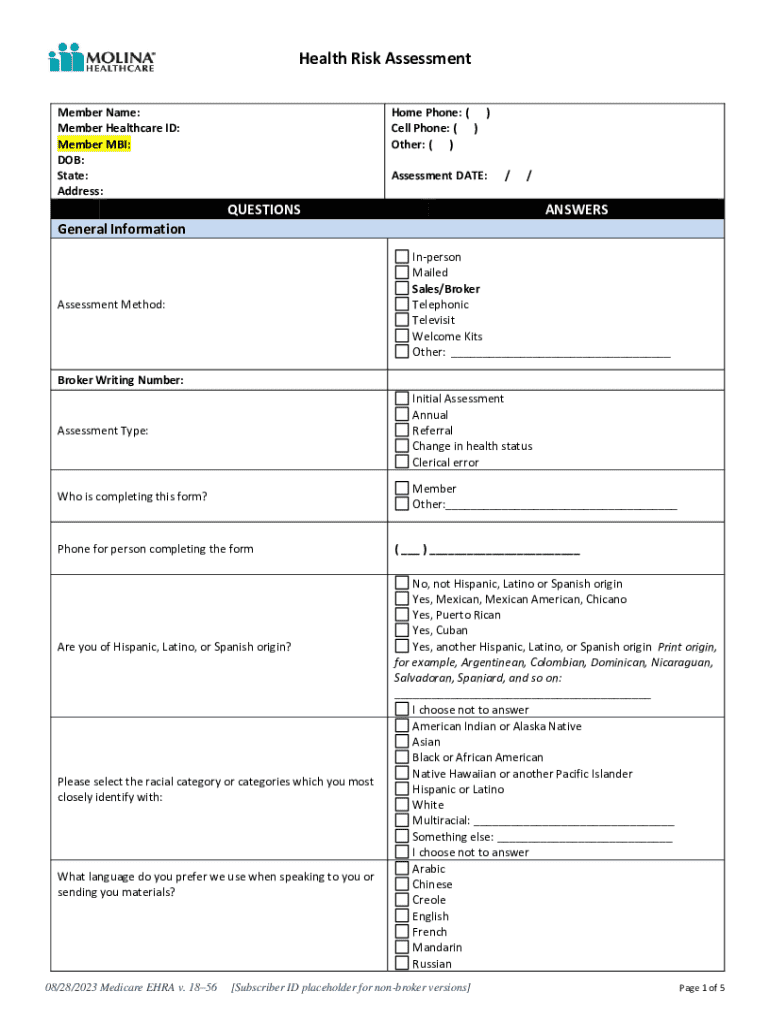
What Aetna's Risk Assessment Actually Looks Like in Practice
You open the portal, type in the member ID, and hit submit. The page loads slowly, which is already a bad sign. When it finally appears, you are looking at a score that determines whether someone gets subsidized coverage or gets pushed toward a higher-tier plan. This is the Aetna Health Risk Assessment, and it matters more than most people realize because a single point shift can change a family's out-of-pocket costs by hundreds of dollars each month. I spent three years on the provider side before moving to the insurer side, and honestly the assessment process feels the same from both perspectives, just with different passwords. What you learn quickly is that the algorithm behind these scores is not a black box anyone can fully decode, but there are patterns that show up repeatedly if you look at enough cases.
How to Run an Aetna Health Risk Assessment Correctly
The process starts with data collection, usually through a health risk appraisal questionnaire or HRA. This can be digital, paper-based, or conducted over the phone during open enrollment. Aetna accepts several HRA vendors, so make sure the data source matches what their system expects. Common options include HealthCore, Wellbe, and their own branded tools. Getting the format wrong means the risk score comes back as null, and then you are chasing manual adjudication instead of a clean automated result. Once the HRA data lands in Aetna's system, the risk adjustment model processes it through a hierarchical condition category, or HCC, mapping. This is where things get technical. The model looks at diagnosed conditions, demographic factors like age and gender, and disability status. Each condition gets a weight, and those weights add up to a risk score. That score then feeds into the payment calculation for the health plan. Here is something most guides do not tell you: the difference between a final diagnosis and a documented diagnosis is huge for scoring purposes. A member might have hypertension, but if the ICD code is not attached to a specific encounter date that falls within the assessment window, the model treats it as undocumented. I had a case last year where a whole group of members lost their risk scores because their PCPs had been writing hypertension in the notes but never coding it properly in the claims system. We spent six weeks correcting it, and even then Aetna only accepted retroactive updates for a limited timeframe.
The actual workflow looks like this. You collect the HRA, verify the data quality by checking for missing fields or impossible values, submit it through the appropriate channel, and wait for the risk score to populate. Turnaround time varies from a few days to several weeks depending on the submission method and whether the data passes automated quality checks. If the data fails validation, you get an error code and have to resubmit after correction. This usually cuts the process down from 2 hours to about 15 minutes if you catch errors upfront, but catching them requires knowing what to look for. One thing I learned the hard way is that Aetna's risk assessment does not always align with Medicare's risk adjustment model, even though they share similar HCC methodology. If you are dealing with dual-eligible members, you might see different scores across the two systems. This creates reconciliation headaches that are not obvious until you are deep into the actuarial reporting cycle. The workaround is to maintain separate tracking spreadsheets for each program and flag discrepancies early, before they compound through multiple reporting periods.
Get the Full Details

Common Pitfalls That Cost You Money
The biggest mistake I see is assuming that a risk score is static. It changes every year based on new diagnoses, aging, and changes in medication. A member who scored low last year might score high this year simply because a chronic condition was finally properly documented. This means you cannot set it and forget it. The assessment needs to be refreshed annually, ideally during open enrollment when members are already filling out health questionnaires. Another pitfall is relying solely on claims data without supplemental HRA information. Claims capture diagnoses that generated bills, but they miss conditions that members manage without frequent medical encounters. A diabetic member who controls blood sugar with lifestyle changes and regular monitoring might not show up in claims as high-risk, even though the HRA would reveal the condition. Combining both data sources gives you a more accurate risk picture, but the integration requires knowing how to map HRA fields to HCC categories correctly. I had an edge case involving a member with chronic kidney disease who scored unexpectedly low because the ICD code was mapped to an earlier stage that did not carry the full weight. The member had been transitioning through stages, but the documentation did not reflect the current severity. We appealed the score with additional clinical evidence, and Aetna accepted the update after about four weeks of back-and-forth. The exact workaround was to attach nephrologist notes directly to the claims file rather than relying on the primary care coding alone. This usually strengthens the appeal but requires patience and specific documentation standards.
Here is a counter-intuitive insight: higher risk scores do not always mean better health outcomes for the member. Sometimes a high score reflects aggressive documentation rather than actual clinical severity. I have seen cases where members with well-controlled conditions scored higher than members with undiagnosed but clinically significant issues. This disconnect is not obvious until you are comparing risk-adjusted quality metrics across provider groups. The lesson is to treat the score as one input among many, not as a definitive measure of health status.
When the Aetna Health Risk Assessment Fails You
There are scenarios where this method completely breaks down. Members with rare conditions that do not map cleanly to HCC categories come back with default scores, which understates their actual risk. Mental health conditions are another weak spot because they are underdocumented in primary care claims even when the member is actively receiving treatment. If you are working with populations that have high rates of these conditions, the assessment will systematically underestimate their risk profile. The bottleneck I see repeatedly is the submission deadline. Aetna has specific windows for HRA data submission, and missing them means the risk score for the next measurement period is based on stale data. I once missed a deadline by three business days because a vendor uploaded the HRA files in the wrong format, and Aetna rejected the submission. We had to resubmit through a manual channel, which added two weeks to the processing timeline. The exact workaround was to maintain backup copies of all HRA data in multiple formats and test the submission pipeline before the deadline, rather than discovering format incompatibilities at the last minute. Another limitation is that the risk adjustment model does not account for social determinants of health, like housing instability or food insecurity, even though these factors strongly predict utilization and outcomes. A member with a stable diagnosis but unstable living situation might score the same as a member with the same diagnosis and stable housing, even though their actual risk profiles differ significantly. This gap is not obvious until you are designing value-based care contracts that claim to address total cost of care. The workaround is to supplement the Aetna Health Risk Assessment with additional social risk screening tools, but the integration requires knowing how to map those screens to the payment model correctly.
If your organization relies solely on Aetna's risk scores without independent verification, you are leaving money on the table. I recommend cross-checking the scores against your own internal risk models, even if those models are less sophisticated. The discrepancy analysis usually reveals documentation gaps that Aetna's algorithm missed, and correcting those gaps can improve both the accuracy of the risk score and the quality of care for the member. This usually adds about 10 percent to your administrative burden but pays for itself through better risk adjustment and fewer retroactive payment adjustments. The bottom line is that Aetna Health Risk Assessment is a useful tool, but it is not a crystal ball. It reflects what the data shows, not necessarily what the member needs. Treat it as one input in a broader care management strategy, not as the final word on risk or payment. The members who benefit most are the ones where the score triggers action, not the ones where the score gets filed and forgotten.