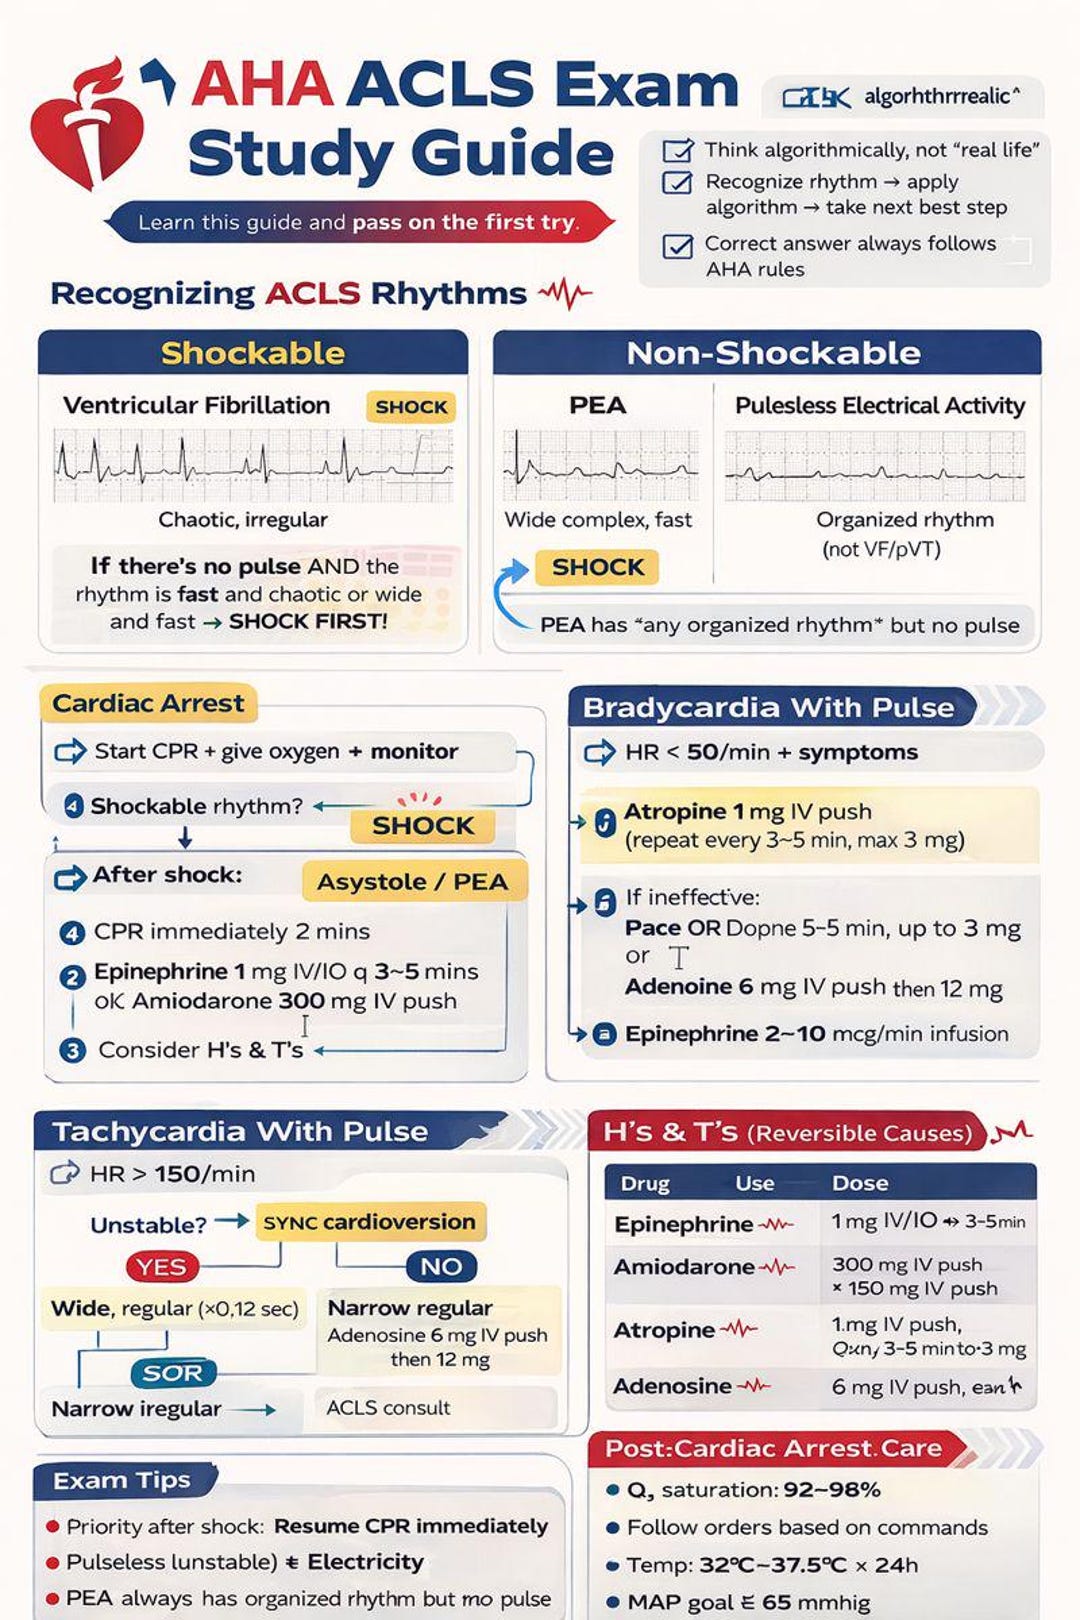
How the AHA ACLS Study Guide Actually Works
I spent three years running ACLS courses at a community hospital before moving into quality improvement, and the thing most people get wrong about studying for the exam isn't the material. It's how they approach it. The AHA ACLS Study Guide is not a book you read cover to cover. It is a reference framework you need to be able to pull from under pressure. That distinction matters more than you'd think when you're staring at a mannequin that won't return a pulse. The ACLS exam has two parts: the written multiple choice section and the hands-on skills stations. Most people prep hard for one and wing the other. I see people ace the written portion and then freeze at the bag-valve-mask station because they've never actually held one during a timed scenario. Or they nail the skills but bomb the written because they memorized algorithms instead of understanding the logic behind them. The study guide covers everything, but knowing where to focus depends on your background.
Using the Aha Acls Study Guide Effectively
Start with the bradycardia and tachycardia algorithms before anything else. These are the ones I see people struggle with most on the exam, and they're also the ones most likely to change depending on whether the patient has a pulse. The AHA updated these algorithms in 2020, and a lot of third-party study materials haven't caught up. Make sure yours is current. The pre-hospital and in-hospital bradycardia pathways are different, and if you mix them up during the exam, you will lose points fast. Here is something nobody tells you about the study guide: the drug dosages matter less than the sequence. On the written exam, they will give you a scenario and four or five medication options. The correct answer is rarely about which drug is right. It is about which drug comes first, second, and third in the algorithm. I had a paramedic once who knew every dose by heart but failed the written twice because he kept choosing amiodarone as a first-line intervention for stable tachycardia when the algorithm clearly calls for vagal maneuvers and adenosine first. He understood the pharmacology. He just didn't follow the flowchart. For the skills portion, you need to practice with the actual equipment. The AHA uses specific manikins and defibrillator trainers that feel different from what you might have in your clinical setting. When I was preparing a group of nurses for their ACLS renewal, I rented the same trainingdefibrillator the testing center used. The pad placement was fine, but the resistance on the chest compressions was noticeably different, and half the group under-compressed on the first try because their muscles were calibrated to a different machine. Worth the seventy-five dollars.
The respiratory and cardiac arrest algorithms are where the real depth lives. The 2020 guidelines changed the emphasis on high-quality CPR metrics, and the exam reflects that. You need to know that the recommended compression depth is at least 2 inches but no more than 2.4 inches for adults, and that you should allow full chest recoil between compressions. These numbers show up directly on the written test. They also matter during the skills station because the trainer monitors your depth and rate in real time. If you are compressing at 140 per minute, the machine flags it even if you think you are right in the 100 to 120 range. One edge case that caught me off guard when I was still taking the exam myself: the modified pediatric algorithms. The AHA ACLS course includes a component on respiratory emergencies and bradycardia in pediatrics, and the drug dosages are weight-based in a way that trips up adults who have not worked in peds recently. I remember calculating epinephrine for a 15-kilogram child during a practice scenario and writing down 0.3 mg instead of 0.15 mg because my brain defaulted to the adult dosing reflex. You have to slow down and actually do the math on the exam. There is no calculator provided. Practice this before test day. The ECG section is another area where people waste time. You do not need to be able to identify every rhythm variant. You need to recognize sinus tachycardia, atrial fibrillation, ventricular tachycardia, pulseless electrical activity, asystole, and the high-grade heart blocks that appear on the bradycardia algorithm. If you spend two days memorizing every dysrhythmia in the textbook, you are studying the wrong thing. The exam tests your ability to act on the rhythms, not your ability to name them.
Get the Full Details

Communication during the team dynamics portion is graded, and it is also the part people ignore. The examiner is listening for clear role assignment, closed-loop communication, and active leadership. If you are the team leader in the skills station and you never say anyone's name or assign a task explicitly, you will lose points regardless of how correct your clinical decisions are. I have seen competent clinicians fail this station because they stayed quiet and let someone else take charge, or because they gave orders without confirming they were understood. Say the name. Get the confirmation. Move to the next step. Download the latest version of the AHA ACLS provider manual from the official AHA website before you start studying. The free study guide that comes with your course registration is adequate, but the full manual has the detailed algorithms and the rationale sections that help you understand why the recommendations exist. Understanding the physiology behind the algorithm makes the written exam significantly easier because the questions often test application, not recall. A question might describe a patient with widened QRS complexes and hypotension and ask what intervention to prioritize. If you only memorized that "wide complex tachycardia equals amiodarone," you might miss the fact that the hypotension changes the answer to synchronized cardioversion. The biggest bottleneck with self-study for ACLS is that you cannot practice the highstakes decision making alone. Reading the study guide will get you through the written portion if you put in the hours, but it will not prepare you for the cognitive load of the skills exam. A peer practice session where you rotate through team leader and performer roles is worth more than another pass through the multiplechoice questions. Time each scenario. Record yourself if you can. Listen back and notice where you hesitated or skipped a step.
Another limitation worth noting: the AHA ACLS course does not cover every advanced airway management technique you might encounter in practice. It focuses on basic adjuncts and the algorithms. If you are an intensivist or a trauma surgeon, the course will feel thin on the procedural side. That is by design. The certification is meant for broad clinical applicability, not subspecialty depth. Bring your own supplemental reading if you need it, but do not expect the ACLS exam to test beyond the published guidelines. The exam costs vary by region and by whether you take it through an AHA training center or an employer-sponsored program. Budget around two hundred to three hundred dollars for the full course including the manual and the exam. Some hospitals cover this for their staff. If you are paying out of pocket, check whether your employer offers a reimbursement program before you register. It saves money and it removes the pressure of feeling like you have to pass on the first attempt. When you walk into the testing center, bring two forms of ID, one of which must be photo identification. They are strict about this. I once watched a respiratory therapist get turned away at the door because his employee badge did not have a expiration date and his driver's license was in another state, and the center required a current address match. Arrive early. Sit down and review the algorithm summary sheets for twenty minutes before they call your name. The whiteboard handout they give you during the skills exam is useful, but it is not a substitute for knowing the sequences cold. It is a safety net, not a crutch.




