Working Through Skeletal Issues In Practice
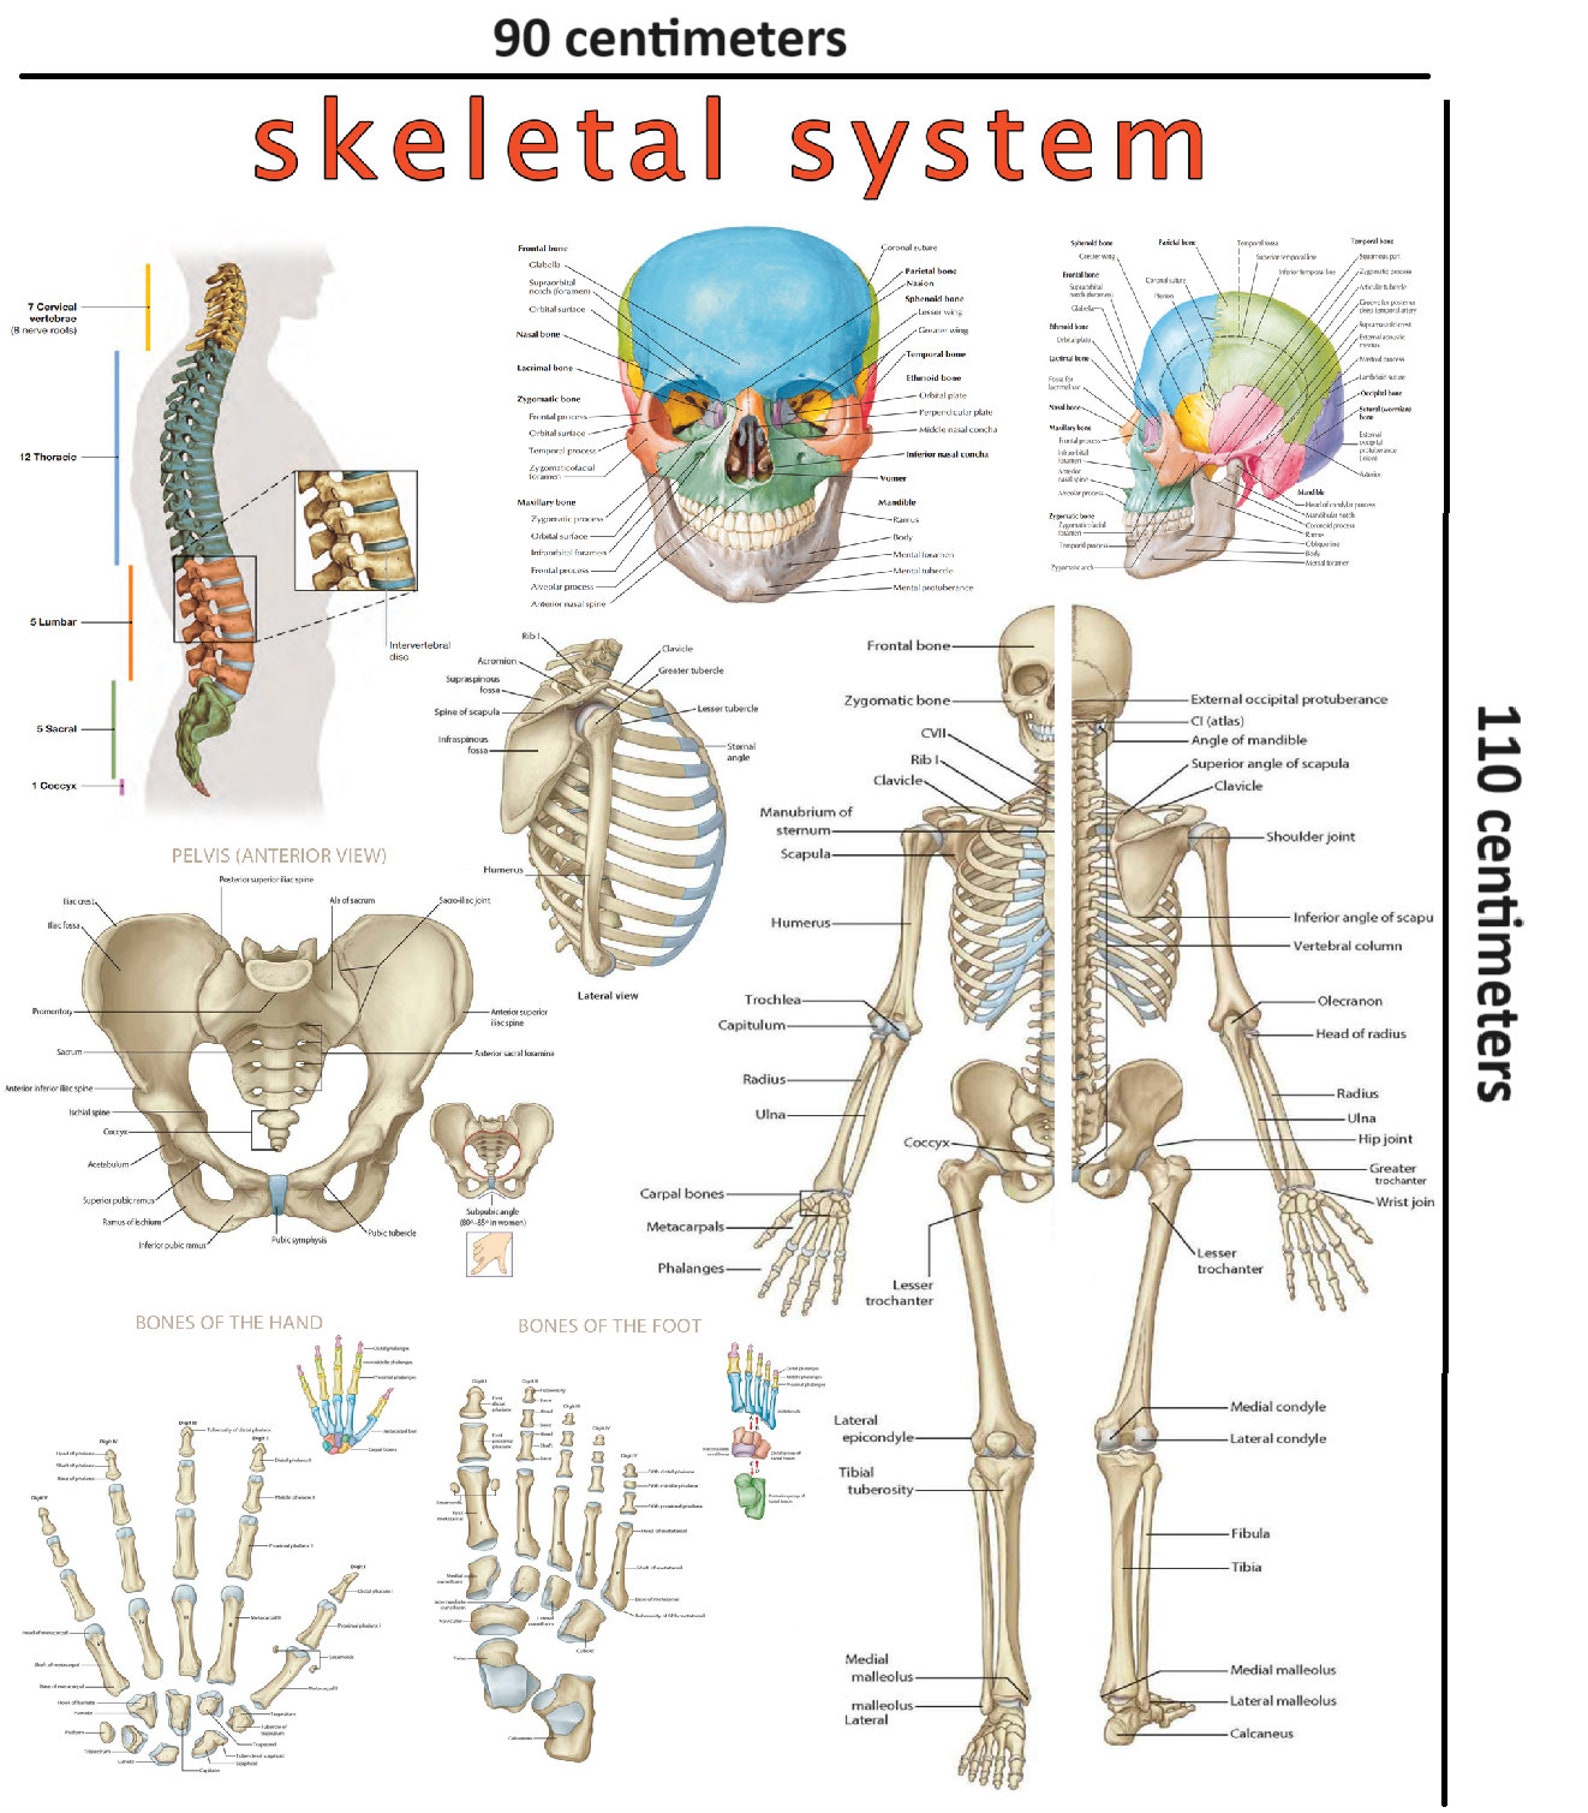
The skeletal system takes a lot of abuse over a lifetime. Cartilage wears down, bones lose density, joints get inflamed, and tendons tear. The usual suspects are osteoarthritis, osteoporosis, fractures, and things like scoliosis. But the real detail nobody talks about is how interconnected it all is. A hip issue changes how you walk, which changes how your knee tracks, which changes how your lower back sits. I once had a patient who came in complaining of persistent knee pain for two years. We spent months working on the knee. Turned out the actual problem was a compressed nerve in the lumbar spine that referred pain down to the joint. Treating the knee never would have fixed it. The spine was the root cause. This is why you need to look at the whole chain when you're dealing with ailments of skeletal system problems. Don't just treat the symptom in isolation. It is lazy medicine and it fails repeatedly in my experience.
Ailments Of Skeletal System — What Actually Goes Wrong
Osteoarthritis is the big one. It is not just "wear and tear" in the simplified sense. The cartilage breaks down, the bone underneath thickens and hardens, and bone spurs form. The joint space narrows on X-ray. Movement becomes painful. It progresses slowly. There is no cure, but progression can be slowed with weight management, targeted strengthening, and occasionally joint replacement when the damage is severe enough. Osteoporosis is another common one. Bone density drops below a threshold where fractures happen from minimal trauma. A fall from standing height, or sometimes just bending over, can break a vertebra. Dual-energy X-ray absorptiometry (DEXA) scans are the standard for diagnosis. T-scores of minus 2.5 or lower confirm osteoporosis. The usual first-line treatment involves bisphosphonates, calcium, vitamin D, and resistance training. The catch is that bisphosphonates have side effects. Atypical femoral fractures and osteonecrosis of the jaw are rare but real risks with long-term use. I have seen both. You do not just hand these out indefinitely without monitoring. Fractures themselves deserve a separate look. Compound fractures, where the bone pierces the skin, need immediate surgical intervention. Stress fractures are trickier because they do not show up on early X-rays. I had a runner come in with what we thought was shin splints. The pain was localized and sharp, not the diffuse ache of periostitis. A bone scan confirmed a stress fracture in the fibula that had been there for weeks. We had been treating it wrong the entire time. MRI or bone scan is the move if clinical suspicion is high and the X-ray is clean.
Diagnosis And Treatment Pathways
Imaging is the starting point. X-rays catch most structural problems quickly. MRI is needed for soft tissue involvement, disc issues, and early stress reactions. CT scans fill in where X-rays are ambiguous, especially with complex fractures involving joints. Blood work matters more than people expect. Inflammatory markers like ESR and CRP help distinguish between inflammatory arthritis and mechanical arthritis. Rheumatoid factor and anti-CCP antibodies point toward rheumatoid arthritis, which is an autoimmune condition, not degenerative. Gout shows up as elevated uric acid, though levels can be normal during an acute flare. Interpreting labs without clinical correlation leads to wrong diagnoses. I have seen patients labeled as having pseudogout when it was actually early-stage rheumatoid arthritis because the joint fluid analysis was not done properly. Treatment ranges from conservative to surgical. Physical therapy is first-line for most mechanical issues. Strengthening the muscles around a joint reduces load on the joint itself. I usually recommend a program that includes isometric holds, progressive resistance, and proprioception work. A unstable knee needs more balance training than a stiff one. A stiff shoulder needs more mobility work than a weak one. Generic rehab programs fail because they ignore this distinction.
Get the Full Details

When conservative treatment does not work, injections become an option. Corticosteroid injections reduce inflammation quickly but should not be used repeatedly. More than three or four per year into the same joint accelerates cartilage damage. Hyaluronic acid injections offer some relief for osteoarthritis, though the evidence is mixed. Platelet-rich plasma (PRP) is popular but expensive and not well-regulated. The preparation method varies between clinics, and outcomes depend heavily on the practitioner's technique. I would approach PRP with realistic expectations rather than assuming it is a miracle solution. Surgery is the last resort for most conditions. Joint replacements have excellent outcomes for end-stage osteoarthritis. Hip and knee replacements reliably restore function and reduce pain. Spinal fusion is more controversial. It works for certain indications like spondylolisthesis or severe stenosis, but it eliminates motion at the fused segment and increases stress on adjacent levels. Adjacent segment disease is a known long-term complication. I have followed patients twenty years after fusion who needed additional surgery at the level above because the compensatory strain became too much.
Prevention And Long-Term Management
Weight-bearing exercise is essential for bone health. Walking, running, and resistance training stimulate osteoblast activity. Sedentary lifestyles accelerate bone loss. This is not new information, but it is consistently ignored. I tell patients that exercise is non-negotiable for skeletal health, not optional. Nutrition plays a supporting role. Calcium and vitamin D are fundamental. Protein intake supports muscle mass, which protects joints. Magnesium and vitamin K2 are often overlooked but relevant for bone metabolism. Supplementing without dietary changes is insufficient. No pill replaces a solid diet and regular exercise. Vitamin D deficiency is widespread. I check levels routinely in patients with unexplained bone or joint pain. Deficiency causes bone softening and muscle weakness, which increases fall risk. The relationship between low vitamin D and fractures is well established. Supplementation at 2000 to 4000 IU daily is common, but dosing should be guided by blood work. Megadoses without monitoring can cause toxicity.
Fall prevention is critical for older adults. Home safety assessments, balance training, and reviewing medications that cause dizziness can reduce fracture risk. Hip fractures in the elderly carry significant mortality. The first-year mortality rate after a hip fracture is around 20 to 30 percent. Preventing the fall in the first place is infinitely better than treating the fracture. Scoliosis deserves mention because it affects posture and can cause chronic pain. Idiopathic scoliosis is the most common type and usually appears during adolescence. Bracing can prevent progression in moderate cases. Surgery is reserved for curves over 50 degrees. Adult-onset scoliosis is different. It develops from degenerative changes and can compress nerves. Treatment focuses on pain management and decompression when neurological symptoms appear.
Common Mistakes People Make
Self-diagnosing based on internet searches is the biggest error. Back pain is rarely a serious condition, but people assume the worst. Most back pain is mechanical and self-limiting. It improves within a few weeks without intervention. Imaging before six weeks of conservative treatment is generally unnecessary and leads to overdiagnosis. Incidental findings on MRI, like disc bulges, are common in asymptomatic people. Treating the image instead of the patient causes more harm than good. Another mistake is ignoring early symptoms. Mild joint stiffness in the morning that lasts less than thirty minutes is normal. Stiffness lasting longer, especially in multiple joints, warrants evaluation. Waiting until pain becomes severe means waiting until structural damage has progressed further. Early intervention preserves function. Over-reliance on pain medication is the third major error. NSAIDs are useful short-term but cause gastrointestinal and renal complications with chronic use. Opioids are worse. They have minimal long-term benefit for non-cancer pain and carry addiction risk. I prescribe them sparingly and only when other options have failed. Physical therapy, lifestyle modification, and targeted injections should come first in almost every case.
The skeletal system is resilient but not indestructible. Understanding how it fails, recognizing patterns early, and taking appropriate action makes the difference between managing a problem and living with permanent damage. The information here reflects what I have seen work and what I have seen fail. Use it accordingly.