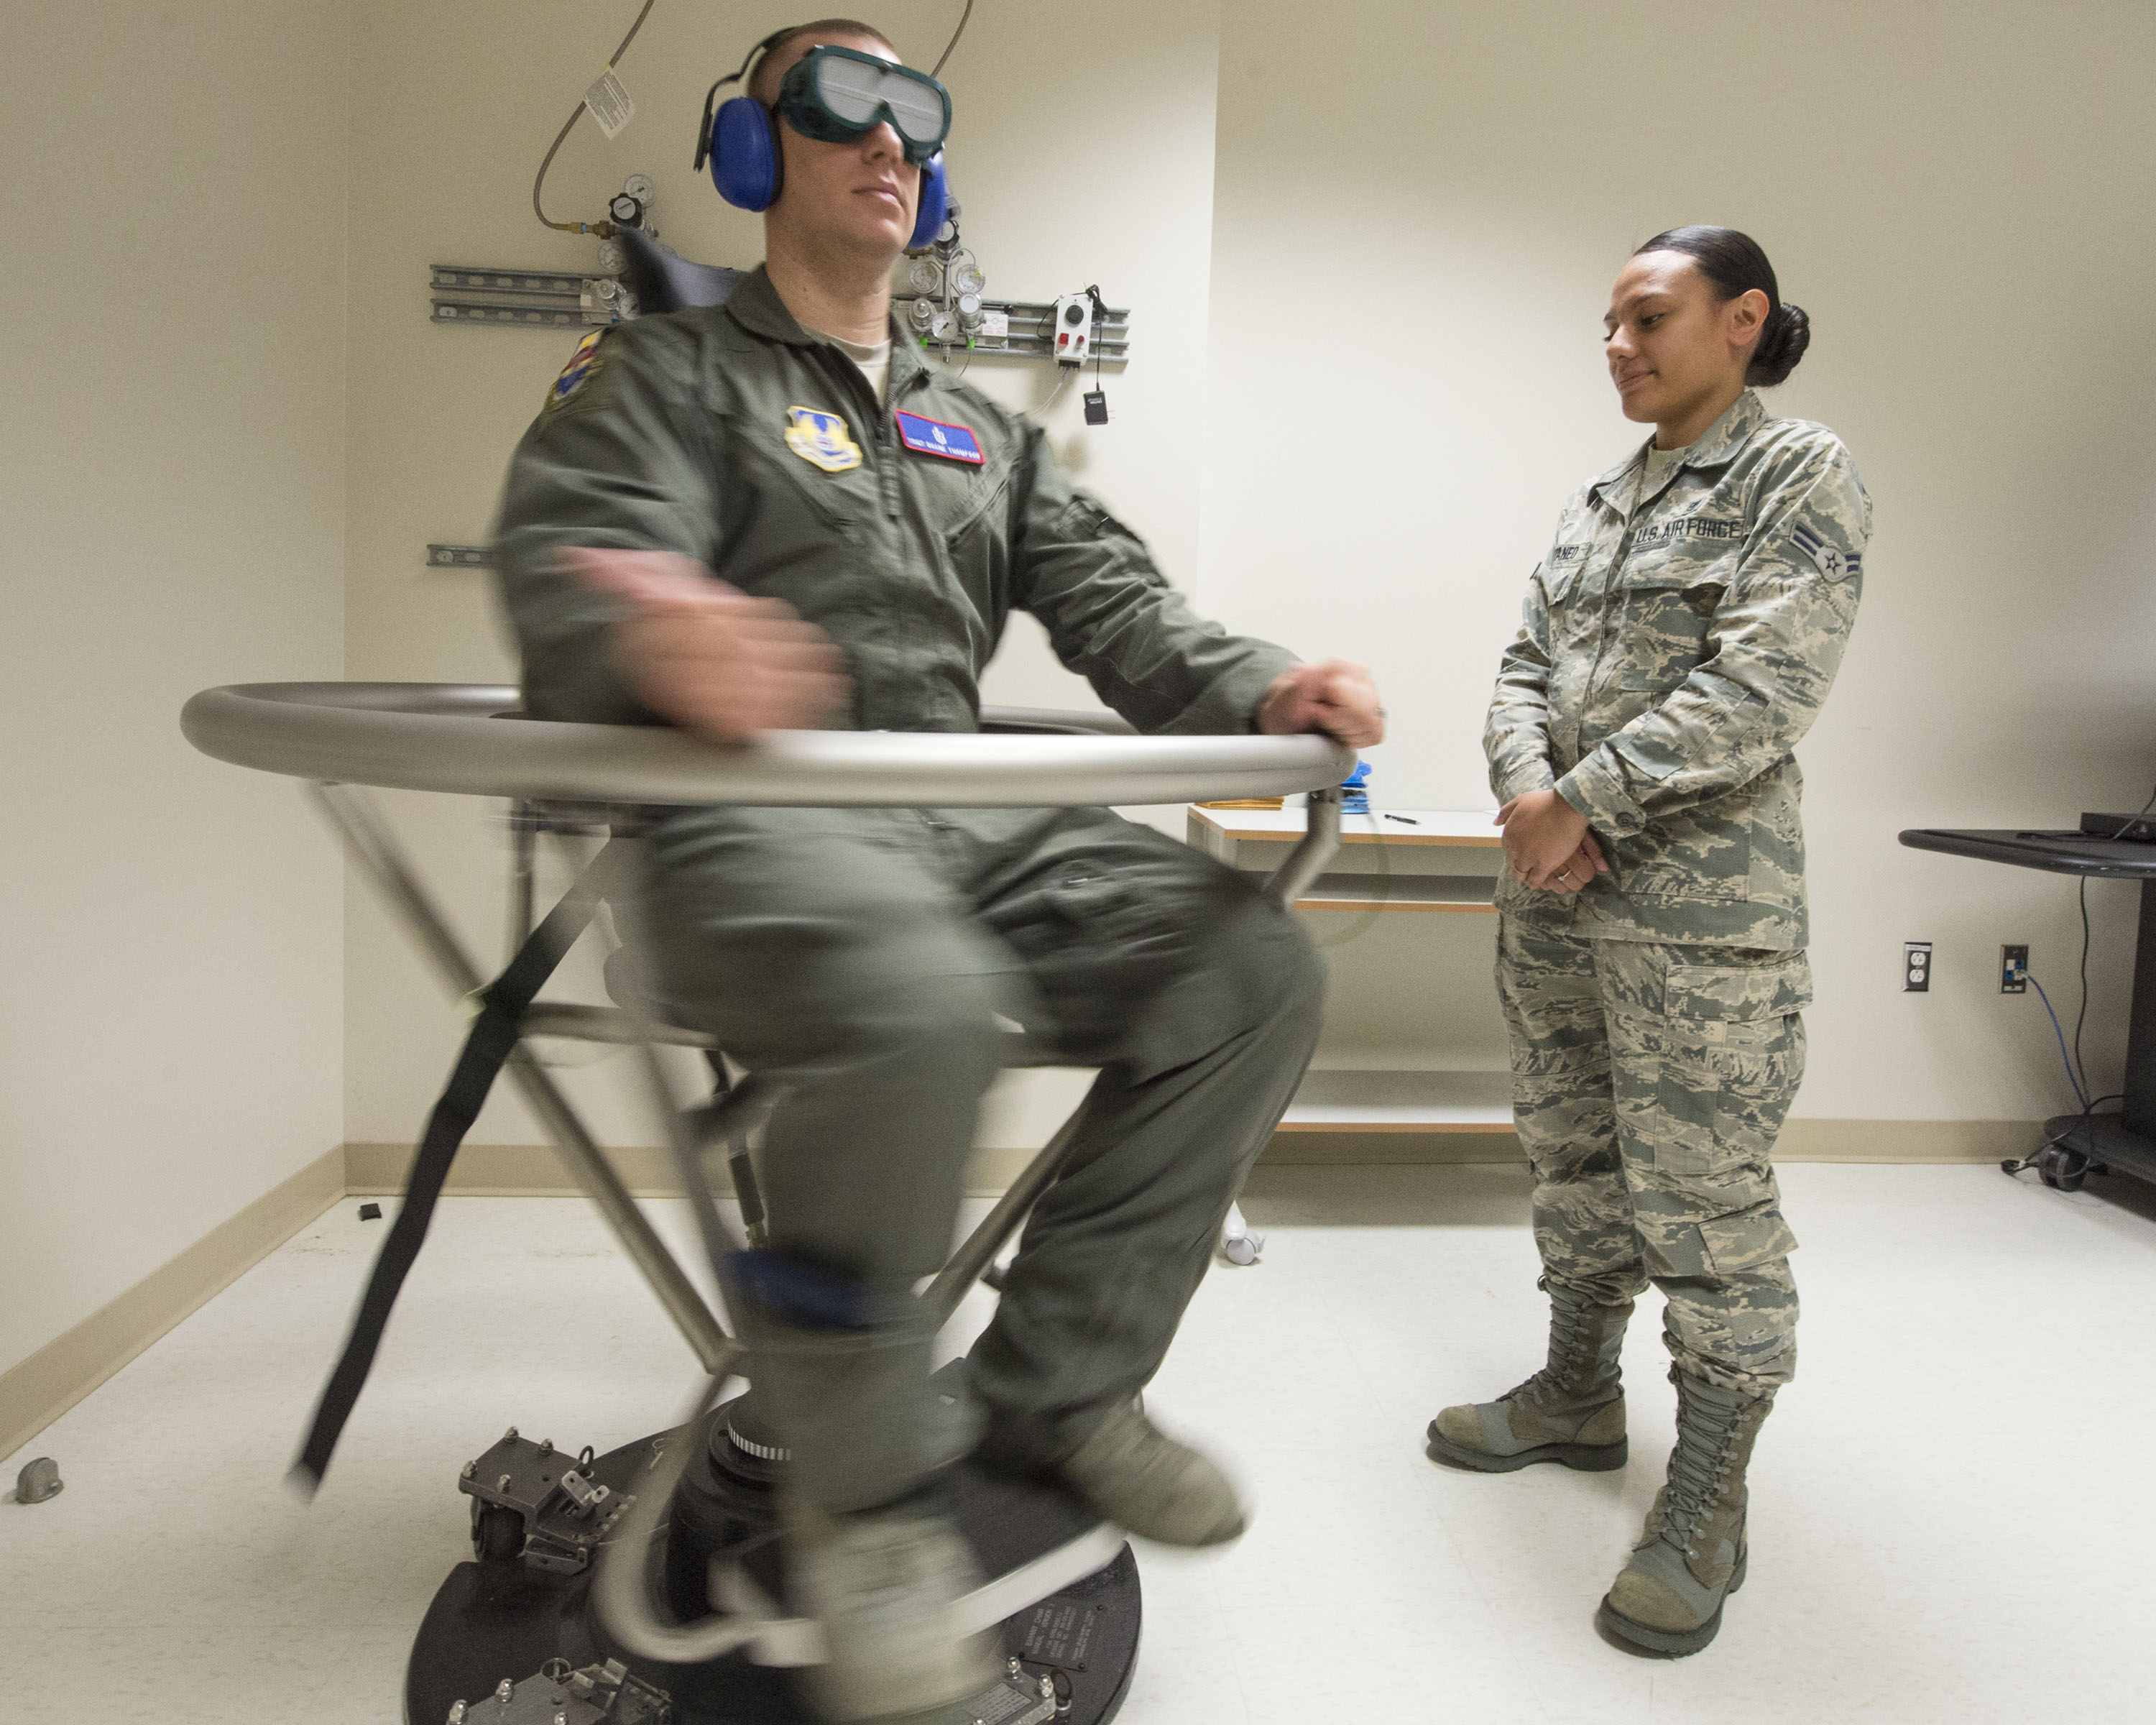
Air Force Aerospace Physiology covers the study of how the human body responds to the extreme environments encountered in aircraft and spacecraft. It spans high altitude, hypoxia, G-forces, decompression, thermal stress, and vibration. If you are studying for a qualification or supporting a flight crew, knowing the textbook definitions is not the same as understanding what actually happens in the cockpit.
The Hard Parts of Air Force Aerospace Physiology
The core challenge is that the body has multiple overlapping systems fighting against each other when you pull 9Gs, lose cabin pressure at 40,000 feet, or get hit with centripetal forces during high-speed turns. Hypoxia is the most dangerous because it impairs judgment before you realize anything is wrong. I have seen pilots dismiss early symptoms as fatigue because the onset is so gradual above 10,000 feet without supplemental oxygen.
G-force tolerance varies wildly between individuals and even between flights for the same person. Hydration status alone can swing your G-tolerance by two or three Gs. Dehydrated pilots black out significantly faster. That is not taught enough in initial briefings.
How This Actually Works in Practice
The standard protocol for high-altitude operations starts with understanding the line of acceptance. This is the altitude threshold where certain physiological effects become inevitable without protection. Above 10,000 feet, the body begins to experience reduced oxygen saturation. Above 40,000 feet, unsupplemented consciousness lasts roughly 3 to 5 seconds after decompression. That number gets people's attention.
For G-force management, the standard anti-G straining maneuver is well documented, but execution is where most people fail. The muscle tension has to be sustained, not pulsed. Many aircrew tense up during the first 3 to 4 seconds of a high-G turn and then relax when they need to hold the squeeze the longest. That is the moment blood pools in the lower extremities and vision gray-outs.
Breathing technique matters more than people admit. At altitude, you should breathe slowly and deliberately through the mask. Rapid shallow breathing from anxiety or stress accelerates CO2 washout, which triggers cerebral vasoconstriction and makes hypoxia symptoms worse faster. I once worked with a pilot who kept passing out during simulator sessions at high altitude. We traced it back to him breathing at 20 breaths per minute through the regulator. Dropped him to 10 and he was fine.
Decompression Events and Real-World Response
When a pressurization failure occurs, the timeline is brutal. At 35,000 feet, effective consciousness time after sudden decompression is around 30 to 60 seconds. At 45,000 feet, it drops to 15 seconds or less. The immediate response is to don the oxygen mask, secure your own airway first, then assist others. Pilots are drilled on this, but the mask sequence itself is a skill. If you fumble with the mask while descending through altitude, you lose precious seconds.
One specific problem I dealt with involved a recurring issue during high-altitude flights where crew members reported headaches and nausea that persisted after landing. The obvious answer was hypoxia, but pulse ox readings in the cabin were normal. We ended up tracking it to a small but consistent leak in the mask seal caused by facial hair on one crew member. The mask was technically on, but ambient air was mixing with the oxygen supply, creating a partial hypoxic environment that was subtle enough to fly through without immediate recognition. The workaround was a strict pre-flight mask seal check procedure and limiting certain facial hair configurations for high-altitude mission crew. It sounds minor. It caused multiple aborted training flights over six months.
G-Force Physiology and Blood Redistribution
During positive G acceleration, blood is forced away from the brain toward the feet and abdomen. The cardiovascular system compensates through baroreceptor reflexes, increasing heart rate and peripheral vasoconstriction. But at 4 to 5 Gs and above, these mechanisms are insufficient without conscious intervention. The anti-G strain maneuver combines leg and abdominal muscle tension with forced exhalation against a closing glottis, creating back pressure that keeps blood in the upper body.
A counter-intuitive point: the maneuver should not be initiated until G forces actually begin to build. Tensing up before the Gs hit wastes energy and causes premature fatigue. Start the squeeze at the same moment you feel the acceleration. Also, many aircrew practice the maneuver by holding their breath under pressure, which is incorrect. You need to be able to sustain the muscle tension while breathing or performing short forced exhales. A held breath only works for about 10 to 12 seconds before CO2 buildup forces you to release.
There is also a common pitfall with G-suits. The bladder inflation needs to be synchronized with G-load. If the suit inflates too early, it restricts venous return before the Gs are even applied, reducing cardiac output unnecessarily. If it inflates too late, the blood has already pooled. The timing is usually automatic in modern systems, but it is worth verifying during pre-flight checks. I have seen suits on older platforms where the inflation port was partially blocked by debris, causing delayed response that went unnoticed until a live flight test.
Thermal and Vibration Stress
High-altitude aircraft operate in temperatures well below -40°C. Cold stress reduces dexterity in fingers and toes, which affects switch operation and control inputs. Heated gloves and boots are standard, but battery life in cold conditions degrades faster than expected. I once had a mission where glove heating failed at altitude because the batteries had been stored in the cold cargo hold overnight instead of being warmed in the ready room. Total loss of finger dexterity for 45 minutes until we could redirect.
Vibration exposure is another underrated factor. Sustained high-frequency vibration from engine and airframe sources causes fatigue, reduces manual tracking performance, and contributes to lower back pain over time. Whole-body vibration standards exist, but they are based on aggregate exposure across a career, not per-mission limits. A single long mission with poor seat maintenance can push you closer to the threshold than you think.
Training and Physiological Readiness
The practical side of Air Force Aerospace Physiology comes down to conditioning and awareness. Cardiovascular fitness is the single best predictor of G-tolerance. An aerobic base improves the body's ability to maintain blood pressure under acceleration. Core strength matters for the anti-G maneuver. There is no shortcut around physical training.
Sleep and circadian disruption also degrade physiological performance significantly. A pilot flying a red-eye mission after limited sleep will have slower reaction times and reduced G-tolerance comparable to someone who is mildly intoxicated. This is well documented but still routinely ignored in operational scheduling.
Limitations and Where This Breaks Down
No amount of training makes you immune to the physics involved. The human body has hard limits. You will blackout at sufficient G-load regardless of how well you are conditioned. You will lose consciousness without oxygen at extreme altitude. The physiological protocols are risk reduction tools, not guarantees.
Similarly, the medical screening process catches many issues but misses others. A pilot who passes a routine flight physical can still have undiagnosed cardiac arrhythmias or vestibular problems that only manifest under stress. This is why in-flight monitoring and honest self-reporting matter. Skipping a symptom because you do not want to lose flight status is the fastest way to create a catastrophic situation.
Key Takeaways for Air Force Aerospace Physiology
Focus on the things you can control. Hydration, fitness, proper mask seal checks, correct breathing patterns, and honest reporting of symptoms. The systems and procedures are there for a reason, but they assume you are executing them correctly. The gap between textbook knowledge and actual performance is where most incidents originate.
Gallery Air Force Aerospace Physiology
USAFSAM aerospace physiology training optimizes airmen’s performance > Air Force Medical Service ...
Aerospace Physiology Technician - U.S. Air Force
USAF Air Force Aerospace Physiology Medical 4" Desert DCU patch c/e | #4604092715
USAFSAM aerospace physiology training optimizes airmen’s performance > Air Force Medical Service ...
USAFSAM aerospace physiology training optimizes airmen’s performance > Air Force Medical Service ...