Working With the 7th Edition Head and Neck Staging System
The 7th edition AJCC manual for head and neck cancers changed more than just number assignments. It introduced meaningful shifts in how certain anatomical sites are categorized, and if you are staging from that era, you need to understand where the system actually holds up and where it breaks down. One of the first things you will notice is the reclassification of oropharyngeal cancers. Before HPV became a dominant driver in this region, the staging was largely anatomical. The 7th edition kept that approach, but it also set the groundwork for the dramatic changes that would come in the 8th edition. I remember reviewing a case of a base of tongue primary with multiple nodal metastases on the contralateral side, and the T category was entirely dependent on whether the tumor invaded through the lingual tonsil or was contained within the lymphoid tissue. That distinction mattered because it shifted the T stage from T1 to T2, which changed the overall stage group and influenced whether we were discussing surgery alone or adding radiation. The guidelines were clear on paper, but in practice, the difference between "invading" and "involving" became a source of contention between pathologists and radiologists.
Ajcc Cancer Staging Manual 7th Edition Head And Neck Cancers Download and Practical Use
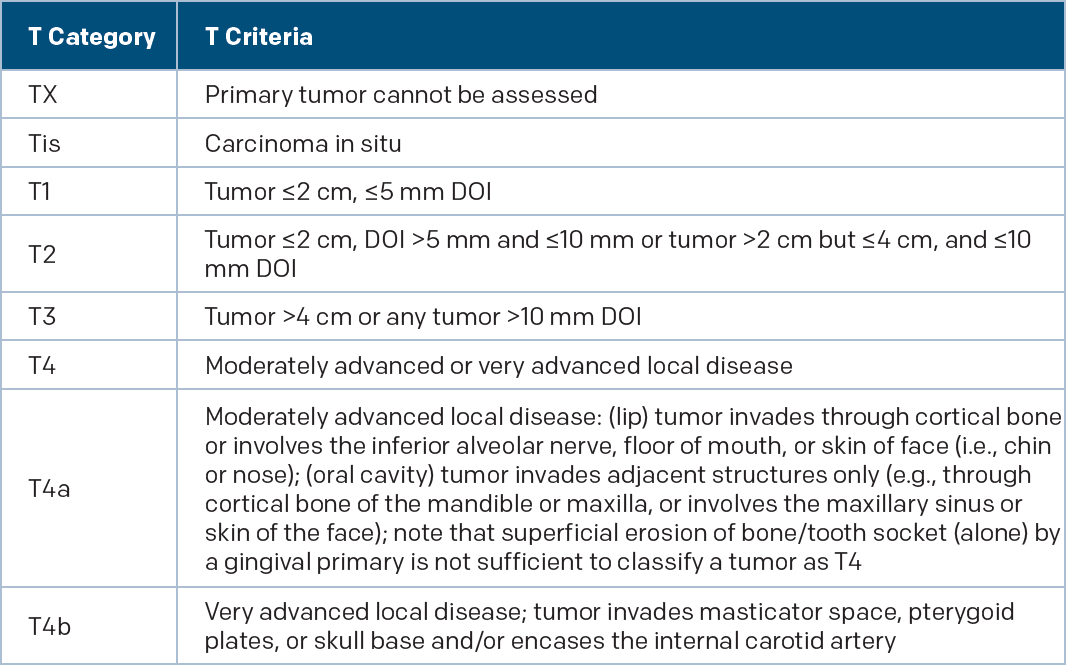
The manual itself is available through the American Joint Committee on Cancer website, and most medical libraries carry the printed version. For clinical reference, the quick-reference pocket guide is often more useful than the full textbook because it strips away the methodology chapters and leaves only the staging tables. You will find that the head and neck chapter spans roughly 40 pages covering oral cavity, oropharynx, hypopharynx, larynx, nasal cavity, paranasal sinuses, and salivary gland primaries. Each subsite has its own TNM definitions, and the nodal staging is unified across most of these sites under the N1 through N3 framework, which is one of the advantages over site-specific systems used in other cancer types. There is a critical detail that is easy to miss. The 7th edition defines extranodal extension as a criterion for upstaging in the N category for most head and neck sites except oropharynx and nasal cavity in this particular version. That means a node with bulky disease but no ENE might stage lower than a smaller node with proven extracapsular spread, and this distinction directly affects adjuvant treatment decisions. I learned this the hard way when a colleague staged a patient as N2b based on a single ipsilateral node measuring 6 centimeters without ENE, while another reviewer, looking at the same CT with subtle fat stranding around the node, argued for ENE presence and pushed it to N3a. The pathology report ultimately confirmed ENE, but not before we had a lengthy multidisciplinary discussion. The takeaway is that ENE assessment on imaging is notoriously unreliable, and the manual explicitly states that pathological confirmation is the standard for N staging accuracy. Another area where the 7th edition gets fussy is depth of invasion for oral cavity tumors. This was one of the most significant changes because prior editions relied almost entirely on tumor diameter. The 7th edition requires DOI measurement for T1 and T2 oral cavity cancers, measured from the surface of the adjacent normal mucosa to the deepest point of invasion. You cannot estimate this from imaging alone in most cases. I have seen multiple instances where a tumor appeared superficial on MRI but on pathological sectioning measured 8 millimeters in depth, shifting it from T1 to T2. The difference is not trivial. T1 oral cavity cancers have significantly better survival outcomes, and staging them correctly matters for prognosis discussions with patients.
The manual also covers recurrent laryngeal nerve palsy as a criterion for T4a classification in laryngeal cancers. This is another nuance that gets overlooked. A patient with a glottic tumor and a paralyzed vocal fold due to nerve involvement stages as T4a regardless of the size or extent of the primary tumor. I encountered a case where the tumor was small and visually limited to the vocal cord, but the patient presented with aspiration and a non-mobile cord. Staging as T4a upstaged the disease and changed the surgical approach from cordectomy to total laryngectomy. The nerve involvement criterion exists because it indicates deeper infiltration beyond what is visible on endoscopy. For nodal staging, the 7th edition maintains the size-based thresholds for most non-HPV-associated head and neck cancers. A single ipsilateral node 3 centimeters or less without ENE is N1. A single ipsilateral node greater than 3 centimeters but not greater than 6 centimeters is N2a. Multiple ipsilateral nodes, each 6 centimeters or less, is N2b. A contralateral or bilateral node is N2c. Anything above 6 centimeters or with ENE moves into N3. This system is straightforward, but it has a well-known limitation. It does not account for the number of nodes in certain configurations, and it treats all nodes equally regardless of whether the metastasis is central or peripheral. The 8th edition attempted to address some of these issues by incorporating ENE more systematically and introducing HPV-specific staging for oropharyngeal cancers, but for cases staged under the 7th edition rules, these definitions are the final word. Salivary gland staging under the 7th edition is grouped by histology rather than site, which is unusual compared to the rest of the head and neck chapter. High-grade histology includes adenoid cystic carcinoma, salivary duct carcinoma, and high-grade mucoepidermoid carcinoma, while low-grade includes low-grade mucoepidermoid carcinoma and acinic cell carcinoma. The T categories are the same across both groups, but the distinction matters because prognosis differs significantly between high and low-grade tumors. I have seen this cause confusion in multidisciplinary meetings where the pathologist and oncologist were using different grade classifications. Always confirm the grade designation before applying the staging table, because misclassification here directly affects stage grouping.
Get the Full Details

One practical issue with using the 7th edition today is that it is outdated for many clinical scenarios, particularly oropharyngeal cancer. If you are working with historical data or staging patients from the 7th edition era, stick to those criteria consistently. Do not mix in 8th edition HPV staging retroactively, because the two systems produce different stage groups for the same clinical presentation. A patient staged as IIIB under the 7th edition might be stage I under the 8th edition HPV-positive rules, and conflating the two creates errors in clinical trials and outcomes analysis. I have seen this happen in database reviews where researchers pulled cases from multiple years without accounting for the staging edition change, resulting in apparent survival improvements that were entirely an artifact of reclassification rather than a real treatment effect. If you need the full text, the AJCC official site at ajcc.org provides the manual for purchase, and cancer staging websites affiliated with academic centers often host the current and previous edition PDFs for reference purposes. The printed book remains the authoritative source, and any online summary should be cross-referenced against it before being used for clinical decision-making or research documentation.