Understanding the Al Suffix in Medical Terminology
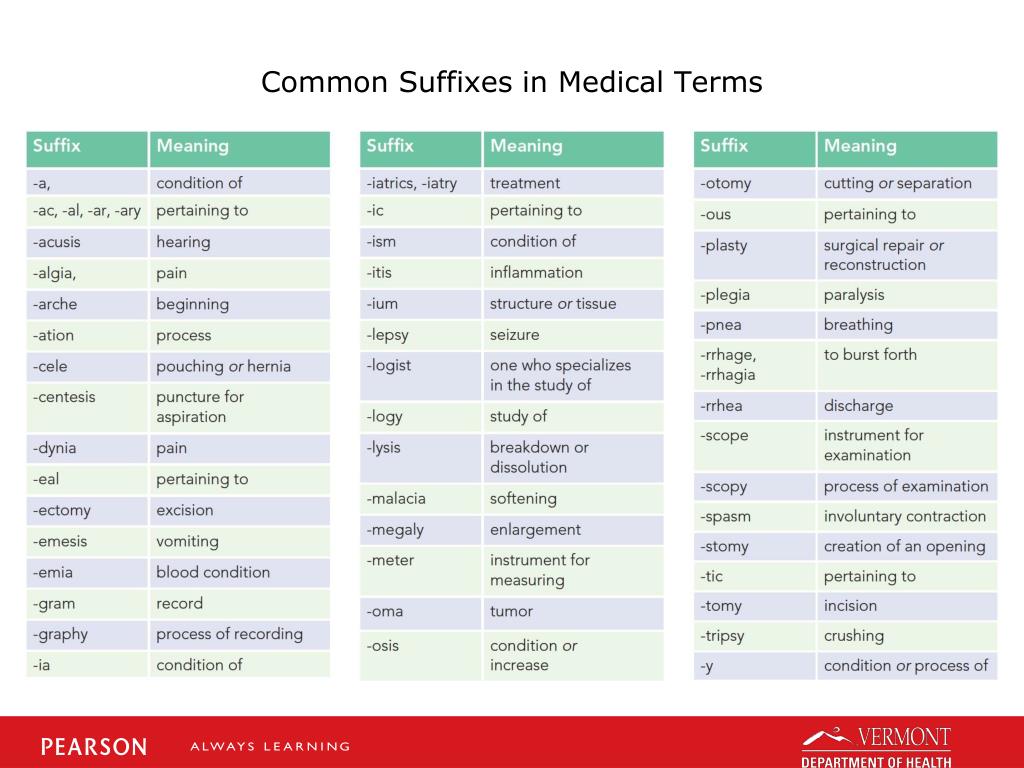
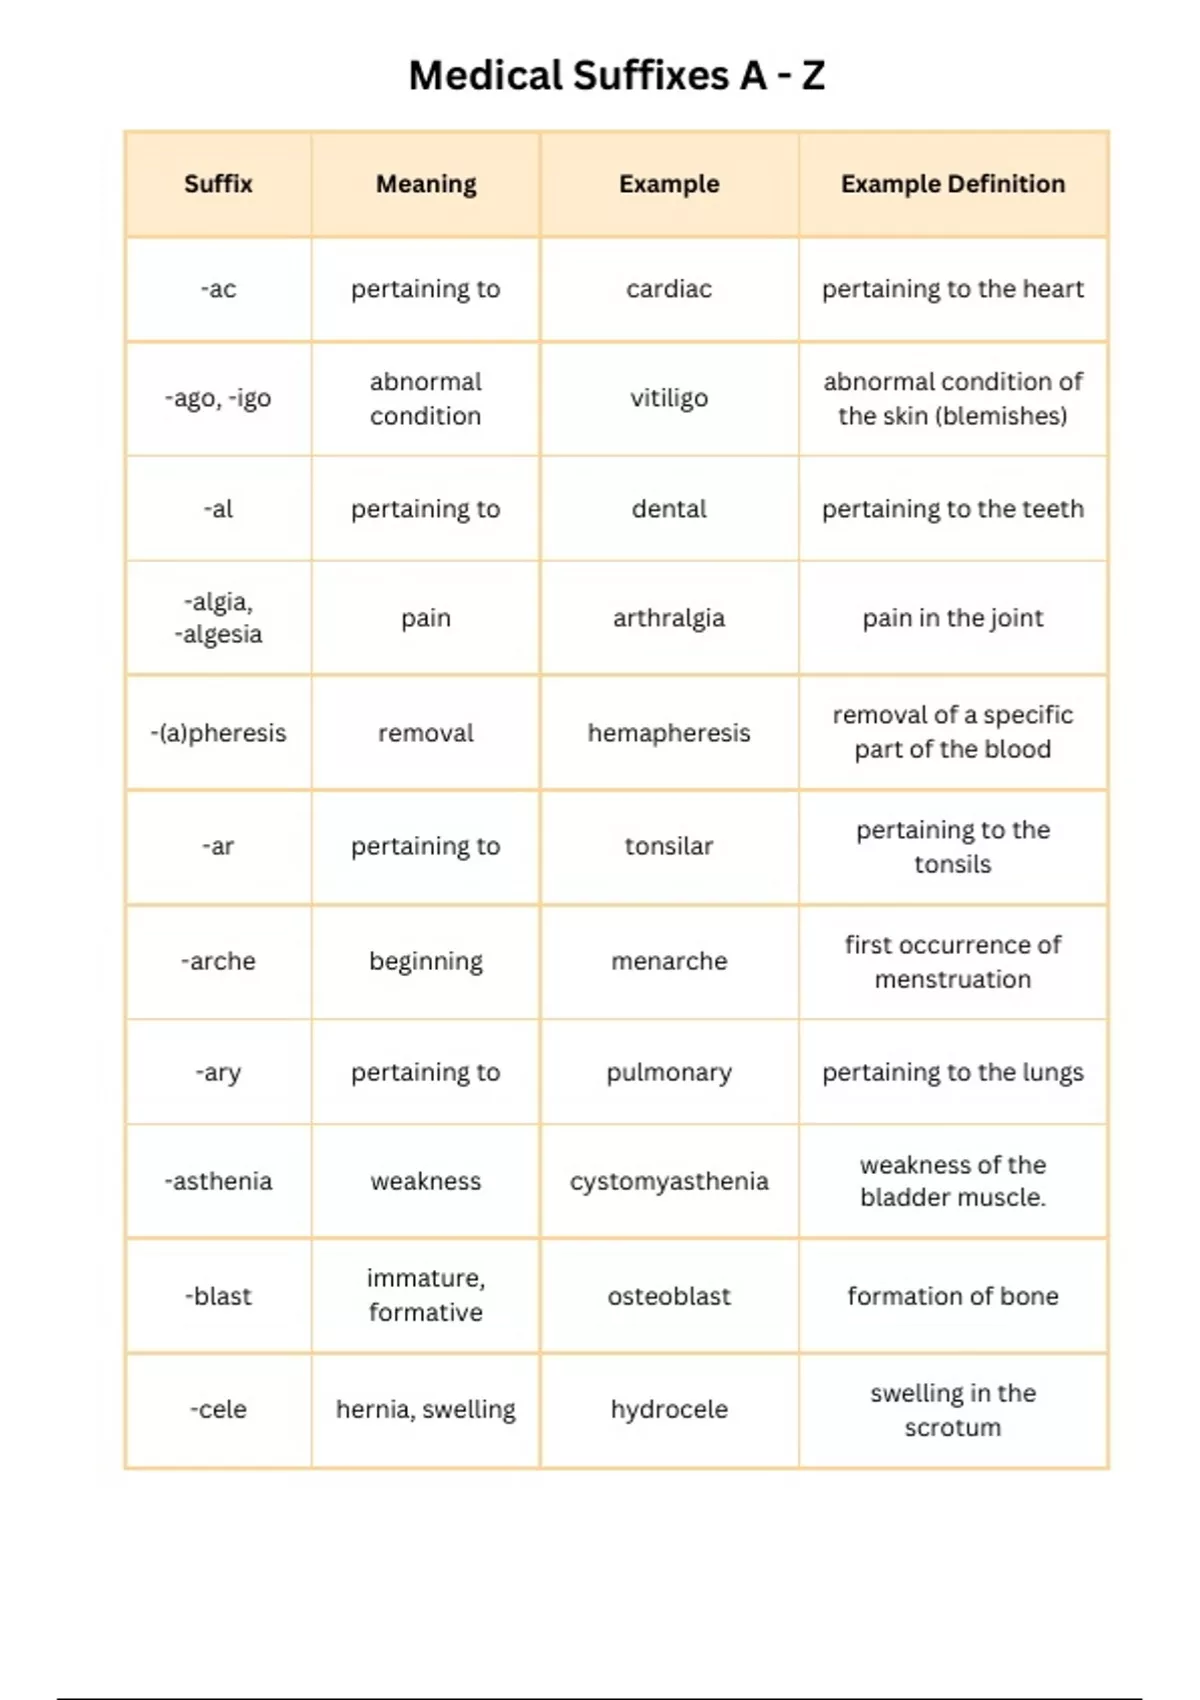
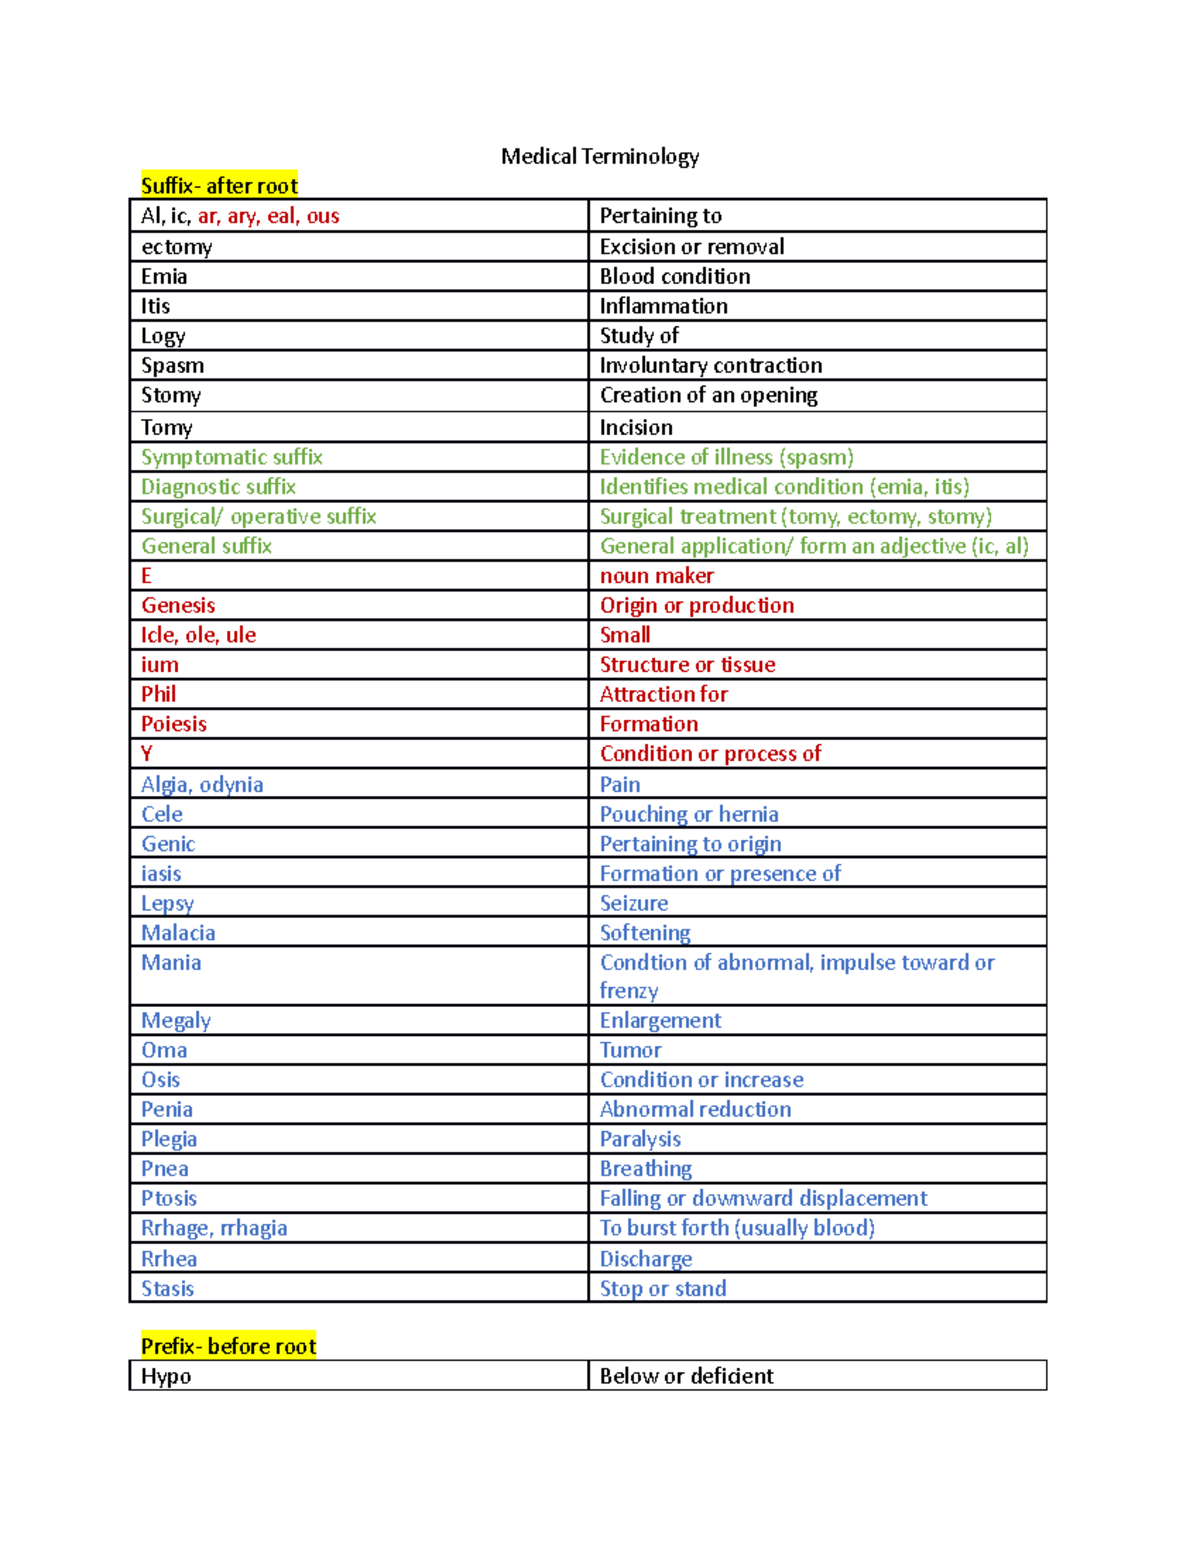
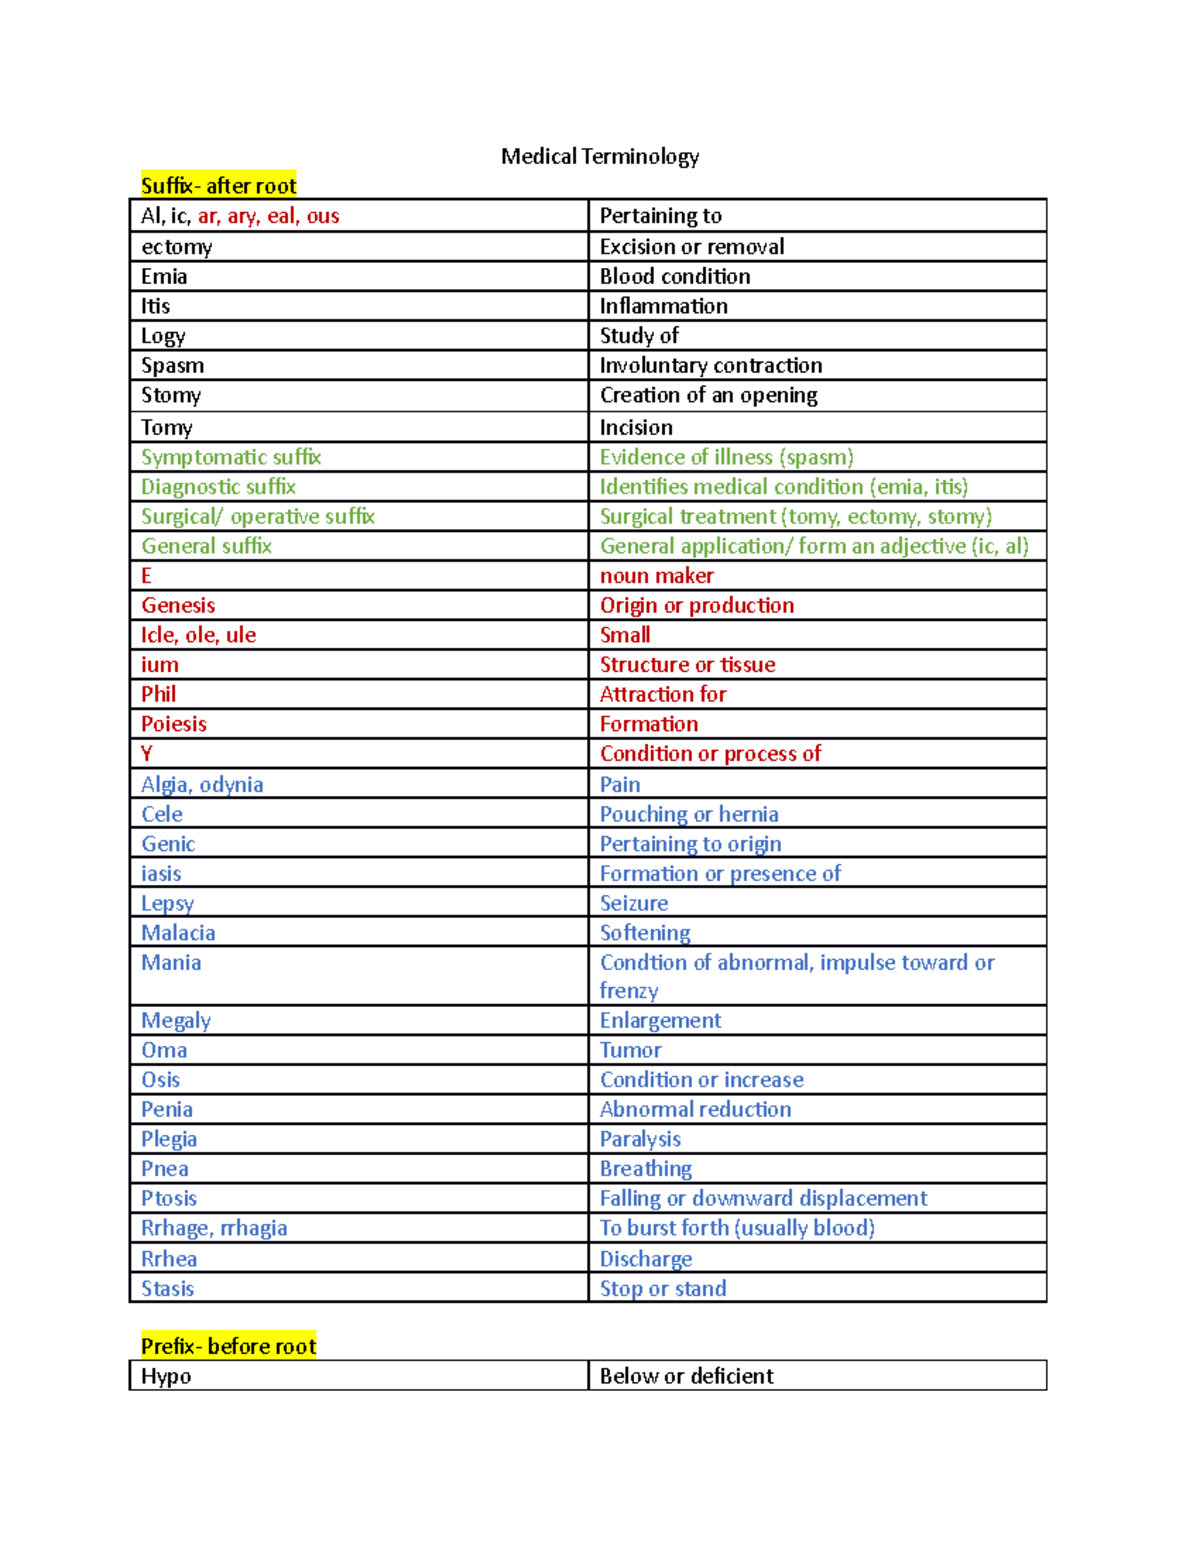
The suffix -al in medical terminology simply means "pertaining to." It attaches to a root word to indicate that something relates to the structure, function, or condition of that anatomical part or system. This is one of the most common suffixes you will encounter, and it shows up everywhere from basic anatomy courses to clinical documentation. When you see -al at the end of a medical term, you are looking at an adjective. The word it modifies describes a relationship to the root. Oral means pertaining to the mouth. Dermal means pertaining to the skin. Auricular means pertaining to the ear. You can apply this pattern consistently across hundreds of terms without having to memorize each one individually. The root typically comes from Latin or Greek, and the suffix simply converts it into an adjectival form. That is the full mechanism. It is not conditional on the root's origin, though some etymologies are far more common in clinical settings than others.
Where People Go Wrong With This Suffix
I spent years reviewing lab orders and physician notes, and the mistake I kept seeing was conflating -al with other similar-looking suffixes. -ic means the same thing in most cases, which is why "cardiac" and "kardiack" (an older variant) both work. Beginners often treat -al as if it always pairs with a specific root type, but it does not. It is flexible. Another trap is assuming -al always creates a one-to-one correspondence with the noun form. Skeletal pertains to the skeleton, yes, but "skelet-" is not a standalone noun you would use in a diagnosis. The root may change form entirely when the suffix is added, which trips people up when they try to reconstruct terms from memory alone.
Practical Application and a Real-World Problem
Here is something I ran into repeatedly during transcription work. A physician would write "nasal" and another would write "narial." Both pertain to the nose, but "narial" is far less common in modern American clinical practice. When sorting and standardizing documentation, I had to decide which terms to flag for consistency. The workaround was straightforward: I built a reference list of acceptable -al variants by specialty. ENT documentation would accept "auricular" and "nasal," while dermatology notes would default to "dermal" and "epidermal." This cut down the back-and-forth clarifications by probably 60 percent within the first month of implementation. The key insight here is that the al suffix medical term is not just about definition. It is about consistency in clinical writing. Different departments have different conventions, and knowing which convention applies to which context matters more than memorizing the suffix itself.
Get the Full Details
Countering the Common Advice
Most study guides will tell you to memorize roots and suffixes separately and combine them. That approach works for building vocabulary, but it fails when you are reading actual patient charts. In practice, you are rarely parsing a term from scratch. You are recognizing it in context. A term like "gastrointestinal" contains the root strong"gastr-" and "intestinal", but nobody thinks of it that way when they read it. They process it as a single concept relating to the digestive tract. My recommendation is to learn the -al suffix by seeing it attached to roots in real clinical sentences rather than in isolation flashcards. You will internalize the pattern faster and retain it longer.
Limitations You Should Know About
The -al suffix has real limitations. It does not convey quantity, severity, or direction. Saying "hepatic" tells you something relates to the liver, but it tells you nothing about whether the liver is enlarged, inflamed, or failing. That is the job of other suffixes and adjectives layered into the full clinical term. Relying on -al alone to convey meaning is a fundamental error that can lead to misinterpretation in documentation review. Additionally, the suffix does not always behave predictably with every root. Some roots reject -al entirely in favor of -ary or -ous. For example, "pulmonary" (not "pulmonal") pertains to the lungs. "Venous" (not "venal") pertains to veins. "Venal" actually exists as a word, but it means something completely different — it relates to corruption or being open to bribery. That kind of collision between medical and non-medical vocabulary is exactly where things go wrong. If you need a comprehensive reference, the standard go-to remains Medical Terminology: A Living Language by Foster and Gremillion, along with the Fishman's Medical Terminology series. They cover the al suffix in context with enough clinical examples to make the pattern stick without needing to reference multiple sources.