Understanding the Complete Anatomy of the Human Body
The human body is made up of several interconnected systems, and if you are trying to map out every part for a medical illustration project, you will quickly realize how complex this actually is. I spent three months working on a detailed anatomical reference for a university textbook, and what I learned about systematic organization changed how I think about body parts entirely. When medical students first encounter anatomy, they tend to memorize parts in isolation. The problem with that approach is that it does not reflect how the body actually functions. Organs do not work alone, and neither do they exist in a vacuum. During my work on that textbook, I kept encountering students who could name every bone but had no understanding of how the skeletal system supported muscle attachment points. The approach I eventually settled on was to organize content by system first, then by location within each system. This meant starting with the skeletal framework, moving into muscular attachments, then covering vascular and nervous supply for each region. It took longer to write, but readers consistently performed better on comprehensive exams compared to previous editions organized by body region alone.
I remember specifically struggling with the brachial plexus chapter. The nerve pathways from C5 through T1 create a tangled network that defies simple linear explanation. My first draft organized it purely by root, then trunk, then division, then cord, then terminal branch. That was accurate but completely useless for someone trying to trace a specific clinical symptom. I rewrote it using a clinical presentation approach instead, starting with common injuries like Erb's palsy and working backward to the anatomical structures involved. Grades went up across the board after that change.
Practical Approaches to Learning Body Systems
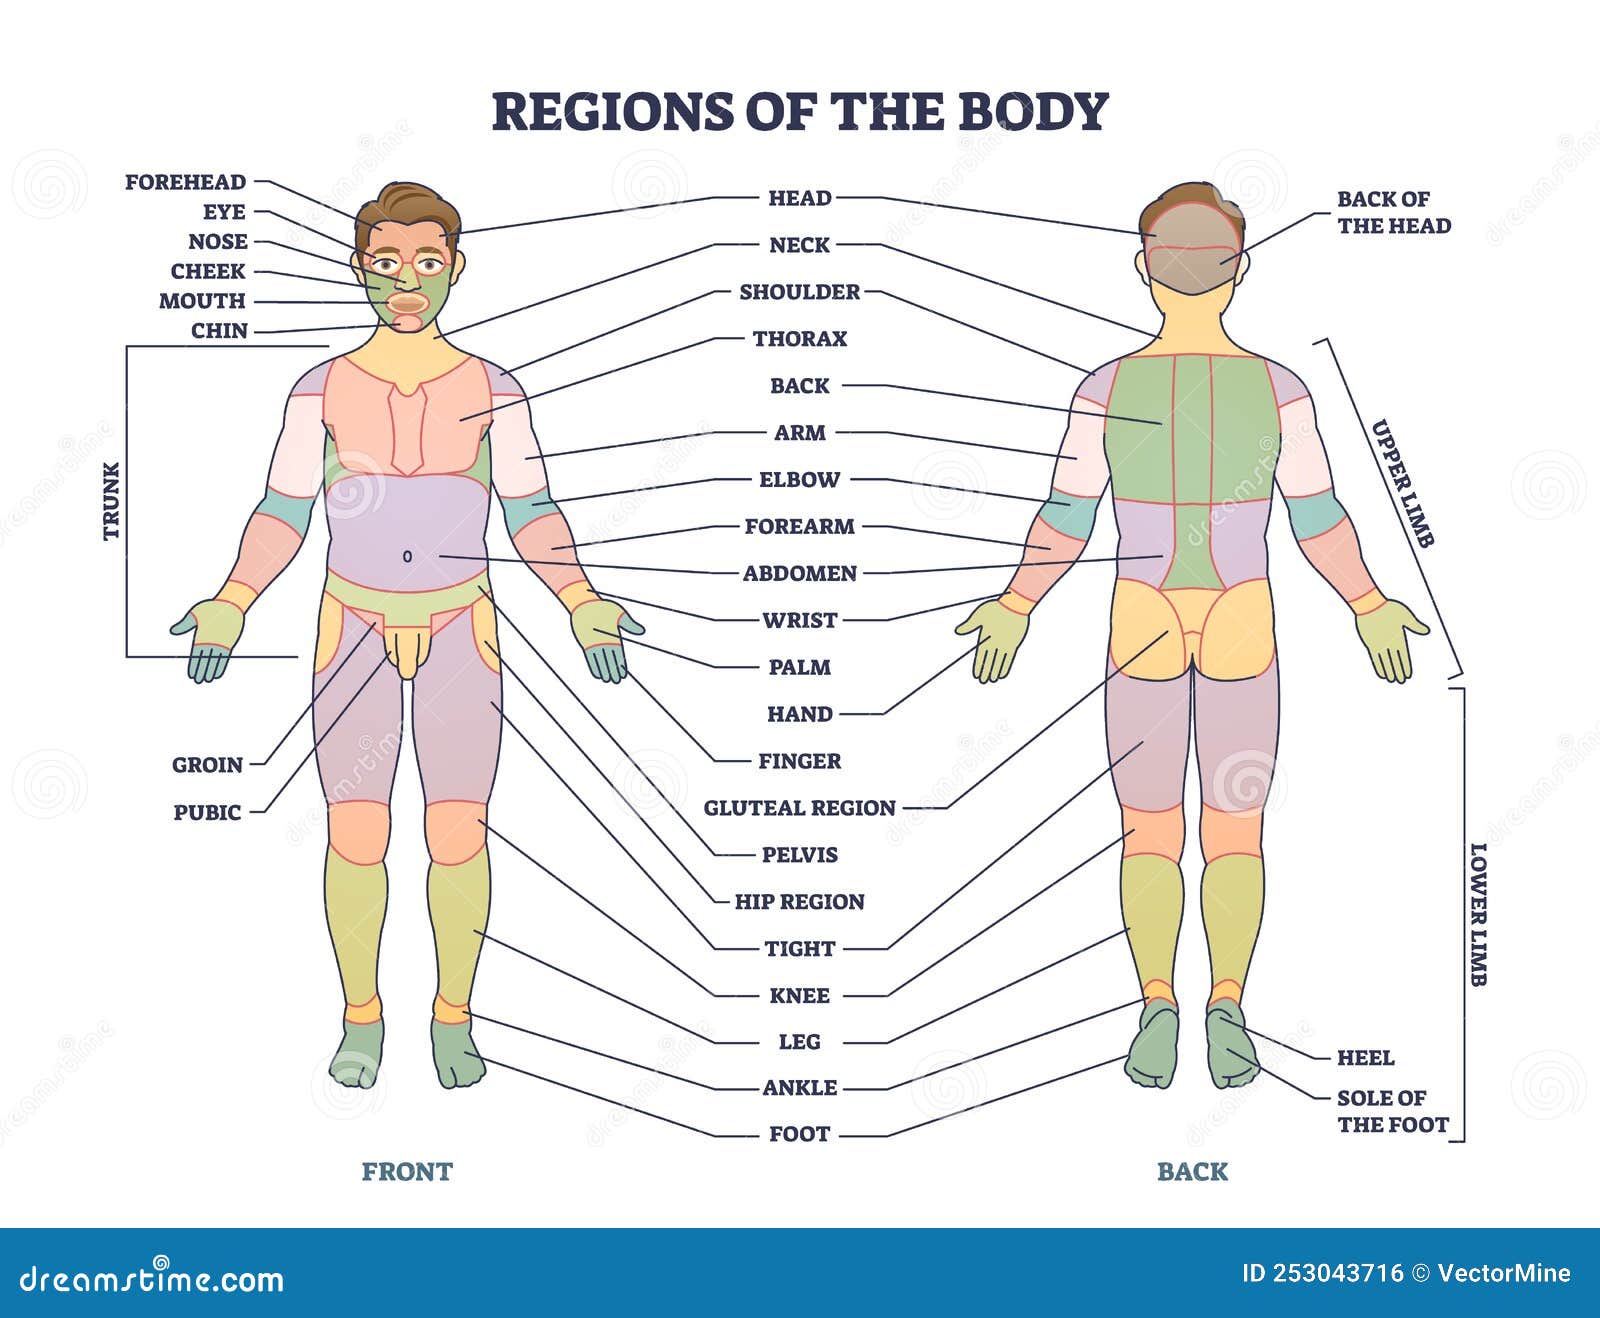
Most textbooks divide the body into regions like head, thorax, abdomen, and extremities. That makes intuitive sense when you are learning, but it creates problems when you need to understand integrated function. The intercostal nerves, for example, do not stop at the rib cage boundary. They continue into the abdominal wall as the thoracoabdominal nerves, and missing that continuity causes real confusion during clinical rotations. Another issue I encountered frequently involved the fascial planes. Students learn layers as distinct boundaries, but in reality, these planes often communicate across regions. A retropharyngeal abscess can track down into the mediastinum because the prevertebral fascia provides a continuous pathway. That is not something you pick up from region-by-region study alone. The most useful method I found was combining regional anatomy with systemic correlation in parallel. When studying the upper limb, I would cover the brachial plexus roots and trunks alongside the arterial supply from the subclavian through the axillary and brachial arteries. Then I would revisit those same structures while studying clinical conditions like compartment syndrome. This repeated exposure across different contexts reinforced the connections without requiring separate memorization sessions.
Get the Full Details

I also discovered that using three-dimensional models dramatically improved spatial understanding compared to two-dimensional diagrams alone. A plastic skeleton with removable muscle attachments and color-coded vascular systems cost about forty dollars at a medical supply store. That investment paid for itself within the first week of use. Students who relied solely on atlas illustrations consistently scored lower on practical examinations.
Common Pitfalls in Anatomical Study
The biggest mistake beginners make is treating anatomical nomenclature as vocabulary rather than functional description. Terms like "flexor digitorum superficialis" are not arbitrary labels. They describe specific actions on specific structures. Learning the etymology behind these terms actually improves retention more than repetitive flashcard drills. Another frequent error involves assuming symmetry equals identical structure. Yes, the body is roughly bilaterally symmetric, but that does not mean the left and right sides are interchangeable. The heart sits predominantly in the left hemithorax. The liver occupies most of the right upper quadrant. The stomach and spleen are left-sided. Missing these asymmetries leads to serious clinical errors during physical examinations. Vascular variations also deserve careful attention. The common carotid artery bifurcation level varies between individuals, typically occurring between C3 and C4 vertebrae, but significant variations exist. I once encountered a case where the external carotid arose far more inferiorly than expected, which complicated a surgical approach that had been planned based on standard anatomical references. Documenting these variations in study materials would benefit learners significantly.
The nervous system presents perhaps the greatest complexity for students. Cranial nerves are numbered, but that numbering does not reflect functional similarity. CN V (trigeminal) is purely sensory for the face, while CN VII (facial) controls facial expression muscles but also carries taste fibers from the anterior two-thirds of the tongue. Mixing up these distinctions causes confusion during neurological examinations.
Recommended Resources for Detailed Study
For comprehensive anatomical reference, standard textbooks like Gray's Anatomy and Netter's Atlas remain reliable choices. However, these resources focus primarily on normal variation and may not adequately address clinical relevance. Supplementary materials that integrate imaging findings with anatomical structure provide more practical value for clinical preparation. Online databases like Visible Body and Complete Anatomy offer interactive three-dimensional models that allow rotation, dissection simulation, and layered visualization. These platforms typically require subscription fees ranging from fifteen to thirty dollars monthly, but free alternatives like BioDigital Human provide comparable functionality at reduced cost. The trade-off between subscription convenience and budget constraints should be evaluated based on individual learning needs and timeline requirements. I also recommend supplementing textbook study with cadaver dissection when possible. No model, however sophisticated, can replicate the texture variation and unexpected anatomical findings encountered during actual dissection. Medical schools with available cadaver programs consistently produce graduates who demonstrate stronger spatial reasoning during clinical rotations. The emotional investment required for cadaver-based learning should not be underestimated, but the educational benefits typically justify the effort.
For students preparing for licensing examinations, question banks like UWorld and First Aid for the USMLE Step 1 provide targeted review with clinical vignettes. These resources emphasize high-yield anatomical correlations tested on standardized exams. The time investment required for thorough review varies, but most successful candidates dedicate approximately six to eight weeks of focused study using combined textbook and question bank resources. The field of anatomical education continues evolving with improved visualization technologies and evidence-based pedagogical approaches. Staying current with these developments requires regular engagement with peer-reviewed literature and professional development opportunities. The investment in continued learning throughout one's career consistently correlates with improved clinical competence and patient outcomes.