What Allscripts Professional EHR Actually Is
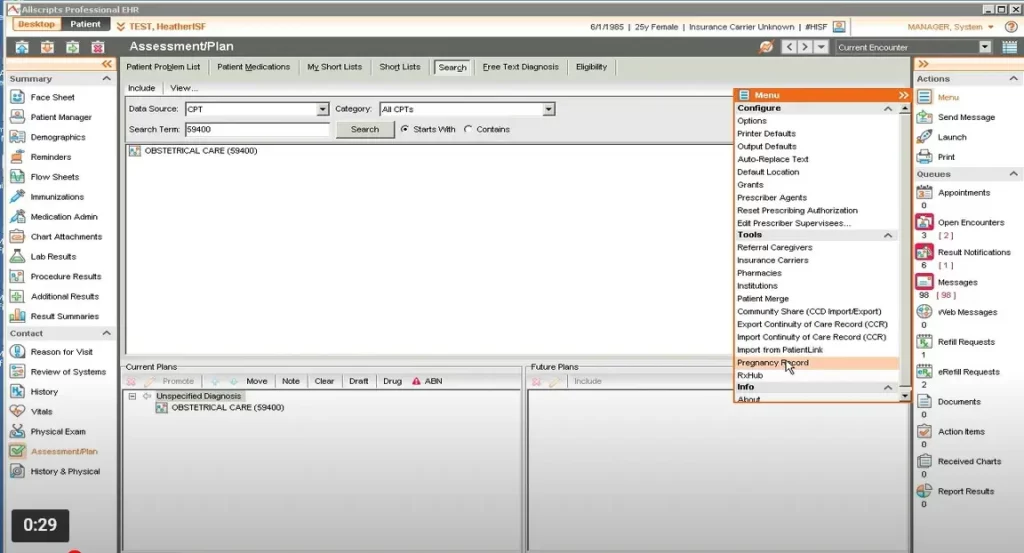
Allscripts Professional EHR was an ambulatory electronic health record system designed primarily for small to mid-sized physician practices. It combined practice management functions with clinical documentation, e-prescribing, and basic quality reporting. The product was rebranded and folded into the Allscripts Sunrise platform as the company shifted its strategy, but many practices ran on it for years and still rely on institutional knowledge about how it behaves. The system was never particularly elegant, but it was functional for practices that didn't require sophisticated specialty workflows. The official manual isn't freely hosted on a public page anymore. Allscripts (now Delphi Health Systems) archives documentation through their support portal, which requires a valid login credential tied to an active subscription. If your organization's contract is still live, you can access the documentation library at the Allscripts resource center. That is the only legitimate source. Third-party sites that claim to host PDF versions of the full manual are typically distributing outdated copies from 2018 or earlier, and some may embed malware. The manual was divided into several separate document files — one for clinical documentation, one for scheduling, one for billing integration, and a few others covering lab interfaces and reporting. These were not bundled into a single volume. Here is the thing about the Allscripts Professional manual that nobody really warns you about. The table of contents is almost useless for figuring out where a feature lives inside the actual application. The navigation structure of the software does not match the structure of the documentation. You will open the manual looking for something called a "medication reconciliation workflow" and find three pages that barely mention the term. The function is actually buried under a completely different label inside the application. I spent about forty-five minutes one afternoon chasing a feature that was documented under "clinical workflow templates" when the actual button was labeled "order sets." The manual references menu paths that exist in older versions but were moved or renamed in later service packs. Always verify the version number on your system before trusting any menu path listed in the documentation.
I also ran into a specific problem with the reporting module that took me two days to resolve properly. The encounter-based patient list report would repeatedly exclude patients who had visited within the selected date range. The cause was not a configuration error on my part. The filter was defaulting to include only patients with a complete date-of-birth field, and the practice had roughly sixty patients whose DOB was entered as an approximate year-only value during migration from paper records. The report simply skipped them. The workaround was to run a separate query using the patient demographic module to pull those incomplete records, then manually append them to the final report. There is no built-in toggle to override the DOB requirement in that particular report. I wrote down the workaround steps and posted them internally so other staff wouldn't repeat the same process when someone needed a clean patient list for a quality measure report. The clinical documentation side of the system had its own set of quiet limitations. Templates were highly configurable but required administrative-level access to create or modify. Most practices assigned one person to handle template changes, which created a bottleneck whenever a provider needed a new template built. The turnaround time averaged between two and four business days depending on how busy the administrative super-user was. Some providers simply stopped requesting new templates and adapted their documentation habits to fit the existing ones, which led to inconsistent charting across the practice. I found that the most efficient approach was to consolidate template requests into a single weekly batch email rather than submitting them ad hoc throughout the week. E-prescribing in Allscripts Professional worked adequately for standard prescriptions but had notable gaps. The integration with state PDMP databases varied significantly by jurisdiction and was not always reliable within the application itself. In our state, the PDMP query would time out intermittently, sometimes requiring a second attempt before returning results. When it failed, the fallback was to access the PDMP directly through the state's separate web portal. The manual mentioned this limitation briefly in a footnote on page 312 of the eRx section, which most users would never read. If your practice relies heavily on controlled substance prescribing, you should plan for a manual backup process regardless of what the documentation promises about seamless integration.
Lab interfaces were another area where the system showed its age. The lab inbox was functional but the layout made it difficult to distinguish between reflex orders and primary orders without clicking through each result individually. I trained two staff members to use color-coding shortcuts within the inbox view, which reduced the time spent reviewing daily lab results from about twenty minutes per person down to roughly seven. The system does not have a native color-coding feature for lab results, so this was a manual work practice we developed internally. If you are currently evaluating this system or trying to navigate an existing implementation, the manual is a reference tool rather than a learning path. It assumes you already understand the basic workflow of an ambulatory practice and the general layout of EHR software. It is not written for someone encountering an EHR for the first time. The glossary is thin, and the index cross-references are inconsistent. Pair the manual with hands-on training in a test environment, and keep a personal notes document where you record where features actually live versus where the manual says they live. That gap between documentation and reality is where most of your time will be spent in the first six months.
Get the Full Details