
Getting Through an AMS Call Without Missing the Details
Altered mental status is one of those presentations where everything feels urgent but nothing moves fast enough to matter. You walk into a room or pull up to a scene and the patient doesn't make sense, and every protocol wants you to follow a sequence you can't quite complete because they keep moving the goalposts. I learned pretty early that documenting whether someone is alert, verbal, or responsive is not the same thing as doing an Altered Mental Status Assessment. Anyone who has stood over a patient in a dimly lit hallway at 3 AM knows this. The difference between a good assessment and a bare-bones one comes down to pattern recognition and knowing which details actually move the needle.
What the Altered Mental Status Assessment Actually Looks Like
The standard framework starts with establishing a baseline and then working through a series of checks. Airway, breathing, circulation are always first, but the mental status portion is where most people slow down unnecessarily or rush through too fast. There is a middle ground. You begin by determining level of consciousness using AVPU or the Glasgow Coma Scale. AVPU is fast but crude. GCS gives you a number you can track over time. I use both. AVPU tells me whether to act now or investigate further. GCS tells me whether the situation is improving, staying the same, or getting worse. From there, you run through the standard history elements. SAMPLE gives you the past medical history, allergies, medications, past events, last oral intake, and signs and symptoms. The first three items in that sequence matter more than most clinicians realize because a missed medication or an undocumented allergy can redirect the entire workup.
I always check blood glucose before anything else related to mental status. Hypoglycemia mimics stroke, seizure, intoxication, and infection all at once. Skipping the glucose check is the single most common error I see in early-career providers. It takes thirty seconds and eliminates a whole category of differential diagnoses if it comes back normal.
Get the Full Details

What Beginners Miss
Most people treat AMS as a checklist. They move through GCS, vitals, glucose, and transport decisions as though the algorithm will protect them. It won't. The algorithm protects against missing obvious things. It does not protect against missing the subtle ones. One thing that catches people off guard is the difference between acute and chronic mental status changes. An elderly patient who lives with mild dementia may appear only mildly confused on arrival. Their baseline is already reduced. The real change is relative to them, not relative to a healthy person. Documenting this requires asking family or caregivers about the patient's usual state, which is often impossible in an emergency setting. When you cannot get that information, note the limitation clearly in your documentation so the receiving team understands the gap. Another issue is assuming intoxication is the cause simply because the patient smells like alcohol or has track marks. I had a call where a young male was found unresponsive in a parking lot. The obvious answer was opioid overdose. Naloxone did nothing. Glucose was normal. The real cause was early meningitis, and the delay in recognizing that cost us critical hours. The workaround was running the full differential even when the scene pointed clearly in one direction. Not every AMS case is what it looks like at first glance.
Tracking Changes Over Time
The value of an AMS assessment is not in the first number you write down. It is in the change between numbers. A patient who goes from a GCS of 14 to 12 over twenty minutes is deteriorating. A patient who goes from 14 to 13 over two hours may be stable enough for a longer observation period. Context matters more than the absolute score. I keep a simple running log during prolonged assessments. Time, GCS, glucose, blood pressure, oxygen saturation, and any interventions given. This log replaces the vague phrase "mental status unchanged" with actual data that a physician can use at handoff.
Pediatric and Geriatric Differences
Pediatric AMS presents differently than adult AMS. Young children do not localize pain the same way. They do not follow commands consistently even when healthy. Using an adult GCS framework on a three-year-old produces misleading results. The Pediatric Glasgow Coma Scale adjusts for these differences, but it is not widely used outside pediatric hospitals. Geriatric AMS often has multiple contributing factors. Urinary tract infections, medication interactions, dehydration, and hypoxia can all combine in ways that do not fit a single diagnosis. The assessment must be broader. You are not looking for one cause. You are looking for the combination.
Common Pitfalls and Limitations
One persistent problem is the assumption that a normal glucose reading rules out metabolic causes. It does not. Thyroid storms, hepatic encephalopathy, and electrolyte disturbances all produce altered mental status without affecting blood sugar. The glucose check is a screen, not a diagnosis. Another limitation is the difficulty of assessing patients who are nonverbal due to intubation or language barriers. In these cases, the GCS verbal component cannot be accurately scored. You note the limitation in your documentation and rely more heavily on motor and eye-opening responses. This introduces subjectivity, so consistency in how you assess becomes critical. Some protocols recommend CT imaging for all AMS presentations above a certain severity threshold. In practice, this leads to unnecessary scans and longer ED stays for patients who will stabilize with observation alone. The threshold should be guided by clinical trajectory, not just the initial GCS score.
Practical Steps for Field Assessment
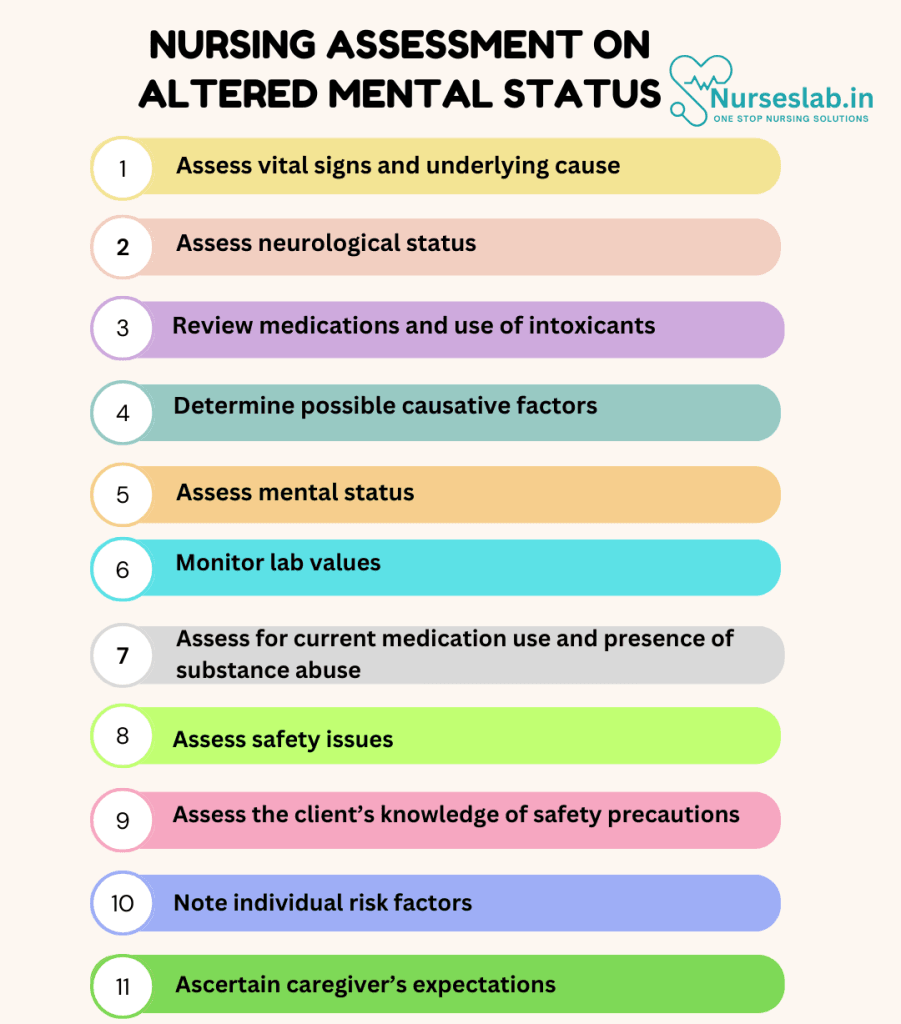
The assessment (process) in a typical prehospital or urgent care setting follows a fairly consistent path, but the order in which you execute the steps depends on the situation. Step one is scene safety and personal protection. Do not skip this. I have seen clinicians get too close to a patient with unknown drug exposure or active agitation without proper barrier protection. You cannot help someone if you become a second patient. Step two is establishing consciousness level. Use AVPU for speed. If the patient is not fully alert, move to GCS immediately.
Step three is checking blood glucose. Point-of-care testing takes under a minute. If the result is abnormal, treat according to protocol and reassess. Improvement after correction supports hypoglycemia as a contributing factor, though it may not be the only factor. Step four is obtaining vital signs and oxygenation status. Hypoxia and hypercapnia are reversible causes. Correcting oxygen delivery can improve mental status faster than almost any other intervention. Step five is gathering history from available sources. Family members, bystanders, medical alert bracelets, and medication bottles on the patient or at home can all provide clues. I once identified a digoxin toxicity case simply by reading the label on a bottle in the kitchen. The patient had been taking double the prescribed dose due to confusion about timing.

Step six is performing a focused physical exam. Pupillary response, skin temperature and moisture, signs of trauma, and neurological screening all contribute to the differential. A sudden headache with neck stiffness and fever points toward meningitis. A unilateral weakness with facial droop points toward stroke. These patterns matter more than any single number.
Documentation Standards
Documentation is where most AMS assessments fall apart. Writing "altered mental status, no focal deficits" tells the receiving provider almost nothing. A useful note includes the GCS components broken down individually, the glucose value, the oxygen saturation on room air or supplemental oxygen, the blood pressure trend, and any interventions given with the patient response. I also note the environment and circumstances. A patient found down in a heated home in winter is a different picture than a patient found down in an unheated garage. Temperature regulation affects mental status significantly, and that context is often missing from charts. When the assessment is incomplete due to patient agitation or combativeness, document why. "GCS could not be fully assessed due to agitation" is honest and useful. "GCS 15" on a combative patient who refused examination is misleading and potentially dangerous.
When the Assessment Leads Nowhere
Sometimes you complete the full workup and find nothing. The glucose is normal. The oxygenation is adequate. The vitals are stable. The neurological exam shows no focal deficits. The patient remains confused or lethargic with no clear explanation. This is not a failed assessment. This is a valid finding. Some causes of AMS remain unidentified in the prehospital or emergency department setting, and that is acceptable. What matters is that you documented the process thoroughly enough for the next clinician to continue the workup without starting over. The alternative is leaving the patient with an incomplete assessment and hope that someone else figures it out later. That is how complications get missed.


