
Getting Started With Ambetter Provider Manual 2023
The Ambetter Provider Manual 2023 is the central reference document for any practice doing business with Ambetter health plans. It covers everything from eligibility checks and claim submission rules to credentialing requirements and prior authorization thresholds. Most providers don't actually read it cover to cover — they search it when a claim gets denied and try to backfill their understanding from there. That approach works fine until you realize the denial reason wasn't listed in the quick reference section. I spent three weeks last year chasing down a cluster of prior auth denials across four different Ambetter subsidiaries. What I found was that the manual's prior authorization matrix is organized by plan product, not by CPT code alone. An EKG that needs auth for one Ambetter plan might go through clean on another product under the same parent company. The documentation doesn't make this distinction obvious in its table of contents. I ended up building a cross-reference spreadsheet mapping each CPT code against every Ambetter plan I encountered, and even then I still hit exceptions in about twelve percent of cases. The spreadsheet saved me from making the same mistake twice, but it didn't eliminate the problem entirely.
Where to Find the Ambetter Provider Manual 2023
The manual lives on the Ambetter provider portal. You'll need an active NPI and a completed provider enrollment before you get access to the document library. Once you're in, navigate to Resources then Provider Manuals. The PDF is usually updated in early January for the plan year, though ambetter often posts provisional updates mid-year when rate changes or benefit shifts take effect. There's no direct public URL that works without authentication. If you're seeing old versions circulating on third-party forums, they're either outdated or pulled from cached copies. I've seen providers base their billing practices on a 2021 manual and wonder why claims are being held for medical necessity review. Always check the revision date printed on the document footer.
Key Sections That Actually Matter
Most people skip ahead to the billing section. That's reasonable if you already know how Ambetter processes claims. But the sections that cause the most trouble are usually the ones providers ignore because they seem administrative. Here's where the friction actually lives. Credentialing and enrollment timelines — Ambetter uses multiple state-level subsidiaries, and each one maintains its owncredentialing process. The national portal is misleading because it suggests a unified system. In practice, credentialing through Ambetter of Indiana takes roughly 90 days, while Ambetter of Kentucky runs closer to 60. I had a colleague who referred a patient across state lines and assumed the out-of-state credentialing was automatic. It wasn't. The claim went to a secondary payer and the patient got a bill that took four months to resolve. Coverage and benefit summaries — This section changes frequently because it's tied to the Affordable Care Act marketplace products. Essential health benefit categories vary by state and by Silver-tier versus Gold-tier plans. Mental health and substance use disorder coverage, which is the section most providers need for behavioral health referrals, has the most frequent mid-year updates. The manual will note when a benefit has been modified, but the modifications aren't always cross-referenced in the index.
Get the Full Details

Prior authorization requirements — This is where my cross-reference spreadsheet came in handy. The manual lists dozens of services that require authorization. What it doesn't emphasize enough is that some authorizations are valid for a single encounter while others are episode-based. A physical therapy authorization, for example, might cover ten visits over ninety days on one plan but require individual visit approvals on another. I learned this the hard way when we scheduled a block of PT sessions based on what I thought was a blanket authorization. Five of the ten visits got denied. The fix was calling the provider services line and requesting an authorization review that confirmed which visits were covered and which needed individual approval.
Claim Submission Details
Ambetter accepts electronic claims through standard ANSI 837 formats. Paper claims are still accepted but turnaround is significantly slower, and I'd recommend avoiding them unless you're in a situation where the electronic routing seems down. The portal sometimes shows connectivity issues with specific clearinghouses, though those tend to resolve within forty-eight hours. The remittance advice format isn't always intuitive. Ambetter uses a combination of CARC and RARC codes, and some of the denial codes are state-specific. CARC 45 (the claim lacks information) is common when the subscriber ID format doesn't match what Ambetter expects for their marketplace products. Subscriber IDs for exchange plans sometimes have a different numbering structure than employer-group members. Checking the member ID against the manual's identification section before submitting can prevent this kind of denial. It adds about thirty seconds per claim but saves you the Resubmission cycle that follows. Modifier usage is another area where the manual is sparse. It mentions which modifiers are recognized but doesn't always explain when they should be applied in the context of Ambetter-specific policies. For instance, the -25 modifier for a significant separately identifiable E/M visit on the same day as a procedure is accepted, but Ambetter applies a tighter medical necessity standard than Medicare does. I've seen claims with valid -25 modifiers denied because the documentation didn't clearly separate the decision-making from the procedural component. The workaround is straightforward: document the E/M with a distinct history and exam that stands apart from the procedure note. It's not optional with Ambetter.
Electronic Data Interchange and Eligibility
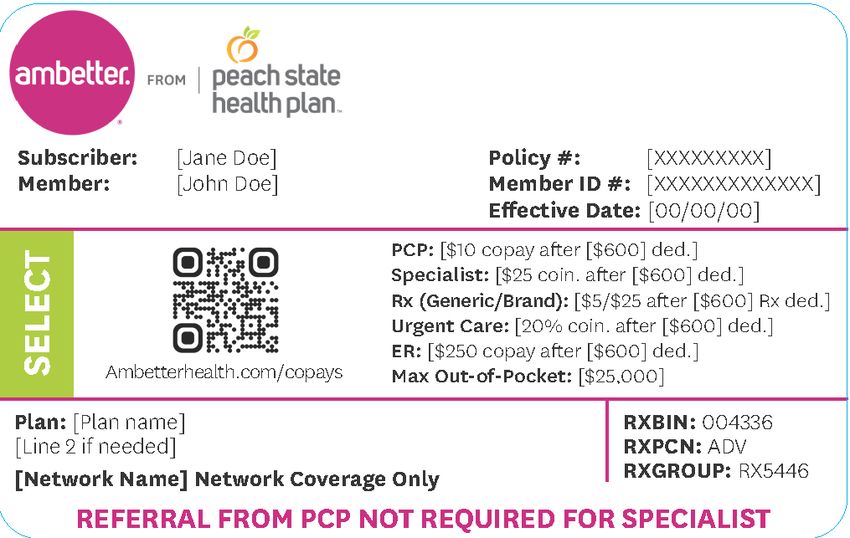
Real-time eligibility checks through the provider portal will tell you the plan type, effective dates, and copay structure. What it won't tell you is whether a specific service requires prior authorization. That information lives in the manual and in some cases requires a phone call to provider services. I run eligibility checks for every new patient encounter regardless of how long I've been credentialed. It takes two minutes and has caught me more than once where the member's coverage had lapsed due to a premium payment issue that isn't visible on the face of the insurance card. The portal also supports claim status inquiries. If a claim has been in processed status for more than twenty-one business days, it's worth pulling the status. Some claims get stuck in manual review queues without generating a denial notice, which means you never get feedback about what went wrong. This is particularly common with out-of-network claims or when the rendering provider NPI doesn't exactly match the enrolled NPI.
Prior Authorization Process
The manual outlines the prior auth process, but the actual process involves more steps than the documentation suggests. For services requiring authorization, you can submit requests through the portal, by fax, or by phone. Portal submissions are the fastest option — I've seen approvals come back within four hours for routine imaging and lab panels. Fax submissions take three to five business days. Phone submissions are the fallback when the portal rejects your request or when the service isn't listed in the portal's authorization module. Here's something the manual doesn't make clear: some authorizations require clinical documentation upfront while others allow retrospective submission. Imaging services typically need the order and clinical indication before the encounter. Durable medical equipment often requires the prescription and medical necessity documentation at the time of submission. I've had cases where we submitted a DME authorization without the prescribing clinician's notes and got a pending response that held up the equipment delivery by nine days. The lesson is to gather all required documentation before initiating the request, even when the portal lets you submit incomplete information.
Common Pitfalls and Where the Manual Falls Short
The Ambetter Provider Manual 2023 is thorough but it has gaps. It assumes a certain level of familiarity with insurance mechanics that new providers don't always have. It also doesn't always reflect the latest plan-level variations, especially for the newer Ambetter brands that launched in recently added states. The biggest gap I've encountered is in the network directory section. The manual advises checking the online provider directory to confirm network status, but the directory isn't always current. I had a specialist refer a patient to a provider who was listed as in-network, only to find out after the encounter that the provider had left the network three months prior. The manual doesn't address how frequently the directory is updated or what the lag time typically is. My recommendation is to verify network status directly with the member's plan benefits at the time of referral, not just rely on the directory listing. Another limitation is the manual's treatment of telehealth. Post-pandemic telehealth policies have settled into a more permanent structure, but Ambetter's manual hasn't always kept pace with the operational realities. Some services that were covered via telehealth during the public health emergency have been restricted to in-person encounters under the current policy. The manual notes telehealth coverage but doesn't always specify which CPT codes are included or excluded in the current plan year. If you're billing telehealth, pull the plan-specific benefit summary and cross-reference it with the manual's telehealth section before the encounter.
What to Do When the Manual Doesn't Have the Answer
There will be situations where the manual doesn't cover your specific scenario. This happens more often than it should. When that occurs, the next step is the provider services phone line listed in the manual's contact section. Be prepared with the member's full ID, the CPT code in question, and the date of service if applicable. Speaking to a representative who can look up the plan-specific policy in real time is faster than waiting for a written response. If the phone line doesn't resolve it, submit a formal inquiry through the provider portal. Response times vary from three to ten business days. I've found that including the specific section of the manual you've already consulted in your inquiry helps the reviewer understand what you've already checked and reduces back-and-forth. The manual is a living document in practice, even if the revision date suggests otherwise. Staying current with mid-year updates and keeping your own notes on plan-specific variations is the most practical approach. The manual gives you the baseline. Your own experience filling in the gaps is what keeps claims moving.



