What People Actually Mean When They Criticize the American Cancer Society
The American Cancer Society is one of the oldest and most visible organizations in the oncology world. That visibility naturally draws scrutiny. American Cancer Society Criticism generally falls into a few buckets: screening guideline changes, marketing messaging, fundraising efficiency, and advocacy positions. The criticism isn't always evenly distributed either. Some of it comes from medical professionals, some from patients, and some from industry competitors. It helps to know which bucket you're looking at before you treat every complaint as the same thing. I spent years working with clinical research sites that had to comply with ACS guidelines for cancer detection programs. The friction wasn't usually about the mission. It was about the gap between national screening recommendations and what actually happens in underserved communities. The ACS publishes clear guidelines for mammography, colonoscopy, and HPV testing. The problem is those guidelines assume a baseline of healthcare access that a significant portion of the population doesn't have. I saw this firsthand when our site in Alabama struggled to meet the recommended colon cancer screening rates for Medicare patients over 75. The ACS guideline says shared decision-making for that age group, but the patients I worked with had never had a colonoscopy and most of their doctors had never offered one. The guideline felt abstract.
American Cancer Society Criticism
The most common thread in public criticism is that the ACS sometimes appears to prioritize awareness campaigns over structural change. Raise the curtain, sell the pink ribbon, fund the research. That model works well for donations. It doesn't solve the problem that late-stage cancer diagnoses are still far too common in rural counties with no oncologist within a hundred miles. Some critics argue the organization benefits financially from the fear and urgency its campaigns generate. That's a fair charge if you look at their nonprofit financials. The ACS spends a significant portion of its budget on advocacy and public education, which is fine for a lobbying organization. It's less fine if you believe that money would save more lives if redirected entirely toward direct patient services or research funding. There's also the matter of screening guideline revisions. In 2018, the ACS lowered the recommended starting age for colorectal cancer screening from 50 to 45. This was based on a documented rise in early-onset colorectal cancer. The change was scientifically justified. The backlash was immediate and loud. Some patient advocates felt the organization was creating panic. Others in the medical community felt it came too late, since the US Preventive Services Task Force hadn't yet aligned with the same recommendation. What most people missed in that debate was that the ACS actually recommends different starting ages for different cancers. Mammography screening starts at 45 now, with a choice between annual or biennial. Lung cancer screening starts at 50 with a 20 pack-year smoking history. These aren't arbitrary numbers. They're derived from modeling studies that balance false positives against mortality benefit. The public doesn't always get that context. Another area where criticism holds weight is the way the ACS handles alternative therapy claims. The organization has publicly pushed back against supplements and diets promoted as cancer cures. That stance has drawn criticism from both sides. Naturopathic practitioners say the ACS dismisses integrative approaches too quickly. Conventional oncologists sometimes say the ACS doesn't push back hard enough on fringe treatments. I ran into this repeatedly when patients would show up to clinical trials with bloodwork ruined by high-dose antioxidant supplements they'd been taking "naturally." The supplements interfere with chemotherapy and radiation efficacy. The ACS position is correct from an evidence-based standpoint. The communication around it is often clumsy. They tell patients what not to do without giving them a practical replacement strategy. That's a failure of messaging, not of science.
The fundraising angle deserves its own look. The ACS runs the Relay For Life event, which is one of the largest fundraising phenomena in the charity world. It raises real money. It also raises real questions. Event costs can eat into the percentage that actually reaches research and patient services. Some chapters report that only 60 to 70 percent of Relay For Life proceeds go directly to programs. The rest covers venue rentals, permits, marketing materials, and staffing. That's not unusual for any large nonprofit event. It's just not always transparent about it. I encountered a specific edge case that illustrates how these criticisms play out in practice. A patient I worked with had been told by her oncologist to enroll in an ACS-supported clinical trial for breast cancer. The trial required frequent imaging and lab work at a specific research site. She lived three hours away. The ACS covered travel reimbursement up to a point, but the documentation process was tedious and inconsistent across different trial sites. Some sites approved reimbursement within a week. Others dragged it out for months. The patient dropped out of the trial because she couldn't sustain the logistics. The ACS didn't fail her because of bad science. It failed her because of bureaucratic fragmentation. That's a structural problem that criticism rarely addresses productively. There's also the question of cancer registry data. The ACS collaborates with the CDC and the National Cancer Institute on the SEER program, which tracks cancer incidence and survival rates. This data is invaluable. It's also subject to manipulation and misinterpretation. Survival statistics are particularly misunderstood. Five-year survival rates sound like a guarantee. They're not. They're a statistical measure based on historical data that lags behind current treatment advances by several years. I've seen physicians use ACS survival data incorrectly when counseling patients because the numbers on the ACS website aren't updated in real time. That's not the ACS's fault entirely, but the organization could do more to emphasize the limitations of its own published statistics.
Get the Full Details

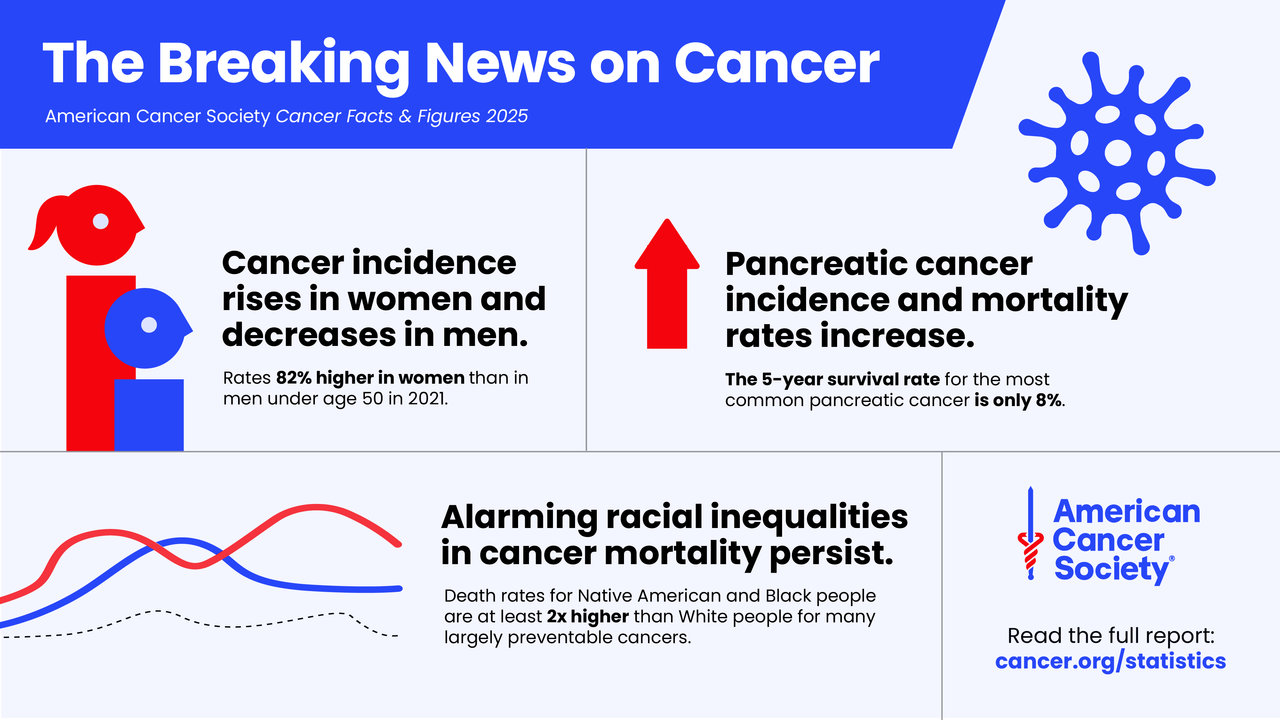
The advocacy position is where things get politically complicated. The ACS lobbies for tobacco control legislation, which is widely supported by medical organizations. They also advocate for patient rights and insurance coverage for cancer screenings. These are reasonable positions. But the organization has also taken stances on broader public health issues that some supporters and donors disagree with. When a charity takes a political position, it alienates part of its base. That's the nature of advocacy. The criticism here is less about the merits of the positions and more about whether a charitable organization should be spending resources on political lobbying at all. It's a valid debate. If you're evaluating the ACS and you want to cut through the noise, look at their annual report on cancer facts and figures. It's their most substantive publication. The data is generally accurate and peer-reviewed. Cross-reference their screening statistics with SEER data and you'll find they're mostly aligned. Where they diverge is in the policy recommendations, which are inherently subjective. The organization is not a research institution first. It's a nonprofit advocacy and service organization. Judging it purely on scientific output is the wrong framework. Judging it purely on donation efficiency ignores the value of its public health infrastructure. Both frameworks miss something important. The practical takeaway is that the American Cancer Society Criticism you encounter online is rarely about one thing. It's usually about the tension between being a charity that needs to raise money and an organization that makes evidence-based medical recommendations. Those two roles don't always sit comfortably together. The criticism is a symptom of that tension, not necessarily a sign that the organization is failing at its core mission. The question is whether the mission is being served efficiently enough. That's harder to answer and it requires looking past the headlines.




