Why the ADA guidelines are harder to follow than they look on paper
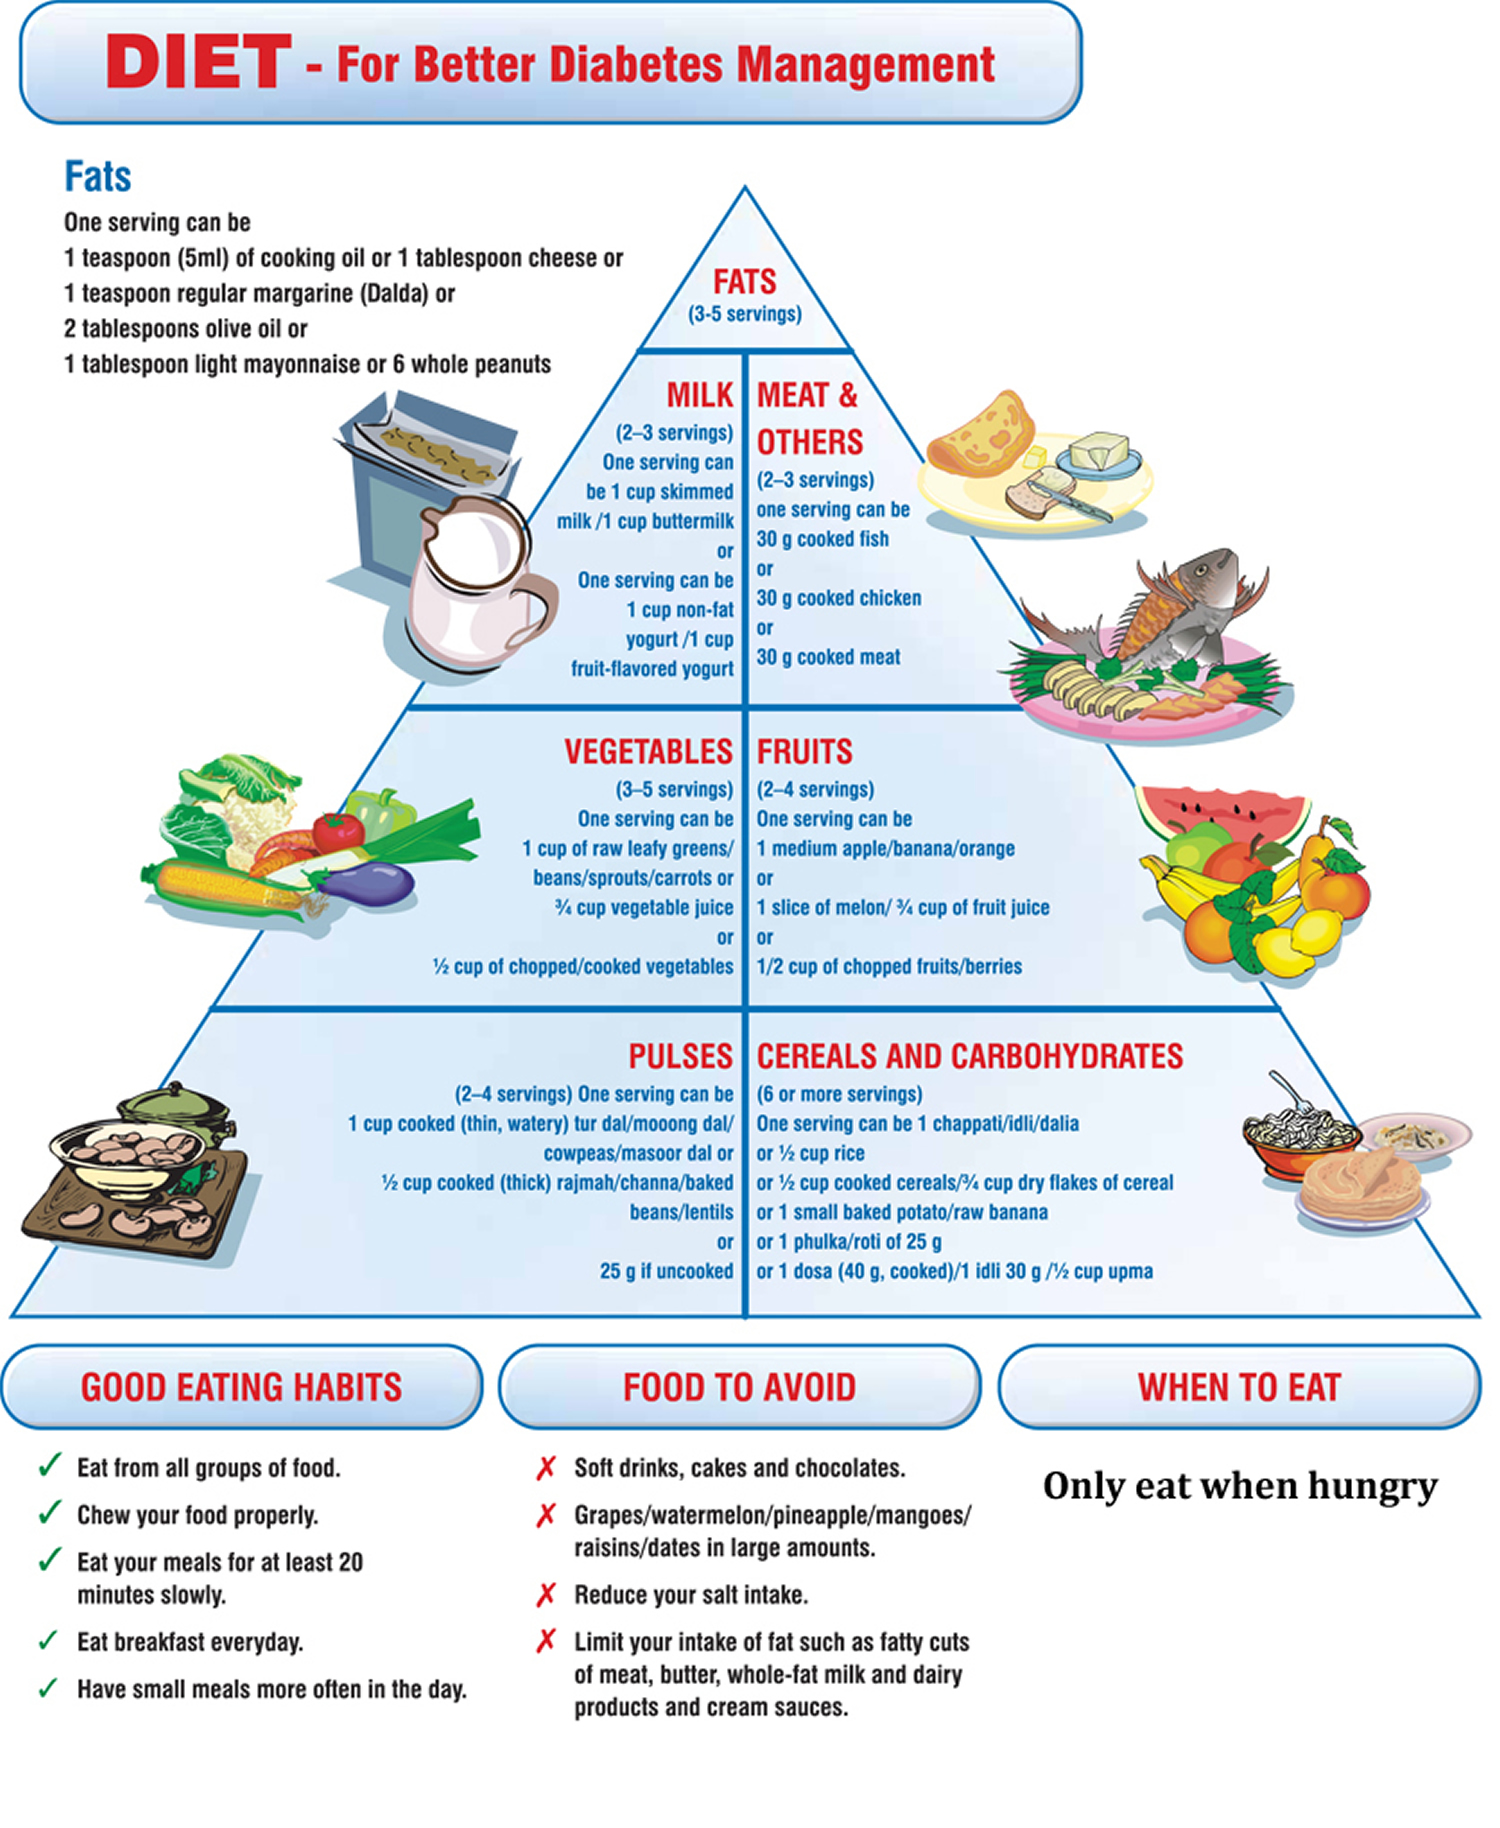
I spent about four years working with clinicians who prescribed diabetes nutrition plans. What I learned quickly is that the American Diabetes Association Diet Guidelines are less of a rigid protocol and more of a flexible framework. That distinction matters because patients treat it like a recipe when it was never designed to be one. The guidelines have gone through multiple revisions since 2019, shifting from a one-size carb counting model toward individualized medical nutrition therapy. If you're actually trying to apply these guidelines to real people instead of flashcards, there are some messy details the summary sheets don't cover. At their core, the current ADA recommendations focus on three things: carbohydrate management, meal timing consistency, and food quality over calorie restriction alone. The official stance is that there is no single ideal percentage of calories that should come from carbohydrates for all people with diabetes. This was a major shift from earlier guidance and it confuses a lot of patients who expected a straightforward number. Instead, the ADA recommends working with a registered dietitian to determine a personalized carb target, generally landing somewhere between 45 and 60 grams per meal for most adults on standard medication regimens, but that number can drop to 20 to 30 grams for someone on insulin with significant insulin resistance. The fiber recommendation is specific: at least 14 grams of fiber per 1,000 calories consumed. Most patients I encountered were getting roughly half that amount. The protein guidance has also evolved. It used to be a blanket suggestion of 15 to 20 percent of total calories. Now the ADA acknowledges that higher protein intakes around 20 to 30 percent may benefit certain patients, particularly those with prediabetes or early type 2 diabetes who need satiety support, but this can strain kidneys in patients with existing nephropathy. That nuance is easy to miss if you're just copying a generic meal plan.
Here is a practical problem I ran into repeatedly that almost no summary guide mentions. A patient came to me who was tracking food using standard USDA database entries and hitting his carb targets perfectly on paper, yet his postprandial glucose readings were spiking to 210 milligrams per deciliter after meals he considered "safe." The issue turned out to be food matrix effects. The same 30 grams of carbohydrate from steel-cut oats produced a significantly different glycemic response than 30 grams from white rice, even though the database listed them as nearly identical carb counts. The American Diabetes Association Diet Guidelines acknowledge this indirectly through their emphasis on whole foods, but they don't give clinicians a practical tool to explain why two foods with the same carb count behave differently. My workaround was introducing the patient to pairing every carb source with at least 10 grams of protein or 5 grams of fat, which consistently flattened those post-meal spikes without requiring a change in actual carb amounts. It saved us both months of frustration.
The execution problems nobody talks about
Carbohydrate counting sounds straightforward until you try to do it outside your own kitchen. Restaurant menus rarely list carb counts, and even when they do, the numbers are frequently wrong. I had a patient who switched from calculating his own meals to relying entirely on restaurant nutrition information and saw his A1C climb from 6.8 to 7.4 over six months simply because the listed values underestimated actual carb content by roughly 25 to 40 percent on pasta and sandwich items. The ADA guidelines expect patients to make informed choices in environments that are structurally hostile to that kind of precision. Another counter-intuitive detail is how the guidelines treat fruit. The older diabetes nutrition dogma treated fruit as something to limit aggressively. Current ADA guidance actually encourages whole fruit consumption because the fiber content and polyphenol profile change the metabolic response entirely. One small study I remember reviewing showed that replacing a refined carb snack with a comparable carb portion of whole berries actually improved postprandial glucose curves in type 2 diabetic patients. The fructose in whole fruit does not behave the same way as added sugar because the cellular structure forces a slower digestive release. This is the kind of thing that contradicts what patients learn in basic diabetes education classes, which often still run on outdated material. The alcohol guidance is another area where the guidelines fall short in practice. The ADA states that alcohol can cause hypoglycemia, especially with sulfonylureas and insulin, but it does not provide clear thresholds for safe consumption across different medication types. A patient on metformin alone might tolerate a glass of wine without issue, while someone on glipizide could drop dangerously low from the same amount. I learned this the hard way when a patient dismissed his evening hypo episode as just feeling tired because the guidelines never gave him a concrete warning about his specific medication combination.
Get the Full Details

Where the guidelines actually break down
The ADA framework works reasonably well for newly diagnosed type 2 patients who are motivated and have access to consistent grocery shopping and meal prep time. It performs poorly for people who work multiple jobs, lack reliable cooking facilities, or have food insecurity. The guidelines assume a level of lifestyle stability that simply does not exist for a large segment of the diabetic population. When I worked with community health clinics, I watched time and again how patients who could not maintain consistent meal timing would spiral into variable glucose patterns that no carb counting system could stabilize. There is also a genuine limitation in how the ADA addresses cultural food patterns. The guidelines are built largely around Western dietary norms. For patients whose traditional cuisine relies heavily on rice, tortillas, or other high-glycemic staples, the recommendation to simply "choose whole grains" can feel dismissive. A practical modification I found useful was working with patients to identify the specific cultural dish causing the spike, then adjusting the medication timing or insulin dose to match that predictable pattern rather than trying to eliminate the food entirely. This approach aligns with the ADA's general philosophy of individualization, even if the published guidelines do not spell out that particular application clearly. The guidelines also underweight the role of eating order, sometimes called nutrient sequencing. Research published in recent years shows that consuming vegetables and protein before carbohydrates in a meal can reduce postprandial glucose excursions by roughly 30 to 40 percent compared to eating the same foods in a mixed or carb-first sequence. The ADA has acknowledged this emerging evidence but has not yet integrated it into formal recommendation language. For patients who struggle with carb counting, eating order can be a simpler behavioral lever that produces measurable results without requiring any change in food selection or portion calculation.
What to actually do with this information
If you are managing diabetes and want to use these guidelines effectively, the most useful step is securing a medical nutrition therapy session with a registered dietitian who understands diabetes specifically. General dietitians often default to outdated carb restriction models. Ask them about your medication-specific food interactions before committing to any meal plan. The guidelines themselves are freely available on the diabetes.org website under the clinical practice recommendations section, but reading them raw without context will leave you with more questions than answers. The document is dense and occasionally internally contradictory because it represents a compromise across multiple specialty viewpoints. For most people, a reasonable starting point is tracking your actual glucose response to common foods for one week using a continuous monitor or fingerstick checks at one hour and two hours post-meal. The data you collect will likely show you that your personal carb tolerance varies by food source, by time of day, and by what you ate earlier in the day. The American Diabetes Association Diet Guidelines provide the conceptual foundation for understanding these patterns, but they do not replace the need to observe your own body's responses. That gap between the framework and real-world application is where most patients get stuck.




