Working With Drug Use Data Across Decades
I spent roughly three years building a timeline of substance abuse patterns for a state health department project. The work was boring in the best way. It involved digging through NSDUH archives, cross-referencing DEA seizure reports, and figuring out why 2009 data suddenly looked different from 2010 in ways that had nothing to do with actual usage changes. Most people think of drug use history as a sequence of moral panics. The crack epidemic of the eighties, the opioid crisis starting around 2010, the meth waves of the early twoThousands. Each one gets labeled and then forgotten until the next one arrives. The reality is messier. Usage patterns overlap, regions diverge, and the data quality varies wildly depending on which survey you are looking at and what year it covers. The main sources anyone should know are the National Survey on Drug Use and Health, the Monitoring the Future survey, and the Arrestee Drug Abuse Monitoring program, though ADAM ended in twentyOne. Each has different coverage, different question wording, and different biases. NSDUH uses household sampling, which misses incarcerated populations and homeless users. Monitoring the Future tracks adolescents and young adults but stops around age twentyEight. The gaps between surveys are where most errors creep in.
I learned this the hard way when a colleague told me heroin use had dropped forty percent between two survey years. The data was technically correct. What actually happened was a question wording change that made former users more reluctant to admit recent use. The trend was real in the dataset. It was not real in the population.
The Patterns Nobody Talks About
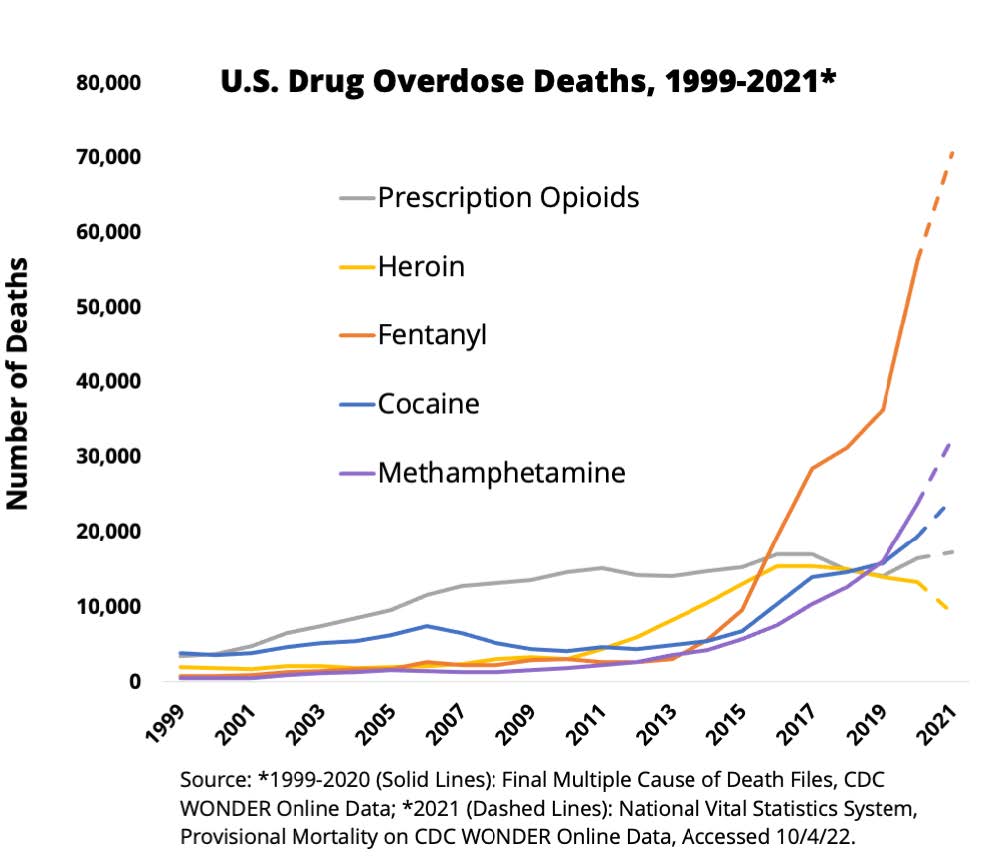
There is a counter-intuitive finding buried in the twentyYear-plus data that almost no one mentions. Prescription opioid abuse did not cause the current overdose crisis by itself. The shift from prescription pills to fentanyl was faster than anyone predicted, and the data trails show a clear inflection point around twentySixteen that coincides with changes in pharmaceutical manufacturing, not changes in doctor prescribing habits alone. Beginners often miss this because they look at mortality numbers without accounting for the supply-side changes. Another thing people get wrong is the regional variation in stimulant use. What looks like a national epidemic in aggregate data often masks sharp geographic differences. Meth abuse concentrated in the Midwest and rural areas while cocaine use remained stable in urban centers. The national average smoothed over patterns that mattered for intervention design. I ran into a specific edge case when trying to reconcile prison admission data with community survey results for a single county. The surveys showed declining cocaine use while arrests for possession spiked. The workaround was simple: check the local enforcement priorities and the charging statutes. Prosecutors had shifted from low-level possession to trafficking charges, which meant more arrests but not necessarily more users. The raw numbers looked alarming. They reflected policy changes, not usage changes.
Get the Full Details

How to Actually Read This Data
Start with the survey methodology, not the headline numbers. NSDUH changed its sampling frame in twenty eighteen to include cells and correctional facilities, which meant the data from that year onward is not directly comparable to earlier years. If you are building a timeline, flag that breakpoint explicitly. Do not smooth over it. Use multiple data sources to triangulate. The DEA National Forensic Information System shows seizure data, which reflects supply and enforcement priorities. The CDC WONDER database shows mortality, which captures the worst outcomes but misses nonfatal overdoses. The Hospital Emergency Department Surveys from SAEM show acute care visits. Cross-referencing these usually reveals discrepancies that raw numbers hide. This usually takes about three to four hours per region for a decent reconciliation, depending on your access to raw datasets. Watch for question wording changes. The 2015 NSDUH added MDMA to its stimulant module, which meant the data from that year shows higher rates than earlier surveys. The change was in the instrument, not in actual use. Anyone building a comparison chart should note this explicitly in the methodology section. Do not assume consistency across survey cycles without verifying the question modules.
The limitations are real. Household surveys miss incarcerated users, who have significantly higher substance use rates than the general population. Self-reporting bias means undercounting, especially for stigmatized substances. The data from the twentyTeens shows higher rates of opioid use disorder than the nineties, but the diagnostic criteria expanded, which inflated the numbers somewhat. Do not pretend these datasets capture the full picture. If your goal is understanding current patterns rather than historical ones, consider supplementing with wastewater epidemiology data, which has become more available since twentyTwenty. It shows community-level drug presence independent of survey response rates. The tradeoff is that it does not break down by demographics, so you lose the age and gender patterns that surveys provide. The core problem with studying drug use history is that each decade gets reframed. The data from twentyTen looks very different from twentyTwenty when you apply the same analytical framework, mostly because of changes in enforcement priorities and charging statutes, not fundamental shifts in usage behavior. I usually recommend building timelines backward from the most recent reliable year rather than forward, because the methodology changes accumulate and make earlier comparisons increasingly unreliable.