Working Through ACLS When You Have Zero Time
The ACLS exam is more of a filter than a proper competency check. The questions move fast, the scenarios are designed to make you second-guess your first instinct, and the rhythm strips matter more than anything else. Most people walk out of the course feeling like they understood everything until they see the actual questions on screen. That is exactly where a structured review document matters. The American Heart Association Acls Study Guide covers the algorithm flow, the medication dosing tables, and the case scenarios you will actually see tested. It does not replace the hands-on station work, but it gives you a reference that maps directly onto the exam format.
Getting Started With the American Heart Association Acls Study Guide
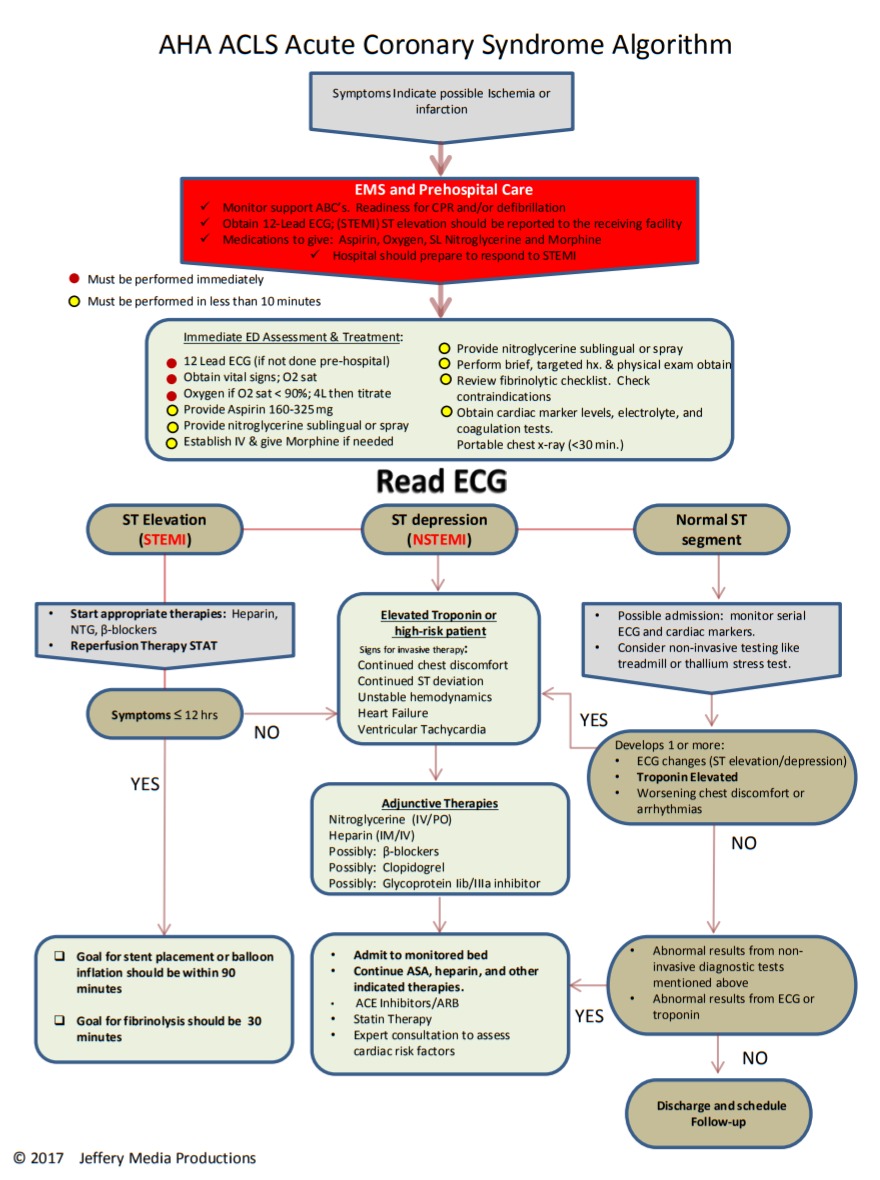
I got my copy through the AHA website when I was prepping for a hospital job requirement last year. The material is organized around the major algorithms: cardiac arrest, bradycardia, tachycardia, acute stroke, and respiratory emergencies. Each section includes the decision tree, the drug doses, and brief rationale for why one intervention beats another in a given scenario. The download is free once you have an AHA account. You need to register with your name, email, and a working address. The portal sends you a confirmation link, and after that you can access the study materials. It is not a shortcut past the course itself, but it is useful for people who already sat through the lecture and now need to lock in the details before the test. I found the PDF version the most practical because it loads fast on a tablet without requiring a browser window. You can search for "amiodarone dose" or "supraventricular tachycardia algorithm" in seconds. That is faster than flipping through chapters during review.
What the Guide Actually Covers
The content maps directly to the AHA's ACLS provider manual. You will find the adult and pediatric algorithms side by side, which helps when the exam throws a mixed-age scenario at you. The medication section lists dosages for epinephrine, amiodarone, atropine, adenosine, magnesium, and the antiarrhythmics used in stable versus unstable tachycardia. There is also a dedicated asthma and anaphylaxis module that shows up on the exam more often than people expect. One thing beginners consistently miss is that the exam tests your ability to recognize unstable signs, not just recite drug doses. A patient with tachycardia and hypotension gets a different pathway than one with the same heart rate and a stable blood pressure. The study guide lays this out clearly, but you have to read the algorithm trees carefully instead of memorizing drug lists in isolation. I ran into a specific problem during my own prep. The atrial fibrillation with rapid ventricular response scenario had a twist that the standard algorithms do not cover directly: the patient was hypotensive and also had Wolff-Parkinson-White syndrome. The guide points you toward cardioversion for unstable afib, but the WPW component changes the medication choices significantly. Synchronized cardioversion is still the right move here, but if you were tempted to use adenosine or certain rate-control drugs first, you would pick the wrong answer. I worked around it by cross-referencing the tachycardia algorithm with the special populations notes in the back of the manual, and then flagged that scenario for extra review. The guide does not call this out explicitly, so you have to connect the dots yourself.
Get the Full Details

How I Actually Used It Before the Exam
I spent about six hours total over two days going through the material. The first pass was reading the algorithms cold, without looking at answers. I marked every section where I hesitated or had to re-read a decision point. That usually pointed to a gap in understanding rather than simple forgetfulness. The second pass focused on the practice questions embedded in the guide. I timed myself at roughly forty-five seconds per question, which mirrors the pacing of the actual exam. If I took longer than a minute on a single question, I flagged it and came back later. This revealed that I was overthinking stable cases instead of applying the algorithm mechanically, which is exactly what the test rewards. For the medication dosing, I did not try to memorize every decimal. Instead, I grouped drugs by their clinical category: antiarrhythmics, vasopressors, bronchodilators, and anticoagulants. Each group has a predictable pattern in dosing frequency and maximum dose limits. That cut my review time from about two hours down to roughly forty minutes per session, and it stuck better under exam pressure.
Pitfalls to Watch Out For
The biggest trap is assuming that all bradycardic patients get the same initial treatment. Symptomatic bradycardia with a perfusing rhythm starts with atropine, but if the patient is hypothermic or has certain overdose patterns, the algorithm shifts. The study guide mentions these exceptions, but they are easy to skim over because they appear as small callout boxes rather than main headings. Another issue is the tension pneumothorax scenario. The exam frequently includes needle decompression as an answer choice for a patient with respiratory distress and unilateral breath sounds. The guide covers this under respiratory arrest, but the connection between tension pneumothorax and the subsequent PEA algorithm is not always obvious on first read. I learned this the hard way after getting a question wrong during a practice run. The manual does have limitations. It assumes you have already completed the didactic portion of the ACLS course. If you are trying to self-study without any instructor guidance, the algorithms can feel abstract and you will miss context that explains why one drug is preferred over another. In that case, supplementing the guide with video walkthroughs of each scenario makes a real difference. The AHA's own online modules pair well with the study guide because they show the clinical decision-making process in motion rather than just presenting static flowcharts.
Final Thoughts on Using This Resource
The study guide works best as a targeted review tool, not a substitute for the full course. It condenses the essential algorithms and dosing information into a format that is easier to scan than the main manual. If you have already been through the training and just need to solidify the material before the written exam, it is worth the time. If you are starting from zero, pair it with the official course modules and practice at least one full case simulation before sitting for the test. Download the guide through the AHA portal, print the algorithm pages if you prefer hard copies, and focus your review on the areas where you hesitated. The exam rewards pattern recognition, and the more you expose yourself to the decision trees under timed conditions, the less you will second-guess yourself on test day.