
Running Through the AHA Guidelines Without Losing Your Mind
I have been doing BLS and ACLS training for years across a few different hospital systems. The American Heart Association Guidelines For Cardiopulmonary Resuscitation And Emergency Cardiovascular Care gets updated periodically, and the 2020 revisions are the current baseline most facilities still follow, with a few 2025 addenda popping up in specific areas like uterine displacement during resuscitation and improved defibrillation waveform guidance. Here is how to actually use them in practice rather than just pass a skills test. The guidelines are organized into chains of survival, algorithms for different arrest rhythms, and medication dosing tables. The core algorithm for adult cardiac arrest starts with identification and activation of emergency response, then immediate high-quality CPR beginning with chest compressions. That sequence has not changed in any meaningful way since 2010, but the details around what high quality actually means got sharpened up. Compression rate is between 100 and 120 per minute. Depth is at least two inches for adults, not more than two and four-tenths inches. Full chest recoil matters. Minimize interruptions to less than ten seconds between compressor switches. These are not suggestions. Real data shows that every second without compressions drops coronary perfusion pressure measurably, and returning to 50 percent of normal after a ten-second pause takes about thirty seconds to recover.
What Actually Happens When You Apply These Rules
I learned this the hard way during a code on a trauma patient who was in pulseless electrical activity. The monitor looked fine, rhythm was essentially regular, but there was no pulse. Someone immediately started talking about arrhythmia and shockable rhythms. I kept compressions going while we worked through the differential. The PEA algorithm is right there in the guidelines. It says identify and treat reversible causes. The five Hs and five Ts. We found a tension pneumothorax within eight minutes. If we had wasted that time debating defibrillation, the patient would have died from something mechanically fixable. That is the thing nobody tells you during training. The algorithms are useful, but they are decision trees, not scripts. The real skill is knowing when to follow the algorithm and when to step back and think about what else could be going on. I have seen people miss a massive pulmonary embolism because they were too busy cycling through the ACLS drug protocol.
Key Changes and Nuances That Matter
One area where the guidelines get messy is targeted temperature management. Post-cardiac arrest care now emphasizes maintaining normothermia or treating fever aggressively rather than the older approach of deliberate therapeutic hypothermia. The 2020 guidelines shifted that direction based on stronger evidence. If you are training people on this, make sure they understand the new framing. It is not about cooling everyone to thirty-three degrees anymore. It is about preventing fever and maintaining stable temperatures. Another practical detail is the emphasis on real-time feedback devices during CPR. Many systems now have pads or vests that give auditory and visual prompts for rate and depth. These are helpful but not foolproof. I had an incident where a feedback device kept signaling adequate depth, but the patient was obese and the anatomical landmarks were difficult to find. The device was measuring compression depth at the sternum, not assessing whether adequate perfusion was actually occurring. We had to rely on capnography instead. End-tidal CO2 above twenty-five mmHg during CPR is a reasonable marker of adequate compressions. Below that, you are probably not doing enough or the patient has a poor prognosis regardless.
Get the Full Details
Dosing and Drug Administration Under the Guidelines
Epinephrine one milligram every three to five minutes remains standard for shockable and non-shockable rhythms. Amiodarone five hundred milligrams IV push after the third shock for persistent ventricular fibrillation or pulseless ventricular tachycardia. Lidocaine as an alternative if amiodarone is not available. The guidelines note that vasopressin is no longer recommended as a substitute for epinephrine. That changed a while back and some older training materials still reference it. For bradycardia with a pulse, atropine one milligram IV is first line, though the guidelines acknowledge it may not work in transplant patients or those with heart block. If atropine fails, transcutaneous pacing or dopamine and epinephrine infusions are options. The dopamine dose range is five to twenty micrograms per kilogram per minute. Epinephrine infusion runs from zero point zeroFive to zero pointFive micrograms per kilogram per minute. These are not numbers to guess about. I have seen wrong decimal placements cause real problems in the field.
Where the Guidelines Fall Short
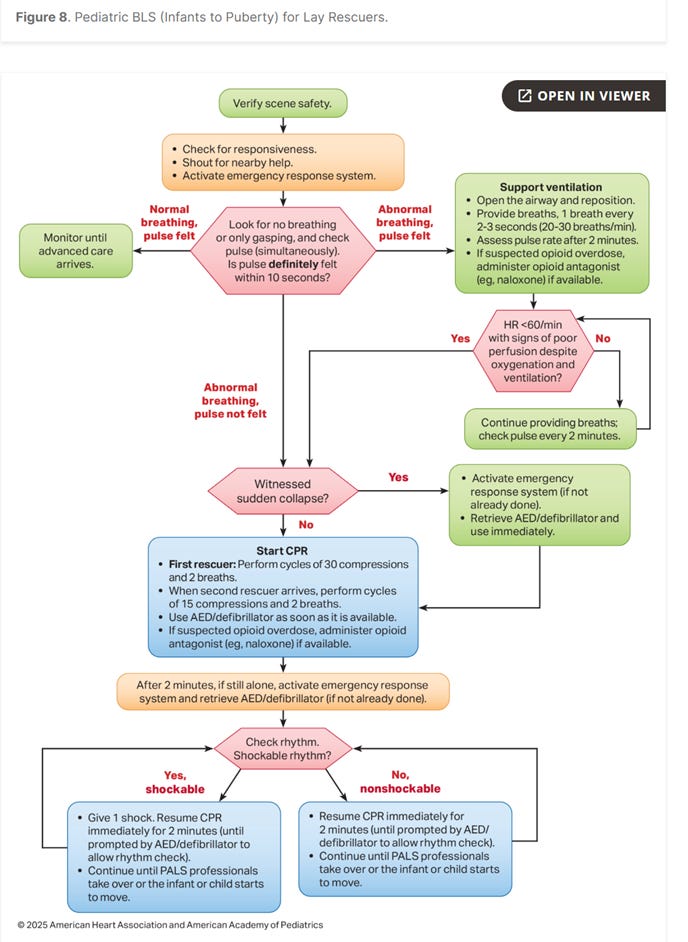
The AHA guidelines are comprehensive but they have blind spots. Resource-limited settings are one. The algorithms assume you have defibrillation capability, advanced airway equipment, and IV access. Rural clinics andambulance services in some areas do not have all of that. The guidelines do not give you much practical help for those situations beyond saying do what you can and get rapid transport if possible. Another gap is pediatric considerations. The adult and pediatric algorithms diverge significantly, but the guidelines assume a certain level of training and equipment that many first responders do not carry. Pediatric dosing is weight-based and error rates are higher. If you are working in an environment where children present frequently, supplement the AHA guidelines with local pediatric protocols and practice weight-based estimation tools like the Broselow tape.
How to Access and Stay Current
The full guidelines are available through the American Heart Association website. The basic lifecycle version is free to read, though the detailed scientific statements and supplementary materials may require a subscription or institutional access. Most hospitals keep digital copies in their clinical databases. If you are studying for certification, the AHA provides downloadable algorithm cards and a companion handbook that many people find more practical than the full guideline document. Expect updates. The AHA typically reviews and revises guidelines every five years based on the most current evidence. The next major update cycle should land around 2025, and early drafts have already surfaced on their website. Keep an eye on the changes around resuscitation in special circumstances like pregnancy, anaphylaxis, and opioid overdose. Those areas are getting more attention and the recommendations are shifting. The bottom line is that the guidelines are a framework, not a replacement for clinical judgment. They will not save you if you cannot recognize when a patient does not fit the standard algorithms. But they will give you a solid structure to fall back on when everything else is falling apart. That is what they were built for, and they do that job well enough.



