So You Want to Actually Use Analysis Models in Social Work
What the Analysis Model Social Work Framework Is and Why Most People Get It Wrong
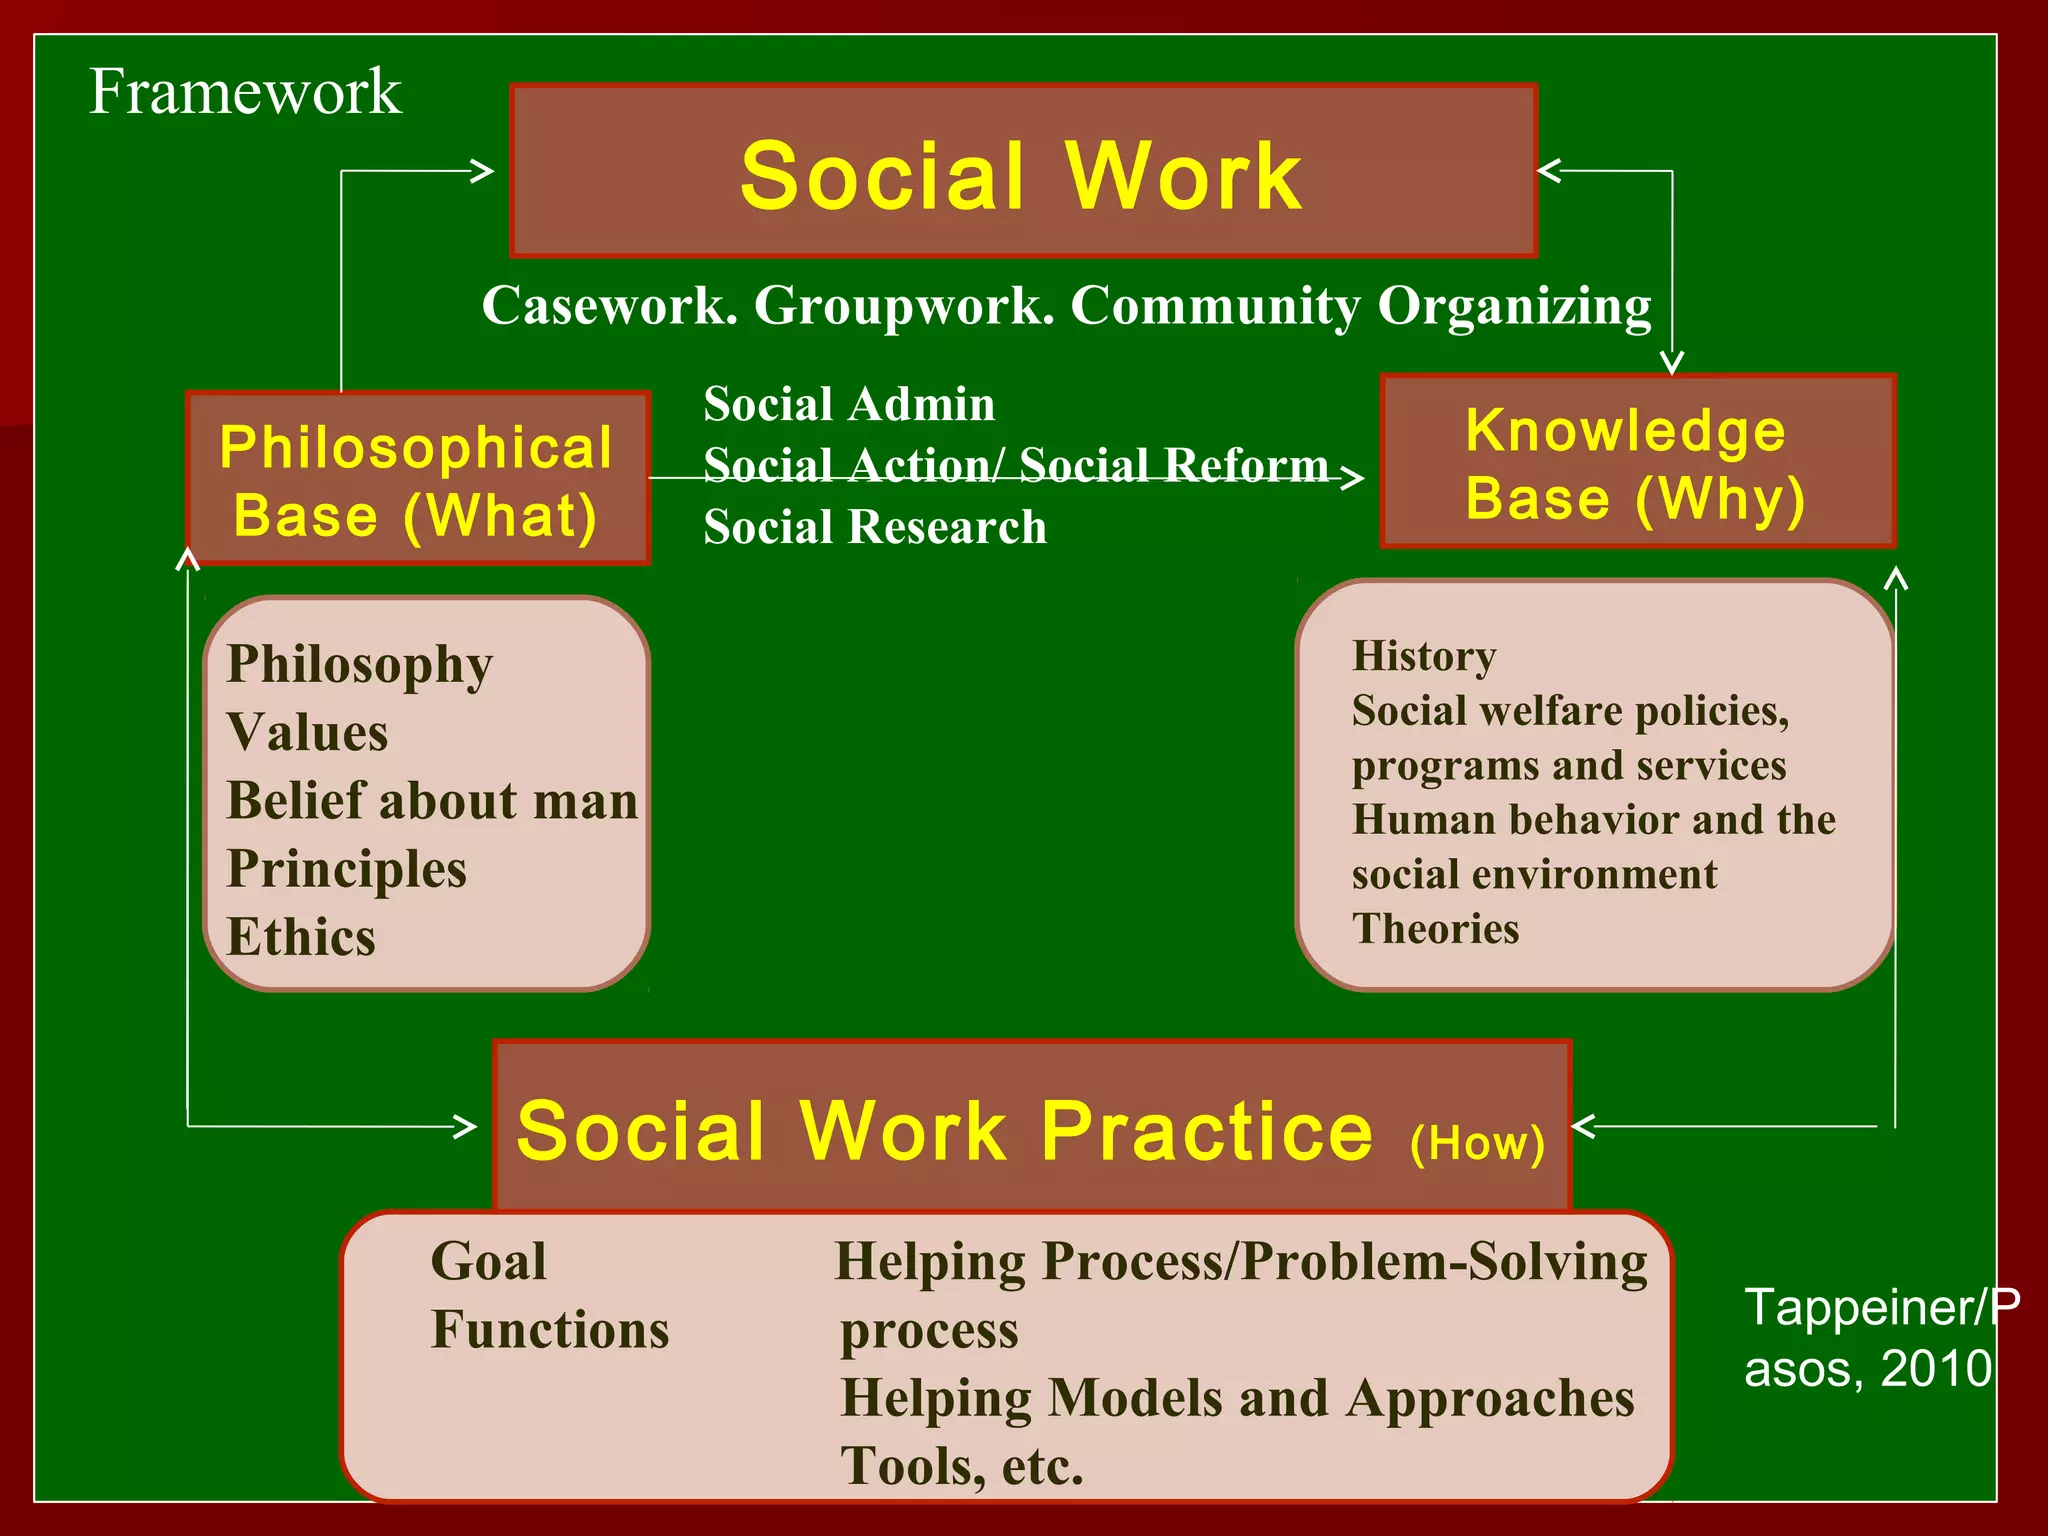
Analysis Model Social Work isn't a single rigid tool. It's a family of structured ways to break down a client's situation into manageable pieces so you can actually see what's going on before you decide what to do. The most common versions you'll encounter are ecological models, biopsychosocial assessments, and strengths-based analytical frameworks. Each one gives you a different lens on the same messy human problem. Here's the part nobody tells you in your training: the model doesn't work if you force it onto the case. I learned that the hard way about four years into my career. We had a young mother, late twenties, referred through child protective services. She was juggling a new diagnosis of bipolar disorder, a crumbling housing situation, and a 14-year-old who had stopped attending school. My first instinct was to run her through a standard ecological assessment, mapping micro, mezzo, and macro systems. It took me two hours to fill out the template. And when I handed it to my supervisor, she pointed at the page and said, "You know what's actually happening here, or did you just color in all the boxes?" She was right. I had filled every section perfectly. The micro system showed a strained relationship with the mother's partner. The mezzo system documented the school and the pediatrician. The macro system listed available housing vouchers and mental health subsidies. The model had captured data, yes, but it had missed the actual problem. The kid wasn't out of school because of systemic factors. He was out of school because he'd been bullied and the mother, fresh out of a psychiatric hospitalization, hadn't known how to respond. The model had given me a map of the territory but not a sense of direction. I ended up throwing away the whole framework, sitting down with the actual case files, and building an analysis from the ground up based on what the family was telling me. That process took me forty minutes instead of two hours, and the resulting intervention plan was sharper than anything the ecological model would have produced.
This is the fundamental tension in any Analysis Model Social Work approach. The framework gives you structure, which is useful when you're drowning in information. But structure without engagement with the actual human being in front of you just produces more paperwork and less understanding.
How I Actually Do the Analysis
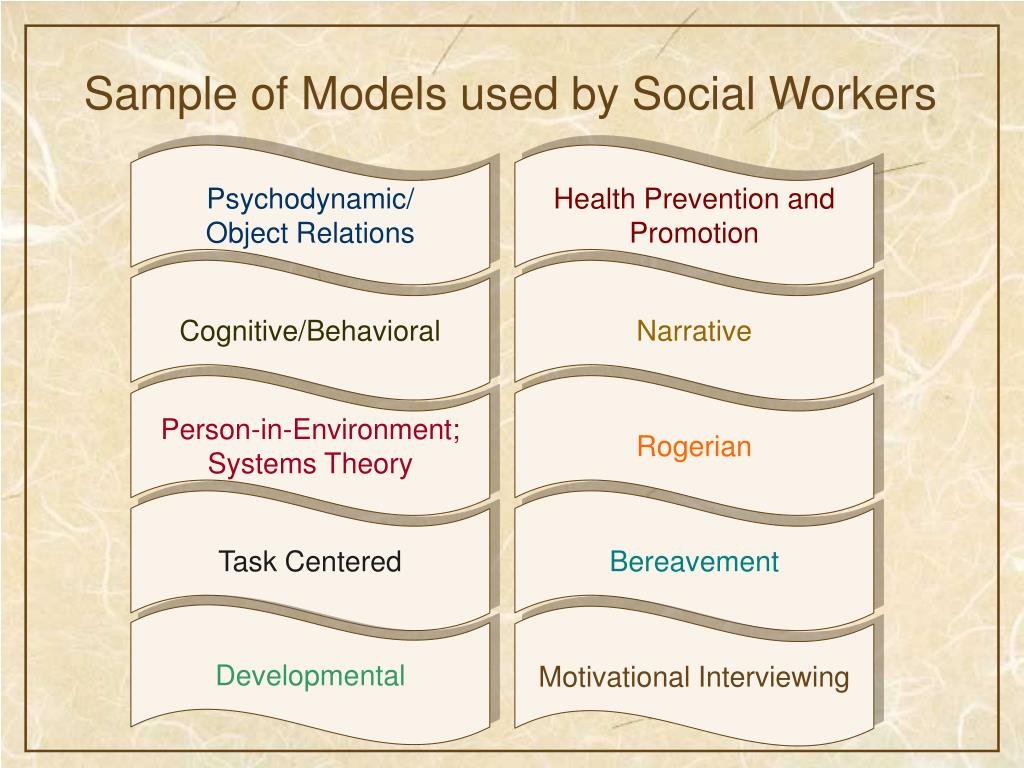
I don't start with a template. I start by reading the referral, then I read the previous case notes if they exist, and then I sit with whatever information I have before I decide which model to apply. Sometimes I'll use a biopsychosocial structure because I need to document medical history alongside social functioning for a court report. Sometimes I'll lean toward a strengths-based model when I'm working with a family that's already been through enough diagnostic labeling to last three lifetimes. The choice of model is tactical, not doctrinal. When I do apply an Analysis Model Social Work framework, I work through it in this order, which I know is unconventional but it saves time and reduces the chance of missing something important: First, I identify the presenting problem in plain language. Not the clinical language from the referral form, but what the person or family would say is wrong. This grounds the entire analysis in reality rather than in administrative categorization.
Get the Full Details

Second, I map the timeline. When did things start changing? What were the conditions before the change? This temporal dimension is something most templates completely omit, and it's usually where the real insight lives. A family presenting with behavioral issues in a teenager, for instance, often shows a dramatically different picture if you trace it back to a parental separation that happened eighteen months ago versus one that happened three weeks ago. Third, I apply the analytical lens. This is where the model comes in. If I'm using a biopsychosocial framework, I'll look at medical history, psychological factors, and social environment simultaneously rather than sequentially. The point isn't to fill in sections. It's to notice connections between them. In my experience, about sixty percent of the meaningful patterns in a case show up at the intersection of two domains, not within any single one. A client's medication non-compliance might be better understood through the lens of housing instability than through any psychiatric diagnosis. That intersection is where the analysis actually produces value. Fourth, I check for counter-evidence. This is the step most people skip. For every pattern I identify, I actively look for data that contradicts it. It's easy to fall into confirmation bias once you've committed to an initial formulation. I make it a habit to write down at least one piece of evidence that doesn't fit my working hypothesis, because that's usually where the most important revision happens.
Fifth, I synthesize into an actionable assessment. This should take one page maximum. Everything after that is either detail for the file or material for a specific audience like a court or a multidisciplinary team meeting.
Common Pitfalls That Slow You Down
The biggest mistake I see people make, including myself early on, is treating the model as the end product instead of a thinking tool. You finish the assessment and feel like you're done. You're not done. The assessment is a hypothesis that needs testing through your interaction with the client. I've had cases where the written analysis was comprehensive and technically correct, and the actual intervention completely missed the mark because I hadn't tested my assumptions against what the client actually experienced day to day. Another pitfall is over-reliance on standardized instruments. There are hundreds of validated scales out there, and it's tempting to just administer them and call it assessment. A depression inventory score tells you how depressed someone reports feeling. It does not tell you whether the depression is driving the presenting problem or is itself a symptom of something else. I had a case where a client scored in the severe range on multiple mental health screens, and the full Analysis Model Social Work process revealed that the symptoms were primarily trauma responses to an unsafe living situation, not a primary mood disorder. The distinction mattered enormously for the intervention plan. Screening tools are screening tools. They flag, they don't diagnose in context. The third common issue is analysis paralysis. You collect enough information to write a textbook chapter and still can't decide what to do. This happens most often with complex cases involving multiple systems and multiple problems. The solution isn't to collect more data. It's to set a deadline for the analysis phase and commit to an intervention based on whatever you have. You can always adjust later. In practice, I find that completing a preliminary assessment in about two hours with a clear focus on the primary problem and working hypothesis is far more effective than spending eight hours trying to account for everything.
When the Model Breaks Down
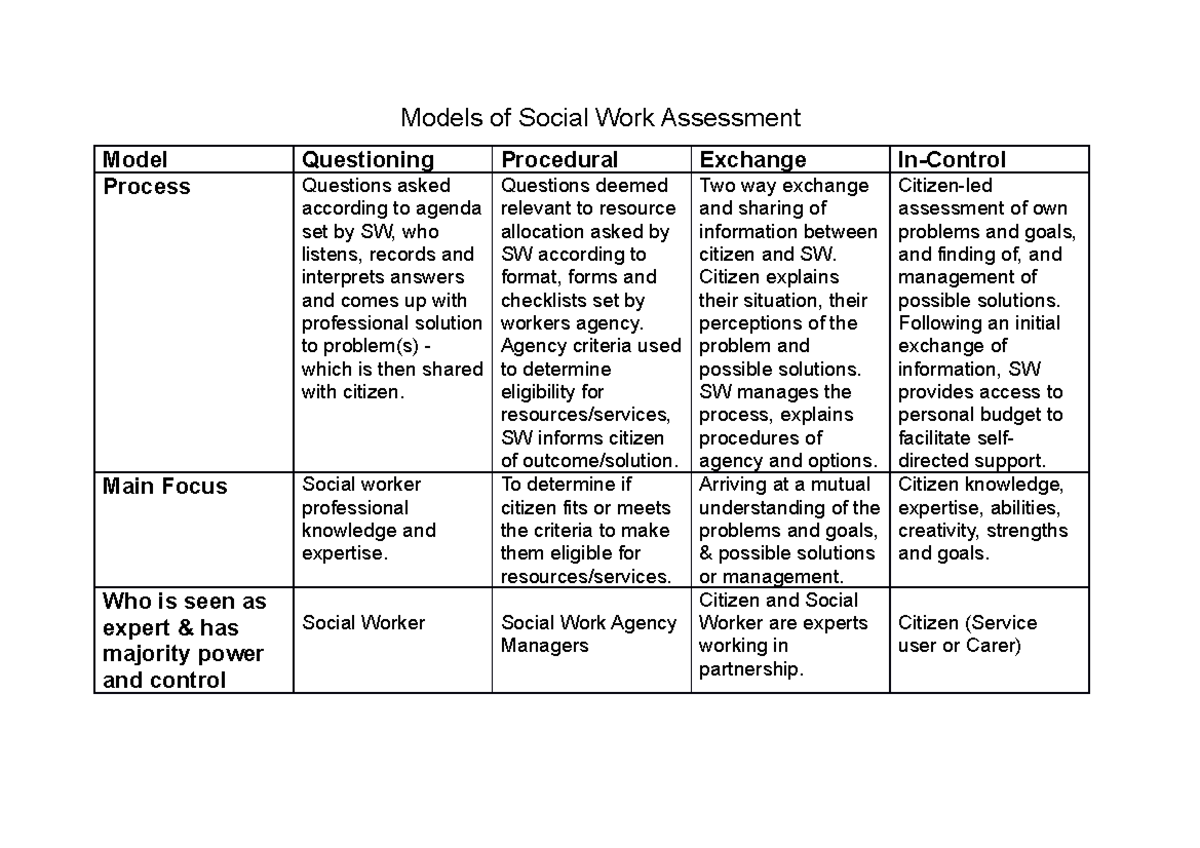
No Analysis Model Social Work framework handles everything well. Crisis situations move too fast for thorough templated analysis. I've had times when a client walked in during an acute episode and the priority was safety and de-escalation, not filling out assessment domains. In those cases, I do a rapid situational assessment, address the immediate need, and come back to the formal analysis once things have stabilized. The framework is there when you have the bandwidth to use it properly, not as a performance metric you hit regardless of circumstances. Cultural mismatch is another area where standard models struggle. Many of the commonly used frameworks are built on individualistic Western assumptions about family, self-determination, and help-seeking behavior. A client from a collectivist cultural background might not fit neatly into categories designed for an individual-focused worldview. I've found that in these situations, adapting the model to include cultural and community context as a central analytical category rather than a peripheral checkbox makes a significant difference. This sometimes means spending more time upfront understanding the client's cultural framework before applying any structured analysis. There's also the bureaucratic pressure to use whatever model your agency has built into its electronic documentation system. I've worked in places where the assessment template was so rigid that trying to use a different analytical approach required jumping through hoops. The practical workaround is to use the template for compliance purposes while keeping your actual analytical thinking in a separate section or document. This takes discipline because it feels inefficient, but it's better than letting a poor-fitting template shape your clinical judgment.
A Practical Example From Recent Practice
Recently I worked with an elderly man in his early seventies who had been referred for assessment after a series of falls. The referral suggested possible cognitive decline, and I was prepared to run a standard geriatric analysis. But when I actually met him, he was sharp as a tack. The falls weren't neurological. They were mechanical. His apartment had loose rugs, poor lighting, and a bathroom setup that was dangerous for someone with a mild knee condition. The Analysis Model Social Work process in this case was almost entirely environmental and social, with the medical component being straightforward and quickly ruled out after a brief screening. A rigid model might have pulled me toward a lengthy cognitive and psychiatric evaluation. The actual analysis took about forty-five minutes because I recognized early that the presenting problem didn't match the assumed framework. I documented the environmental hazards, connected him with home modification services, and closed the case with a follow-up in six weeks. The intervention was simple and directly targeted the real problem. The model served the analysis, not the other way around. If you're looking to get better at this, the most useful resource I've found isn't a textbook or a certification program. It's reviewing your own assessments six months later and seeing which ones led to effective interventions and which ones didn't. The pattern recognition you develop from that feedback loop is more valuable than any model you memorize. The frameworks are starting points, not destinations.